How Psychoanalytic Therapy Actually Works In Practice
The Basic Aim Of Psychoanalytic Therapy Is To
Make the unconscious conscious. That's the short version. Freud's original framework, then refined by decades of practitioners, comes down to bringing repressed material into awareness so patients can actually process it instead of acting it out unconsciously. The work happens through free association, dream analysis, and especially transference patterns that emerge in the therapy room. I spent years running these sessions before moving more toward integrative approaches. What people don't understand is that insight alone doesn't change behavior. You can have full intellectual awareness of why you do something self-destructive and still do it the next day. The therapeutic work is more about creating the conditions where new responses can develop, not just cataloging old ones. One edge case I ran into constantly involved patients with severe defense structures around specific traumas. Standard free association would hit a wall. The patient would start talking and then abruptly shift topics, or fall silent for twenty minutes, or get angry at nothing apparent. I learned to stop pushing interpretation at those moments. Instead, I'd note the rupture in the transference itself. What happened between us in that silence often mattered more than anything the patient said afterward. The resistance wasn't an obstacle to the work; it was the work showing up in real time.
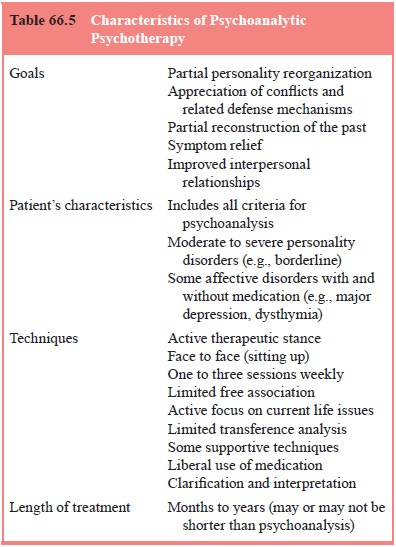
Free association sounds simple but most beginners handle it poorly. They ask patients to just "say whatever comes to mind" and then sit there waiting. It rarely works that way. People feel stupid saying random thoughts. A better approach is to have them focus on bodily sensations first, then trace where those sensations lead. The body usually notices what the mind is avoiding. Transference is where things get complicated. Patients will project feelings onto you from past relationships. A woman might treat you like her critical father. A man might respond to you as if you're his absent mother. This isn't manipulation. It's genuine and automatic. The goal is to notice these patterns, name them carefully, and let the patient experience them differently within the therapeutic relationship. There's a common misconception that psychoanalytic therapy means three or four sessions per week for years. That was the classical model. Modern psychodynamic therapy often runs once weekly and can produce meaningful change in six months to two years depending on the presentation. The depth work is similar, just compressed differently. Don't let outdated textbook descriptions scare you away from the approach.
The main failure mode I see is therapists who interpret too aggressively. A patient will be sitting there visibly distressed and the therapist offers a sharp unconscious meaning. The patient doesn't feel understood. They feel analyzed. The alliance fractures. Better to stay with the affect first, help the patient tolerate it, and only then introduce interpretive work. Timing everything is the actual skill here. Another thing textbooks underplay: countertransference. You will have strong reactions to patients. Sometimes they're useful data. Sometimes they're your own stuff. Learning to tell the difference takes years and honestly probably requires your own therapy. I've had patients trigger my own unprocessed family dynamics and I wish I'd recognized it sooner. The therapy stalled for months because I was responding to ghost material instead of the actual person in front of me. If someone has active psychosis, severe borderline personality with chronic suicidality, or acute substance dependence, classical psychoanalytic work isn't appropriate as a first intervention. Those cases need stabilization, containment, and often pharmacological support before any deep unconscious work becomes viable. The approach has real limits. It's not a universal fix.
Get the Full Details

The evidence base for psychodynamic therapy has improved significantly over the past decade. Meta-analyses now show effect sizes comparable to CBT for depression and anxiety disorders, with gains that tend to hold or improve after treatment ends. That's the so-called sleeper effect. People keep getting better after therapy stops, which makes some sense if the work actually changed how they relate to themselves rather than just teaching coping strategies. For anyone studying this, I'd recommend reading Hannah Segal's work on symbolism alongside contemporary relational psychoanalysis. The classical Freud material is necessary foundation but it won't prepare you for how actual modern practice looks. The field has moved substantially away from the blank screen model most people imagine when they hear "psychoanalysis."