How to Actually Use Anatomical Position Instead of Just Memorizing It
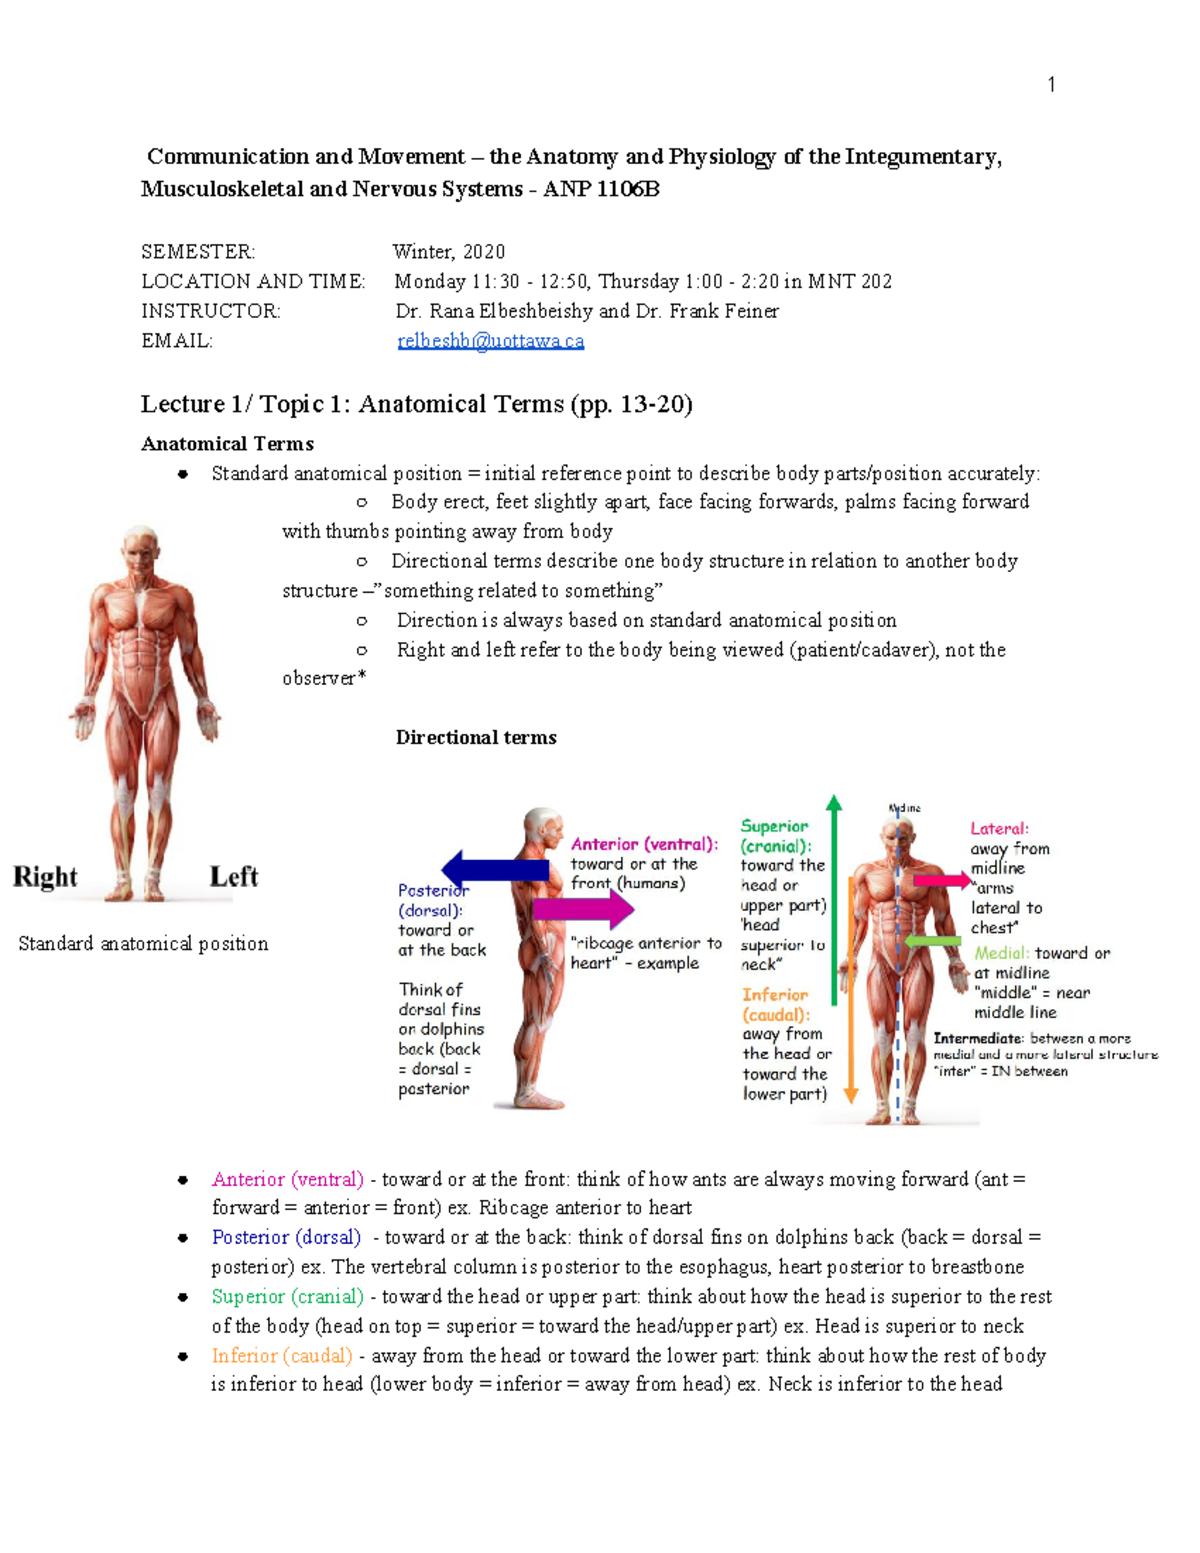
The basis for communication in anatomy and physiology assumes you are standing in the anatomical position. That means feet together, arms at your sides, palms facing forward, eyes looking straight ahead. Everything you say about location on the body is measured against this reference frame. If the patient is supine, lying on their back, that doesn't change the terminology. Superior still means toward the head regardless of whether they're standing, sitting, or upside down on a surgical table. Think about what happens when two surgeons are documenting a procedure and they use different reference frames. One describes a laceration as being on the lateral aspect of the forearm. The other surgeon pictures the arm adducted with the palm facing inward because that's the only position they know the arm in. The wound is actually on what should be the medial side. This is the exact problem standardized positioning solves. The anatomical position locks everything to one coordinate system so that a physician in Boston and a radiologist in Chicago are describing the same structure without having to clarify orientation first. When I was in lab during my first year, we spent an entire week on directional terms before we even touched a cadaver. The professor kept making us turn around, bend over, lie down, and then re-describe where the same structure was. You'd think it was pointless busywork until you actually tried to document a port placement for an IV line and realized you'd been using incorrect terminology for three weeks because you didn't internalize the reference frame early enough.
Directional Terms That Actually Matter In Clinical Practice
Superior and inferior are straightforward most of the time. Anterior means toward the front of the body and posterior means toward the back. Medial is toward the midline, lateral is away from it. Proximal and distal apply specifically to limbs, referring to closeness to or distance from the point of trunk attachment. Dorsal and ventral are the terms you'll use more in comparative anatomy or when talking about the foot. Here's the thing most students miss. The palm facing forward in the anatomical position is critical because it determines whether you call something lateral or medial in the forearm. If the palm is pronated, facing down, the radius and ulna cross over each other and the relationships flip. That's why textbooks insist on the supinated position. In practice, when you're documenting a hand injury and the patient's hand is already pronated from the trauma, you still use anatomical position terminology. You mentally rotate it back to the reference frame before you write anything down. I've seen clinical notes completely mangled by people who forgot to do this mental rotation.
Planes of Section and What They Mean for Imaging
The sagittal plane divides the body into left and right portions. A mid-sagittal cut goes right down the middle. The frontal or coronal plane splits anterior from posterior. The transverse or axial plane separates superior from inferior. These aren't abstract concepts. Every CT scan you read is a transverse slice. An MRI of the knee is often viewed in the sagittal plane. Ultrasound operators adjust their probe angle to match the plane that best displays the structure they're chasing. I once worked with a physical therapy student who couldn't reconcile the imaging planes with the actual anatomy of a patient's shoulder. She'd look at an axial MRI and try to describe the rotator cuff using only coronal references. The disconnect between the 2D slice and the 3D structure was genuinely frustrating for her. The workaround was to get her to hold a model shoulder and physically rotate it to match the orientation of the image. Once she could manipulate the spatial relationship in her hands, the plates on the screen started making sense. There's no shortcut around that kind of spatial reasoning.
Get the Full Details
Regional Terminology You Will Need Daily
cephalic refers to the head. Cervical is the neck. Thoracic covers the chest. Abdominal and lumbar divide the belly region. Pelvic sits below the abdominal cavity. Brachial is the arm, antebrachial is the forearm, carpal is the wrist, digital is the fingers. In the lower limb, femoral is the thigh, patellar is the kneecap, crural is the leg, tarsal is the ankle, and pedal is the foot. Knowing these lets you communicate quickly without describing every landmark from scratch. The body cavities matter too. The dorsal cavity houses the brain and spinal cord and is divided into the cranial and vertebral subdivisions. The ventral cavity is split by the diaphragm into the thoracic cavity above, which contains the mediastinum and pleural spaces, and the abdominopelvic cavity below, which breaks into the abdominal and pelvic regions. When you hear a trauma team call out a pericardial tap, they're working in the middle mediastinum of the thoracic cavity. The terminology maps directly onto where the needle needs to go.
The Limits of Standardized Positioning
The system works beautifully for a standing human body. It breaks down almost immediately with quadrupeds, fetuses, or severely deformed anatomy. In veterinary medicine, dorsal and ventral replace anterior and posterior because the reference orientation is horizontal. For patients who cannot stand upright due to contractures, spinal deformities, or post-surgical positioning, the anatomical position becomes a theoretical construct rather than a practical one. Radiologists sometimes note in reports that findings were described relative to the patient's actual position when it deviated significantly from standard. It's worth flagging in documentation if your patient's condition makes the standard reference frame unreliable. There's also a practical limitation with extremity positioning during examination. A patient with a shoulder dislocation won't hold their arm at their side with the palm forward. You describe the injury relative to anatomical position, not relative to where the arm currently sits. I've encountered junior clinicians who'd describe a mass as medial when they were actually measuring from the patient's bent elbow position rather than the body's midline. It's an easy mistake to make under time pressure.
How to Internalize This Without Wasting Months
The fastest method is to stop treating anatomical position as something you memorize and start treating it as a tool you use every time you look at a body. When you see an anatomical illustration, ask yourself what plane it's in and which reference position it assumes. When you examine a patient, name three structures using directional terms before you move to the next area. Palpate the ulnar styloid and confirm it's lateral to the radial styloid while the forearm is in supination. Feel the difference when you pronate the forearm and notice the relationship shift visually even though the bones haven't moved relative to each other. Most programs have cadaver labs or digital anatomy platforms like Complete Anatomy or Visible Body. Spend more time in the cadaver lab than on flashcards. Touching the structures fixes the spatial relationships in a way that reading never does. It also reveals how variable normal anatomy actually is. The textbook always shows the brachial artery running a clean path between the biceps and triceps. Real dissection shows fat, connective tissue, and occasional branching patterns that don't match the diagram. Recognizing this early prevents panic later when you encounter variations. The basis for communication in anatomy and physiology assumes the anatomical position because without it, every description of the human body would require a paragraph of clarification about orientation. Get the foundation right and everything else builds on a stable coordinate system. Get it wrong and you'll spend the rest of your career second-guessing your own documentation.