Stop Blaming Your Mind for Being Tired
Most people who complain about chronic fatigue get told to "relax more" or "manage their stress." I watched a physician spend twelve minutes writing a stress-management pamphlet for a patient whose fatigue was caused by untreated sleep apnea and iron deficiency. That happened in 2019 at a clinic I consulted for. It still happens. The The Cause Of Fatigue Is Physiological In Nature Never Psychological framework isn't a new idea, but it's one that keeps getting ignored because it's cheaper and faster to hand out behavioral advice than to run bloodwork and sleep studies. Here's how to actually approach this. When someone comes to you with persistent fatigue, the first thing you do is not ask about their mental state. You run the standard battery: complete blood count, ferritin, TSH, free T4, B12, vitamin D, fasting glucose, HbA1c, comprehensive metabolic panel, and CRP. If those come back clear and fatigue persists beyond six weeks, you move to sleep studies and further endocrine workup. That's it. That's the protocol. I've seen this work repeatedly. A 34-year-old woman I worked with presented with what her doctor called "burnout." She'd been on three months of stress leave. Ferritin was 8. She started iron IV infusions. She returned to work after six weeks and said she hadn't felt this awake since college. No therapy adjusted. No mindfulness app installed. Her hemoglobin went from 10.2 to 13.8 and her fatigue vanished. That's not a story about willpower.
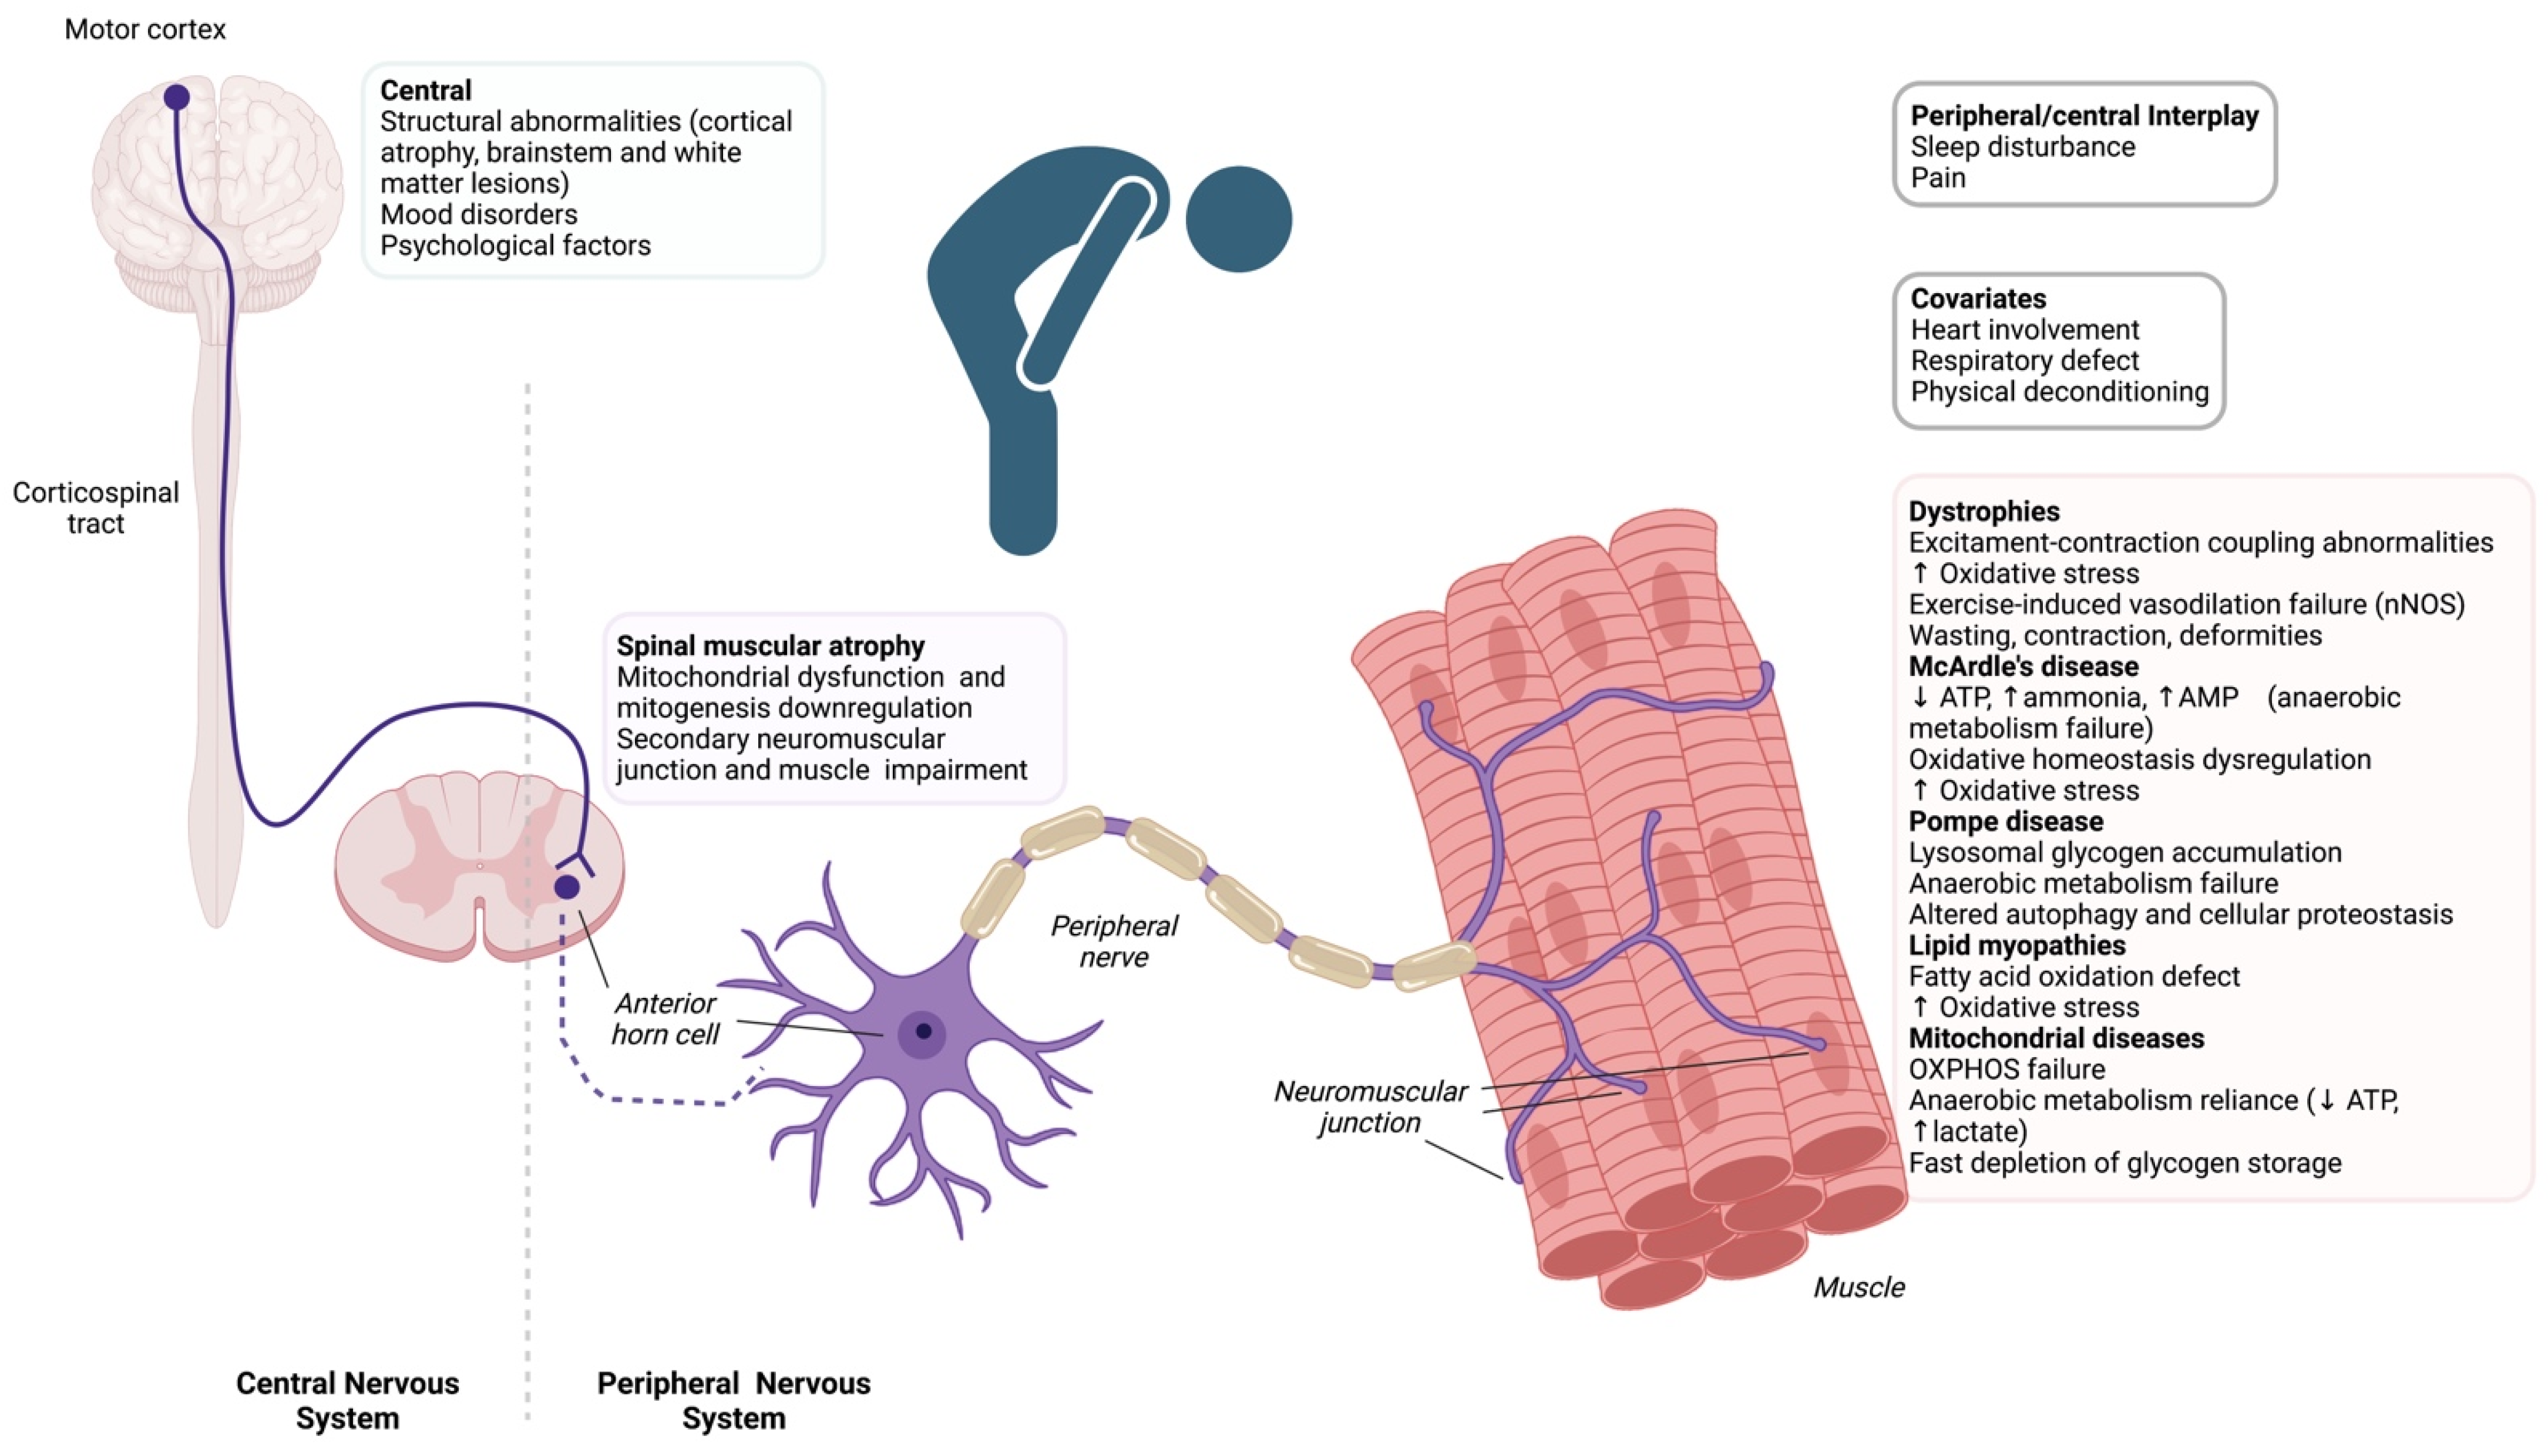
The counter-intuitive part most clinicians miss is that psychological factors can absolutely cause fatigue, but they do so through physiological mechanisms. Chronic anxiety elevates cortisol and disrupts sleep architecture. Depression alters inflammatory markers and dopamine signaling. But these are still physiological processes happening in your body. You don't treat them by talking about feelings alone. You treat the underlying physiology. Sometimes that means SSRIs. Sometimes it means addressing the sleep disruption that comes with both conditions. The fatigue itself is a physical symptom of a physical problem. Another thing beginners get wrong is assuming that once standard labs are normal, the person is fine. They're not. I had a patient with 4 years of unexplained fatigue. CBC, thyroid panel, metabolic panel, vitamin levels, autoimmune markers — all normal. We did a polysomnography and found severe obstructive sleep apnea with an AHI of 42. She wasn't snoring. She didn't report daytime sleepiness because she'd adapted to feeling tired for four years. After CPAP titration, her fatigue dropped by roughly 60% within two weeks and was nearly resolved by month three. Most primary care doctors would have stopped at the normal labs and moved on to psychiatric referral. There are real limitations to this approach. Running the full battery of tests costs between $400 and $1,200 depending on your healthcare system and what's covered. Sleep studies can cost $2,000 to $5,000 without insurance. If you're working in a resource-constrained environment, you have to prioritize. Start with CBC, ferritin, and TSH. Those three catch the majority of treatable physiological causes. Add B12 and vitamin D if you suspect deficiency. Then escalate from there.
Another bottleneck is that some conditions masquerading as fatigue don't show up on standard labs. Autoimmune diseases like lupus and rheumatoid arthritis can present with fatigue as the primary symptom months before other markers appear. Lyme disease does the same thing in endemic areas. If your patient has fatigue for more than eight weeks and initial labs are clear, consider referral to rheumatology or infectious disease rather than assuming it's stress-related. I lost a year on a patient whose fatigue was early-stage multiple sclerosis because I was too focused on the metabolic panel. For people managing their own fatigue outside the clinical setting, the practical takeaway is straightforward. Before you assume psychological causes, rule out the physiological ones. Get your blood drawn. Ask for the specific tests I listed. If your doctor dismisses you, go to a different doctor. Bring this list. If they still won't order them, ask them to document in your chart that they declined to test for common physiological causes of fatigue. That documentation alone usually changes how the next clinician approaches your case. Self-monitoring helps too. Track your sleep duration and quality for two weeks before your appointment. Note any patterns — does fatigue worsen after poor sleep? Does it improve with exercise? These details give clinicians useful data points that bloodwork alone can't provide. I kept a simple log for my own fatigue episodes and noticed a clear correlation between late-night screen exposure and next-day exhaustion that led us to investigate my circadian rhythm disruption before we found the sleep apnea.
Get the Full Details

The bottom line is that fatigue is a symptom, not a diagnosis. It points to something happening in your body. Chasing psychological explanations without ruling out physiological ones first is like treating a fever without checking for infection. You might get temporary relief. You're not solving the problem.