Breaking Down How the Eye Actually Works
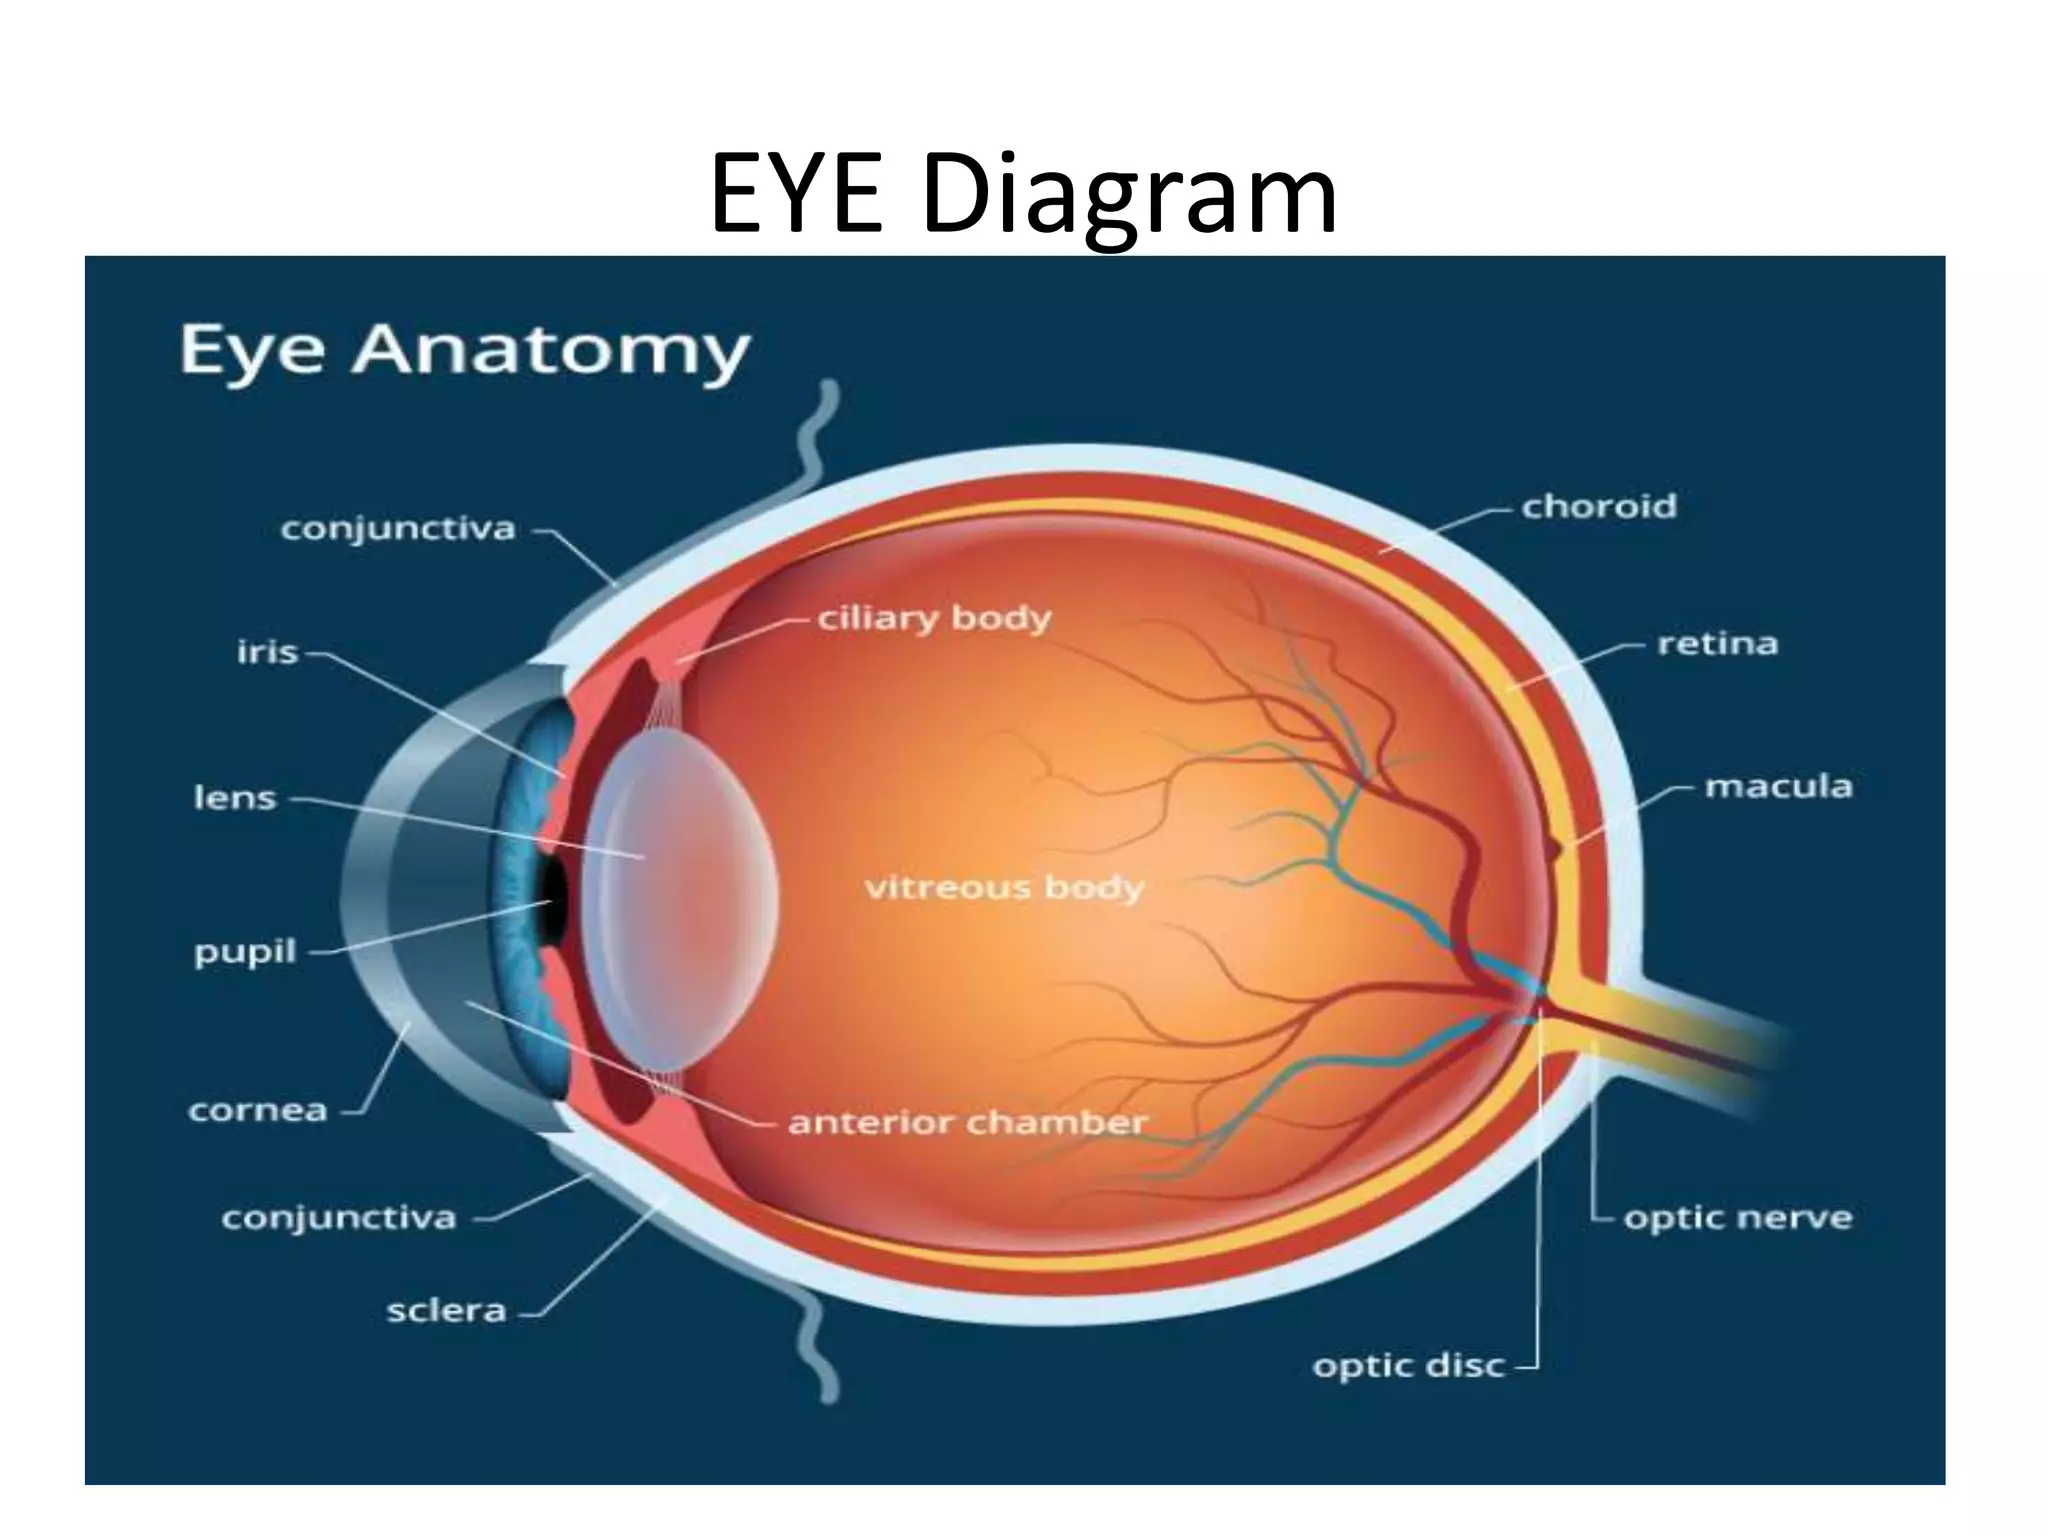
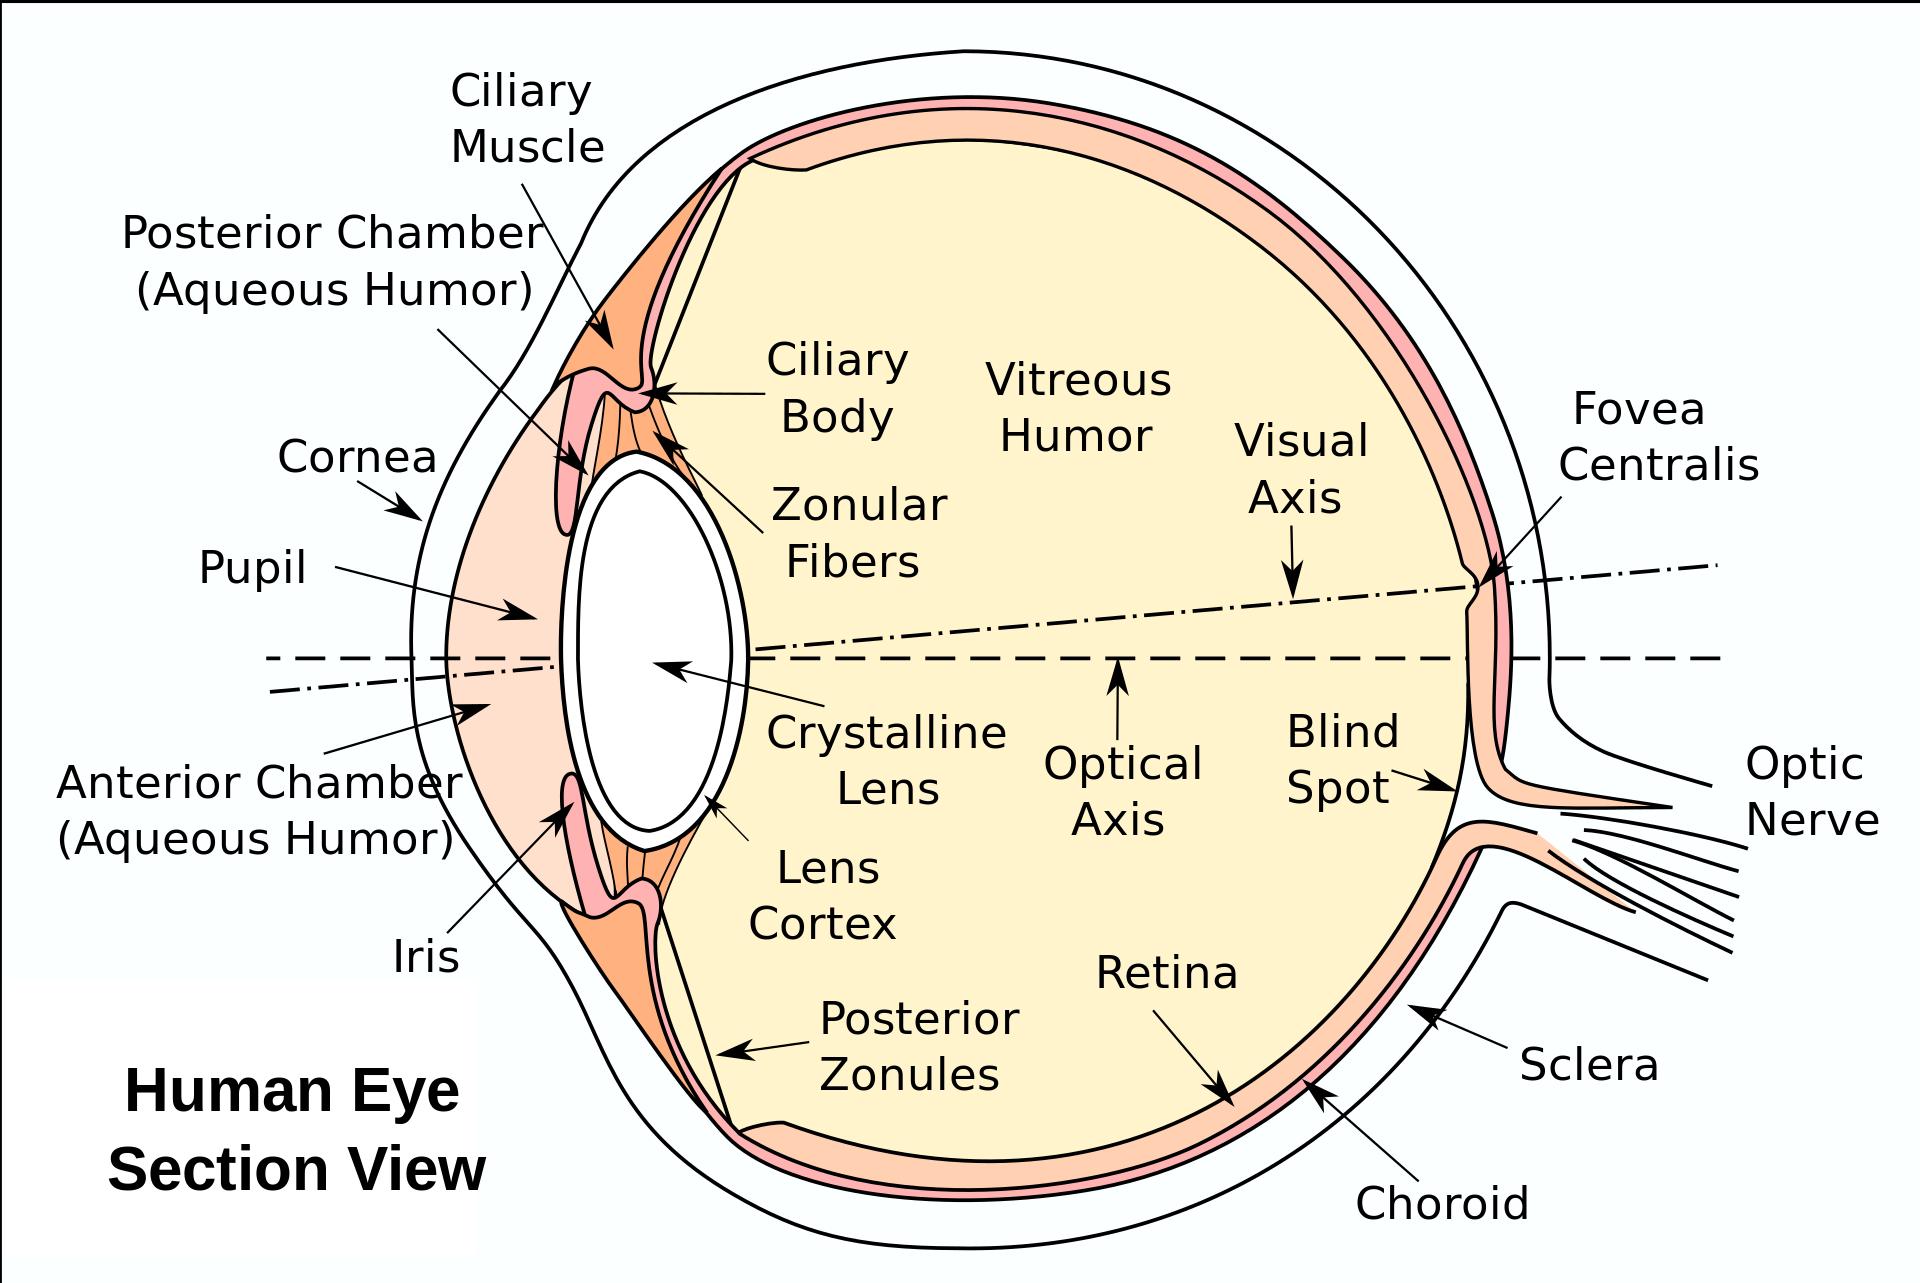
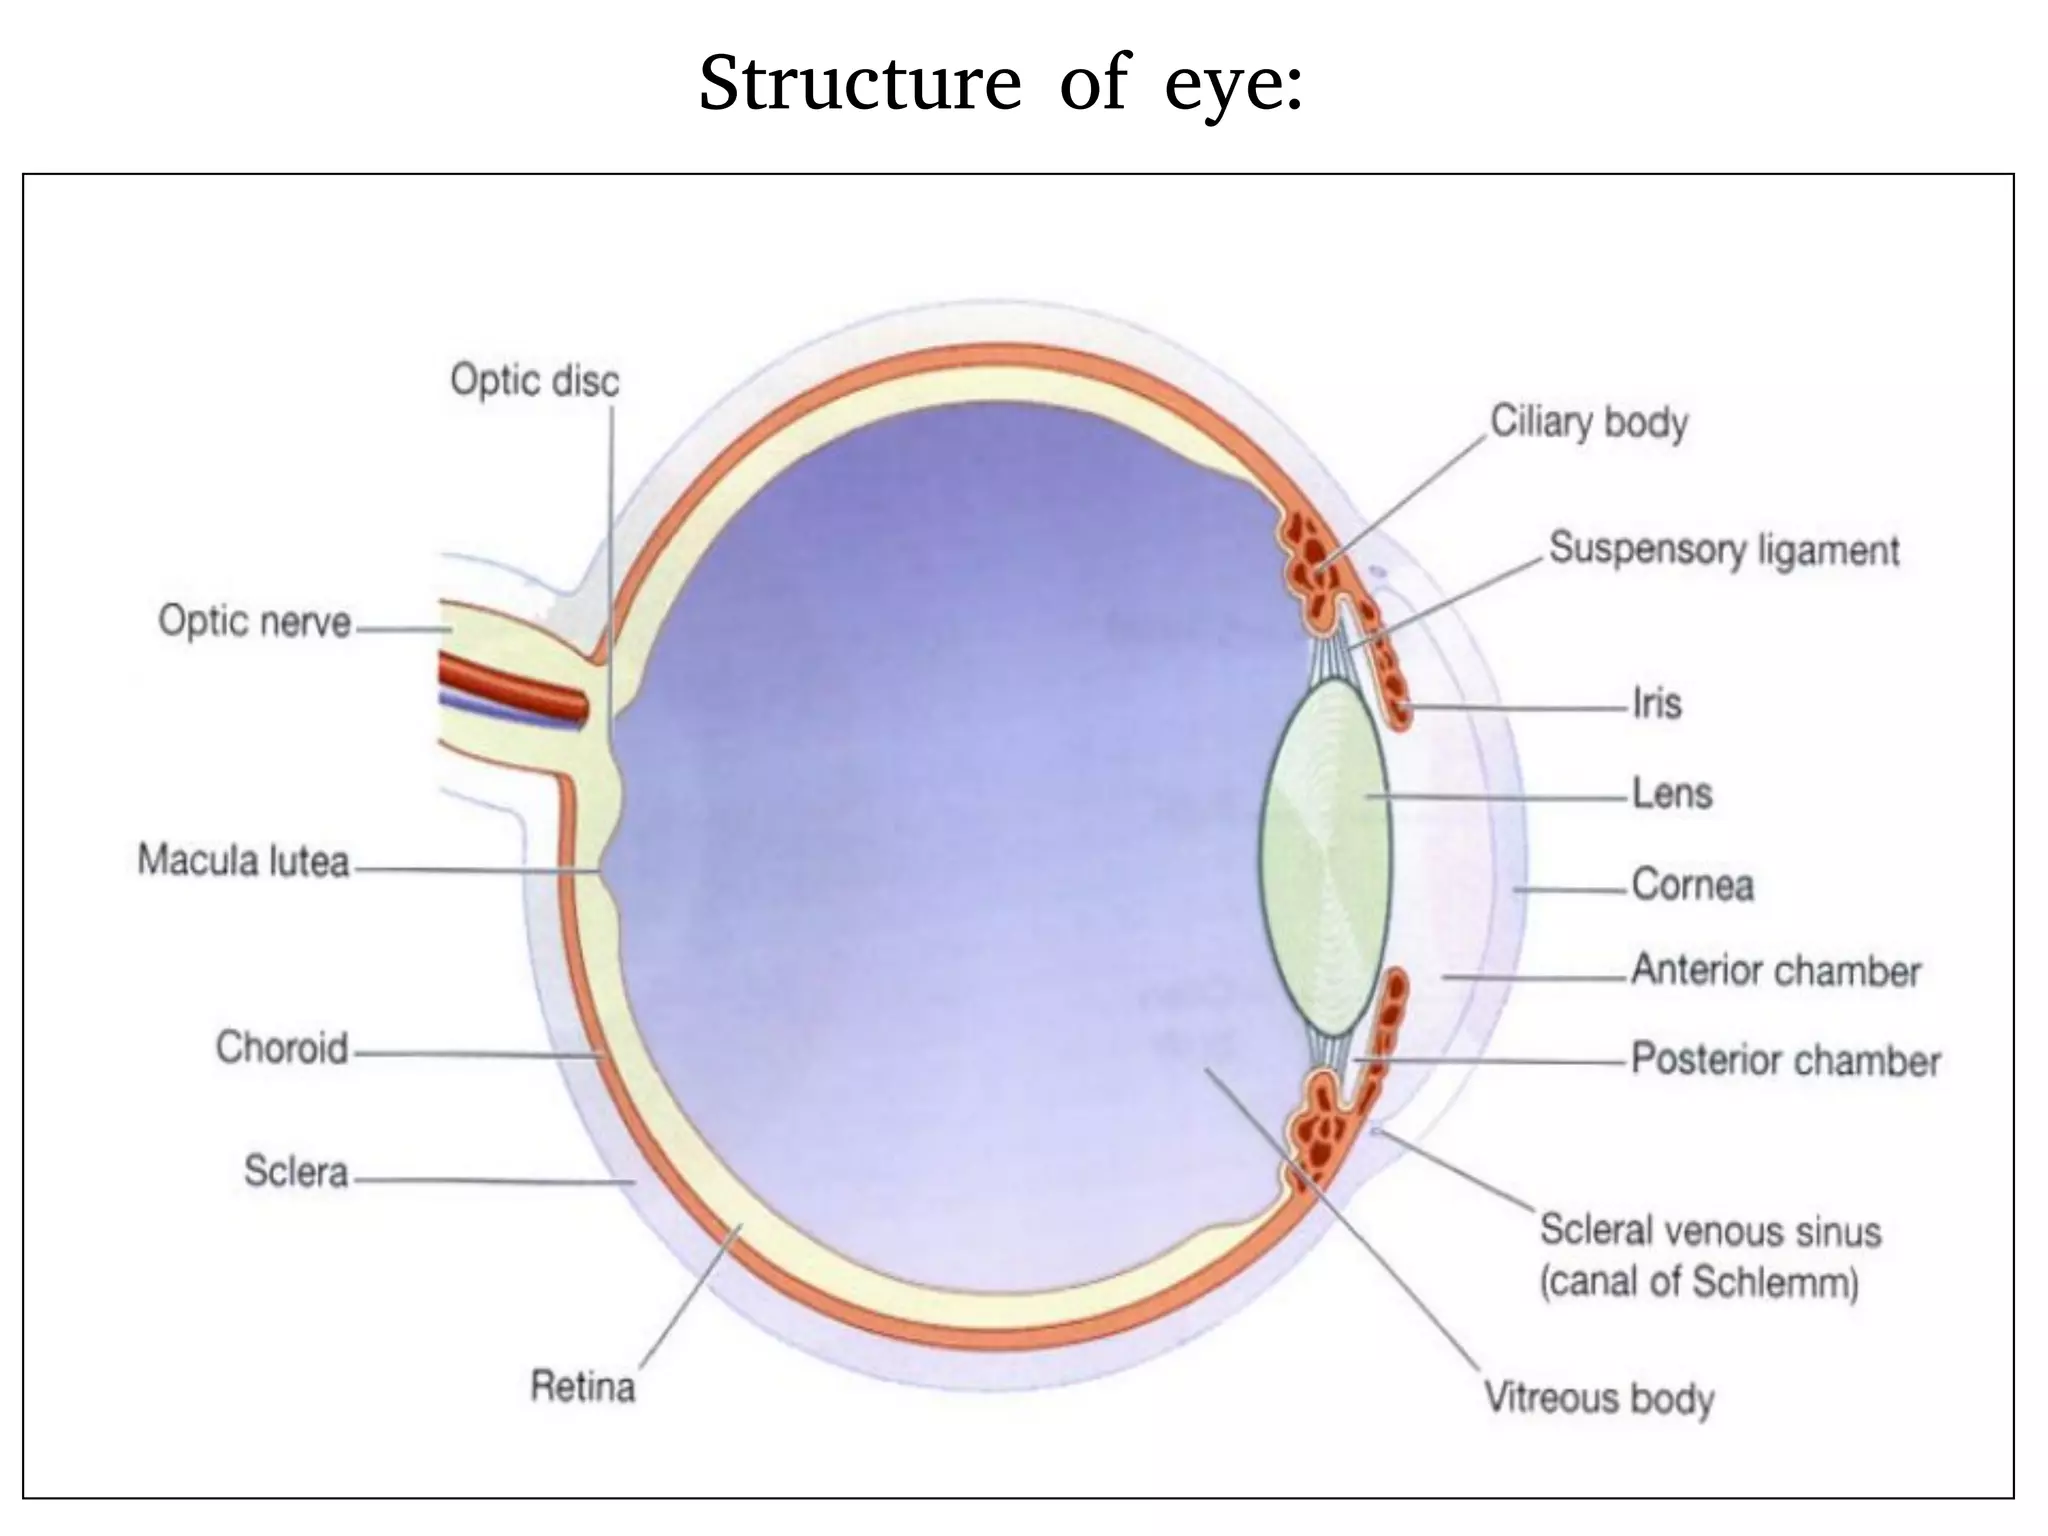
Most people think of the eye as a camera. That's the wrong mental model from the start. The eye is more like a biological sensor array that does heavy preprocessing before the signal even reaches the brain. The anatomy is built for exactly that kind of parallel processing. Start with the outer shell. The sclera is the white part, a collagen-rich fibrous coat that maintains intraocular pressure and provides attachment points for the extraocular muscles. Behind it sits the uveal tract — the choroid, ciliary body, and iris. The choroid is a vascular layer between the sclera and retina. It supplies oxygen and nutrients to the outer retinal layers. If you're studying cross-sections in a lab, this is the dark brown pigmented tissue you see filling the space between the retina and the sclera. The cornea covers the anterior portion. It's avascular, transparent, and responsible for about two-thirds of the eye's total refractive power. The curvature alone typically sits around 7.8 millimeters radius. That's why corneal topography matters so much in refractive surgery — small changes there produce large shifts in focal point.
Behind the cornea is the anterior chamber, filled with aqueous humor produced by the ciliary body. This fluid exits through the trabecular meshwork into Schlemm's canal. Aqueous humor turns over roughly every 90 minutes. Blockage at the trabecular meshwork is what causes primary open-angle glaucoma, the most common form of glaucoma worldwide. I've seen patients who had normal eye pressure for years and then suddenly spiked because of a subtle change in outflow resistance that wasn't caught on routine screening. The iris sits behind the anterior chamber and controls pupil diameter through smooth muscle fibers. The sphincter pupillae constricts the pupil. The dilator pupillae, arranged radially, dilates it. These are both autonomic — you don't consciously control your pupils. The lens sits just behind the iris. It's a transparent, biconvex structure held in place by zonular fibers that attach to the ciliary body. When the ciliary muscle contracts, zonular tension relaxes and the lens becomes more convex for near focus. This process is called accommodation. The vitreous body fills the large posterior cavity. It's a gel-like substance composed of 98% water with a sparse network of collagen fibers and hyaluronic acid. Over time, the vitreous undergoes liquefaction — a process called syneresis. Posterior vitreous detachment is common after age 55 and typically presents as floaters and flashes of light.
Retina and the Neural Processing Layer
The retina is neural tissue. It's technically part of the central nervous system, not a simple light sensor. Light passes through the cornea, aqueous humor, pupil, lens, and vitreous before reaching the photoreceptor layer at the back. That inversion matters because the retinal vasculature runs in front of the photoreceptors. The blood-retina barrier prevents those vessels from leaking into the photoreceptive layer under normal conditions. There are two types of photoreceptors. Rods handle scotopic (low-light) vision and are concentrated in the peripheral retina. Cones handle photopic (daylight) vision and color detection, concentrated in the fovea centralis. The fovea is a small depression about 1.5 millimeters in diameter where cones are packed tightly and the inner retinal layers are displaced laterally to minimize light scattering. Visual acuity is highest here — roughly 20/20 or better. Beyond the photoreceptors are bipolar cells, horizontal cells, amacrine cells, and ganglion cells. The signal path goes photoreceptor bipolar ganglion. Horizontal and amacrine cells provide lateral inhibition, which is how contrast enhancement happens at the retinal level before anything reaches the brain. Ganglion cell axons converge at the optic disc to form the optic nerve. The optic disc has no photoreceptors — that's your blind spot. Most people never notice it because the brain fills in the gap using information from the surrounding visual field.
Get the Full Details

The macula sits temporal to the optic disc and contains the fovea at its center. It's responsible for central vision and fine detail. Macular degeneration is the leading cause of irreversible vision loss in people over 60 in developed countries.
Optic Pathway and Central Processing
Optic nerve fibers exit the eye at the optic disc and travel posteriorly. Fibers from the nasal half of each retina cross at the optic chiasm. Temporal fibers stay on the same side. After the chiasm, the reorganized fibers form the optic tract. The lateral geniculate nucleus of the thalamus is the main relay station. From there, fibers project through the optic radiations to the primary visual cortex in the occipital lobe at the posterior pole of the brain. Something most textbooks gloss over: the superior colliculus in the midbrain receives direct retinal input and coordinates eye movements and orienting responses. This is separate from the conscious visual pathway. It's why you can reflexively turn your eyes toward a movement in your peripheral vision without being consciously aware of it first.
A Practical Problem I Dealt With
I once worked with a patient whose OCT scans looked perfectly normal across every parameter — retinal thickness, ganglion cell layer integrity, macular volume. But their visual field testing showed a consistent paracentral scotoma that didn't match any known anatomical defect. Standard interpretation would have suggested early glaucomatous damage, but the structural data said otherwise. What we eventually found was a subtle vitreomacular interface abnormality — a tiny epiretinal membrane causing microscopic wrinkling of the retina in the papillomacular bundle region. It wasn't showing up on standard OCT because the B-scan resolution was insufficient for that degree of surface irregularity. High-resolution macular OCT with en face reconstruction finally revealed it. This is the kind of edge case that comes up when you stop treating the numbers and start looking at the image. Most clinicians rely heavily on automated segmentations from OCT. Those algorithms assume a clean layered structure. When that assumption breaks, the data can look deceptively normal. The eye doesn't focus like a camera lens. The cornea does most of the refraction. The lens fine-tunes. When someone says their "lens is cloudy" from a cataract, they're not wrong, but they might miss that the cornea is doing the heavier lifting optically. That's why corneal astigmatism matters enormously in cataract surgery planning. If you replace the lens but ignore pre-existing corneal astigmatism, the patient will still need correction for distance vision. Intraocular pressure isn't constant. It follows a circadian rhythm. Pressure is typically highest in the early morning hours, around 4 to 6 AM. For glaucoma management, that means a single clinic reading doesn't capture the full picture. Some patients have normal office readings but dangerous nocturnal spikes. I've seen this repeatedly with patients whose best-case IOP was 16 but whose worst was 26. The standard once-daily drop schedule often misses these peaks. Switching to a twice-daily regimen or adjusting the timing of medication to cover those morning hours made a measurable difference in progression rates for those patients.

Refractive errors aren't just about the lens. Axial myopia — an eyeball that's too long — accounts for the majority of nearsightedness cases. A 1 mm increase in axial length produces roughly 3 diopters of myopia. That's why childhood myopia control strategies focus on limiting axial elongation, not just prescribing stronger glasses. Glasses correct the symptom. They don't slow the progression.
Limitations in Clinical Practice
The biggest gap in understanding eye anatomy and physiology is how interconnected everything is. You can't treat one structure in isolation. A corneal condition affects intraocular pressure measurement accuracy — keratoconus flattens the cornea and gives falsely low IOP readings on Goldmann applanation tonometry. Conversely, a thick cornea can mask elevated pressure. This is why corneal pachymetry should be routine whenever IOP is being measured. I've lost count of the number of patients who were told their pressure was normal and sent home, only to present later with advanced glaucomatous damage because their cornea was thicker than average and masked the true reading. Another limitation: color vision testing is surprisingly unreliable in primary care settings. The Ishihara plates catch some congenital defects but miss acquired color vision loss from optic neuropathy or macular disease. If a patient complains about color changes — like noting that reds look washed out — that's worth investigating regardless of a normal Ishihara result. Fluorescein angiography or spectral domain OCT can reveal problems that basic color testing won't catch. The eye also doesn't regenerate. Neural tissue in the retina doesn't repair itself the way skin or liver does. Once ganglion cells die from glaucoma or optic nerve damage, they're gone. This is why early detection matters more than almost any other condition in medicine. By the time a patient notices vision loss from glaucoma, significant neural tissue has already been lost. There's no coming back from that. Prevention and monitoring are the only tools we have.