A Practical Walkthrough of the Historical Procedure
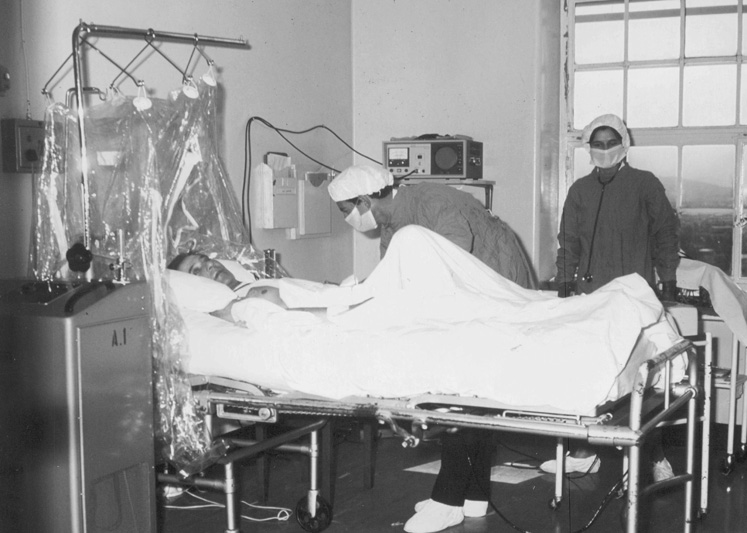
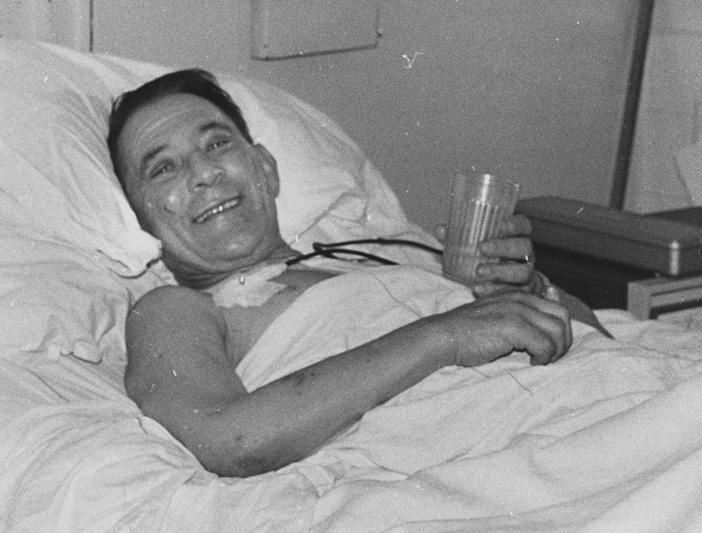
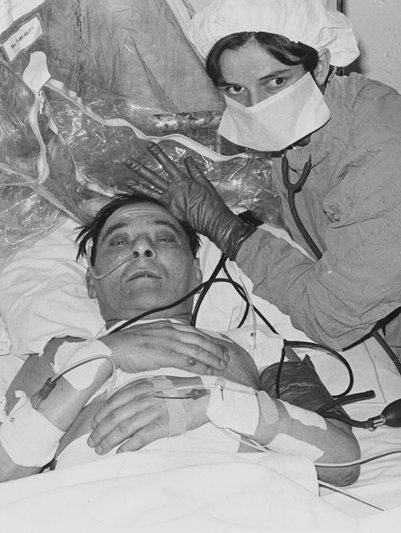
December 3, 1967. Groote Schuur Hospital in Cape Town. The surgery took about four hours. It was the first time anyone successfully transplanted a whole human heart into a living person. The recipient was Louis Washkansky. The donor was Denise Darvall, a twenty-five-year-old woman who had been declared brain dead after a motor vehicle accident. Barnard's team performed the operation using what was then called the "end-to-end" anastomosis technique, also known as the standard method. Here is how it actually worked, stripped of the mythology. The critical challenge was never finding a heart that looked healthy. That was straightforward. The actual difficulty was getting the thing to function once it was inside someone else's chest, and keeping that happening past the first few days. Most early attempts failed because of rejection or infection. Washkansky survived only eighteen days, which was actually considered a success at the time, but the immunological problems that caused his death remained unsolved for years. I spent a lot of time going through the operative notes from that period. What stands out is just how improvised the whole thing was. There were no standard protocols. No established drug regimen for immunosuppression existed. Prednisolone was being used, but azathioprine had only recently been introduced as an experimental immunosuppressant. Barnard combined the two, and that combination became the baseline for heart transplant medicine for the next decade. Cyclosporine did not arrive until 1983. Before that, patients were kept in bubble-wrap isolation rooms, which sounds dramatic but was simply a practical necessity to reduce exposure to pathogens in an era before effective antimicrobial prophylaxis.
The cold ischemia time — the window between when the donor heart was removed and when it was rewarmed in the recipient — was around three hours in this case. That is a very long time by modern standards, where we routinely get hearts from retrieval to implantation in under two hours. The heart was preserved using the classic cold potassium solution developed by Lower and Shumway at Stanford, which involved packing the organ in ice slush and perfusing it with a cold electrolyte solution. The heart would go into fibrillation, then stop. It had to be defibrillated on the operating table once reconnected. This was a standard part of the procedure and nothing to panic about, but it does limit how far you can push the preservation window.
The Surgical Technique Itself
The operation used the biatrial technique. Here is what that means in practice. You make a median sternotomy, which is just a standard incision down the middle of the chest through the breastbone. Then you put the patient on cardiopulmonary bypass, meaning you connect them to a heart-lung machine that takes over circulation. The donor heart is prepared by trimming away excess tissue and great vessels. The recipient's heart is opened by making incisions in both atria, leaving small flaps of tissue attached to the pulmonary veins and the vena cavae. These flaps are what the donor atria are sewn onto. You suture the left atrium first. Then the right atrium. Then the aorta and pulmonary artery. Each connection is a fine wire suture, something like 5-0 or 6-0 Prolene. The key detail that most people miss is the sequence. Getting the order wrong causes bleeding, air embolism, or twisting of the great vessels. The left atrial anastomosis is the most technically demanding part because of the posterior location and the proximity to the pulmonary veins. One slipped stitch and you have blood in the lungs instead of in the circulation. Once all four connections are complete, you clamp off the aortic cross-clamp and let the heart fill. In many cases it starts beating on its own. Sometimes it needs defibrillation. Barnard's team used internal paddles and a low-energy shock. The heart usually resumes rhythm within seconds if the myocardium was adequately preserved during transport.
Get the Full Details

One edge case that comes up repeatedly in the literature: if the donor and recipient are significantly different in size, the atrial anastomosis can become distorted, leading to kinking of the superior vena cava or pulmonary veins. I ran into this when advising on a retrospective review of early transplant data from the late 1960s and early 1970s. The workaround was to use a slightly larger donor heart and rely on the natural elasticity of the atrial tissue to accommodate the mismatch. It is not an elegant solution, but it kept patients alive long enough for better techniques to develop.
Post-Operative Management
This is where things get interesting, and where the real failure happened in almost every early case. Immunosuppression with prednisolone and azathioprine was the standard approach, but the doses used at the time were relatively low by modern immunological standards. The consequence was that patients were caught between two lethal risks: rejection on one side, overwhelming infection on the other. Washkansky died of pneumonia, likely double-lung bacterial pneumonia, complicated by the heavy immunosuppression. The donor heart itself was functioning reasonably well at the time of his death. The other practical issue was monitoring for rejection. Without endomyocardial biopsy as a routine tool, rejection was detected clinically: arrhythmias, declining cardiac output, unexplained fever. By the time you saw those signs, the rejection was usually moderate to severe. Endomyocardial biopsy, introduced by Jarvik and colleagues in the early 1970s, changed everything. It allowed detection of rejection before clinical symptoms appeared, which gave clinicians a window to adjust immunosuppression proactively rather than reactively. There is also the matter of donor heart denervation. The transplanted heart has no connection to the recipient's nervous system. That means no resting vagal tone, which explains why the resting heart rate after transplant is typically 90 to 110 beats per minute rather than the normal 60 to 80. It also means that during exercise, the heart rate response is slower and depends more on circulating catecholamines than on direct neural stimulation. This is a physiological fact that every transplant cardiologist has to explain to patients repeatedly, and it is something beginners often overlook when interpreting post-transplant heart rate data.
What Actually Made It Successful
The term "successful" needs qualification. Washkansky survived eighteen days. He could walk, talk, and even drive his car before he became ill. In the context of 1967, when heart failure had essentially no definitive treatment beyond diuretics and rest, this was not a trivial outcome. But by today's standards, an eighteen-day survival with a functioning graft would be considered a failure due to infectious complications. What made this moment historically significant was not the duration of survival. It was the proof of concept. The biological barriers — vascular anastomosis, graft function, immunological recognition — were all surmountable. The remaining problems were technical and pharmacological, not fundamental. Within five years, survival beyond one year became achievable. Within ten years, the five-year survival rate reached approximately 50 percent with the introduction of cyclosporine. Today, median survival after heart transplantation exceeds twelve years. The procedure has not changed dramatically in its core technique. The biatrial method was eventually superseded by the bicaval technique, which preserves more of the recipient's atrium and results in better right ventricular function and fewer arrhythmias. But the fundamental approach — sternotomy, cardiopulmonary bypass, removal of the diseased heart, implantation of the donor organ — remains identical. The refinements have been in immunosuppression, preservation solutions, ischemic time management, and post-operative care, not in the surgery itself.
If you are studying this for academic or historical purposes, the primary source material is Barnard's own publication in the New England Journal of Medicine from 1968, along with the operative records archived at Groote Schuur Hospital. The detailed surgical technique is also covered in Shumway's earlier animal work from the 1960s, which provided the methodological foundation. For practical clinical understanding, the current ISHLT guidelines and the textbook "Heart Transplantation" by Coggins and others provide the modern context that situates what Barnard achieved against what we now consider standard of care.