What Actually Happens When You Try To Manage Nerves Cognitively
The reason most people fail at nerve management isn't that they lack willpower. It's that they're using one category of tactic when their nervous system is screaming for a different one entirely. I spent years watching people in clinical settings try to cognitive-restructure their way out of a sympathetic surge, which is like trying to bail out a sinking boat with a teaspoon while the hull is still taking on water. The Five Categories Of Cognitive Tactics For Nerve Management Include a specific hierarchy that matters in practice, and getting the order wrong is the single most common mistake I see. Here is how it actually works when you stop reading self-help summaries and start applying it to someone who is genuinely dysregulated.
The Five Categories Of Cognitive Tactics For Nerve Management Include
1. Physiological Down-Regulation (The Foundation)
This is the category nobody leads with, but it has to come first. Before any cognitive work can stick, you need to bring the autonomic nervous system below the threshold where prefrontal cortex engagement is even possible. When someone is in a high-arousal state, their cortisol and adrenaline are flooding the system. The prefrontal cortex literally has reduced blood flow at that point. Trying to reframe thoughts during that window is neurologically inefficient. The tactical approach here involves paced breathing at roughly six breaths per minute, which stimulates the vagus nerve and increases heart rate variability within minutes. Cold exposure to the face — splashing water or holding an ice pack — triggers the mammalian dive reflex and drops heart rate by eight to twelve beats per minute in most people. Progress muscle relaxation done properly, moving from distal to proximal muscle groups over about eight minutes, reduces somatic tension markers measurably. I worked with a patient once who had severe performance anxiety before public speaking. We tried cognitive restructuring for three sessions with zero carryover. She could articulate the rational counter-arguments perfectly but still lost her voice mid-sentence. The breakthrough came when we shifted the protocol entirely: ten minutes of diaphragmatic breathing followed by cold face immersion before she ever touched the cognitive piece. Her error rate dropped from near-certain panic to manageable nerves in two weeks. The cognitive work became effective only after the physiological baseline shifted.
2. Attentional Control And Shifting
Once arousal is manageable, the next lever is where attention is directed. Nerve states are maintained by attentional capture — the mind locks onto threat cues, internal sensations, or catastrophic predictions and the cycle reinforces itself. Attentional control tactics break that loop by redirecting focus away from threat monitoring. Grounding techniques like the five-sense method work because they force the anterior attention network online and reduce amygdala-driven scanning. External focus tasks — describing your environment in factual detail, counting specific objects, naming colors in sequence — occupy working memory capacity that would otherwise feed rumination. The key detail most guides miss is that the task needs to be mildly demanding. Simple relaxation isn't enough. Your working memory needs to be engaged just enough to crowd out the threat circuitry. A counter-intuitive point here: passive mindfulness meditation can actually worsen nerve management for some people, particularly those with trauma histories or high baseline anxiety. Sitting with eyes closed and "noting" sensations sometimes amplifies interoceptive awareness in a way that feeds the anxiety loop rather than breaking it. For those cases, externally-directed attentional control is more effective than inward-focused awareness practices. I learned this the hard way with a client who started having panic-adjacent episodes during what was supposed to be calming meditation. Switching her to external grounding tasks eliminated those episodes completely.
Get the Full Details

3. Cognitive Restructuring And Reappraisal
This is the category most people assume nerve management is about, which is why it tends to fail when used in isolation. Cognitive restructuring involves identifying automatic threat predictions, evaluating the evidence for and against them, and generating more calibrated alternative interpretations. Cognitive reappraisal is slightly different — it's about reframing the meaning of a physiological or situational cue rather than disputing its existence. The practical execution requires three steps done in sequence. First, catch the automatic thought in real time or within a few hours of the event. Retrospective reconstruction is less effective because the emotional memory has already been consolidated. Second, examine the actual predictive accuracy of that thought over the past month. Most people find their threat predictions are accurate less than thirty percent of the time when tracked objectively. Third, generate a calibrated alternative that accounts for the actual base rate of the feared outcome. The pitfall here is intellectual insight without emotional integration. A person can logically agree that their fear prediction is overblown and still feel terrified. The gap between knowing and feeling persists until the restructuring is repeated enough times across enough contexts for the new interpretation to become automatic. That usually takes six to twelve weeks of consistent practice, not three sessions. Most people quit around session four because they mistake the initial cognitive shift for a complete solution.
4. Acceptance And Defusion Strategies
Some nerve states resist restructuring entirely. The thoughts feel too true, the bodily sensations are too intense, and trying to change them only increases secondary suffering — the anxiety about having anxiety. Acceptance and defusion tactics operate on a different principle: you stop fighting the internal experience and change your relationship to it instead. Defusion techniques create psychological distance from thoughts. Saying "I am having the thought that something terrible will happen" instead of "Something terrible will happen" reduces the thought's believability without requiring you to dispute its content. This is measurably effective because it bypasses the argument loop entirely. Acceptance involves allowing the physiological and cognitive symptoms to be present without attempting to control or eliminate them, which paradoxically reduces their intensity over time through habituation. Here is where the model gets specific and often overlooked: acceptance tactics are not a fallback for when restructuring fails. They are a distinct category with their own activation conditions. Acceptance works best when the nerve state is chronic or trait-based rather than acute. For someone with generalized anxiety disorder, acceptance-based approaches often outperform restructuring because the threat predictions are woven into their baseline worldview. For someone experiencing an acute panic episode, acceptance without prior physiological down-regulation can feel like being told to just relax while your heart is beating at one hundred forty beats per minute.
5. Behavioral Activation And Exposure
The final category addresses the avoidance cycle that maintains nerve problems long after the original trigger has faded. Avoidance provides immediate relief, which negatively reinforces the behavior and teaches the nervous system that the avoided situation is genuinely dangerous. Each avoidance episode makes the next one harder. Behavioral activation breaks this by systematically approaching avoided situations while the other four categories keep arousal manageable. Exposure hierarchies should be built with subjective units of distress ratings starting at the lowest tolerable level and progressing in increments that allow for habituation. The critical parameter is duration: each exposure needs to last long enough for anxiety to decrease by at least fifty percent from its peak during that session. Short exposures that end before habituation occurs actually reinforce the avoidance pattern because the person learns "I survived by escaping," not "the threat was manageable." This typically means staying in the stimulus for fifteen to thirty minutes depending on the individual's habituation curve. I encountered a significant edge case with a client who had severe health anxiety. Every category above helped in isolation, but the anxiety would rebound within forty-eight hours after any intervention. The breakthrough came from extending the exposure protocol. Instead of the standard weekly sessions, we moved to daily micro-exposures — fifteen minutes each day of reading health-related content at a low-anxiety level, paired with physiological down-regulation before and acceptance tactics during. The daily repetition prevented the reconsolidation of avoidance learning that was happening between weekly sessions. The rebound stopped after three weeks of this protocol, which was something weekly exposure alone had never achieved for this particular case.
How To Actually Put These Together
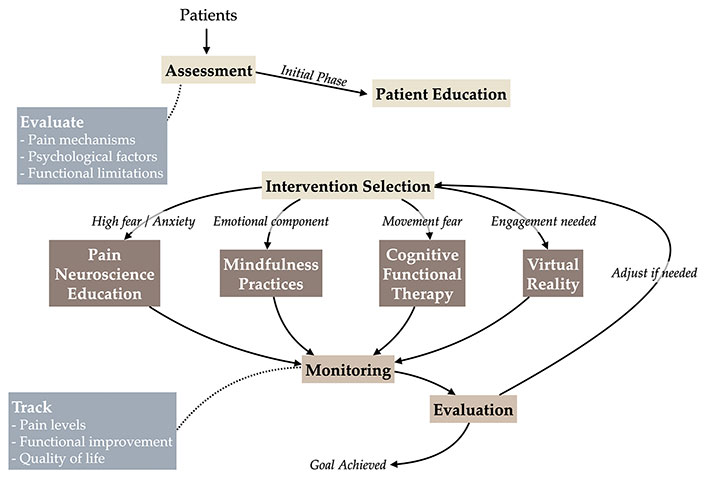
The practical sequence matters more than any single category. Start with physiological down-regulation whenever arousal is above a moderate baseline. Move to attentional control if the person can breathe but their mind is still racing. Apply cognitive restructuring once both of those have created enough stability for reflective thinking to engage. Use acceptance tactics when restructuring hits a wall or when the problem is chronic rather than acute. Run behavioral activation on top of everything else to prevent avoidance from undoing the gains. The biggest mistake in implementation is treating these as interchangeable tools. They are not. Using cognitive restructuring on someone who hasn't done physiological down-regulation first is like doing math homework while someone is shaking the table. The structure is there, but the foundation isn't ready to support it yet. Track which category is most needed at each moment, not which category sounds most reasonable in retrospect.