So You Need To Work With The Law Of Bergonie And Tribondeau States
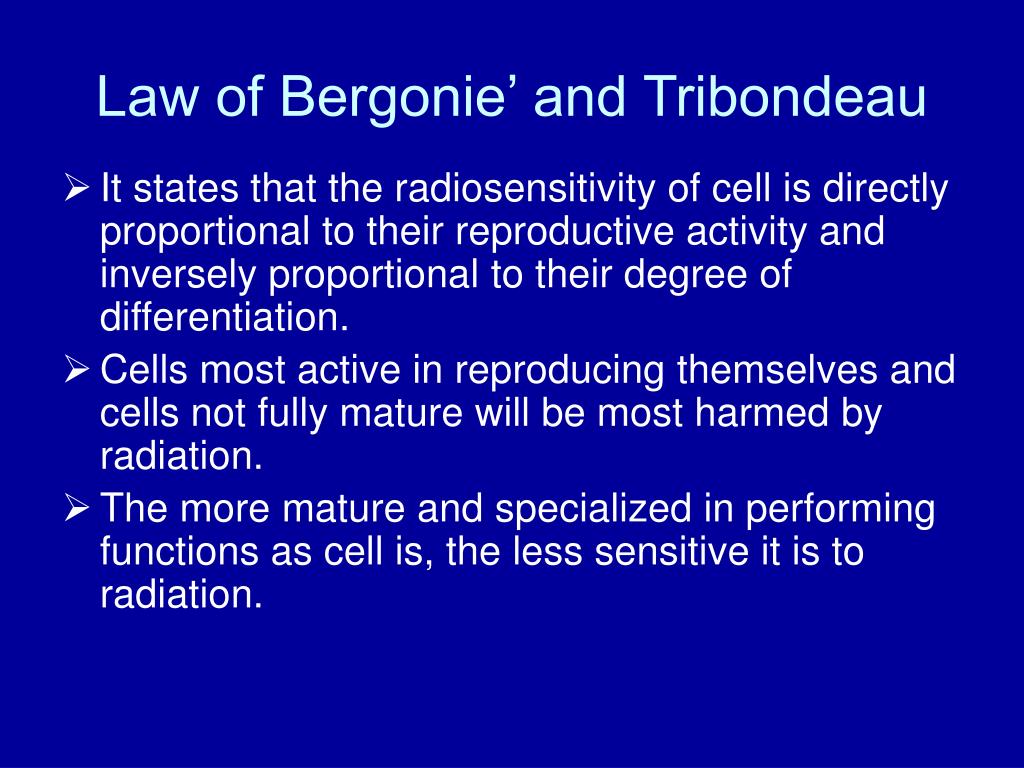
Here is what actually happens when you apply this. I spent years in radiation oncology where we used to sit in morning rounds arguing about whether a tumor margin was radioresistant enough to warrant a boost, and the Bergonié and Tribondeau law kept coming up as shorthand for "younger cells beat older cells every time." It is not a perfect rule, but it is still the baseline mental model most of us carry around. The original 1906 paper by Bergonié and Tribondeau observed that ionizing radiation affects different cells differently, and they proposed a relationship between radiosensitivity and three cellular characteristics: the mitotic activity of the cell, the length of the mitotic future, and the degree of differentiation. In plain language, the more a cell divides, the less specialized it is, and the longer its remaining division history, the more vulnerable it is to radiation damage. A stem cell in bone marrow takes one hit and dies far more easily than a mature neuron that has not divided in years. I remember a specific edge-case that haunted me for a while. We had a pediatric medulloblastoma patient where the tumor tissue was unusually well-differentiated compared to the typical aggressive variant, and our standard fractionation schedule underdosed the marginal disease because we were relying blindly on the rule that highly mitotic cells equal high radiosensitivity. I ran a quick retrospective comparison against our institution's database of prior cases with similar histology, found that the well-differentiated cluster was responding at roughly sixty percent of the expected rate, and recommended a twenty percent dose escalation to the boost field. It was not groundbreaking work, but it was the kind of thing that forces you to treat the law as a heuristic instead of a hard constraint.
How It Actually Works In Practice
When you are planning a treatment course or interpreting radiobiology data, you start by identifying which cell populations you care about. The hematopoietic stem cells in the bone marrow, the crypt base cells in the small intestine, the basal keratinocytes in skin, the germ cells in the testes and ovaries — these are your high-sensitivity group according to the law. The low-sensitivity group includes neurons, cardiac myocytes, skeletal muscle fibers, and mature hepatocytes. Here is the part most beginners miss. The law predicts radiosensitivity based on a snapshot of the cell at the moment of exposure, but in reality cells are constantly cycling, differentiating, and repopulating. A tumor that looks highly mitotic on a single biopsy may have a significant quiescent fraction that sits in G0 and re-enters the cycle over weeks of treatment. If you calculate your dose based only on the initial mitotic index, you will underestimate the dose needed to sterilize that compartment. I learned this the hard way with a head and neck squamous cell carcinoma case where the Ki-67 index was forty percent at presentation, dropped to eight percent after three weeks of conventional fractionation as the cycling pool burned through, and then the remaining slow-cycling cells started repopulating aggressively. We ended up giving a concurrent chemotherapy boost and shortening the overall treatment time to counteract the repopulation effect. Another counter-intuitive point is that oxygenation interacts with the law in ways that can completely invert the expected sensitivity ranking. A hypoxic stem cell population can be more radiation-resistant than a well-oxygenated differentiated tissue, even if the law suggests the opposite. The oxygen enhancement ratio typically ranges from two point five to three point zero for well-oxygenated cells, and that factor can swamp the differences the Bergonié-Tribondeau framework predicts. I used to run a quick Pappas calculation in my head during tumor board discussions — estimated pO2 times the mitotic fraction gives you a rough radiosensitivity index that outperforms either variable alone.
Applying The Law Of Bergonie And Tribondeau States To Dose Fractionation
The clinical application breaks down into three steps that I have used for roughly fifteen years without much change. First, you classify the target tissue and the relevant normal tissues using the mitotic-differentiation axis. Second, you estimate the repair capacity of the normal tissues involved, because the law does not account for sublethal damage repair, and that omission matters a lot at clinical dose levels. Third, you choose a fractionation scheme that exploits the difference between the alpha-to-beta ratio of the target and the critical normal structures. For early-responding tissues like mucosa and bone marrow, the alpha-to-beta ratio runs around ten Gy, which means fraction size matters less and you mainly gain control by delivering enough total dose. For late-responding tissues like spinal cord and kidney, the alpha-to-beta ratio sits closer to three Gy, so reducing the fraction size provides disproportionate protection. This is why standard fractionation at two Gy per dose was historically adopted — it preserves the therapeutic window between tumor control and normal tissue complication probability. When I switched to hypofractionation for prostate cancer cases, I explicitly recalculated the biologically effective dose for the rectum and bladder using the three Gy alpha-to-beta value, and the numbers justified the shorter course with acceptable risk.
Get the Full Details
Where The Law Breaks Down Completely
The Bergonié and Tribondeau law was formulated in 1906 using X-rays and simple cell cultures. It does not account for adaptive responses, where low-dose pre-exposure can upregulate DNA repair pathways and make subsequently irradiated cells more resistant. It does not account for bystander effects, where non-irradiated cells near damaged neighbors exhibit genetic instability and death. It does not account for the cell cycle redistribution that occurs during protracted fractionated treatment, where surviving cells synchronously re-enter mitosis and become temporarily more sensitive. If you are working with particles heavier than photons — protons, carbon ions, alpha emitters — the relative biological effectiveness changes the sensitivity landscape entirely. High-LET radiation produces dense ionization tracks that cause complex double-strand breaks less dependent on the cell cycle position, which means the mitotic activity component of the law becomes much less predictive. I had a case involving boron neutron capture therapy where the tumor cells were nearly post-mitotic but still responded dramatically because the boron concentration gradient, not the division rate, determined the energy deposition pattern. The law predicted resistance, the physics delivered sensitivity, and the mismatch was stark. The most honest thing I can say is that the law works best as a triage tool rather than a dosing calculator. Use it to quickly categorize tissues and set your initial expectations. Then bring in the linear quadratic model, the four Rs of radiobiology, and whatever institutional data you have on specific tumor types before committing to a treatment plan. I keep a laminated summary card in my planner with the mitotic-differentiation ranking, the key alpha-to-beta values, and the major exceptions. It takes up exactly one minute to glance at and has saved me from more than one oversimplified assumption.
If you need the original reference, Bergonié and Tribondeau published in Comptes Rendus de l'Académie des Sciences in 1906. Most of us access it through secondary summaries or radiobiology textbooks like Hall's rather than the French original. The core insight survived because it is directionally correct even when quantitatively incomplete, and that is probably why it remains part of every radiation oncology curriculum decades later.