Breaking Down Cranial Anatomy Without the Fluff
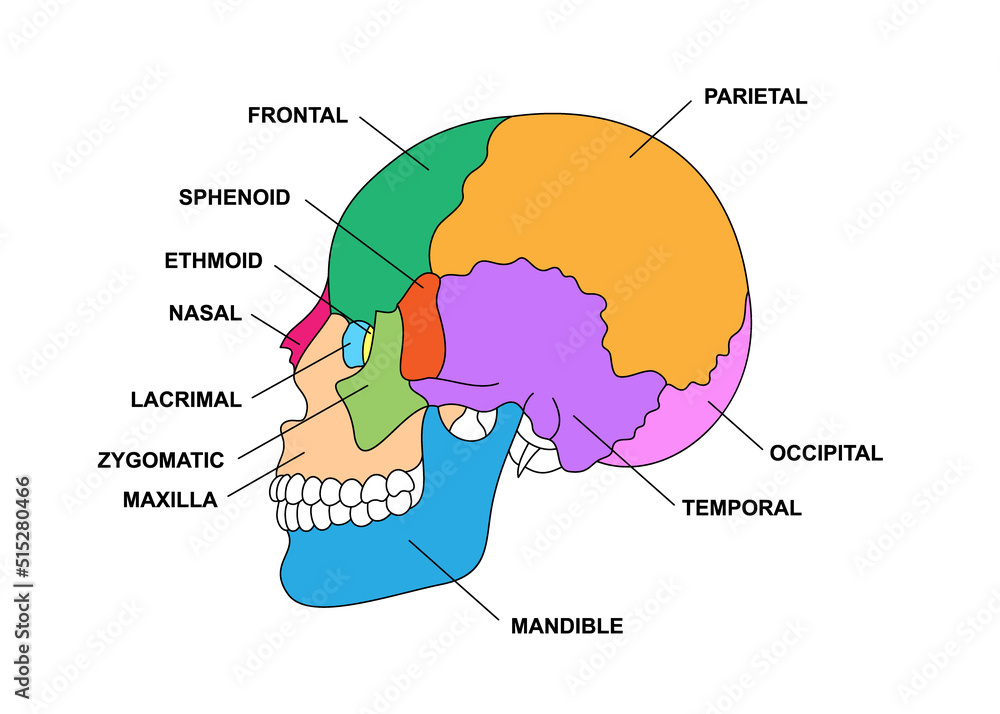
The skull is made up of several distinct bones, and when you're trying to understand them, most guides either oversimplify or drown you in Latin names you'll forget by Tuesday. Let's go through what's actually there, how they fit together, and where people typically mess this up. The cranium consists of eight bones: the frontal bone (forehead area), two parietal bones (top and sides), two temporal bones (sides near the ears), the occipital bone (back of the skull), the sphenoid bone (a bat-shaped bone at the base), and the ethmoid bone (between the eyes). Below the cranium sits the facial skeleton, which includes the maxilla, mandible, zygomatic bones, nasal bones, and a handful of smaller bones like the lacrimal and palatine bones. In practice, the sutures between these bones are what matter most clinically and anatomically. The coronal suture connects the frontal to the parietals, the sagittal suture runs between the two parietals, and the lambdoid suture separates the parietals from the occipital. These joints fuse over time, which creates a real headache when you're working with older skeletal remains or trying to interpret CT scans where the sutures have essentially disappeared into a single line.
I spent months cataloging cranial variations for a forensic anthropology project, and the one thing nobody warns you about is the wormian bones. These are extra little ossicles that show up in the sutures, especially around the lambdoid area, and they appear in roughly 20-30% of the population. If you're learning the standard diagram, you won't expect them, and you'll either misidentify them as fractures or just leave them off your labels entirely. My workaround was simple: after identifying the major sutures, I went back through every specimen specifically looking for small irregular densities along those suture lines before finalizing my annotations. The temporal bone is where most people run into trouble. It's not one uniform piece. It has the squamous part, the tympanic ring, the mastoid process, and the petrous portion, which houses the entire inner ear apparatus. The petrous part is the densest bone in the human body, and on CT imaging it shows up almost-white against the rest of the skull. When I was reviewing trauma scans, I initially kept missing fractures through the petrous apex because the bone's natural density variations make it look like artifact. The fix was opening the bone window and adjusting the level and width settings rather than relying on the standard soft tissue preset. Another thing beginners miss: the sphenoid sinus. It's located right under the sella turcica, the depression where the pituitary gland sits, and it varies enormously in size between individuals. Some people have tiny underdeveloped sinuses there, others have these massive air cavities that extend far laterally. This matters if you're ever dealing with surgical planning through the nasal passage, because an unusually large sphenoid sinus means less bone to work with and higher risk of hitting adjacent structures like the internal carotid artery, which runs right alongside it.
The frontal sinus is similarly unpredictable. It's not symmetrical, it's not constant, and it changes with age. Most adults have well-developed frontal sinuses, but a meaningful percentage don't, and when they do develop, they continue to expand throughout life. If you're matching a skull to antemortem records and the frontal sinus pattern is part of your identification method, missing the fact that a person simply lacks developed sinuses will waste your time. The mandible is sometimes overlooked in basic listings because it's technically separate from the cranium, but it's still a part of the head and it's the only mobile bone in the skull. The body, ramus, condylar process, coronoid process, and mental foramen are the key landmarks. The mental foramen is usually between the first and second premolars, but that's a guideline, not a rule. I've seen it as high as the first molar and as low as the inferior border in different specimens. If you're studying this for an exam, focus on the sutures and the key landmarks rather than memorizing every minor process. If you're studying this for clinical work, spend time on the temporal bone and the skull base because that's where things go wrong. The skull base anatomy, particularly the foramina through which nerves and vessels pass, is where the real complexity lives, and it's also where most quick-reference guides cut corners.
Get the Full Details