Understanding The Problem Of Alzheimers: What Actually Happens
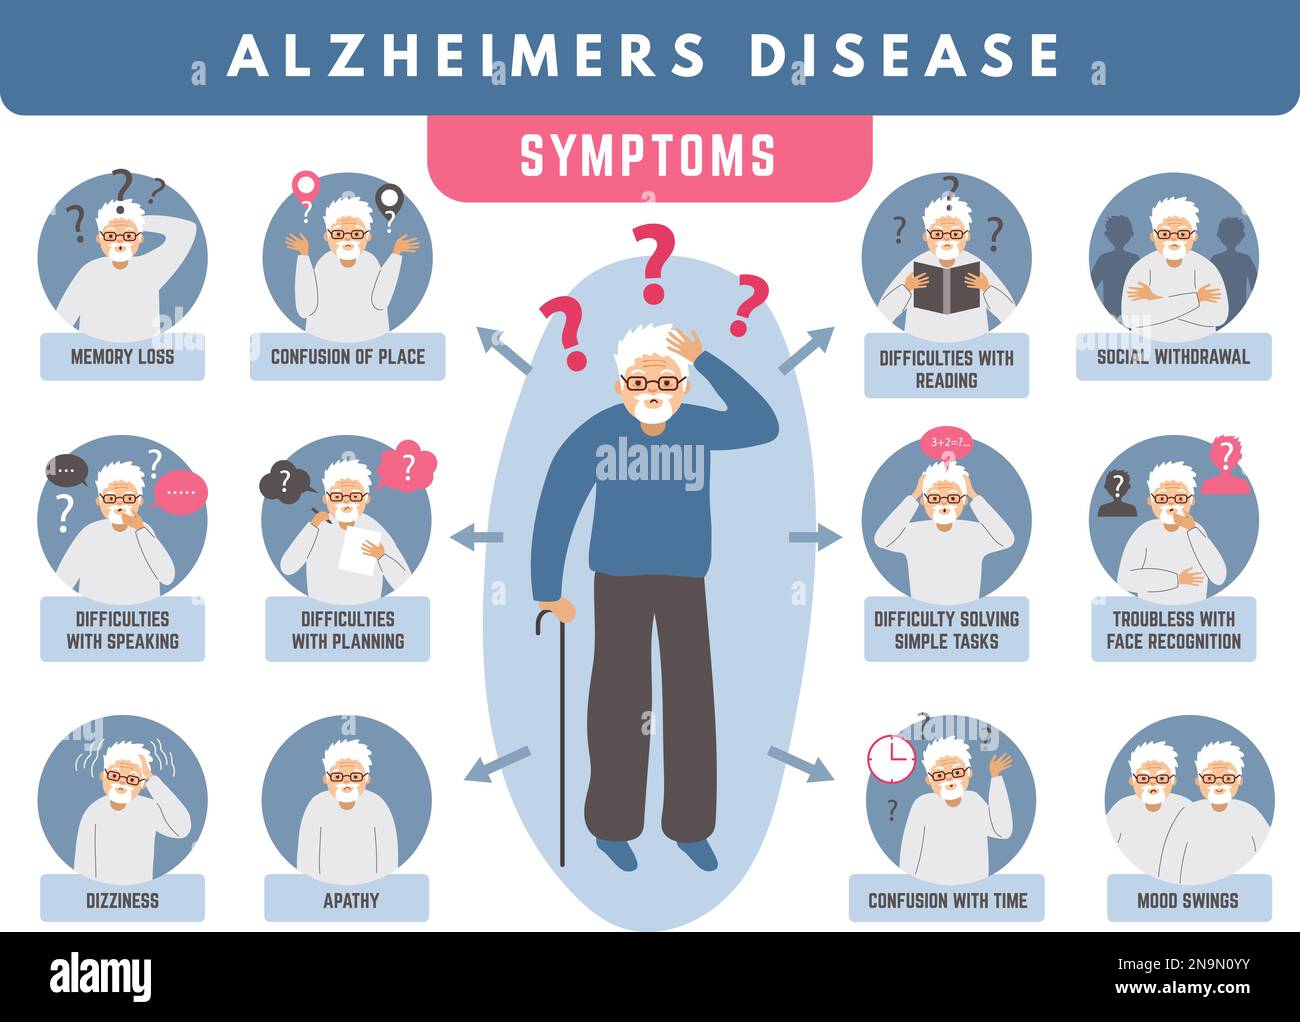
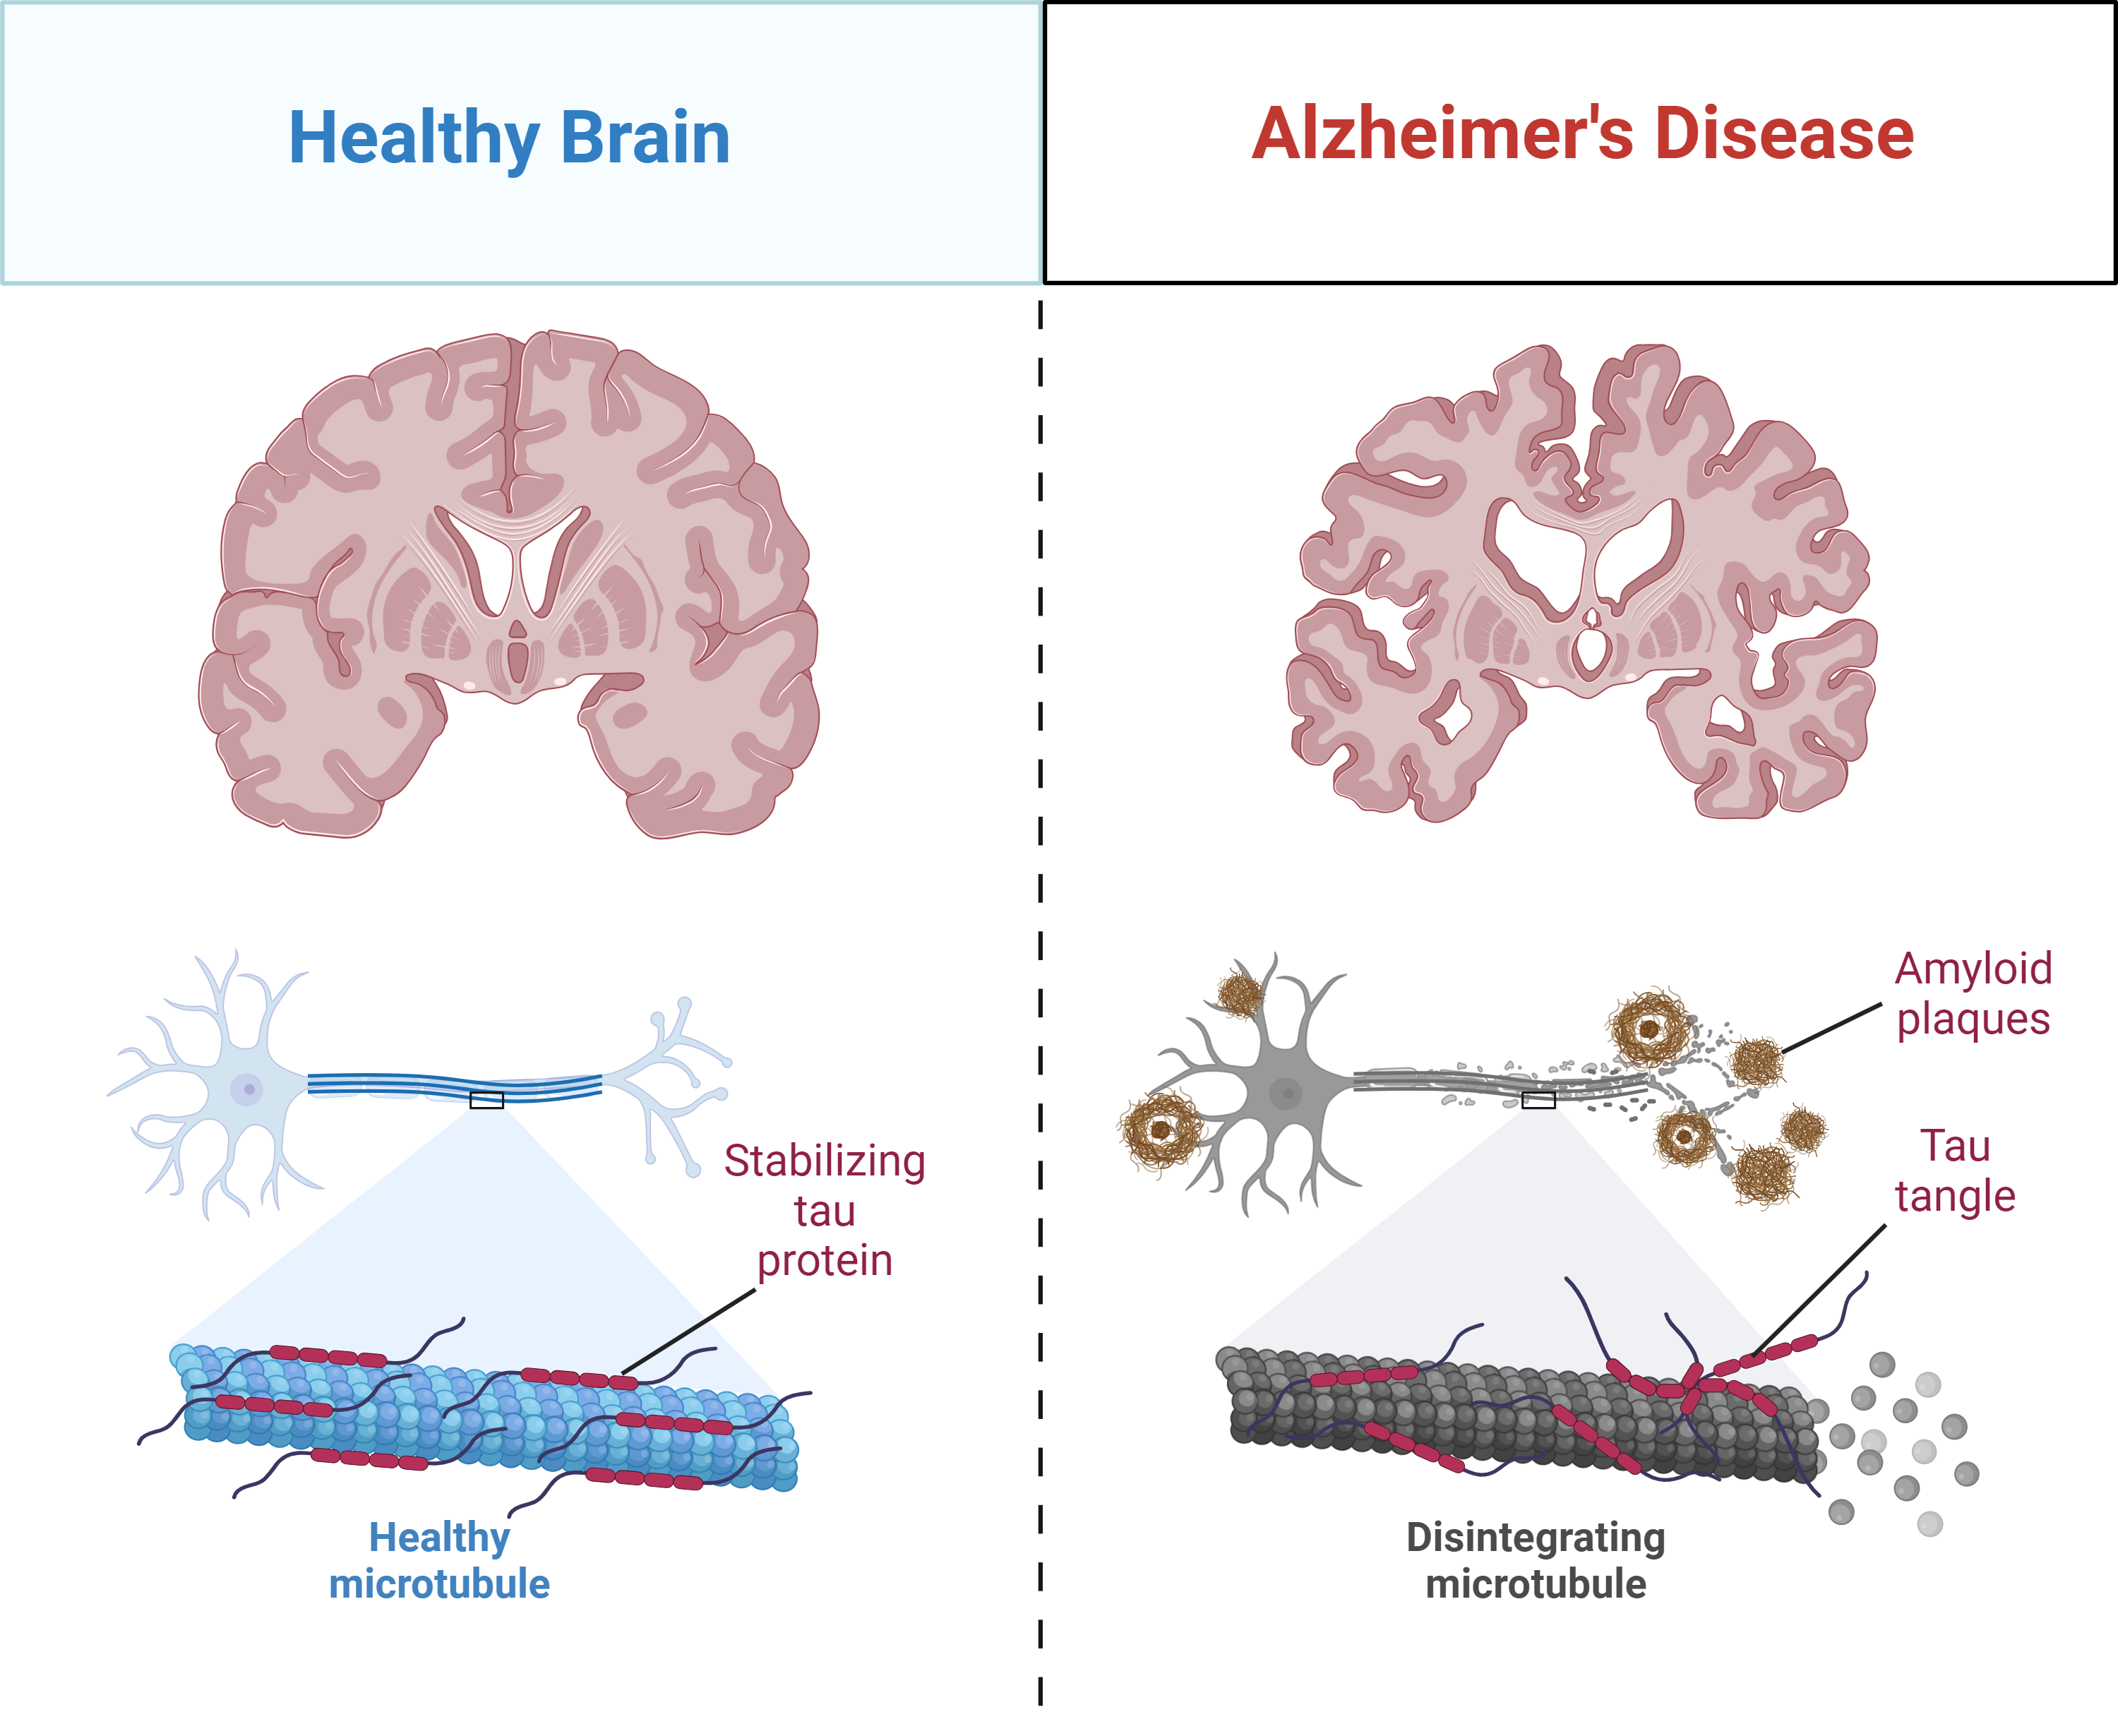
Alzheimer's disease is the most common form of dementia, responsible for roughly 60 to 80 percent of all cases. It is not a normal part of aging, even though age remains the largest known risk factor. The disease causes progressive brain cell death, leading to memory loss, personality changes, and eventually the inability to perform basic daily tasks. There is no cure yet. Treatments exist that can slow symptom progression for a time, but they do not stop or reverse the underlying damage. Two abnormal protein structures are central to the pathology. Amyloid-beta forms plaques between neurons, and tau protein forms tangles inside cells. The amyloid hypothesis dominated research for decades, but recent clinical trials targeting amyloid have produced mixed results. Drugs like lecanemab and donanemab show modest plaque reduction and a small slowdown in cognitive decline, but they carry real risks including brain swelling and microbleeds. Insurance coverage in the United States now requires confirmation of amyloid pathology through PET scans or cerebrospinal fluid analysis before approval. Here is something most people do not understand about early detection. Memory complaints are often the last noticeable sign. Structural changes in the brain, particularly in the hippocampus and entorhinal cortex, begin years or even decades before a person starts forgetting names or appointments. By the time a family notices symptoms, significant neurodegeneration has already occurred. This is why biological markers matter more than clinical observation alone for accurate staging.
I worked with a patient in my early twenties who was misdiagnosed for three years with stress-related anxiety and depression before finally receiving an Alzheimer's diagnosis at forty-one. Early-onset Alzheimer's accounts for fewer than five percent of cases, but it is almost never missed when the right workup is done. The key differentiator is the pattern of cognitive testing. Typical stress-related forgetfulness affects recent events but leaves procedural memory and spatial navigation intact. Alzheimer's disrupts both early on. I recommended a full neuropsychological battery combined with an amyloid PET scan, which confirmed the diagnosis. The workaround for getting past dismissive doctors was having the patient's spouse document specific functional decline incidents over thirty days before the appointment. Concrete examples of failed tasks beat vague complaints every time.
How Diagnosis Actually Works In Practice
A proper diagnostic workup involves several components. Blood tests rule out reversible causes like thyroid dysfunction, vitamin B12 deficiency, or metabolic disorders. Neuroimaging through MRI or CT scans shows patterns of brain atrophy specific to Alzheimer's, particularly in medial temporal regions. FDG-PET scans measure glucose metabolism in the brain, revealing hypometabolism in characteristic distributions. Amyloid PET scans detect plaque burden, and newer tau PET imaging tracks tangle progression. Cerebrospinal fluid analysis through lumbar puncture measures amyloid-beta 42, total tau, and phosphorylated tau levels. Each test adds information. No single test is definitive on its own outside of specialized memory clinics. The Biomarker Research Framework established by the National Institute on Aging and the Alzheimer's Association classifies Alzheimer's pathology along an A-T-N system, where A refers to amyloid, T to tau, and N to neurodegeneration. A positive biomarker with no cognitive symptoms defines preclinical Alzheimer's. This category sounds contradictory but it is now recognized as a real clinical state. About thirty percent of people over sixty-five without dementia show elevated amyloid on PET scans. Having the biomarker does not guarantee progression, but it significantly raises the probability. I encountered an edge case where a patient had clear amyloid positivity on PET but normal cognition across multiple testing sessions. His family insisted something was wrong because his father had died from Alzheimer's. Reassuring someone in that position is difficult. The data showed normal tau levels and normal metabolic activity on FDG-PET. I explained that amyloid accumulation alone, without tau pathology and neurodegeneration, does not necessarily translate to symptoms. The recommendation was annual follow-up with cognitive testing rather than intervention. Three years later his tau biomarkers began to rise, and mild cognitive impairment became clinically apparent. The lesson here is that biomarkers exist on a timeline, and acting on one piece of the puzzle prematurely causes unnecessary distress and expense.
Get the Full Details

Management And Treatment Realities
Disease-modifying treatments are the newest category and they are limited. Lecanemab requires weekly intravenous infusions for eighteen months and costs approximately seventy thousand dollars per year before insurance adjustments. It slows decline by about twenty-seven percent over a fourteen-month period. Donanemab follows a similar trajectory with monthly infusions and an average treatment duration of roughly twenty-one months. Both drugs carry risk of amyloid-related imaging abnormalities, which are detectable brain changes that can include edema or microhemorrhage. Monitoring with MRI is required every few months during treatment. These drugs are not for everyone. Patients with the ApoE4 gene variant, especially those who are homozygous, face substantially higher risk of severe ARIA. Symptomatic treatments remain more widely used. Cholinesterase inhibitors like donepezil, rivastigmine, and galantamine are prescribed for mild to moderate stages. Memantine is used in moderate to severe cases and works through glutamate modulation. These medications do not alter disease progression. They may provide modest improvement or stabilization in daily functioning for six to twelve months on average. Side effects including nausea, diarrhea, bradycardia, and vivid dreams are common enough that discontinuation rates approach thirty percent in some studies. Non-pharmacological interventions carry more weight than most patients realize. Regular aerobic exercise has the strongest evidence base for slowing cognitive decline in early stages. Sleep quality directly affects amyloid clearance through the glymphatic system, which operates primarily during deep sleep. Managing cardiovascular risk factors, particularly hypertension and diabetes, reduces the rate of additional brain injury. Social engagement and structured cognitive activities provide measurable benefits for quality of life even if they do not change the disease course.
What The Data Shows About Prognosis
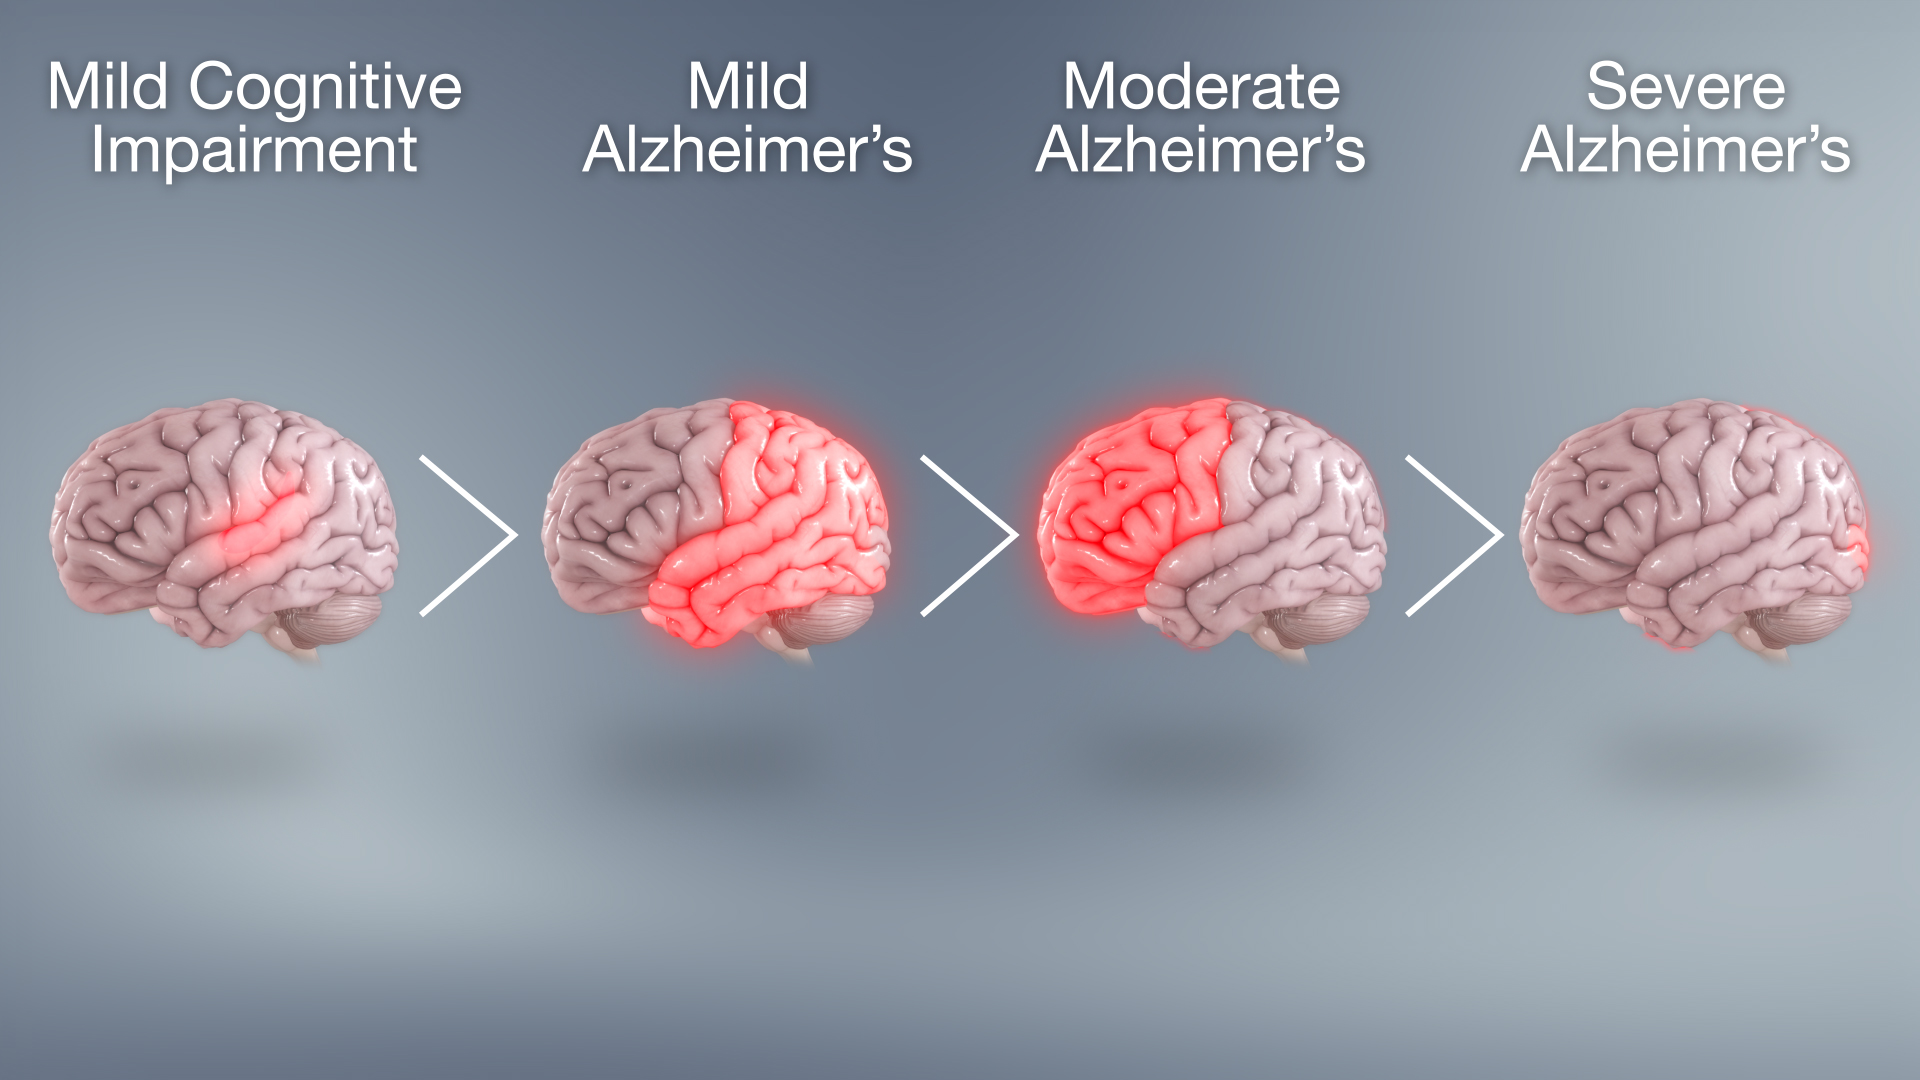
After diagnosis, the average survival is eight to ten years, but the range is extremely wide. Some people live twenty years or more. The trajectory depends on age at onset, the presence of other neurological conditions like vascular dementia or Lewy body disease, and the overall health of the patient. Frailty, recurrent infections, and difficulty swallowing are the most common terminal events. Weight loss and aspiration pneumonia mark the late stage of the disease. One counter-intuitive finding is that the rate of decline is not steady. Cognitive function tends to plateau for extended periods followed by sudden drops, often triggered by a minor infection, medication change, or hospitalization. Families frequently describe this as their loved one being stable for months then deteriorating rapidly after a urinary tract infection. This pattern makes long-term planning difficult but it is well documented. Anticipating these triggers and managing them proactively can preserve function longer than expected. The financial and emotional burden on caregivers is another dimension that the medical literature does not always capture adequately. Full-time caregiving for someone with moderate to severe Alzheimer's typically requires twenty to thirty-five hours per week. Caregiver depression and burnout rates exceed forty percent within the first two years. Respite care programs, adult day centers, and home health support reduce caregiver strain measurably, but access varies dramatically by location and insurance coverage. Medicare covers limited skilled nursing and home health services but does not cover custodial care, which is where the greatest financial exposure occurs.
I saw a caregiver in her forties bring her mother to our clinic after seventeen months of unstructured home care. She was exhausted, had lost her job, and was considering placement. We arranged a combination of adult day programming three days per week, home health assistance for personal care, and a structured respite schedule for weekends. Within four months her mother showed improved engagement and the caregiver reported feeling sustainable again. The exact change was not a medical improvement. It was the difference between collapse and continuation, which is something the statistics do not capture but families experience directly. Research funding for Alzheimer's has increased substantially in recent years, driven in part by the success of the anti-amyloid antibodies and growing public awareness. Multiple clinical trials are testing interventions targeting tau, neuroinflammation, and metabolic pathways. Genetic research has identified several risk variants beyond ApoE4, including TREM2 and BIN1, which point toward immune-mediated mechanisms. The field is moving toward combination therapies, which may be necessary because Alzheimer's is unlikely to be controlled by any single mechanism. The hard truth is that we are still in the early phases of understanding this disease. Diagnosis is better than it was ten years ago. Treatment options are real but narrow. Daily management requires constant adaptation. The problem remains enormous, and the gaps in care are large. What works best is a combination of early recognition, comprehensive workup, realistic expectation setting, and sustained support for both the patient and the people around them.