Running Through The Secondary Assessment Without Losing Your Mind
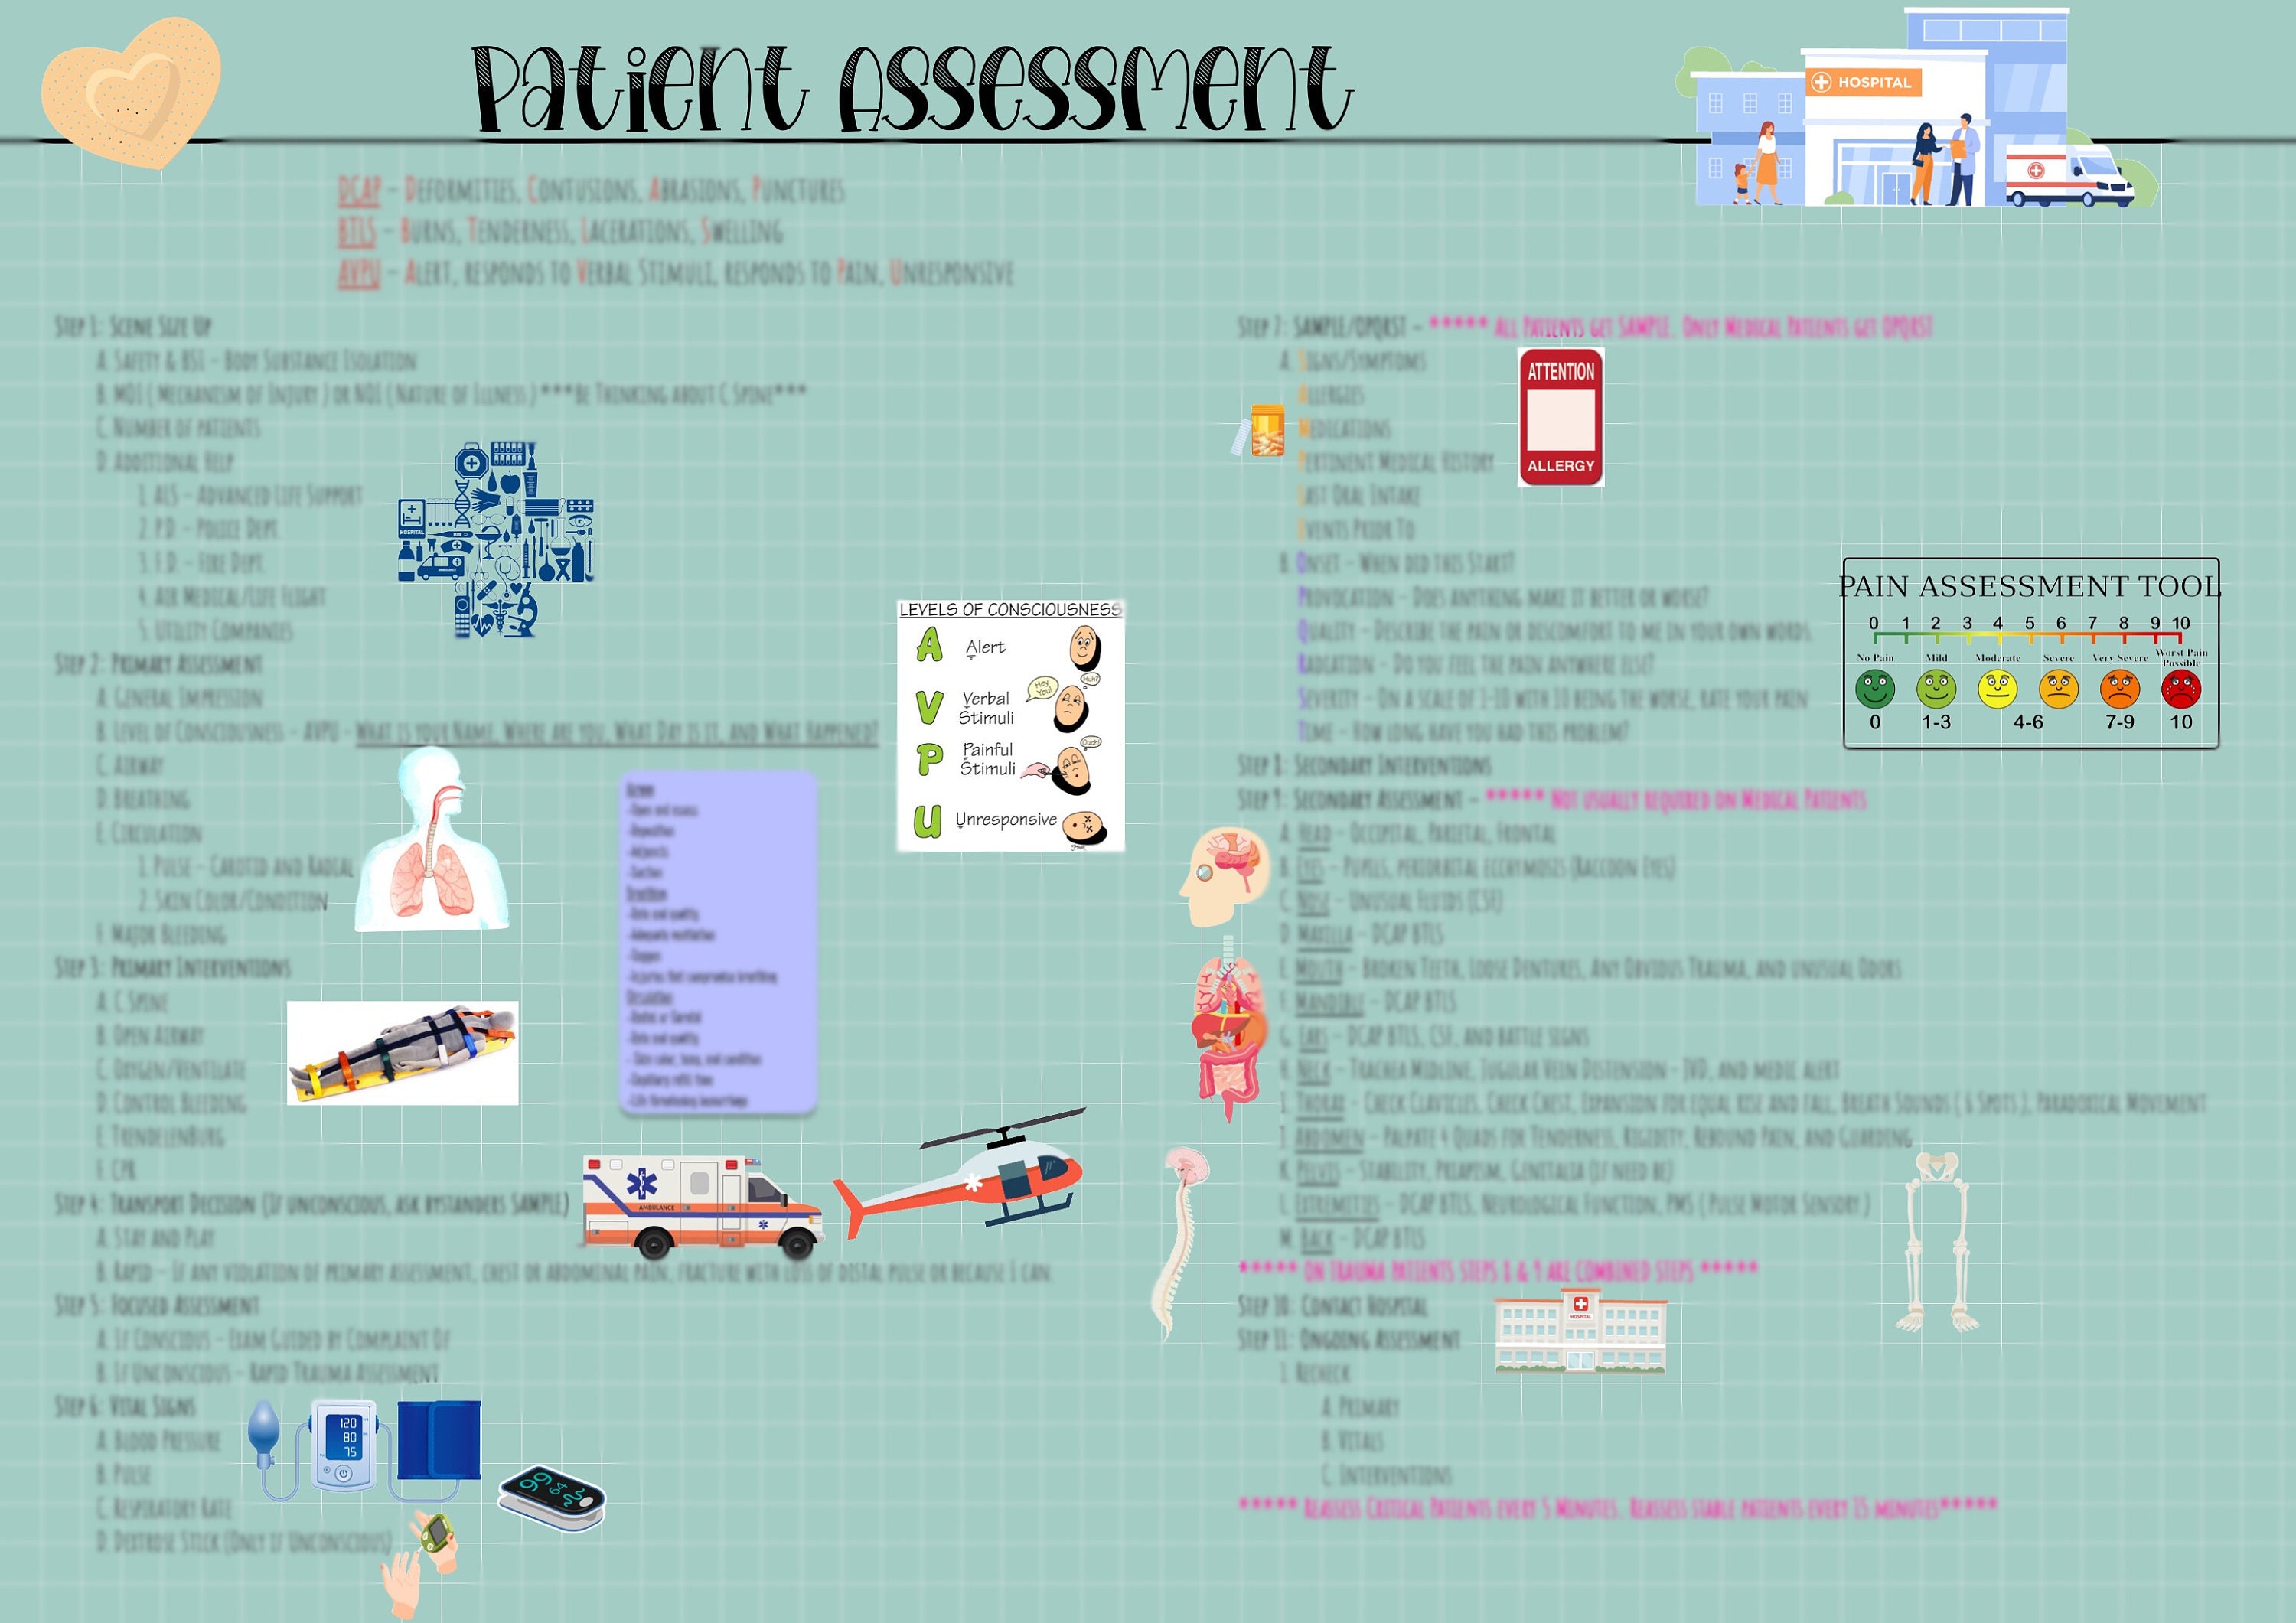
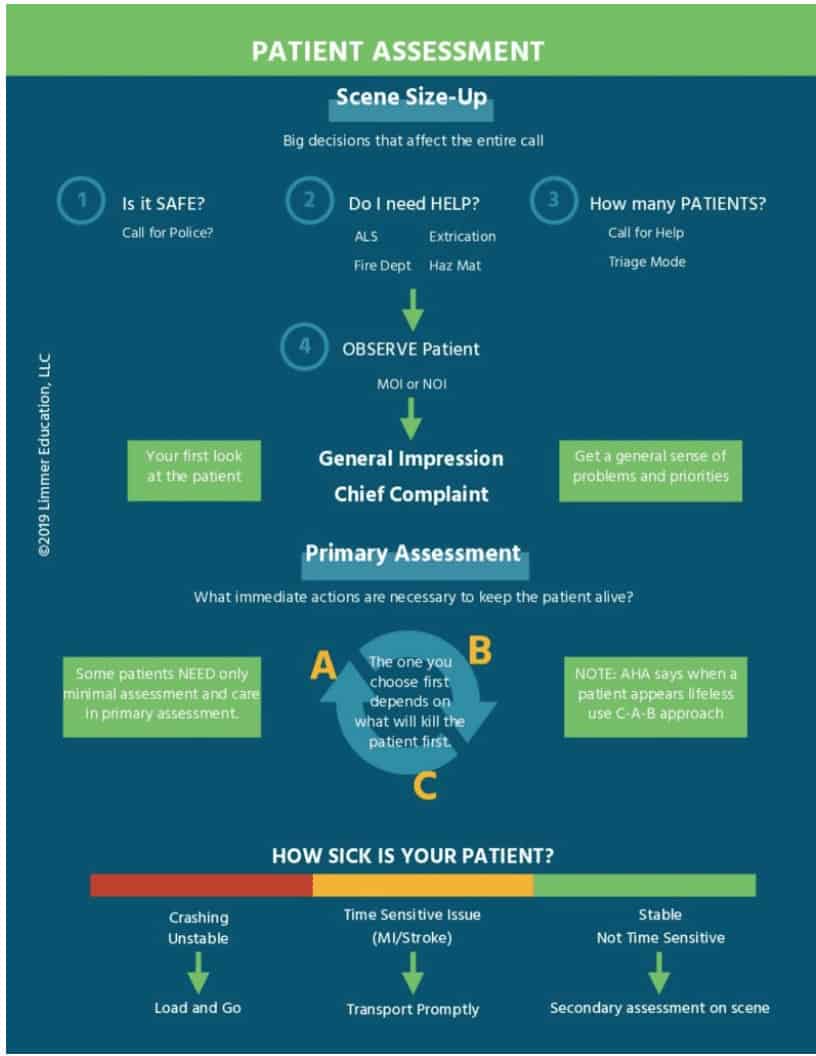
The secondary assessment is where most EMTs screw up because they treat it like a checklist instead of a tool. You finish the primary, the patient is stable enough for you to take your time, and now you're doing a head-to-toe exam while your partner is calling ahead. That's when things go sideways. I've seen it happen way too many times where a missed pelvic fracture or a depressed skull fracture gets overlooked because someone was focused on filling out paperwork instead of actually looking at the patient. Here's how it actually works in practice. You're standing over a 67-year-old female who fell in her kitchen. She's alert, breathing fine, pulses are good. Now you move into the secondary. Start with the SAMPLE history because getting the timeline right changes everything. When did she last eat? What medications is she on? This isn't fluff — last Tuesday her endocrinologist adjusted her insulin and she's been having hypoglycemic episodes. Without that detail, you're just treating numbers instead of the person. Then you do the physical exam. Head to toe, anterior and posterior if you can get them flipped safely. Palpate the head for depressions, listen to lung sounds on both sides, check pulses distal to any suspected injury. But here's what nobody tells you in basic class: medical patients often don't present with obvious trauma, so your exam needs to be more thorough, not less. A patient complaining of "indigestion" might be having an inferior wall MI. That means checking the precordium, listening for murmurs, and not just assuming it's gastric until you've ruled out cardiac. I learned that the hard way on a call where the patient was laughing about heartburn while his EKG was showing ST elevations.
The re-assessment piece is where people get lazy. You're told to re-check vitals every fifteen minutes for stable patients, every five for unstable ones. But the real value isn't in the numbers — it's in the trend. A blood pressure that's dropping from 110 over 70 to 102 over 68 over thirty minutes tells you something is wrong even though both readings look "normal" in isolation. I once watched a rookie miss a deteriorating patient because he kept saying "vitals are within normal limits" without actually comparing them to baseline. Don't do that. Documentation is another area where efficiency matters. Write as you go if you can. If your service uses electronic PCR, type while your partner is prepping for transport. I've found that grouping findings by system — cardiopulmonary, neuro, musculoskeletal — keeps me from repeating myself and makes it easier for the receiving nurse to parse quickly. They get enough garbage to deal with without hunting through your notes. One edge case that catches people off guard: altered mental status in medical patients. You'll run your assessment and find nothing outwardly wrong. No trauma, clear lungs, regular heart rhythm. The patient's confused, maybe agitated. Your instinct is to check glucose and move on. But I've encountered situations where the glucose was normal and the real issue was a stroke or intracranial bleed that wasn't showing on initial exam. The workaround I use is to keep reassessing neurological status throughout the entire secondary exam, not just at the start. Document the Glasgow Coma Scale, check pupil reaction, ask the patient to smile and raise both arms. If anything is asymmetric or declining, you escalate accordingly. I had a patient once who seemed fine on initial neuro check but was clearly slurring and drifting over ten minutes. CT showed a subdural hematoma. Missing that would have been catastrophic.
Another counter-intuitive thing about secondary assessments for medical patients: the history often matters more than the physical exam. For trauma, you're hunting for injuries. For medical, you're hunting for patterns. Onset, provocation, quality, radiation, severity, time — each element narrows the differential. A patient with crushing chest pain radiating to the left jaw at rest versus one with sharp pleuritic pain that worsens with deep breaths are heading to completely different places in your management. There are limitations to this approach, obviously. In low-staffed systems where you're the only one on scene, doing a full secondary takes time you might not have if transport is twenty minutes away. You have to triage what's important. If a patient is tachycardic and diaphoretic, spend more time on cardiac and less on a thorough musculoskeletal survey. And some patients won't cooperate — the agitated dementia patient, the intoxicated trauma cocktail, the non-English speaking patient without an interpreter. In those cases, you adapt. Grab what you can, note the limitations in your report, and let the receiving facility know what you couldn't assess. Also worth noting: the secondary assessment is not a substitute for good judgment. If something feels wrong, keep reassessing. The textbook says what to do, but real patients rarely read the book. I've had secondary assessments come back completely negative on patients who turned out to be septic, and I've had patients with alarming vitals whose workup was completely benign. Trust your eyes and your gut more than any single data point.
Get the Full Details
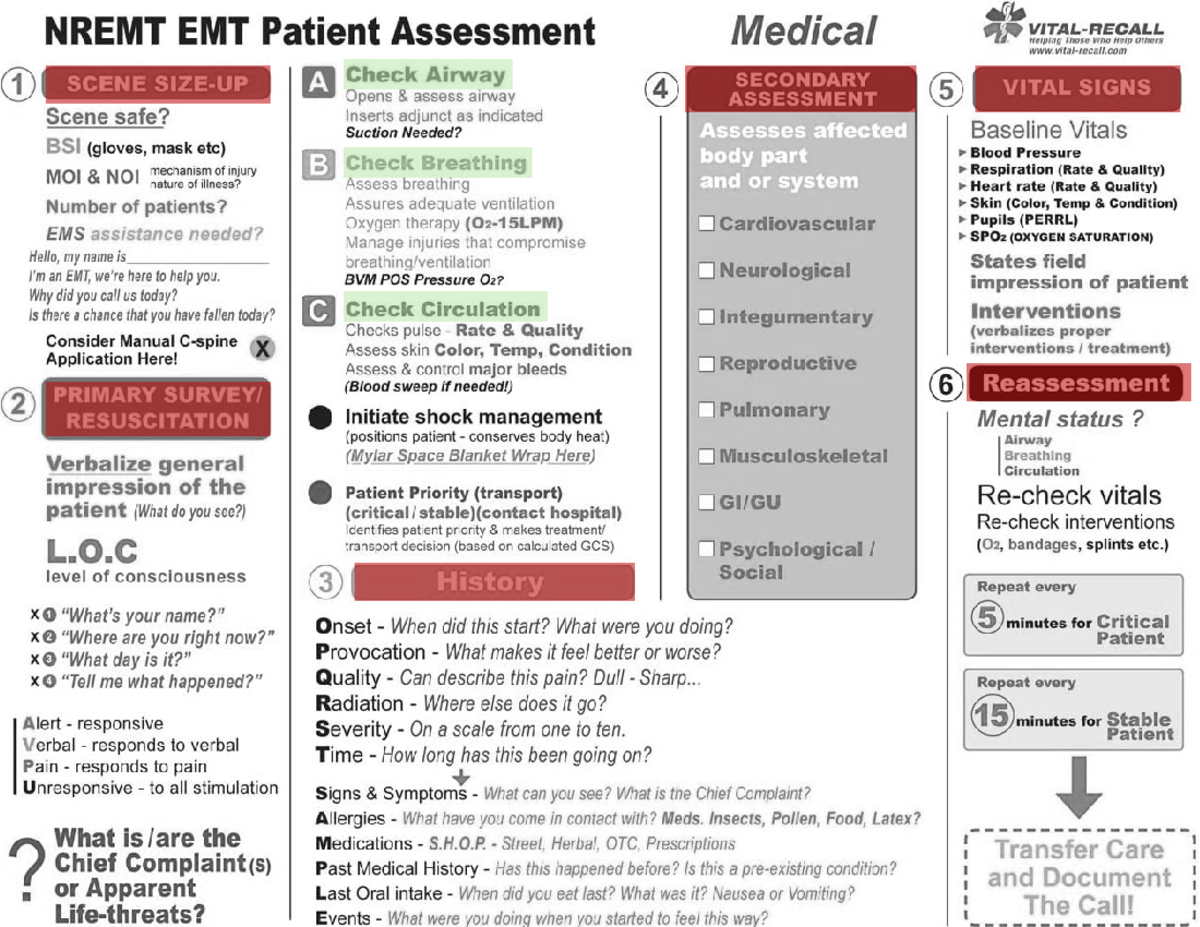
If you want a reference guide, most state protocols and the NREMT skill sheets cover this in detail. I keep a laminated card in my pocket with the key steps because muscle memory helps when everything is happening at once. Practice the sequence until you don't have to think about it anymore, then you can focus on the patient instead of the process.