Why Cardiac Sectional Imaging Is Actually Useful
Most people think of heart imaging as just looking at a scan and saying "looks fine" or "that's a blockage." The reality is much more methodical. You are working through defined anatomical planes, checking structures systematically, and cross-referencing findings across multiple views. Without sectional anatomy, you are guessing. I remember early in my residency doing echo readings where I would spot something odd on a single view and immediately flag it as pathology. Then someone would ask for a different plane, and the "abnormality" vanished because it was an artifact of beam angle or a normal variant seen from the wrong perspective. That was the day I started actually learning The Sectional Anatomy Of The Heart instead of just memorizing what things should look like on one slice.
What The Sectional Anatomy Of The Heart Actually Means
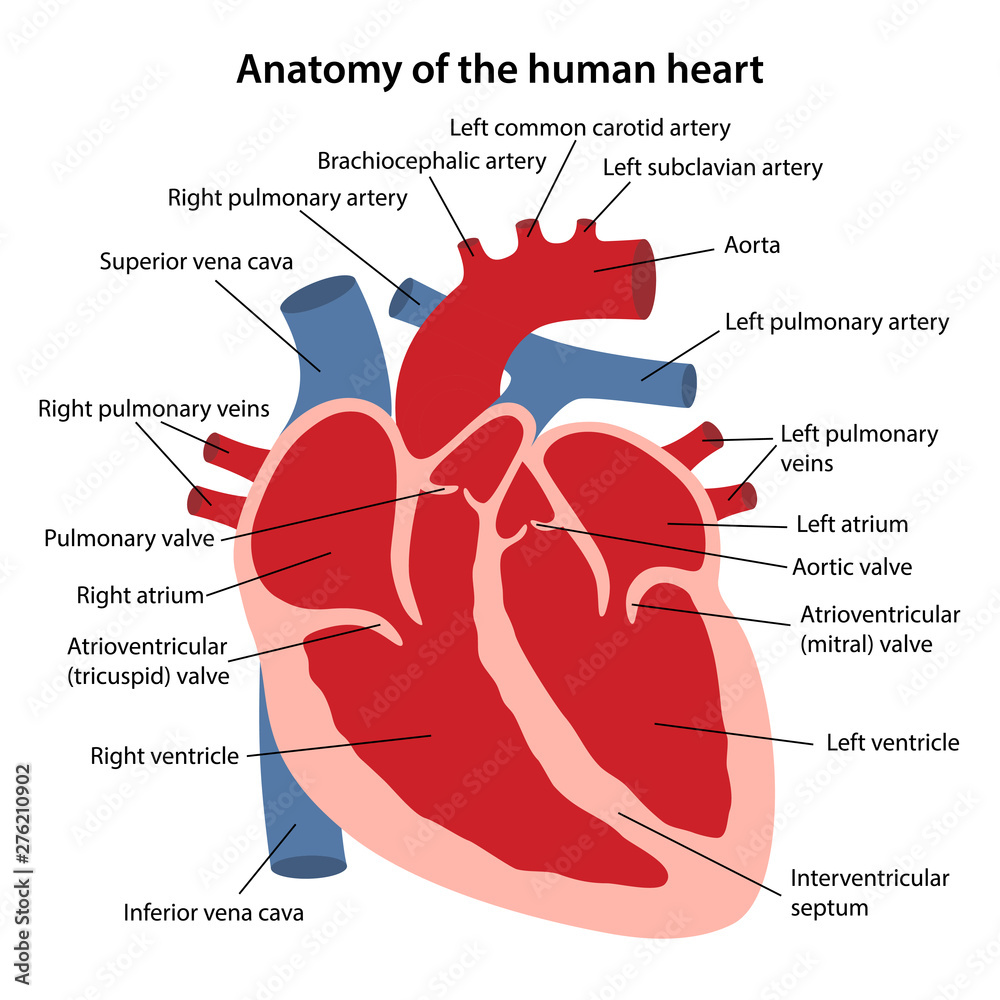
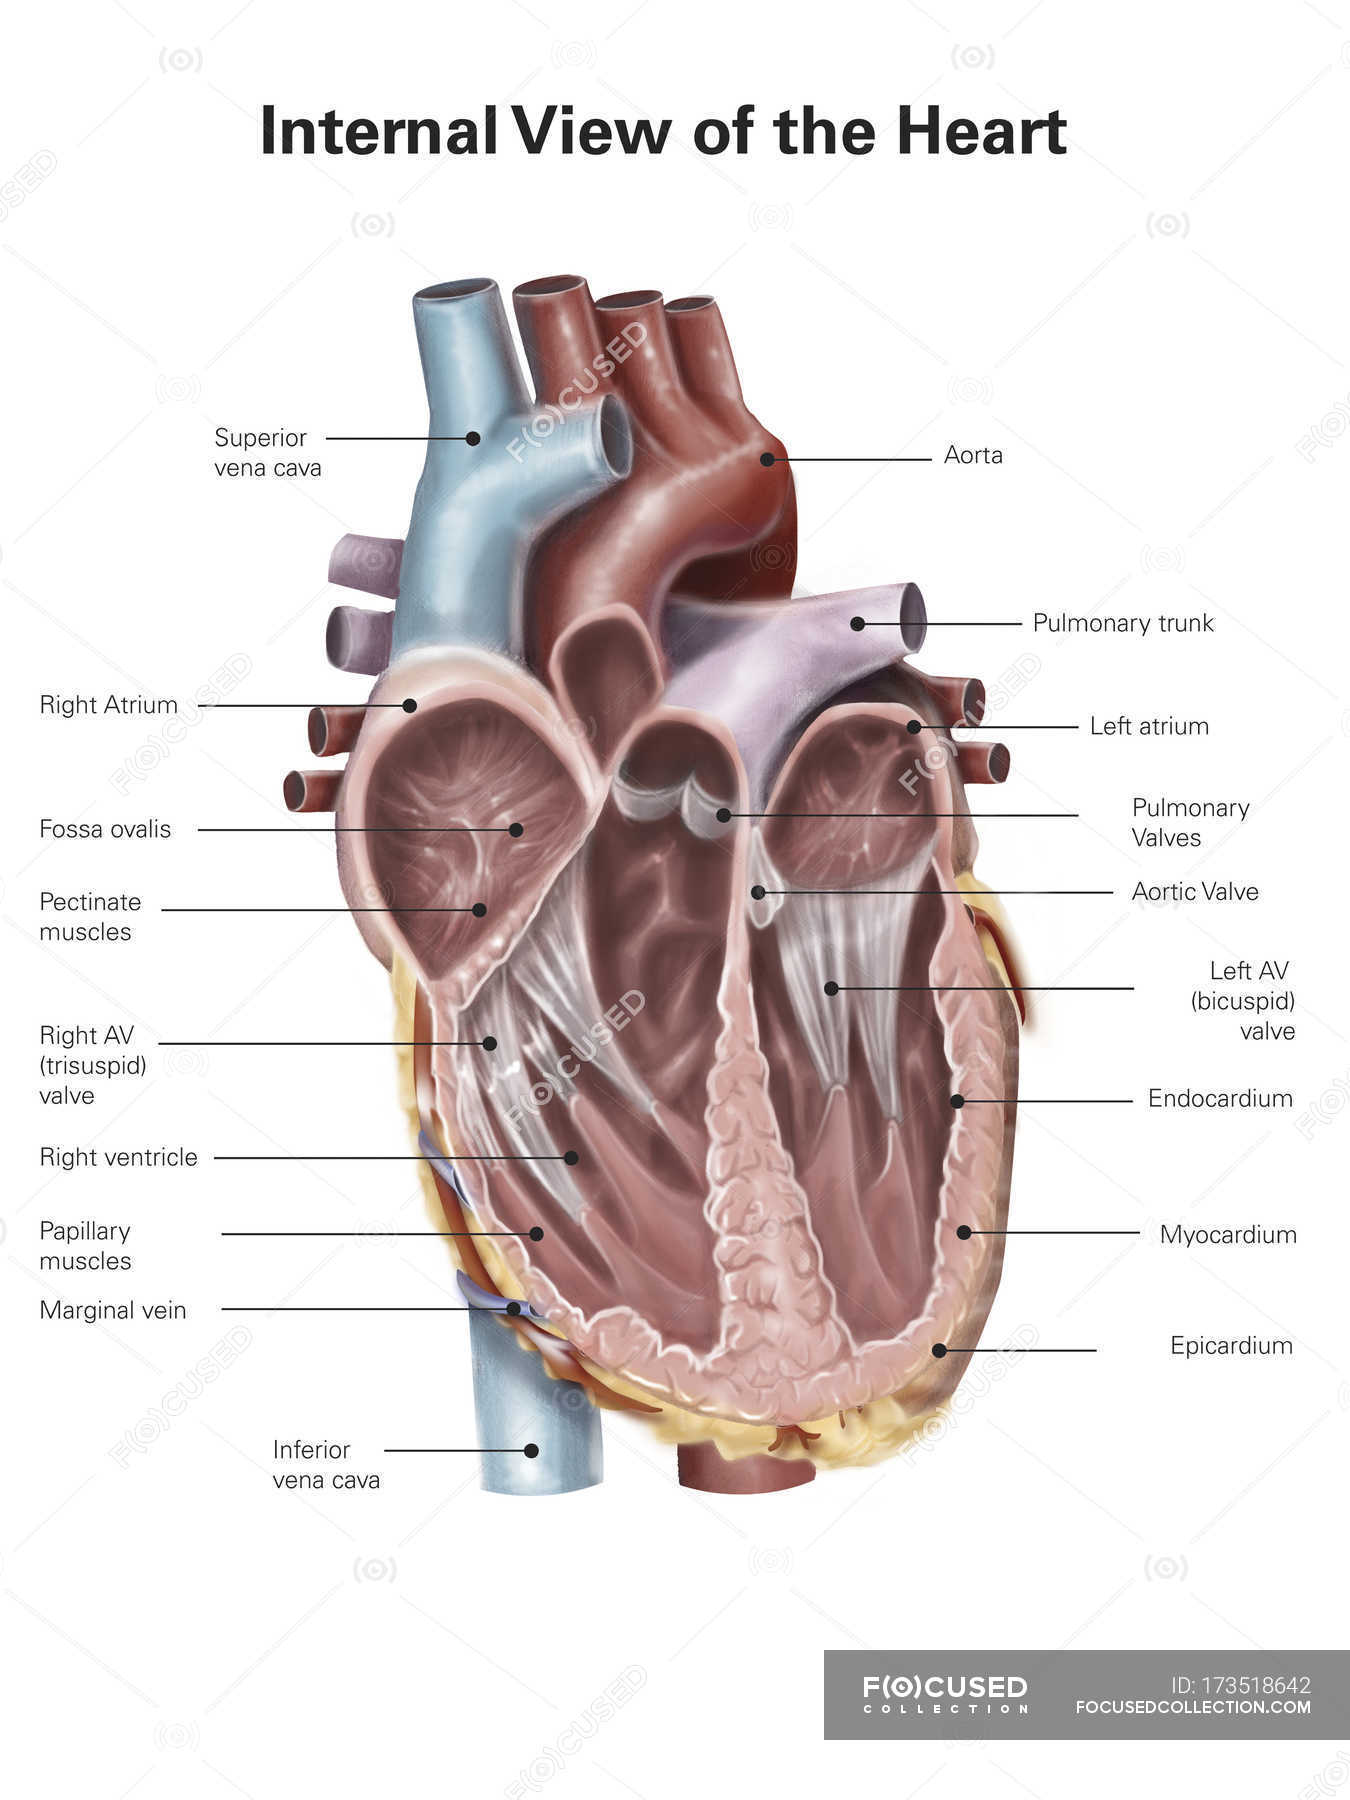
Cardiac sectional anatomy refers to the organized study of heart structures as they appear in specific imaging planes. This applies across echocardiography, CT, and MRI. Each modality uses slightly different conventions, but the underlying principle is the same: the heart is a three-dimensional structure, and you need multiple two-dimensional slices to understand it accurately. The standard planes are parasternal long axis, parasternal short axis, apical four-chamber, apical two-chamber, and apical three-chamber. That last one is also called the left ventricular outflow tract view. Beginners often skip the apical three-chamber because it requires a bit more probe manipulation. That is a mistake. It is the single most important view for assessing the aortic valve and mitral valve simultaneously.
How The Standard Views Map To Real Anatomy
Here is what each plane actually shows, and more importantly, what it misses. Parasternal long axis: This gives you the left ventricle from base to apex, the left atrium, the mitral valve, the aortic valve, and the right ventricular outflow tract. You get a good look at LV wall thickness and chamber size. What you do not get is a complete picture of the lateral or inferior walls. Those are better assessed in short axis. Parasternal short axis: This is the cross-sectional view. You rotate the probe 90 degrees and slice the heart like a loaf of bread. At the mitral valve level, you see the anterior and posterior leaflets. At the mid-ventricular level, you assess regional wall motion and wall thickness around the entire circumference. At the apex, you confirm there is no apical thrombus. This view is where most regional wall motion abnormalities are caught during stress echoes.
Get the Full Details

Apical four-chamber: Both ventricles, both atria, and both AV valves are visible. This is your workhorse view for overall systolic function. The problem is that the true apex is often foreshortened. If you do not pull the probe slightly laterally and cephalad, you are imaging a mid-cavity slice, not the apex. I have lost count of the times I called a normal exam, only to have a follow-up show apical hypokinesis that was missed because the true apex was out of frame. Apical two-chamber: This isolates the anterior and inferior walls of the left ventricle. It is essential for ruling out anterior wall disease when the four-chamber view is ambiguous. Skip it and you are flying blind on the LAD territory. Apical three-chamber: This is where the LVOT, aortic valve, and mitral valve are all in one plane. It is critical for quantifying aortic stenosis and detecting mitral valve systolic anterior motion. Most trainees struggle with obtaining this view consistently. Practice it until you can get it on the first attempt every time.
A Case Where The Textbook Failed Me
Years ago I was reading a pediatric echo for a patient with a murmur. The standard four-chamber and short axis views looked completely normal. The radiologist on call said "no structural abnormality." I kept looking. There was a subtle brightness near the aortic root on the parasternal long axis that did not match anything in the textbook. I repositioned the probe, got a better subcostal view, and found a small ventricular septal defect just below the aortic valve — a perimembranous VSD that was completely hidden on the standard apical views because of the beam angle. The lesson was simple: normal standard views do not mean normal heart. When something feels off clinically but the images look fine, change the window. Go to subcostal, go to suprasternal, adjust the depth and gain. The defect was there the whole time. I was just looking at it from the wrong angle.
CT And MRI Sections — Different Rules
If you are working in cardiac CT or MRI, the plane conventions shift slightly. Short axis is still the gold standard for LV function. You acquire contiguous slices from the base of the mitral valve to the apex. The challenge here is breath-holding. Even a 5-second movement between breath-holds can create a misregistration artifact that looks like a perfusion defect. I have seen this happen repeatedly in patients who cannot hold their breath for more than 10 seconds due to COPD or deconditioning. The workaround is retrospective gating with respiratory compensation, or simply accepting that some patients need a repeat scan. There is no way around physics. A moving heart in a stationary slice is always going to blur.

Pitfalls That Will Cost You Points On Exams And In Practice
Beveling artifact on the mitral valve is the most common source of false-positive regurgitation calls. The ultrasound beam hits the valve leaflet at an angle, creating a artificial gap that looks like a leak. Rotate the probe slightly and reassess. If the gap disappears, it was beveling. If it stays, you have real pathology. Another frequent error is failing to recognize the interatrial septum correctly. The fossa ovalis is naturally thinner and can bulge into the left atrium, mimicking an atrial septal defect on certain views. Use agitated saline contrast. If the bubbles cross, it is a defect. If they do not, it is just a prominent fossa. I wasted an entire afternoon chasing a "shunt" that turned out to be a normal septal anatomy variant. The bubble study saved me from ordering an unnecessary transesophageal echo.
What This Method Cannot Do
Sectional imaging has hard limits. You cannot adequately visualize the distal left anterior descending artery or the posterior descending artery with transthoracic echo. You cannot reliably quantify coronary artery disease without CT or catheterization. You cannot image the heart in patients with severe lung disease or obesity and expect diagnostic-quality slices. These are not weaknesses of your technique. They are limitations of the modality itself. In those cases, the correct answer is to move to a different imaging pathway. Do not push a suboptimal echo and call it diagnostic. That is how missed diagnoses happen. I once saw a colleague call a normal echo on a obese patient with classic angina. Two weeks later, that patient had a large anterior MI. The echo was technically normal. The coronary disease was never visible. That case changed how I approach difficult bodies: when the windows are poor, I recommend CT angiography or stress MRI upfront instead of wasting time on inadequate transthoracic studies.