How The ASAM Criteria Actually Work In Practice
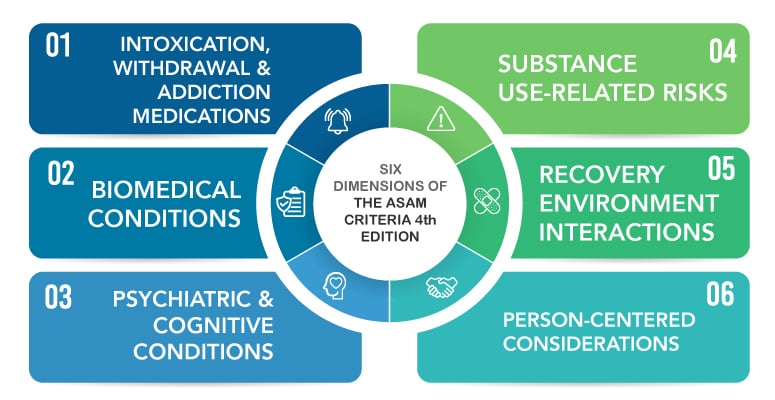
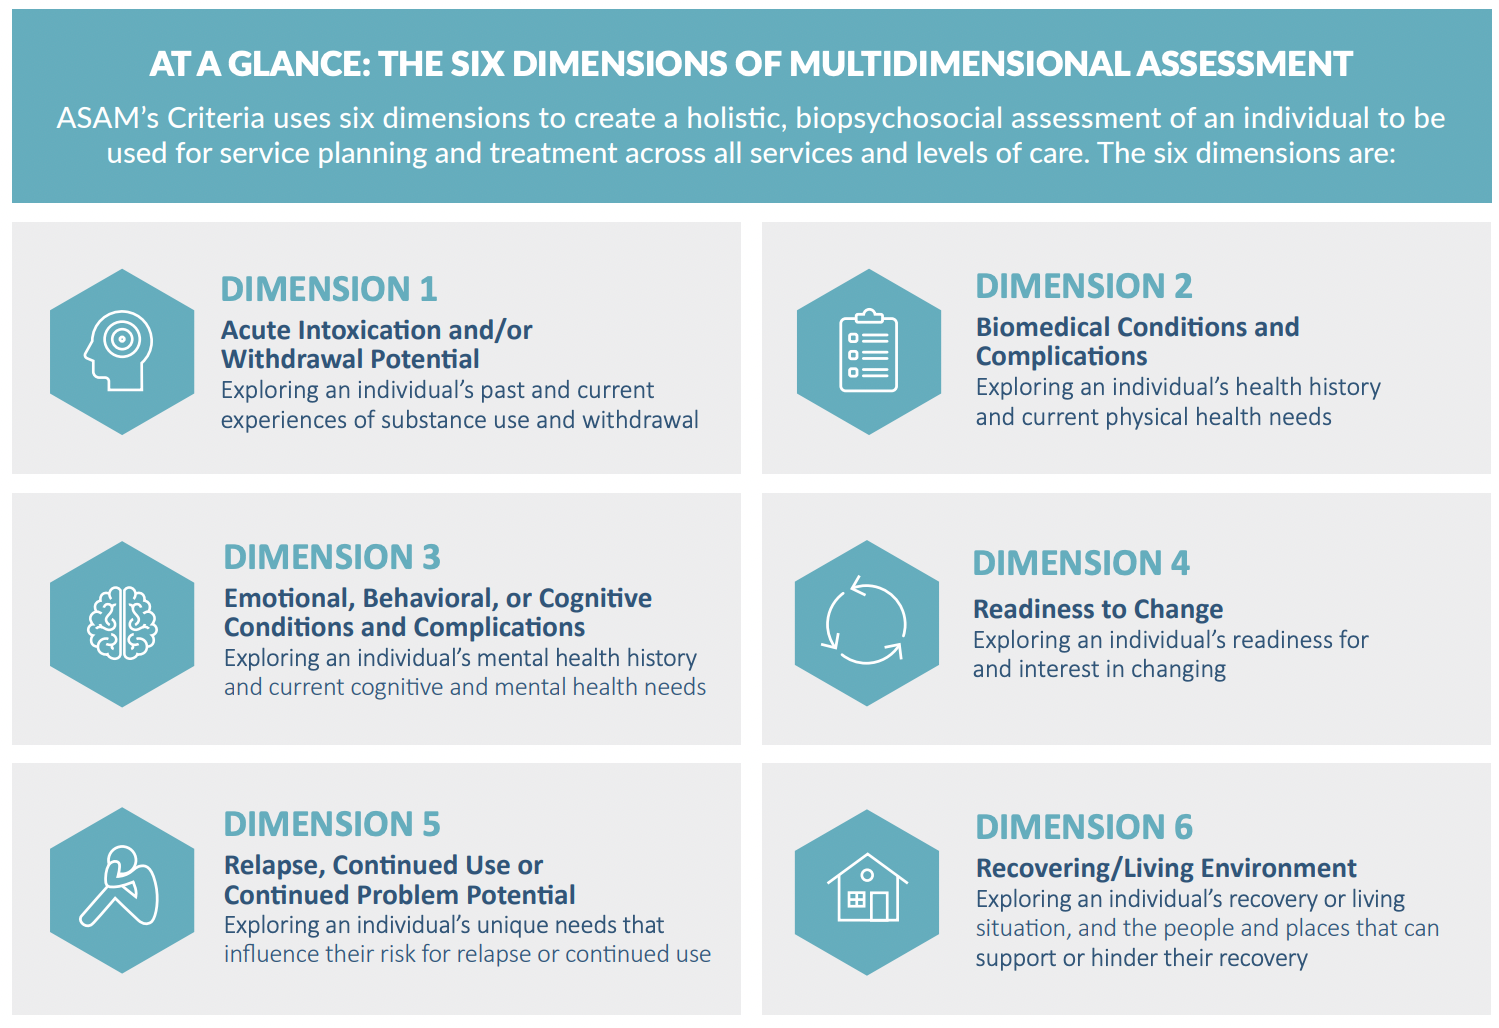
I have used the ASAM Placement Criteria more times than I care to count across a dozen different treatment settings. The framework itself is straightforward on paper, but getting it right on a real patient—especially under time pressure or when you're not sure what the next level of care should be—is where things get messy. I am going to walk through the six dimensions as I actually use them, including the part where people routinely mess up dimension four. The ASAM Criteria are organized around six assessment dimensions that you work through in sequence. They were originally published by the American Society of Addiction Medicine to standardize where someone with a substance use disorder should be placed in the continuum of care. Here is what each dimension looks like when you are filling out the form on a live case. Dimension 1: Acute Intoxication and/or Withdrawal Potential. This is the gatekeeper dimension. If a patient is currently intoxicated, in active withdrawal, or at significant risk of seizures or delirium tremens, everything else gets paused until they are medically stable. The question here is not whether withdrawal is possible—it is about likelihood and severity. I have seen cases where a patient was cleared for residential placement and then went into seizures 48 hours later because the assessor checked "low risk" based solely on a urine screen and a vague history of prior detoxs. Always pull the CAGE-AID or at least a thorough timeline of past withdrawals. Severity of prior withdrawal matters more than frequency.
Dimension 2: Biomedical Conditions and Complications. This covers any co-occurring medical issues—liver disease, cardiovascular problems, uncontrolled diabetes, pregnancy, chronic pain—that interact with substance use or complicate treatment. The trick here is knowing which conditions actually change placement level. A well-managed hypertensive patient does not need a higher level of care. Uncontrolled hepatitis C with active IV drug use is a different conversation. Document the interaction, not just the diagnosis. I once argued successfully for moving a patient from IOP to a higher medical monitoring level because their opioid use was causing repeated falls due to an underlying vestibular disorder that the facility had not assessed. They had only documented the vestibular issue, not the interaction with substances. Dimension 3: Emotional/Behavioral Conditions and Complications. This is where most assessors get stuck because the language is broad. It includes co-occurring psychiatric disorders, suicide risk, acute stress reactions, and cognitive impairments. The key distinction is whether the psychiatric condition is stable enough to participate in treatment at the proposed level, or whether it needs to be addressed first. Severe untreated bipolar disorder is not compatible with standard IOP. A stable, medicated PTSD patient is fine in IOP. I spent three years arguing with insurance reviewers who wanted to put suicidal patients in outpatient because they were "stable on medication." Suicidality is not a static condition. Always assess current risk, not just historical risk. Use a tool like the Columbia-Suicide Severity Rating Scale and document the date of the last assessment. Most reviewers accept a C-SSRS score within 30 days. Dimension 4: Readiness to Change. This is the dimension that causes the most disputes between assessors and insurance companies, and honestly, the one that is hardest to get right. The ASAM framework ties placement level to the patient's stage of change—precontemplation, contemplation, preparation, action, maintenance. A patient in precontemplation should not be placed in residential if they are not ready for that level of engagement, because they will likely leave against medical advice. The problem is that "readiness" is often confused with compliance. A patient who says yes to everything is not necessarily ready for change. I had a case where a patient was placed in residential because they verbally agreed to sobriety, but by week three they were caught using on property. The readiness assessment should have flagged the mismatch between their stated motivation and their actual behavior pattern. Look at what they have done over the past six months, not what they say today. That said, readiness can shift rapidly in treatment, which is why reassessment every 30 days is built into the criteria.
Dimension 5: Relapse, Continued Use, or Continued Problem Potential. This dimension evaluates whether the patient's substance use is likely to return or escalate at the proposed level of care. It looks at frequency, severity, and chronicity of use, plus any history of relapse after previous treatment. A single relapse after long abstinence is not the same as a cycle of use-treatment-use-treatment that spans a decade. The nuance here is that high relapse potential does not automatically mean higher level of care. Sometimes it means a different type of care—like continuing in a lower level but with more intensive aftercare planning. I learned this the hard way when I pushed a patient into residential based purely on a long history of relapse, only to realize they were actually doing well in a lower level of care with a solid sober living plan. The relapse history was from years before they had moved back into their hometown and re-established support networks. Context matters more than the raw number of prior treatment episodes. Dimension 6: Recovery/Living Environment. The final dimension looks at the patient's environment—housing stability, family dynamics, social support, exposure to substances, and access to recovery resources. A patient who is medically stable but living in a house where everyone is using heroin is not safe in outpatient. A patient who is chaotic but has a supportive family member offering sober housing might be fine in IOP. The dimension is designed to catch environmental triggers that would undermine treatment at any level. I had a case where the living environment was the sole reason a patient needed a higher level of care despite otherwise low scores across dimensions one through five. Their "home" was a shelter where staff turned a blind eye to fentanyl use. Sending them back there from IOP was essentially sending them back to the addiction. Document the environment, not just the address. The full criteria document is available from the ASAM website and has been adopted as a standard in most U.S. states and by Medicare. The most recent version is the third edition, published in 2013 with updates through 2024. Training materials and the official scoring forms are available through the ASAM membership portal at asam.org. Most states also require ASAM-based assessment for Medicaid reimbursement, so if you are working in publicly funded treatment, you will be using this regardless of your personal preference.
Get the Full Details
The biggest practical issue I run into is the tension between the criteria and insurance authorization. The ASAM Criteria are designed to guide clinical placement decisions. Insurance companies use them to justify denials. Dimension 4 in particular becomes a battleground because "readiness to change" is subjective enough that two assessors can reach opposite conclusions on the same patient. My workaround has been to anchor every subjective dimension to observable behavior—treatment attendance records, toxicology results, self-report consistency, family collateral—so that the assessment is defensible rather than purely clinical opinion. It takes longer to document but it survives a peer review. Another thing the formal training materials do not emphasize enough is that the dimensions are not scored independently and then averaged. They are meant to be integrated. A patient who scores low on every dimension except dimension six (dangerous living environment) may still need a higher level of care than their aggregate score suggests. The criteria allow for cross-dimensional overrides, but they are underused in practice. I have recommended residential placements based primarily on dimension six alone, and I have recommended outpatient for patients who looked like they needed a higher level based on dimensions one through five. The system works when you actually read the whole thing.