Group Therapy Models: What Actually Works In Practice
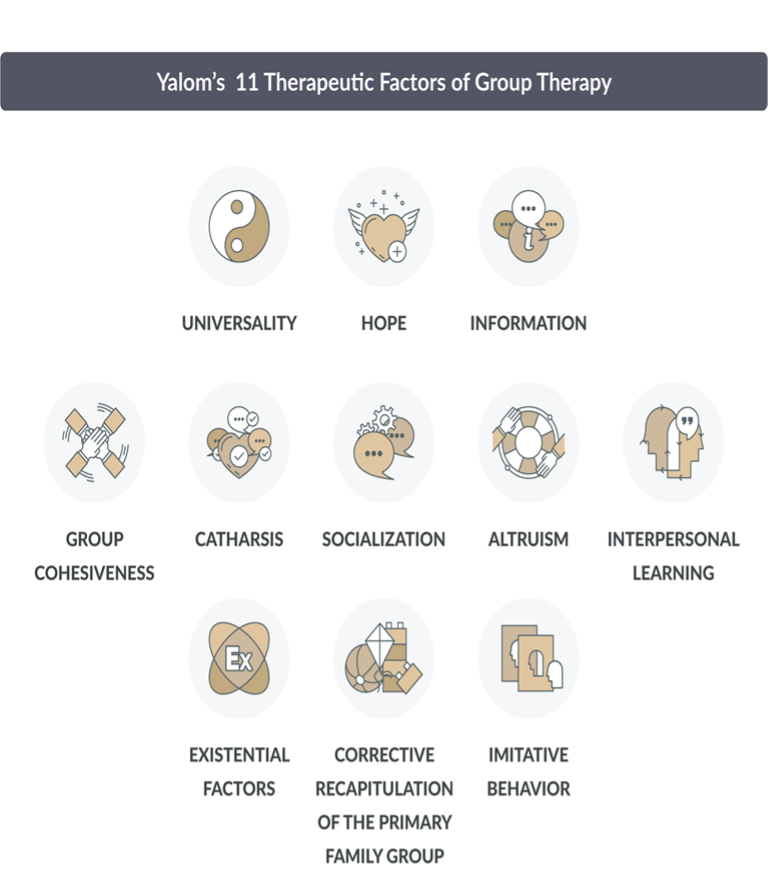
Group therapy isn't one thing. It's a collection of frameworks that grew out of different traditions, and most practitioners end up borrowing from several of them without really thinking about it. If you're trying to run a group and you just pick something at random, people will notice within three sessions. The group's energy will go sideways and you'll be scrambling to figure out why. I spent years running outpatient groups for anxiety and depression before I really understood what was happening under the surface. The first model most people learn is Yalom's therapeutic factors framework. It's not technically a treatment model in the same way CBT or psychodynamic therapy are, but it's the default operating system for almost every group therapist alive. You set up a group, you observe what happens, and you name the mechanisms. Yalom identified eleven of them: instillation of hope, universality, imparting information, altruism, corrective recapitulation of the primary family group, development of socializing techniques, imitative behavior, interpersonal learning, group cohesion, catharsis, and existential factors. The framework works because it's descriptive rather than prescriptive. It tells you what's happening instead of telling you what to do about it.
The Theories Of Group Therapy
Psychodynamic group therapy comes out of object relations and self psychology. The group becomes a replay space where members unconsciously reenact early relational patterns. The therapist's job is to interpret those patterns as they emerge in here-and-now interactions. It's slow work. A typical psychodynamic group runs for eighteen to twenty-four months and meets weekly for two hours. You're not going to see dramatic shifts in the first six months. People are polishing their defenses and testing whether you'll hold. CBT-based group therapy is structurally different. It's psychoeducational, skills-based, and deliberately present-focused. Each session has an agenda. Members learn cognitive restructuring, behavioral activation, exposure techniques, or social skills depending on the diagnosis. A standard protocol for social anxiety group, for example, runs ten to twelve weeks with one 90-minute session per week. The homework compliance rate is usually between 40 and 60 percent, which means a quarter or third of your group isn't doing the work between sessions. That matters more than you'd think. Process-experiential group therapy draws from Emotion-Focused Therapy and Gestalt approaches. The emphasis is on awareness, emotional processing, and enactment. Members are encouraged to speak directly to each other rather than through the therapist. It feels riskier in practice than it does on paper. A lot of therapists who swear by this model in training get nervous when someone actually says something raw to another member in real time and the room goes quiet.
Interpersonal group therapy was adapted from Klerman and Weissman's individual model. It focuses on current relationship patterns and uses the group as a microcosm of the member's social world. The therapist helps the person see how they show up in relationships and then experiments with different behaviors in the safety of the group. It's particularly effective for depression and personality disorder features. Transactional analysis group therapy uses the ego state model—Parent, Adult, Child—as its organizing framework. Members identify which ego state they're operating from and how they're interacting with others. It's more structured than pure process work but less standardized than CBT. I've found it useful with clients who respond well to clear models and concrete language about their own behavior. Here's something nobody tells you in training: cohesion is not the same as harmony. A group that gets along perfectly and never challenges each other is usually avoiding conflict, not building rapport. The groups that actually produce change are the ones where members push back, get irritated, and work through it. I ran a grief group once where two members had a genuine falling out in session eight. One said the other was "performing" their sadness for attention. The group split into factions. I wanted to intervene and smooth it over, but I didn't. We spent the next four sessions working through it. That was the most therapeutic part of the entire group. People learned they could survive disagreement without the group falling apart. You can't schedule that. It has to be allowed to happen.
Get the Full Details
Mixed-model groups are the reality for most practitioners. You'll have someone who needs the structure of CBT, someone who responds to insight-oriented work, and someone who just needs to feel less alone. The trick is picking a primary framework and letting the secondary elements serve it. If you're running a CBT group for panic disorder, for instance, you can use Yalom's universality factor explicitly by having members share their symptoms and normalize each other's experiences. That's not mixing models. That's using the research on what makes groups work inside a defined treatment structure. One counter-intuitive thing about group composition: homogeneity helps you start, but heterogeneity keeps the group interesting. If you put six people with the same diagnosis in a room, the first three sessions fly by because everyone relates immediately. By session six, you've exhausted the shared material and there's nothing left to explore. A group with mixed diagnoses but a common theme—say, difficulty with intimacy across different conditions—tends to have more sustained depth. The caveat is that too much heterogeneity early on can make it hard for members to feel understood. That's why most structured protocols stick with diagnostic homogeneity while process-oriented groups lean toward thematic grouping. The dropout problem is real and mostly unaddressed. Group therapy dropout rates hover around 20 to 30 percent across most modalities. The biggest predictor isn't symptom severity. It's the mismatch between what the member expected and what the group actually delivers. People sign up for CBT and get a process group, or vice versa. They expect the therapist to lead and get told to work directly with each other. Screening matters more than any theoretical orientation. A ten-minute structured interview before admission—covering expectations, motivation, interpersonal style, and current functioning—will cut your dropout rate significantly. I started doing this and lost maybe one person per cohort instead of two or three.
There are also situations where group therapy simply won't work and you should be honest about it. Active substance dependence without a period of stabilization. Acute suicidality. Severe paranoia or psychosis. Antisocial personality disorder with active manipulation. Narcissistic presentations that can't tolerate any focus shifting away from them. These aren't contraindications in every case, but they require careful consideration and usually a different level of care. I once had a member with borderline features who would text six other group members between sessions, creating alliances and triangulation that poisoned the room. No amount of interpretation fixed it. She needed individual therapy first. Pulling her from the group wasn't failure. It was the right clinical decision. The evidence base is strongest for CBT-based groups with specific disorders—social anxiety, panic disorder, substance use, eating disorders. Yalom's model has solid outcome data for depression and adjustment issues, though the mechanisms are harder to measure. Psychodynamic group therapy has a growing evidence base for personality disorders and chronic depression, with studies showing effects that persist after treatment ends. The problem is that most of this research comes from controlled trials that look nothing like how groups actually run in community mental health centers. Real-world effectiveness is probably lower than the published numbers suggest, and that gap matters if you're trying to justify group therapy to administrators who only read meta-analyses. If you're setting up a group and don't have a clear model in mind, start with Yalom. It's the diagnostic tool that will help you understand what's happening regardless of which therapeutic framework you eventually settle on. Then layer in whatever structure your population needs. A panic disorder group needs CBT structure with Yalom's cohesion and universality factors baked in. A process group for people with relationship difficulties needs Yalom's interpersonal learning dimension plus enough structure that people don't just vent and leave without learning anything.
The model you pick shapes your role as therapist. In CBT groups, you're an instructor and coach. In psychodynamic groups, you're an interpreter and holder of the frame. In process groups, you're a facilitator of here-and-now experimentation. Each role requires different skills. Knowing which one you're actually doing prevents the confusion that makes groups stall out around session four.