Understanding the ATI Therapeutic Communication Framework
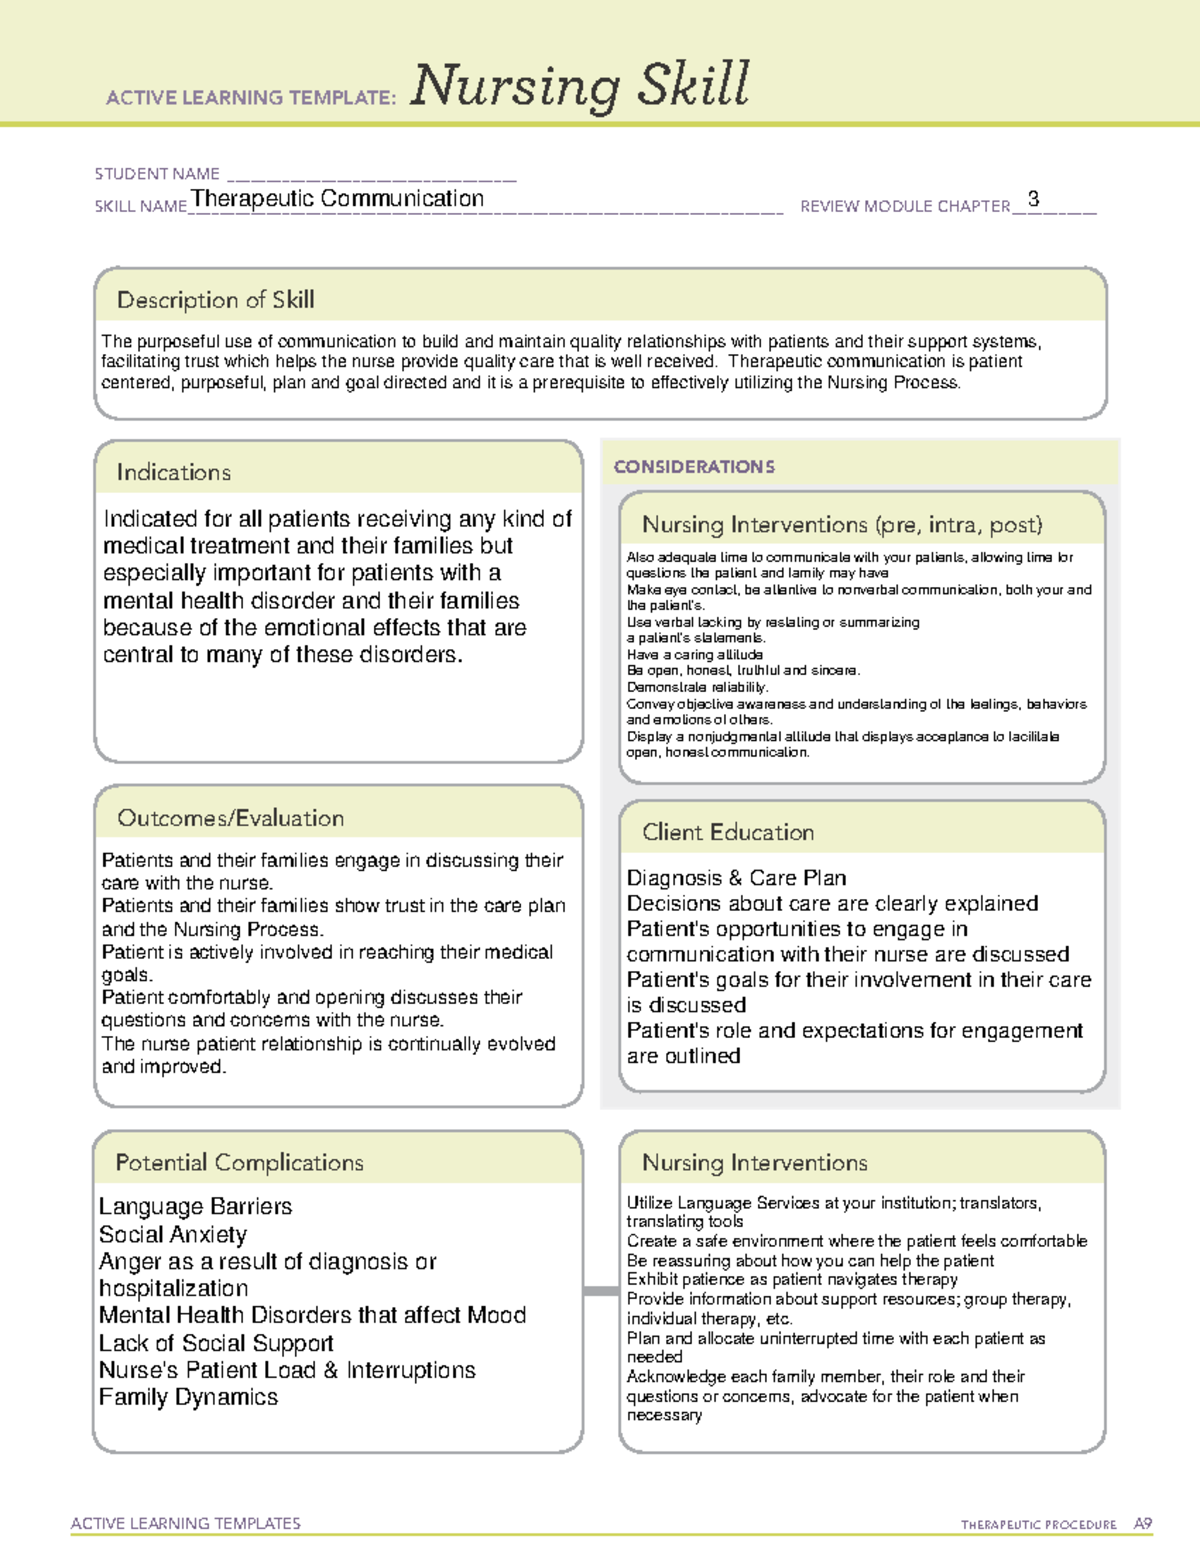
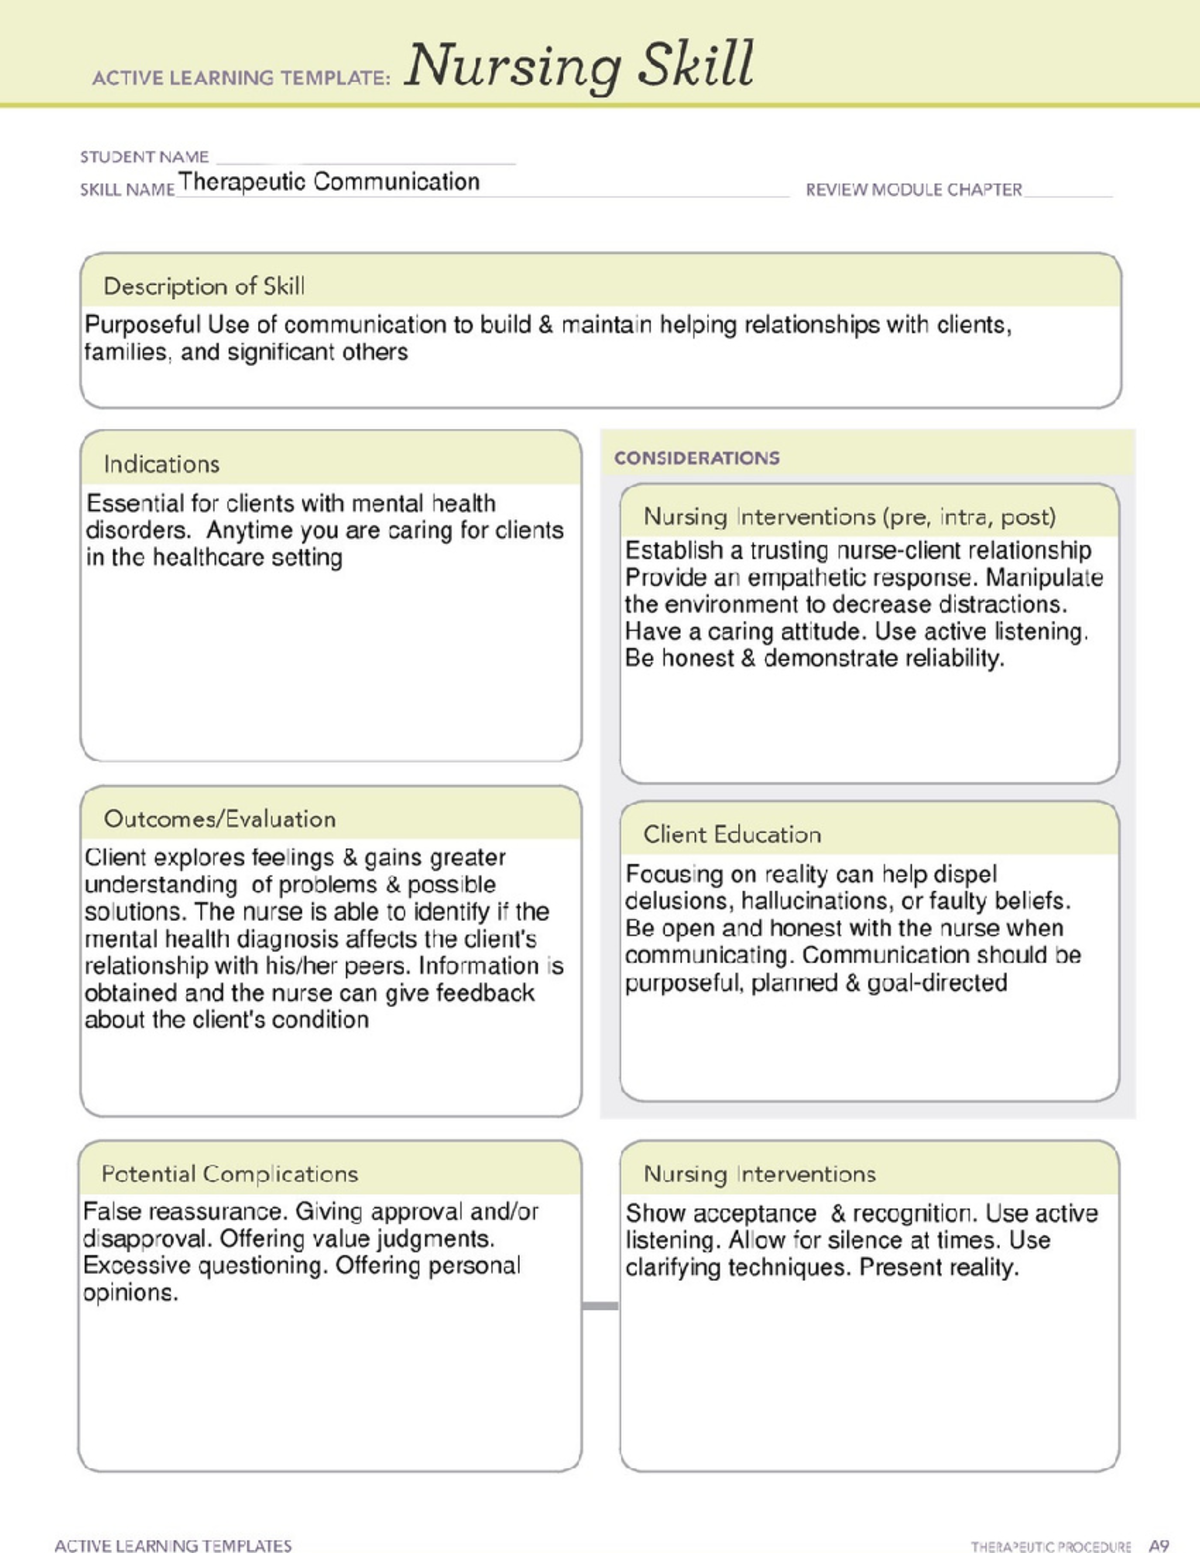
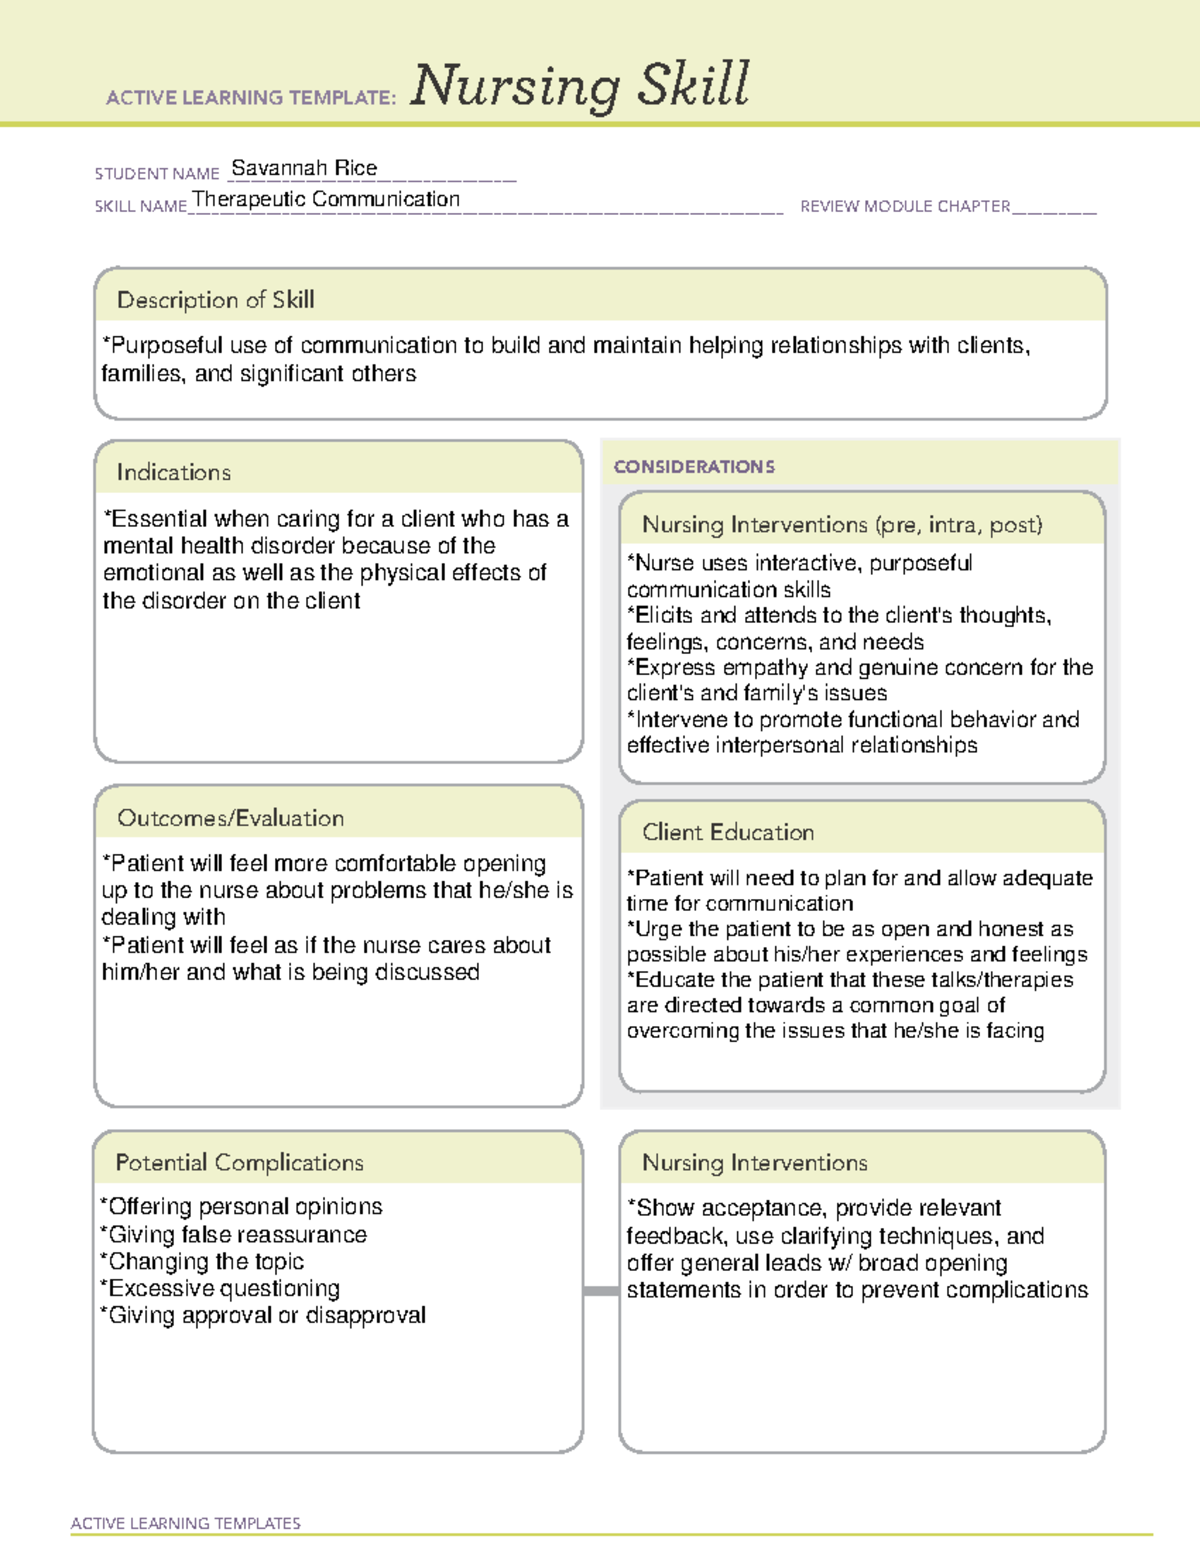
The ATI nursing curriculum has a specific template for teaching therapeutic communication, and it is more structured than most students realize going in. The template itself is not a script you follow word-for-word. It is a rubric that evaluates whether you are using recognized techniques like active listening, reflection, open-ended questions, clarification, and silence. When you understand how the scoring works, you stop guessing and start applying the right interventions at the right time.I first ran into this during a med-surg clinical rotation when my skills checklist evaluator handed me a case about a patient experiencing a panic attack. The template expects you to identify which communication technique applies to each moment of the conversation, then document it accurately. I kept trying to "fix" the situation with advice, and I failed the checkpoint. The issue was I was giving solutions instead of using reflection and validation. Once I slowed down and actually mirrored what the patient said before responding, I passed on the retake. That was the moment I understood the template values process over outcome. The template breaks down into three main parts: the scenario you are given, the communication techniques you deploy, and the documented rationale. Here is how it works in practice. First, read the entire case before you respond. ATI scenarios often include distractor information or emotional cues that change which technique is appropriate. A patient saying "I just can't do this anymore" after hip replacement surgery triggers a different response than a patient saying the same thing while facing a new cancer diagnosis. The context determines whether you use validation, exploration, or redirection.
Second, match your response to the correct therapeutic technique. The five core categories ATI tracks are open-ended questions, reflection, clarification, validation, and silence. You should be able to name which one you are using and why. Documentation matters because the evaluator reads your rationale. Writing "I used an open-ended question to encourage the patient to express feelings" is what they want to see, not "I talked to the patient." Specific language maps directly to rubric points. Third, avoid the trap of stacking too many techniques in one response. Beginners often try to hit reflection and an open-ended question and validation all in one sentence. That reads as forced and artificial. One technique per exchange is cleaner and scores higher. Pick the single most appropriate intervention for that moment and move forward.
Common Pitfalls and What Actually Works
There is a counter-intuitive thing about this template that most study guides miss. The template does not reward you for being empathetic in a general sense. It rewards precise technique identification. A response that sounds warm but uses non-therapeutic language like "everything will be okay" or "you should stay positive" will lose points even if it feels kind. Those are platitudes and they are explicitly flagged in the rubric. Another pitfall is overusing clarification. Students think asking "Can you tell me more about that?" is always the right move. It is not. Clarification is for when you are genuinely uncertain about the meaning. If the patient has already been clear, switching to an open-ended question or reflection is more appropriate. Using clarification when you already understand the message can make the patient feel interrogated. Here is a specific edge case I encountered. A student once had a scenario where the patient was refusing medication and becoming increasingly agitated. The template guidance says to use validation first, then explore. But the scenario also included time pressure because the medication was due. The student got stuck trying to complete a full therapeutic exchange and missed the fact that de-escalation through short, direct statements was the priority. The workaround was recognizing that the scenario had shifted from assessment to crisis management, and the template allows for a different technique hierarchy when safety or acute distress is present. Documenting that shift explicitly earned full credit.
Get the Full Details
What the Template Does Not Cover
The ATI therapeutic communication template has real limitations. It is designed for standardized testing and simulation, not for the messy reality of actual patient interactions. In practice, patients do not wait for you to identify which technique you are using. They interrupt, they go silent for unexpected reasons, they change the subject entirely. The template simplifies this into clean exchanges that rarely exist outside a classroom. Another limitation is that the rubric tends to favor verbal techniques over nonverbal ones. Silence is listed as a technique, but demonstrating actual comfortable silence in a role-play scenario is difficult to grade fairly. Some evaluators interpret any pause as a student faltering rather than a deliberate therapeutic choice. This means you sometimes have to slightly overact silence to make it count on paper, which is an odd compromise to navigate. If you are looking for a downloadable version of the template, ATI provides it through their official student resources portal at oncourse ATI. The most reliable versions are the ones included in your program's skills checklist packet. Third-party copies circulate frequently but some have outdated scoring criteria, so always cross-reference with what your current instructor is using. The template itself is usually a one-page rubric with columns for technique type, example phrases, and points allocated per category.