Attachment Therapy Is Not What You Think It Looks Like
I spent years watching people get sold on dramatic breakthroughs that lasted exactly three weeks. The reality of therapy for attachment issues is slower, quieter, and a lot less cinematic than the Instagram posts make it seem. You sit in a room once a week for months and gradually learn that your brain's alarm system has been misfiring since childhood. That's it. No magical reconciliation with your parents. No overnight shift. The most effective framework is EMDR-based attachment work combined with parts work, specifically IFS or Ego State Therapy. Most people go straight to psychodynamic talk therapy because that's what they've heard about, but the evidence base favors modalities that actually process the nervous system responses rather than just talking around them. Here's the thing nobody tells you: attachment wounds live in the body first and the narrative second. Your brain has already written the story about why you push people away before your body even registers someone is getting close.
What Therapy For Attachment Issues Actually Addresses
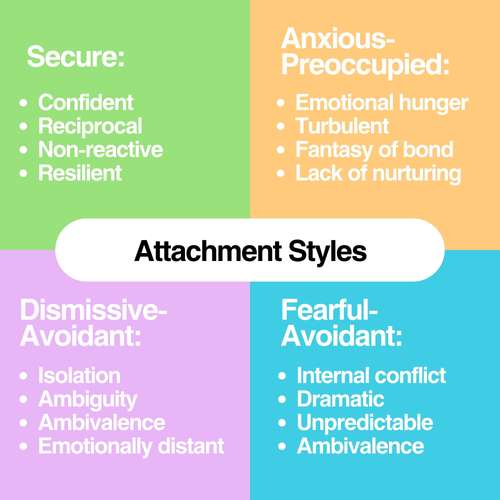
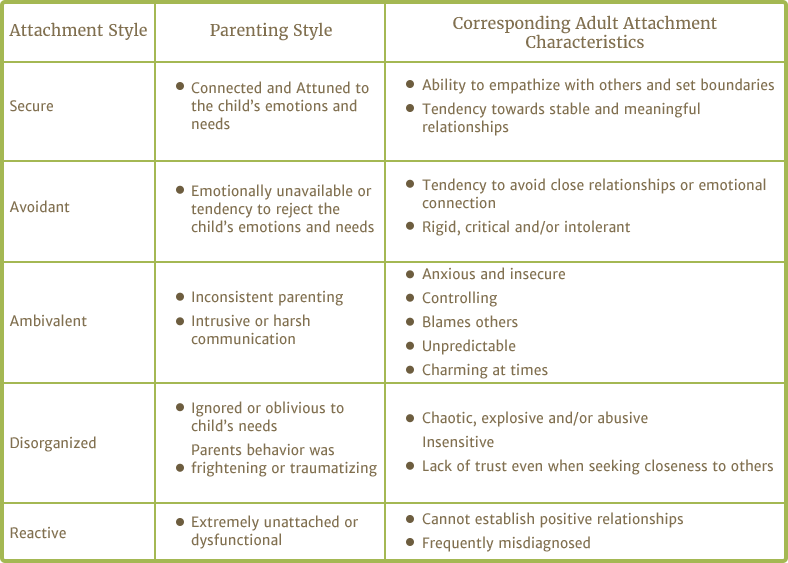
Attachment issues show up as either hyperactivation or deactivation of your attachment system. Hyperactivation means you chase, cling, panic when someone doesn't text back, and can't regulate without external validation. Deactivation means you shut down, intellectualize, disappear when things get emotional, and treat closeness like a threat. Most people are a mix depending on the trigger. The fearfull-avoidant style, which combines both patterns, is the hardest to treat and the most common in clinical practice. It usually stems from having a caregiver who was simultaneously a source of comfort and a source of fear, which trains the nervous system to approach and retreat at the same time. I had a client last year who presented as classic avoidant. Cold, self-reliant, couldn't imagine needing anyone. Standard attachment therapy would have him exploring childhood dynamics for six months before anything shifted. Instead, I started mapping his triggers through a somatic lens. We identified that his avoidance wasn't really about independence. It was about predicting rejection before it happened, which is a fundamentally different thing. Once we addressed the anticipatory threat response rather than the surface behavior, the work moved fast. He stopped needing to leave the room before the other person could.
The Modalities That Actually Work
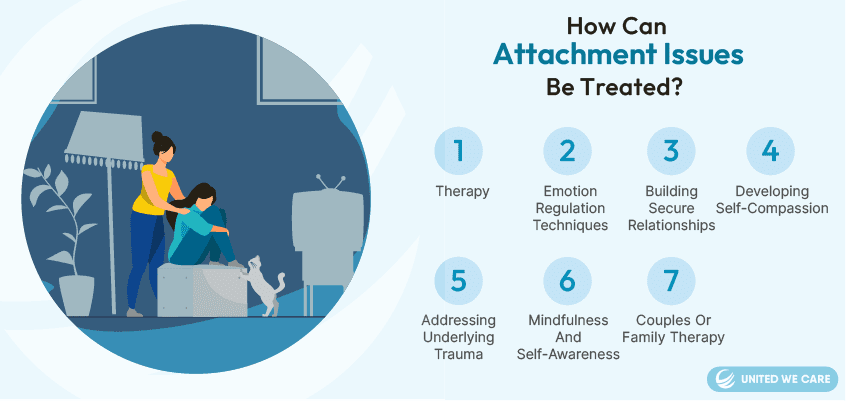
Emotionally Focused Therapy, or EFT, is the gold standard for couple-based attachment work. It was developed by Sue Johnson and Leslie Greenberg and has strong outcome research behind it. For individuals, the same principles apply but with more focus on the internal attachment system rather than the dyadic dance. AEDP, or Accelerated Experiential Dynamic Psychotherapy, is less known but extremely effective for individual attachment trauma because it moves through the affective layers quickly instead of circling around them for months. IFS is useful when your attachment patterns feel fragmented, which they often do when the wound occurred early. The concept of exiles and protectors maps cleanly onto anxious and avoidant subparts. Your anxious part isn't a malfunction. It's a protector that learned to escalate needs because quiet needs went ignored. Your avoidant part is also a protector that learned to preemptively cut off because connection turned painful. The therapy doesn't try to eliminate either. It builds enough internal safety that neither one has to operate at maximum volume. Body-oriented approaches matter more than people expect. Somatic Experiencing and sensorimotor psychotherapy address the freeze and fawn responses that talk therapy completely misses. If you've never noticed your breath change when someone raises their voice, or your stomach drops when a friend doesn't reply within an hour, that's your attachment system running on autopilot. The body keeps the record. Any therapy that ignores it is only treating half the problem.
Get the Full Details
What To Expect When You Start
The first six sessions are mostly assessment. A good therapist will ask about your relationships, your family of origin, your physical symptoms, and your response to conflict. They should also be able to identify which attachment style dominates and whether you have any disorganized elements. If they're not doing that, find someone else. The assessment determines whether you need EMDR for trauma storage, EFT for relational patterns, or IFS for structural dissociation. Sessions typically run fifty minutes, twice a week is more effective than once for attachment work, and the total timeline is somewhere between six months and two years depending on severity. I've seen clients move significant ground in four months when the issue was primarily anxious-preoccupied and single-attached. I've also seen people stall at the same conversation for eight months when the attachment injury was complex developmental trauma from multiple caregivers. There's no shortcut around the complexity. The hardest part isn't the work. It's the window between recognizing your pattern and actually changing it, which can stretch for months. You'll know exactly what you're doing wrong in session and still do it wrong in your actual life. That's normal. Neural pathways don't rewire through insight alone. They rewire through repeated new experience in the presence of a regulated other. Your therapist is that regulated other. The relationship itself is the intervention.
Where This Approach Falls Short
Attachment therapy doesn't work if your current relationships are actively unsafe. You can't process attachment trauma while you're still in the situation that recreated it. That means staying in an abusive partnership, a manipulative friendship, or a work environment that mirrors your original wound isn't a therapeutic problem. It's a logistical one. The therapy won't fix the environment. It will only make you better at surviving in it, which is not the same thing. Another limitation: attachment work requires a therapist who actually understands the model. Too many clinicians label any relationship difficulty as attachment-related without distinguishing between anxious, avoidant, and disorganized presentations. The treatment differs significantly. Anxious attachment responds well to co-regulation and distress tolerance. Avoidant attachment responds to gradual exposure to vulnerability within safe limits. Disorganized attachment needs stabilization first, because the nervous system has no coherent strategy for connection at all. Throwing all three into the same bucket produces mediocre outcomes. If your attachment issues are tied to a personality disorder, particularly BPD or NPD, standard attachment therapy will underperform. You'd need dialectical behavior therapy or schema therapy alongside or instead. DBT in particular has strong evidence for the emotional dysregulation that accompanies insecure attachment, and it gives you concrete skills while the deeper attachment work happens in parallel.
Finding the Right Therapist
Look for someone trained in EFT, IFS, or AEDP. Ask them directly how they conceptualize attachment and what their typical treatment length is for someone with your profile. A qualified therapist will give you a clear answer. If they say it depends or deflect, that's a signal. Check the International Centre for Excellence in Emotionally Focused Therapy directory for EFT-trained clinicians. For IFS, the IFS Institute maintains a locator. These are more reliable than generic psychology today listings. Also pay attention to how they handle ruptures. A therapist who can't tolerate your anger or withdrawal is going to either push you toward compliance or withdraw themselves, and both replicate the original wound rather than repair it. The rupture and repair cycle is literally where the attachment change happens. If your therapist can't manage that moment, the therapy is just another performance of the dynamic you're trying to escape.