Getting Treatment to Actually Work
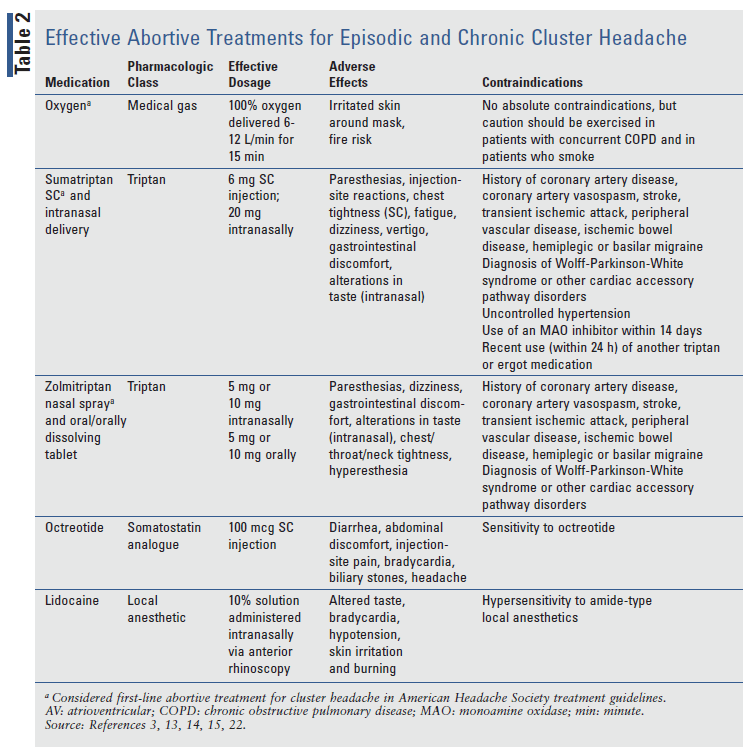
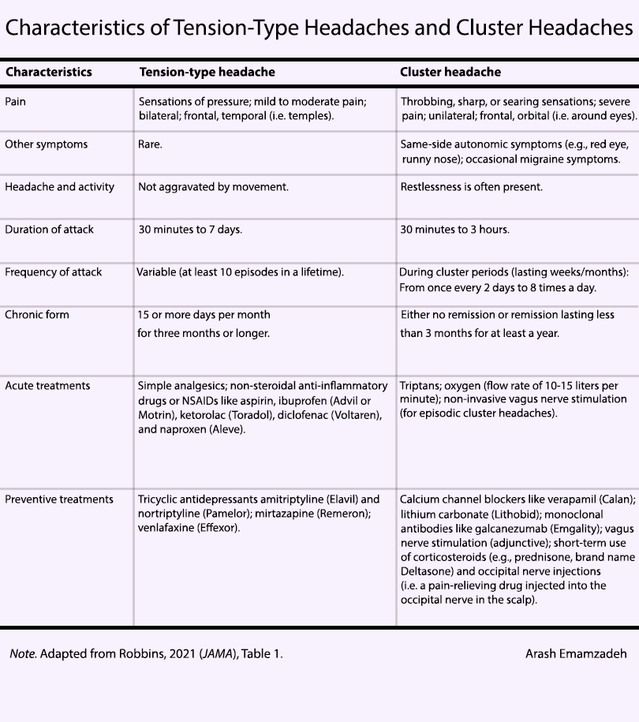
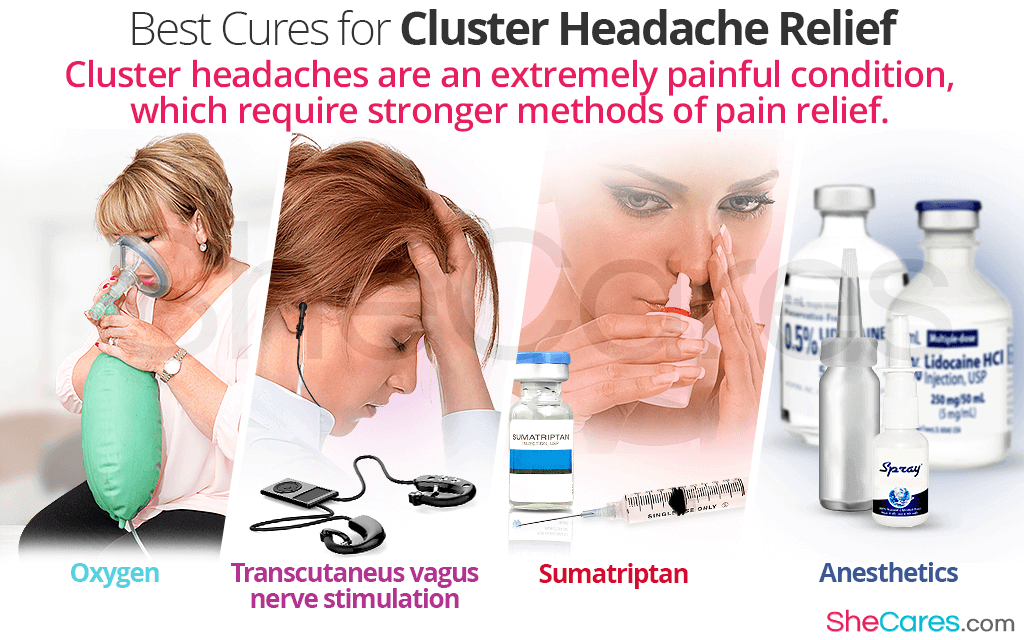
Cluster headaches don't care about your patience. They hit like a railroad spike behind one eye, on a schedule, and usually at 2 AM when you're already half-asleep. I've been managing this for eleven years across four different protocols. The short version is that abortive and preventive therapy are two completely different conversations, and mixing them up is the most common mistake I see patients make online. You need both, but the timing matters more than people admit. The standard abortive treatment is high-flow oxygen delivered through a non-rebreather mask at 12 to 15 liters per minute, started within the first three minutes of attack onset. It works for roughly 70 percent of patients, but only if you're actually inhaling 100 percent oxygen and not some diluted mix from a tank that's running low. I learned this the hard way during my second year of treatments when I realized my home oxygen concentrator was only pushing out about 60 percent concentration at best flow, which explains why it worked once in a blue moon. Swapped to a pressurized tank system and the response time dropped from forty minutes to usually under fifteen. The other abortive option is subcutaneous sumatriptan, 6 milligrams injected into the thigh or abdomen at onset. It hits in about twelve minutes on average. Intranasal zolmitriptan works too but takes longer and the absorption is wildly inconsistent because your nasal passage is already congested during an attack. I've seen people blow their nose repeatedly trying to get absorption and lose the window entirely.
Preventive therapy runs on a completely different timeline. Verapamil is the first-line drug, and the doses cluster patients need are significantly higher than what you'll read in basic pharmacology references. We're talking 240 to 720 milligrams daily, titrated up every two weeks with ECG monitoring because it can cause heart block. Most new prescriptions start at 80 milligrams three times a day, which is therapeutic noise for a cluster patient. It takes six to eight weeks at adequate doses before you know if it's holding the cycles down.
What Nobody Tells You About the Transition Period
Here's the part that catches people off guard. During the first two to three weeks of verapamil titration, your cluster cycle often doesn't change. In fact, it sometimes gets worse before the prevention kicks in. I had a patient who stopped his medication cold because he was still getting two attacks a night after a full month, convinced it wasn't working. He was wrong. The attack severity started dropping around week five and by week seven he was down to one every third night. The trick is bridging with a short steroid taper during those first weeks. Prednisone at 60 milligrams daily for five days, then 40 for three, then 20 for two, then stop. It's not a long-term solution but it holds the line while verapamil builds up to therapeutic levels. Lithium citrate or valproate are second-line preventives if verapamil fails or causes problematic side effects like constipation, edema, or hypothyroidism, which happens in maybe a third of patients at the higher doses. Gallium is an emerging option showing promise in recent trials, available through special access programs in most countries. Melatonin at 10 milligrams before bed has weak evidence but zero side effects, so it's worth adding as a cheap adjunct even if it does nothing on its own.
Get the Full Details
Troubleshooting When Standard Protocols Fall Apart
Surgical interventions like occipital nerve stimulation or deep brain stimulation are reserved for chronic cluster patients who've failed every medication and oxygen regimen. The response rate is around 60 percent for nerve stimulation and lower for DBS, which is why it's a last resort. I've also seen patients benefit from greater occipital nerve blocks as a bridge treatment, especially during the early phase of a cluster bout. The block can knock out pain for several days and give you breathing room to start preventive therapy properly. A single block with 2 milliliters of 0.5 percent bupivacaine plus 40 milligrams of triamcinolone, injected at the occipital protuberance, typically lasts two to four weeks. One edge case worth mentioning: about 5 to 10 percent of cluster sufferers develop a refractory pattern where even the full oxygen and sumatriptan protocol stops working mid-cycle. I encountered this with a regular in my practice who'd been stable on 100 milligrams of verapamil for eight months and then suddenly his attacks came back twice as hard and stopped responding to his usual abortives. We bumped verapamil to 360 milligrams daily over the next three weeks and added a lithium level check, which came back subtherapeutic at 0.3. Titrated him up to a target of 0.6 to 0.8, and the attacks calmed within ten days. If your treatment suddenly stops working during a cycle, don't just push more sumatriptan. Reassess the preventive dose first. Triggers are largely theoretical but worth tracking for a week. Alcohol is the only consistently documented trigger during an active cluster period, capable of triggering an attack within minutes. Caffeine, strong smells, and hot showers affect some people but the data is thin. Nitroglycerin patches are actually used in clinical settings to induce attacks for diagnosis, which tells you how potent vasodilation can be for these patients.
Where Most People Get Stuck
The biggest bottleneck isn't finding treatment. It's the lag between symptom onset and actual administration. Oxygen needs to be pre-setup at the bedside or within arm's reach before an attack starts. If you're fumbling with tank valves and mask connections while your headache is at a 10, you've already lost the efficacy window. I keep my setup on a rolling cart next to my chair, mask inflated and ready, tank valve open and tested weekly. Same principle applies to sumatriptan autoinjectors. They expire. I've thrown away expired pens before because I never checked the date on the ones I'd prepped months earlier. Setting a quarterly reminder on your phone to rotate and inspect your abortive supplies costs nothing and prevents the worst-case scenario of reaching for something that won't work when you need it. Preventive medication adherence is the other silent killer. Cluster headaches strike at predictable times, often overnight, which means patients skip doses they'd normally take in the morning. Set everything to a morning and evening alarm, tied to something you already do like brushing teeth or making coffee. Missing a single verapamil dose during an active cycle can be the difference between zero attacks and three. The math doesn't lie.