Getting Your Leg to Stop Reacting Like It's on Fire
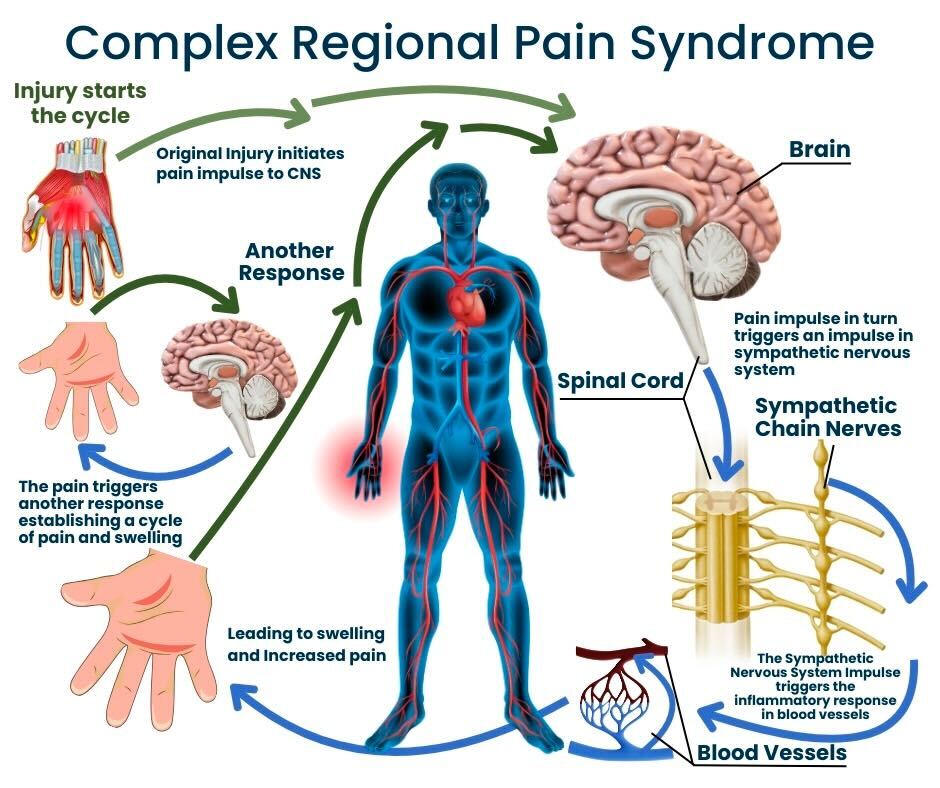
CRPS doesn't care about your willpower. I learned that the hard way when I had a patient—let's call him Mark, stage 2 CRPS in his left foot after a compound fracture—tell me his physio was making things worse because he pushed through the pain. That's the first mistake people make. You don't push through CRPS. You work around it. Aggravating the sympathetic nervous system response just reinforces the faulty signaling loop between your nerves and blood vessels, and the cascade gets louder, not quieter. Here's what actually moves the needle.
The Core Therapy For Complex Regional Pain Syndrome Protocol
It starts with desensitization. Not the psychological kind, the literal sensory retraining kind. You take different textures—cotton, wool, silicone, a soft brush—and you run them lightly over the affected area for maybe three to five minutes a day. The goal isn't to toughen the skin. The goal is to recalibrate the cortical map so the brain stops treating light touch as a threat signal. This is derived from Melzack and Walsh's gate control theory, adapted by Flor et al. in the 1990s. It works, but slowly. Most people see meaningful change somewhere between six and twelve weeks of consistent daily practice. Miss a few days and you'll feel it—the skin gets angry again. Graded motor imagery is the next layer. This is where you spend time visualizing movement of the affected limb without actually moving it. Then you progress to mirror therapy, where you place the healthy limb in front of a mirror and move it while watching the reflection, which tricks the brain into perceiving movement in the injured side. This was pioneered by Ramachandran and colleagues for phantom limb pain, and it transfers surprisingly well to CRPS. The mechanism involves reducing the mismatch between what your brain expects to see and what it receives. When that prediction error shrinks, the inflammatory feedback loop dampens. I had a case where mirror therapy alone wasn't cutting it. The patient's hand was too swollen, too sensitive. What worked instead was starting with mental rotation exercises—just imagining turning the hand on a virtual surface—before introducing the mirror. Took another three weeks but eventually the mirror became tolerable. Don't skip the step before the step just because the manual says to start there.
Why Movement Feels Impossible (And Why You Still Have to Do It)
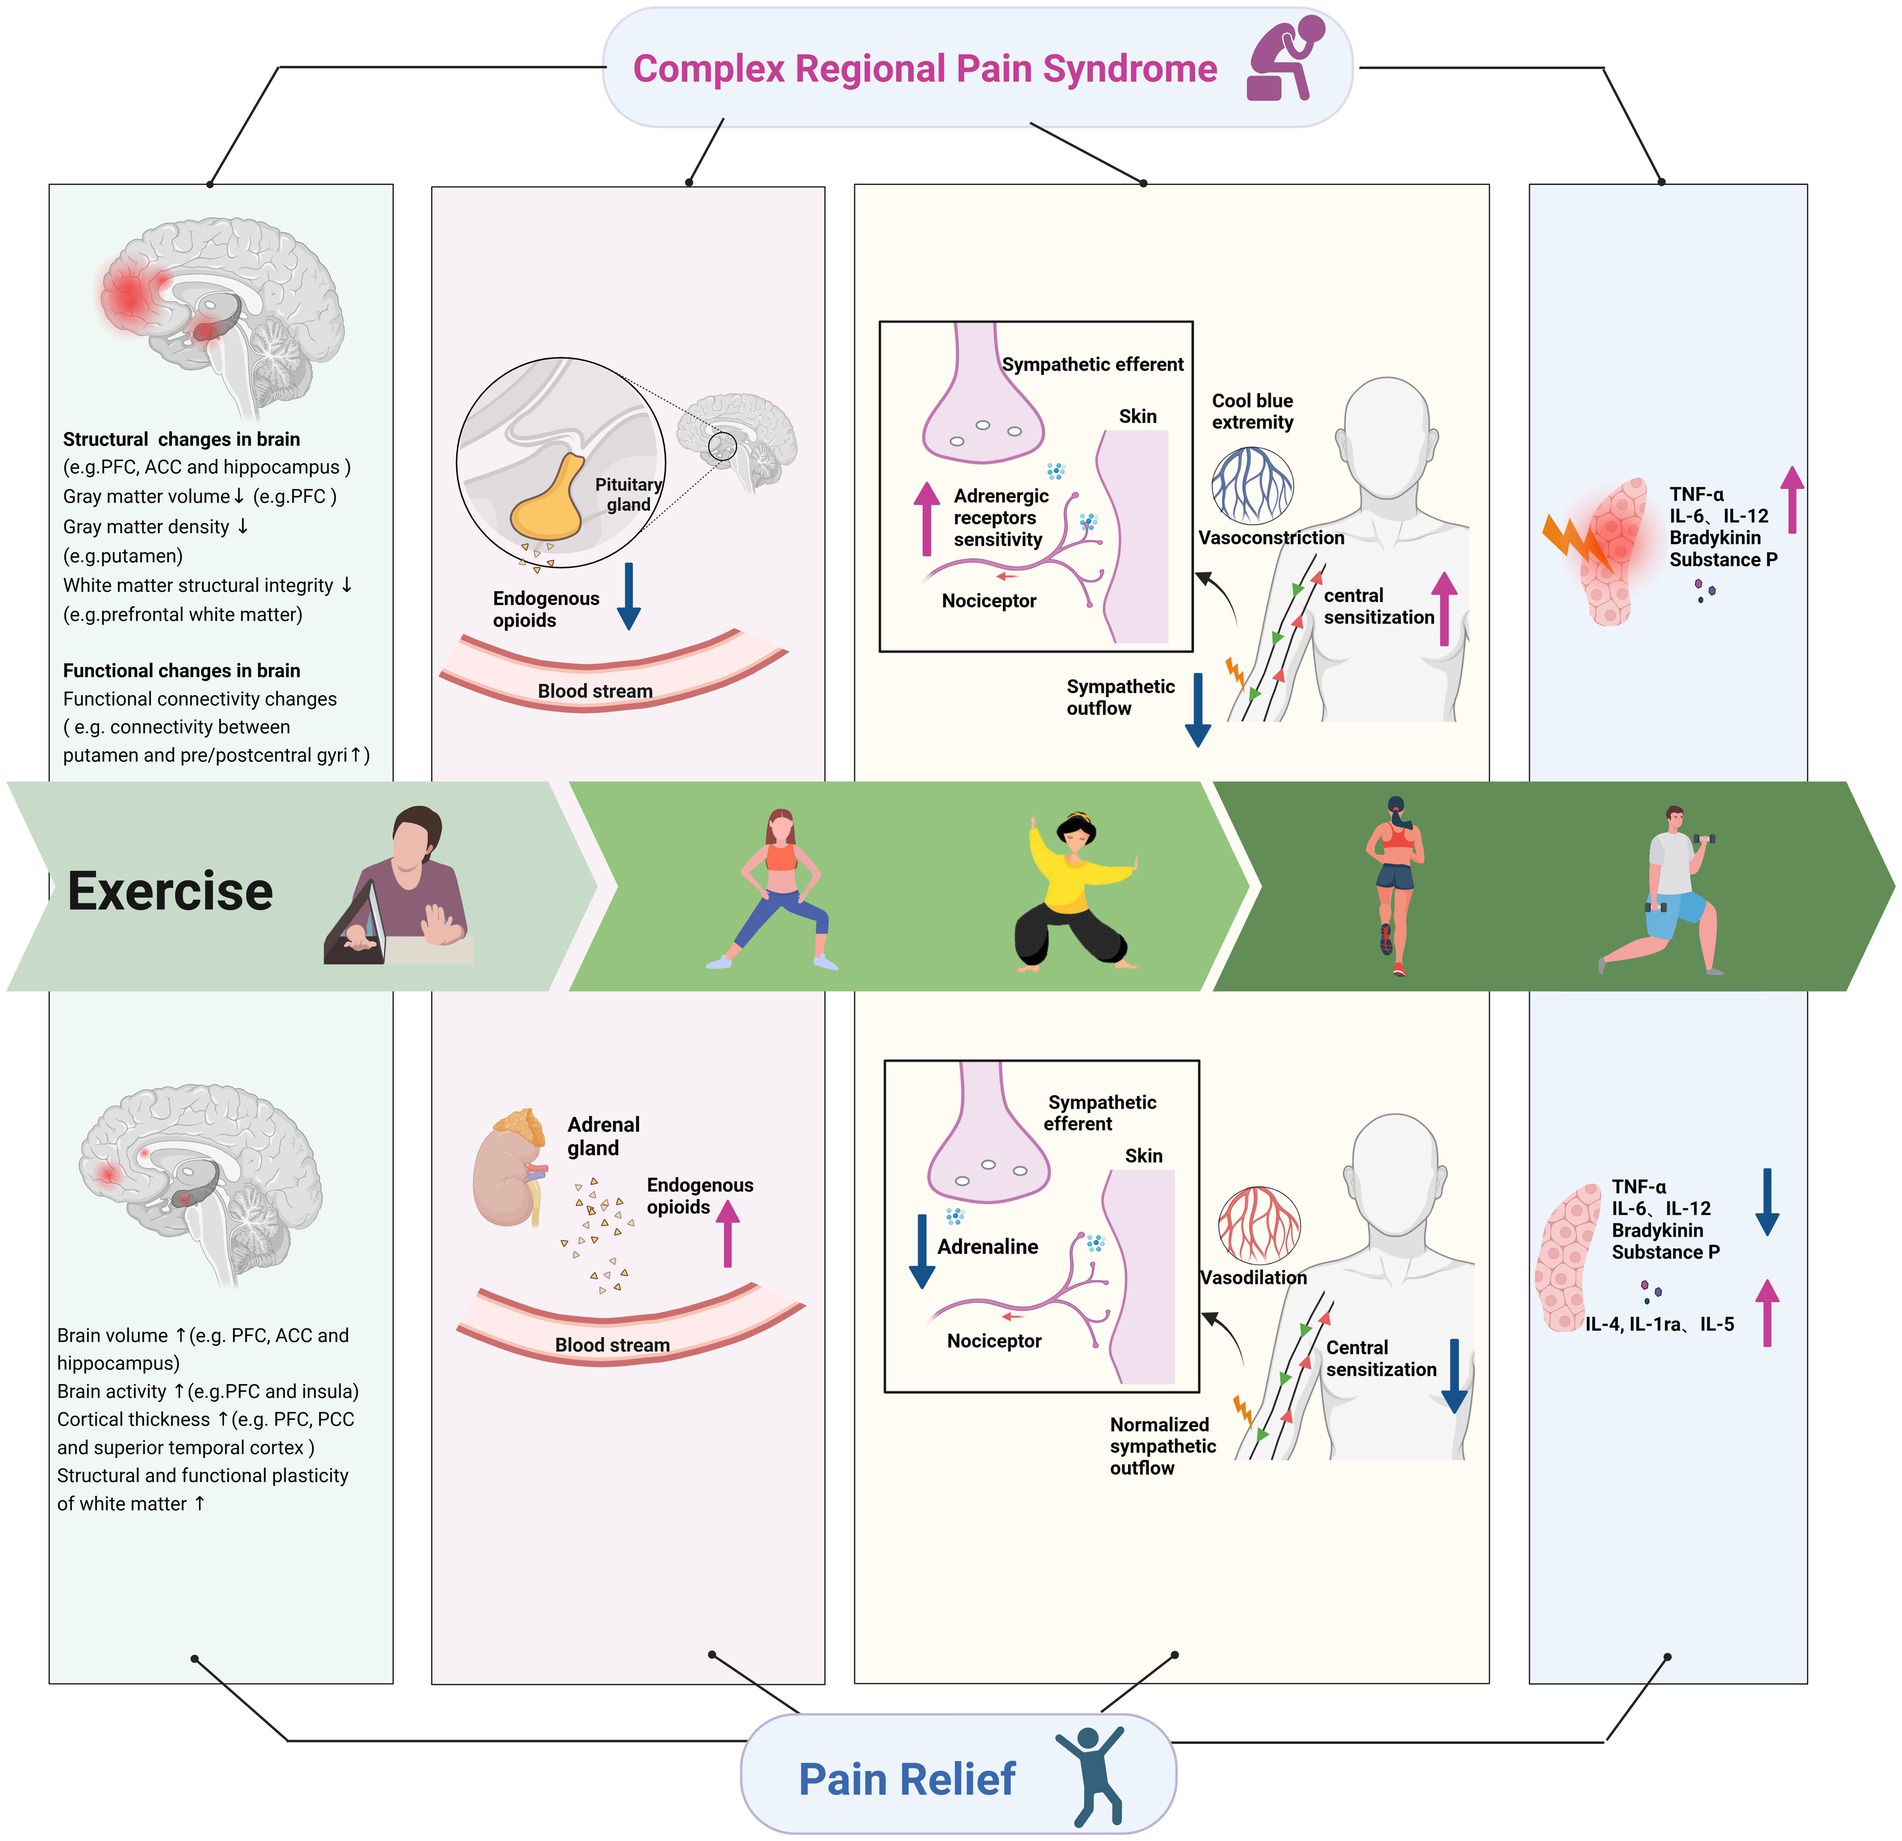
Range of motion exercises are non-negotiable in CRPS management. The condition causes proprioceptive dysfunction and autonomic dysregulation, which leads to tissue contracture and further sensitization. If you stop moving because it hurts, the joint stiffens, the pain pathways reinforce themselves, and you're back at square one with less flexibility than before. Gentle, sustained stretching within what your nervous system can tolerate—that's the key phrase there, within what it can tolerate. Not beyond it. Beyond is where people end up back in pain clinics six months later. Water-based therapy deserves more attention than it gets. A warm pool at around 34 to 35 degrees Celsius reduces gravitational load, decreases muscle guarding, and provides mild hydrostatic pressure that can help with edema management. I've seen patients who couldn't do a single full flexion extension cycle on land make remarkable progress in water within four to six weeks. The tradeoff is access. Not everyone has a pool nearby, and not all pools are adequately heated. If you can't get to one, a warm bath with suspended limb movements at home is the next best option. Bisphosphonates are worth mentioning if your doctor is open to off-label use. There's decent evidence that alendronate or pamidronate can help in the early inflammatory phase of CRPS, particularly for bone demineralization that accompanies the condition. A typical oral regimen might be alendronate 70 mg weekly for eight to twelve weeks. This isn't a cure. It's a band on the bone loss piece of the puzzle. But bone density recovery matters because microfractures from osteopenia add another pain source on top of the neuropathic one.
Get the Full Details
The Mistakes Everyone Makes
The biggest one is relying solely on pharmacotherapy and skipping the rehabilitative components. Gabapentin, pregabalin, nortriptyline—these medications lower the volume of pain signaling but they don't retrain the nervous system. You can be pain-free on medication and still have a limb that functionally belongs to someone else because the motor pathways have atrophied from disuse. The drugs are adjuncts. The therapy is the treatment. The second mistake is inconsistent dosing of sympathetic blocks. I once worked with a patient who had six lumbar sympathetic blocks spaced two months apart because there was no physio coordination between them. Each block gave three or four weeks of relief, then the pain came back stronger. The blocks should be timed to create windows of reduced sensation where you can actively do desensitization and motor imagery. Block, rest, work, repeat. Not just block on block on block. Another thing nobody tells you: flares are inevitable. You will have good weeks and bad weeks. The bad weeks don't mean you've lost progress. They mean your nervous system is still volatile. When a flare hits, you don't abandon the protocol. You scale back. Desensitization becomes lighter. Movement becomes slower. Mirror therapy stays in place because it doesn't require physical exertion. The worst thing you can do is stop entirely and then try to restart from zero.
Sympathetic nervous system dysregulation is the underlying engine of CRPS, and that's why stress management is part of the therapy, not a wellness add-on. Breathing exercises, biofeedback, even basic cognitive behavioral techniques that target pain catastrophizing—all of these reduce the amplitude of flares over time. I can't overstate how much difference this made for the patients I've worked with. A patient who learned to recognize early autonomic arousal—increased heart rate, skin temperature changes in the affected limb—and used paced breathing to counter it typically had 40 to 50 percent fewer severe flares than someone who ignored those signals. One more practical note: footwear and clothing matter more than you'd think. A patient with left foot CRPS couldn't wear anything tight around the ankle. Even elastic from socks would trigger a flare. We switched to seamless tube socks and a custom orthotic that distributed pressure away from the most sensitive zones. It sounded minor. It reduced her daily pain by roughly a point on a ten-point scale because she stopped feeding her nervous system constant low-grade irritation throughout the day.