What Actually Moves the Needle for Neck Pain
Most people with chronic neck pain are doing the wrong exercises. Not because they're lazy, but because the standard advice you find online assumes a generic population. I've worked with enough clients to know that generic advice is why their pain comes back after a few weeks of feeling better. Therapy For Neck Pain that actually sticks has to account for what's driving your symptoms. Is it upper cross syndrome from sitting at a desk? Degenerative disc issues? Post-concussion tension? The approach shifts depending on the root cause, and skipping that step is the fastest way to waste three months trying things that don't apply to you.
The One Exercise Most People Skip
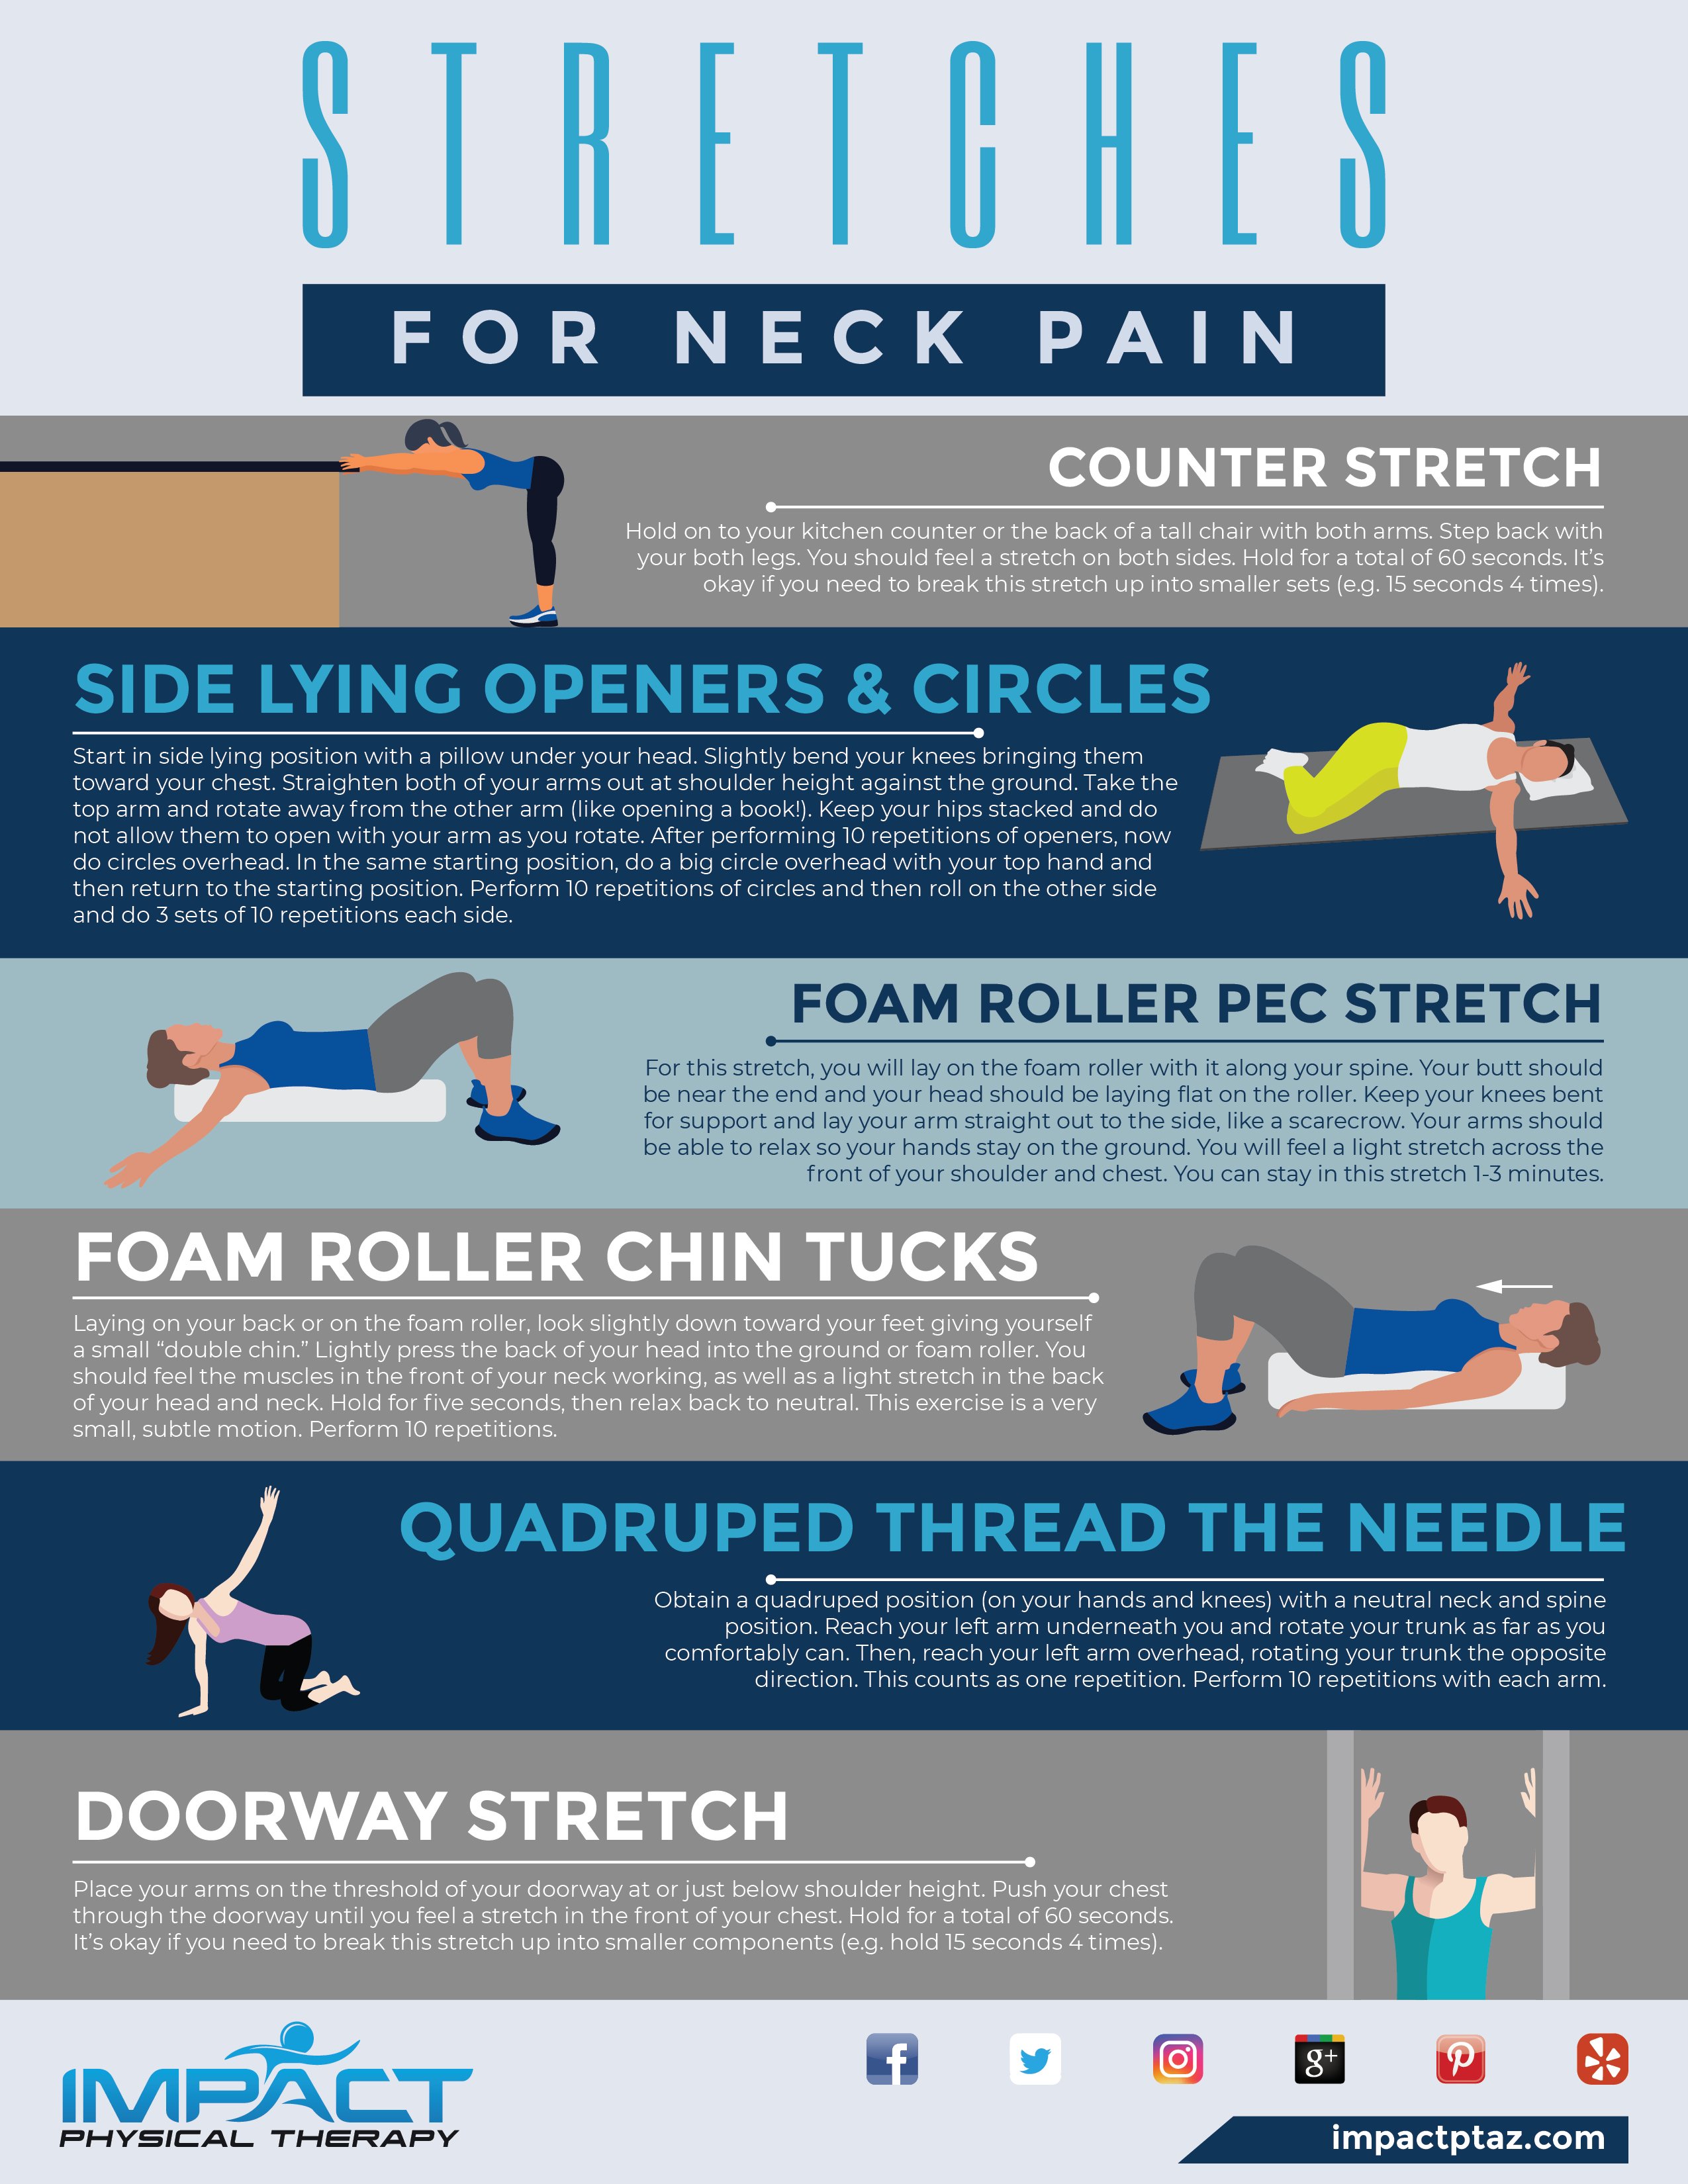
Deep neck flexor endurance work. I know, I've seen the same exercise sheet for ten years. The standard instructions tell you to do chin tucks until your neck burns. The problem is most people are doing them wrong. They're cranking their hyoid up toward their chin instead of creating a long, controlled posterior glide from the base of the skull. You can tell if you're doing it right by checking whether your lower cervical spine stays in neutral. If your head jerks back or your throat bulges forward, you're recruiting the superficial flexors instead of the deep ones, and you're basically just retraining your neck to be tense in a new pattern. Here's what I did with a client last year who'd been in and out of physio for two years with zero lasting improvement. She had severe cervicogenic headaches and her upper traps were knotted to the point where palpation was painful. We stopped all stretching. We stopped all manual therapy on her traps. We spent six weeks exclusively on isometric hold work for the deep neck flexors at 30 percent maximum effort, thirty seconds per set, three sets, twice daily. Her symptom load dropped by maybe sixty percent in the first month. The reason it took so long is she had neuromuscular inhibition of those deep flexors going back years, probably from early injuries she never properly rehabbed. Retraining neural recruitment doesn't happen fast, and nobody tells you that.
What Manual Therapy Can and Can't Do
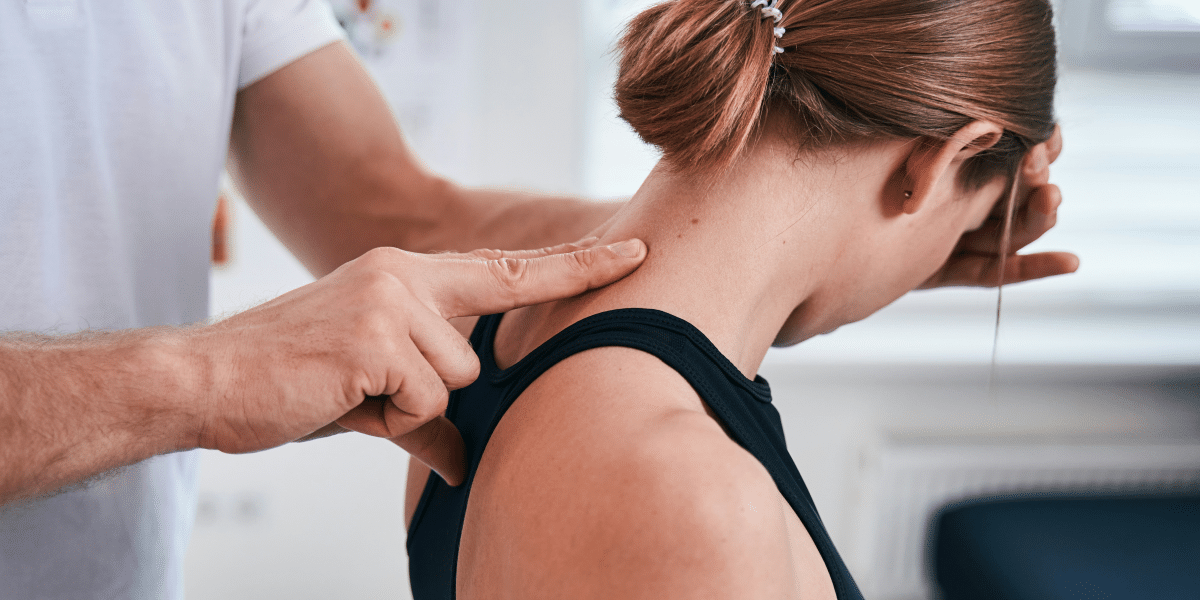
Manual therapy provides short-term relief. That's the honest answer. Joint mobilizations, myofascial release, trigger point work — these reduce pain signaling and temporarily improve range of motion. The effects typically last anywhere from a few hours to maybe two weeks depending on the severity of your underlying dysfunction. If your therapist is only doing passive treatment and not giving you active loading protocols to maintain gains, you're paying for a temporary bandage. There's a specific pitfall with cervical manipulation I want to flag. High-velocity low-amplitude thrusts on the upper cervical spine carry real risk, including vertebral artery dissection, which is rare but documented. I've seen it happen. The consent forms make this clear, but most people skim past it. If your therapist isn't screening for vascular compromise before attempting manipulation — things like the vertebrobasilar insufficiency test and neural tension tests — that's a red flag. Not every neck click is worth the risk. For my own neck issues, which I picked up from years of bad sleeping posture combined with heavy bench pressing without adequate antagonist work, I found that graded cervical loaded isometrics beat everything else. Not the easy kind. I'm talking isometric holds against resistance at different angles — flexion, extension, lateral flexion, rotation — at around forty to fifty percent of max effort, held for twenty to thirty seconds. The protocol takes about twelve minutes total. Doing it consistently across a four-week period produced more lasting improvement than any single manual therapy session I'd ever received.
Get the Full Details
Where Therapy For Neck Pain Falls Flat
It doesn't work for everything. Structural issues like severe cervical spondylosis with radiculopathy, herniated discs pressing on nerve roots, and certain types of arthritis won't respond to conservative therapy in a meaningful way. In those cases, you need imaging and a referral to a spine specialist. Pushing hard exercise protocols into an acutely compressed nerve is how people end up with permanent weakness. I had a client once who ignored radiating arm symptoms and kept doing neck mobility drills. By the time he saw a neurologist, he'd developed thenar atrophy on one side. It never fully came back. Pregnancy-related neck tension is another scenario where standard protocols need modification. Hormonal changes increase ligamentous laxity, which means aggressive stretching during pregnancy can destabilize the cervical joints rather than help them. Gentle stabilization work is the safer bet, and even that should be cleared with an OB provider first. The timeline also needs to be realistic. If you're dealing with chronic neck pain that's been present for more than six months, expect a minimum of eight to twelve weeks of consistent work before you see stable improvement. Shorter bursts of therapy followed by quitting when you feel better are exactly why people cycle through endless rounds of treatment without any lasting result. The tissue remodeling and neuromuscular re-education that actually changes your baseline takes time and consistency, not intensity.