Peptic Ulcer Treatment: What Actually Works In Practice
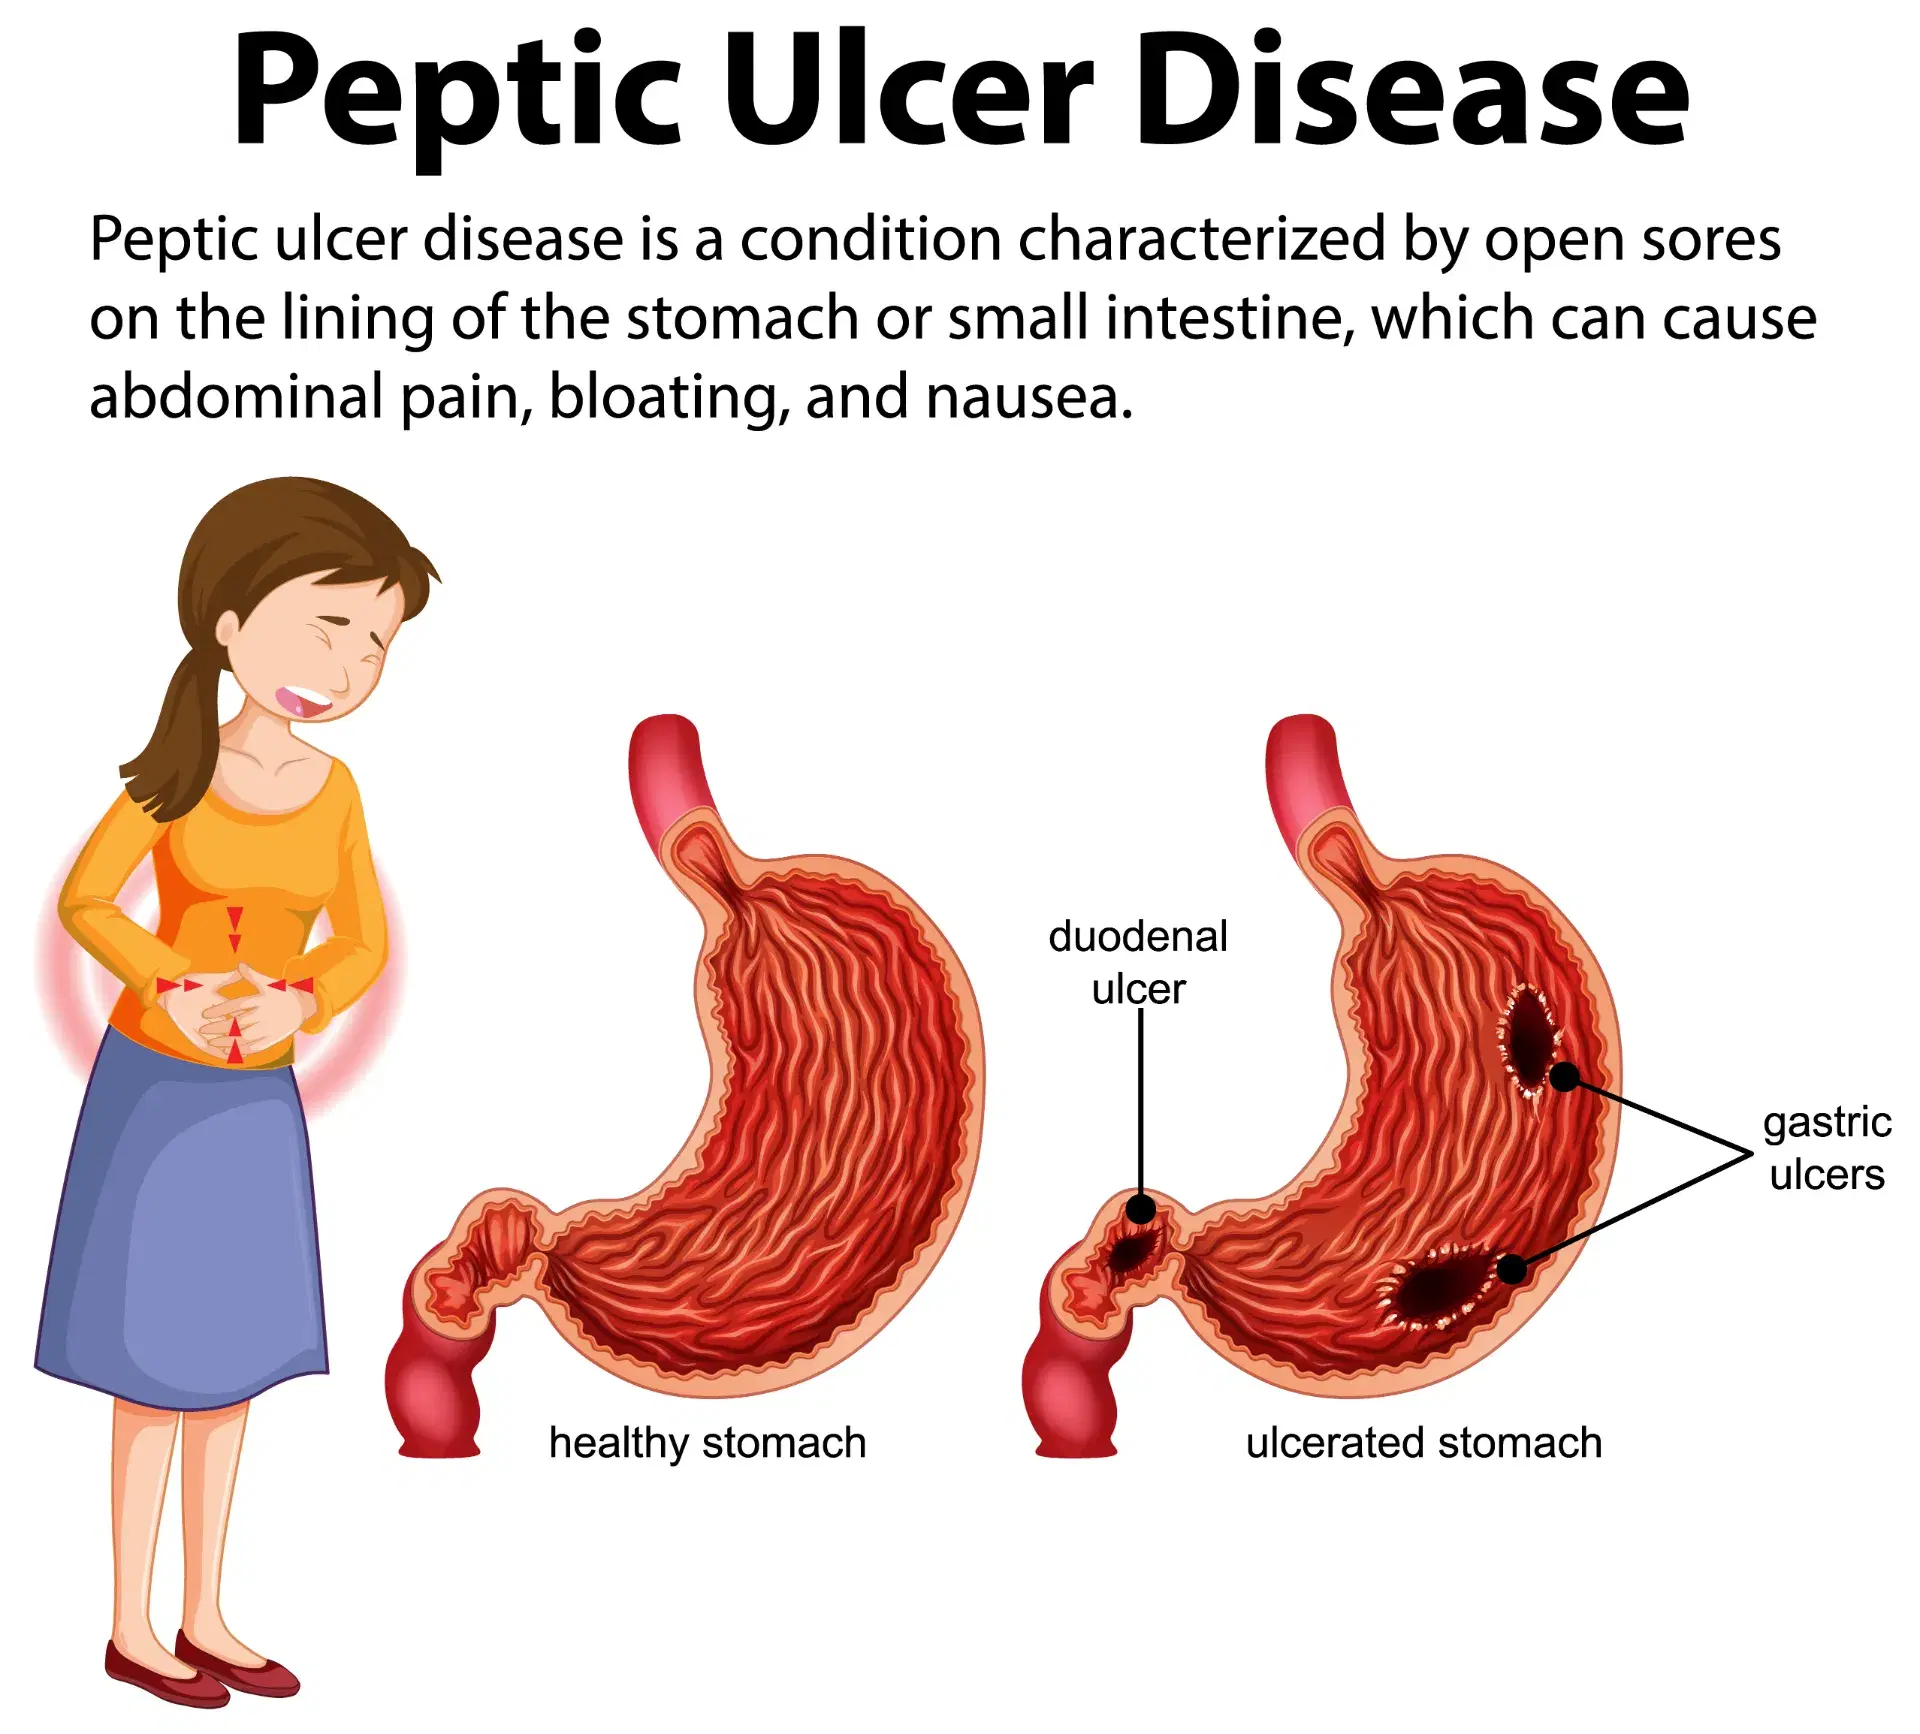
Peptic ulcers are essentially sores that develop on the lining of the stomach or the upper part of the small intestine. The two main causes are Helicobacter pylori infection and long-term NSAID use. Treatment is straightforward if you hit the right protocols, but there are enough variables that people who just memorize a textbook algorithm will miss the cases that don't respond. If H. pylori is confirmed, the standard first-line treatment is a 14-day course of bismuth quadruple therapy: a proton pump inhibitor (PPI) like omeprazole or pantoprazole, bismuth subsalicylate, tetracycline, and metronidazole. This is now preferred over the old clarithromycin-based triple therapy in most places because clarithromycin resistance has gotten out of hand. In areas where local resistance is known to be under 15%, you can still use amoxicillin plus clarithromycin with a PPI for 14 days, but I wouldn't bet on it without checking local resistance patterns. For NSAID-induced ulcers, the priority is stopping the offending drug. If the patient absolutely needs to stay on an NSAID, you pair a PPI with it and treat for at least 8 weeks. The ulcer won't heal reliably if they keep taking ibuprofen or naproxen, period. I've seen patients bounce back with recurrent bleeding because they thought "a few pills won't hurt" while still on their ulcer regimen.
Confirmation of eradication is where people cut corners. You do a urea breath test or stool antigen test at least 4 weeks after finishing antibiotics and off PPIs for 1–2 weeks. Testing too early gives false negatives. I once had a patient who was told they were cured two weeks after treatment ended, felt fine, stopped all medication, and came back three weeks later with melena. The test was falsely negative because the bacterial load had dropped below the detection threshold but hadn't been fully eradicated.
Refractory Ulcers And The Things Nobody Talks About
Sometimes the ulcer just doesn't heal. A small percentage of patients have refractory ulcers, and before you just increase the PPI dose, you need to rule out non-compliance, re-infection, Zollinger-Ellison syndrome, and gastric malignancy. Yes, you repeat the endoscopy. I've seen it missed multiple times because the clinician assumed a benign ulcer based on the first look and stopped investigating. There's also the issue of CYP2C19 rapid metabolizers. These people process omeprazole and esomeprazole so quickly that standard doses don't maintain adequate acid suppression. If a patient is adherent, tested negative for H. pylori, isn't taking NSAIDs, and still isn't healing on a standard PPI dose, switching to rabeprazole or vonoprazan can make a difference. Vonoprazan is a potassium-competitive acid blocker that doesn't depend on acid-dependent activation like PPIs do, so it works consistently across metabolizer types. It's newer and more expensive, but in stubborn cases it's been a reliable fallback. Another thing that catches people off guard: H. pylori-negative, NSAID-negative ulcers. They exist. The workup here is more extensive. You're looking at Crohn's disease, malignancy, vasculitis, infections like CMV in immunocompromised patients, or rare causes like hyperparathyroidism causing excessive acid secretion. I had a patient whose ulcer kept coming back at the same spot in the duodenal bulb despite perfect eradication therapy and complete NSAID cessation. The repeat endoscopy with deeper biopsies revealed a small duodenal adenocarcinoma that had been missed on the initial superficial samples. It changed everything about how I approach recurrent ulcers.
Get the Full Details
What Patients Actually Deal With
The antibiotic regimen for H. pylori is unpleasant. Tetracycline and metronidazole together cause metallic taste, nausea, and gastrointestinal upset in a significant number of people. Some patients stop the course early because of the side effects, which guarantees treatment failure and promotes resistance. I always warn patients upfront: the side effects are real but temporary, and finishing the full 14 days matters more than anything else. If the nausea is severe, splitting the dose or taking it with food helps, though food can slightly reduce absorption of some of these drugs. It's a balance. PPIs themselves are generally well tolerated, but long-term use has downstream effects. Chronic acid suppression alters the gut microbiome, reduces magnesium and B12 absorption, and has been associated with increased risk of community-acquired pneumonia and Clostridioides difficile infection. I tell patients we'll use the lowest effective dose for the shortest necessary duration. An uncomplicated duodenal ulcer typically needs 4 weeks of PPI after H. pylori eradication. A gastric ulcer may need 8 weeks. Beyond that, you're keeping them on maintenance therapy and the risk-benefit ratio shifts. Lifestyle advice gets overemphasized in patient discussions. Stress and spicy food don't cause peptic ulcers. They might aggravate symptoms temporarily, but they're not the underlying pathology. Patients will ask about diet repeatedly, and it's tempting to give a long list of restrictions, but the evidence doesn't support it. What actually moves the needle is eradication of H. pylori, discontinuation of NSAIDs, and consistent PPI use for the prescribed duration.