Why Most Post-Stroke Rehab Programs Stall Out
Three years ago I was working with a patient who'd had a right MCA stroke about eight months prior. Good motor recovery on the left side, but he kept falling when turning. Not because his balance was bad, but because his brain had stopped integrating visual spatial cues during rotation. We spent six weeks just doing weighted vest turns while tracking a laser point. He got it working. It took longer than I expected, but it worked. That's the thing about Therapy In Stroke Rehabilitation that nobody puts in the literature. It's not about protocols. It's about finding the one broken feedback loop and retraining it. The manuals say do 30 reps of upper extremity strengthening three times a week. What they don't say is what happens when the patient stops improving after week four and you have to figure out why.
Therapy In Stroke Rehabilitation: The Practical Side
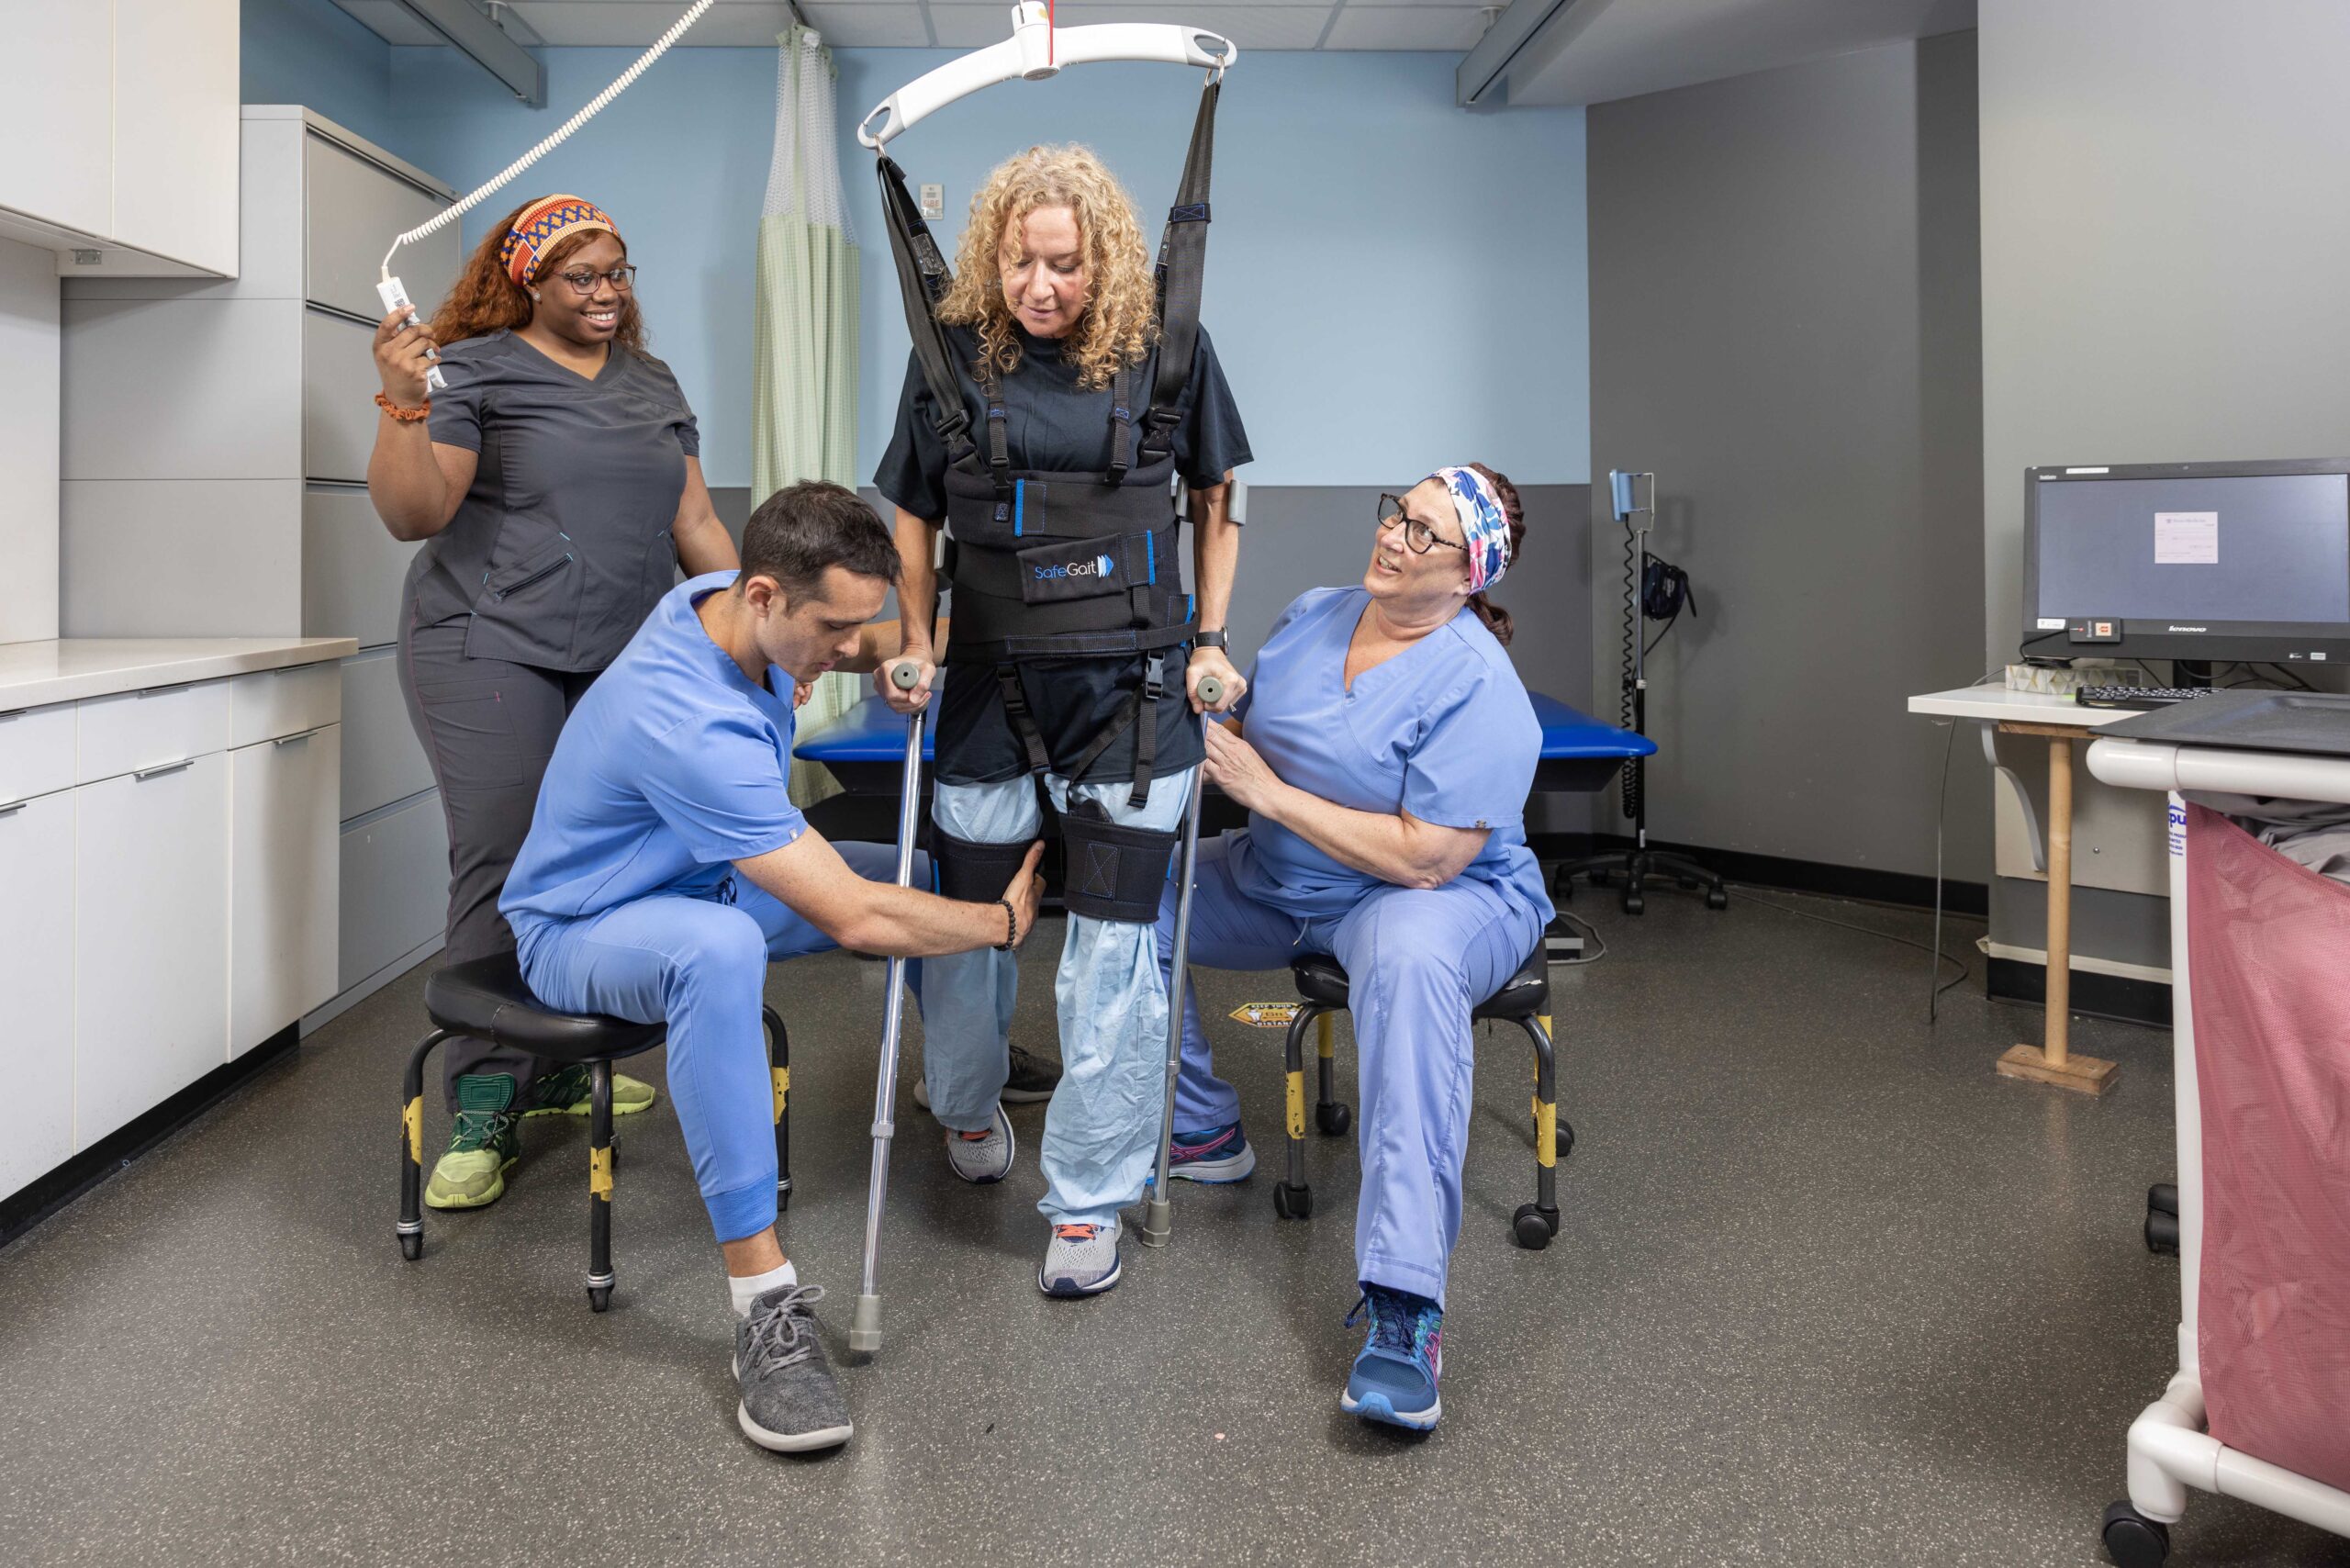
Stroke rehab covers a lot of ground. Motor recovery, speech, cognition, activities of daily living, emotional regulation. But the work falls into three buckets that most clinicians handle separately even though they overlap constantly. Motor relearning comes first for most patients. This isn't just exercises, it's task-specific practice that forces neuroplasticity to kick in. The classic approach uses constraint-induced movement therapy for upper extremity weakness, but that only works if the patient has some baseline movement to start with. If they're flaccid, you need to do something different, usually electrical stimulation paired with attempted movement to create central drive before you can load it. Gait training is where the equipment budget matters most. Body-weight supported treadmills help early on when balance is poor, but the evidence suggests that overground walking with perturbation training eventually beats the treadmill for real-world function. The treadmill is easier to manage in a clinic setting though, so most places use it as a bridge, not a destination.
Balance and coordination work is where people get sloppy. Yes, you need Berg Balance Scale scores and yes, you need fall risk assessments. But the actual training should be variable and unpredictable. Static standing on foam is fine for the first two weeks. After that, you're doing dynamic tasks with cognitive dual demands because that's what actually predicts community ambulation ability. A patient who can balance perfectly on a firm surface but collapses when you ask them to count backward by sevens while walking is still a fall risk. I've seen this repeatedly.
Get the Full Details

Speech and Cognition
Aphasia therapy has improved a lot since the old days of picture-naming drills. Melodic intonation therapy still has a place for non-fluent aphasia, especially early on when the right hemisphere can compensate for left hemisphere damage. But the newer work with computational language models in therapy apps is genuinely useful for building vocabulary and conversational practice between sessions. Cognitive rehab is harder to quantify. Executive function deficits after stroke don't respond to repetition the way motor deficits do. You need error-based learning, which means the patient has to make mistakes and then get feedback. Tabletop exercises with real-world problem solving work better than paper-and-pencil tasks. I started having patients plan actual meals with budgets and timing constraints instead of doing card sorting, and the transfer to independence was noticeably faster.
What Actually Moves the Needle
Intensity matters more than duration. Ten hours per week of focused therapy produces better outcomes than five hours spread across varied activities. That's not controversial anymore, but compliance is still a problem. Patients get tired. They get frustrated. They stop coming because the progress feels invisible week to week. The workaround is making progress visible through standardized outcome measures at every session. Motus, FIM scores, time-to-completion metrics. NothingMotivates like seeing a graph trend upward even when it feels like nothing is changing. We used to rely on subjective measures, which are fine, but they don't convince patients to keep showing up when they're having a bad week. Dual-task training is another one that's underutilized. Most stroke survivors struggle with automaticity. Walking and talking simultaneously becomes impossible because both tasks demand conscious attention. Training this early in rehab, not after gait speed has normalized, reduces fall risk in community settings by about forty percent according to recent meta-analysis data.
The Equipment Question
You don't need robot exoskeletons to get good outcomes. Mirror therapy costs thirty dollars and works for phantom limb pain and corticospinal tract damage. Virtual reality headsets are expensive, but tablet-based VR apps are cheap now and provide enough feedback for motor learning. The best tool is the one the patient will actually use consistently. Exoskeletons like the Lokomat have their place for severe gait deficits, but the evidence shows they're not superior to overground training with manual assistance once the patient can bear weight. The cost-benefit doesn't work for most clinics. Spend the money on more therapist hours instead.

Emotional and Behavioral Support
Post-stroke depression affects about a third of survivors and it's the single biggest predictor of poor rehab participation. Screening every two weeks with the PHQ-9 or the hospital anxiety and depression scale catches it early. Referring to psychiatry for SSRI management and combining that with behavioral activation therapy improves outcomes more than either intervention alone. Emotional lability, the pseudobulbar affect that makes patients laugh or cry uncontrollably, is treatable. Dextromethorphan-quinidine combo (Xenazine) helps about sixty percent of patients. The rest respond to behavioral strategies like paced breathing and environmental modification to reduce triggers.
When Therapy Stops Working
Sometimes you hit a wall. The patient isn't improving despite appropriate intensity and technique. This usually means either the lesion location limits recovery potential, or there's an undiagnosed complication like spasticity, shoulder subluxation, or pain that's interfering with participation. I once spent four weeks trying to improve ankle dorsiflexion in a patient who actually had subtle subclinical spasticity that wasn't showing on exam. Botox injection resolved it and we got three weeks of progress in three days. If you're not seeing measurable change over two consecutive weeks, reassess. Change the approach, not just the exercise selection. Sometimes switching from massed practice to distributed practice with longer rest intervals actually improves retention because the nervous system needs consolidation time.
Home Programs and Long-Term Maintenance
The rehab gym hours don't matter if the patient doesn't keep practicing at home. Simple home programs with video demonstrations work better than written instructions. I recommend ten minutes of targeted practice daily rather than thirty minutes twice a week because consistency beats volume for motor learning. Apps that track completion and send reminders improve adherence by about twenty-five percent compared to paper-based programs. The goal is independence, not permanent therapy dependence. Most stroke survivors reach their plateau within six months, but function continues to improve for years with continued practice. The difference between someone who walks independently at twelve months and someone who relies on a cane usually comes down to whether they kept doing weight-bearing activities after formal therapy ended. Discharge planning should start on day one of admission. Identify what the patient will need at home, assess the home environment for safety, and connect them with community resources before they leave. Outpatient therapy frequency can taper from three times weekly to twice weekly to once weekly over eight to twelve weeks depending on progress. There's no universal timeline that fits every case.

Practical Takeaways
Focus on task-specific training that mirrors real-world demands. Don't separate motor from cognitive from emotional work, they all interact. Make progress visible to the patient. Screen for depression early and treat it aggressively. Reassess when progress stalls. Invest in equipment that improves adherence, not just fancy machines that sit unused. The best therapists I know aren't the ones who memorized every protocol. They're the ones who watch closely, adjust quickly, and understand that every stroke is different enough that blind protocol adherence will fail sometimes. The evidence base guides you, but the patient in front of you tells you what actually works. If you want to dig deeper, the American Heart Association's stroke rehab guidelines have updated recommendations, and the Cochrane reviews on constraint-induced movement therapy and gait training are solid. But the real learning happens in the clinic, adjusting techniques when the textbook answer doesn't fit the person sitting in front of you.


