A Practical Guide to Mirror Therapy for Phantom Limb Pain
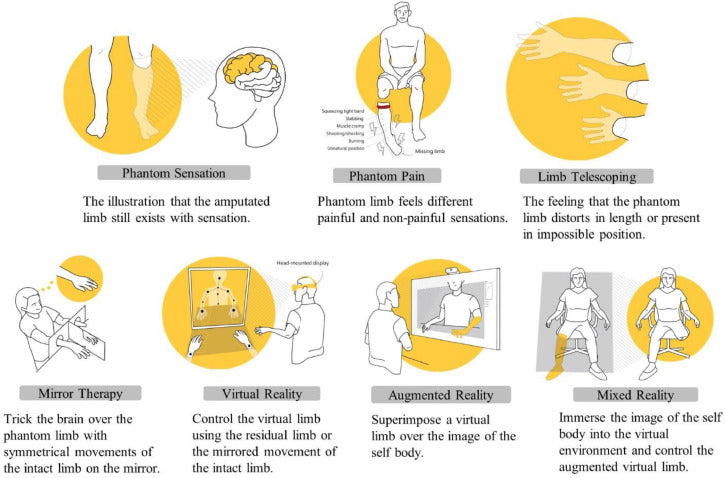
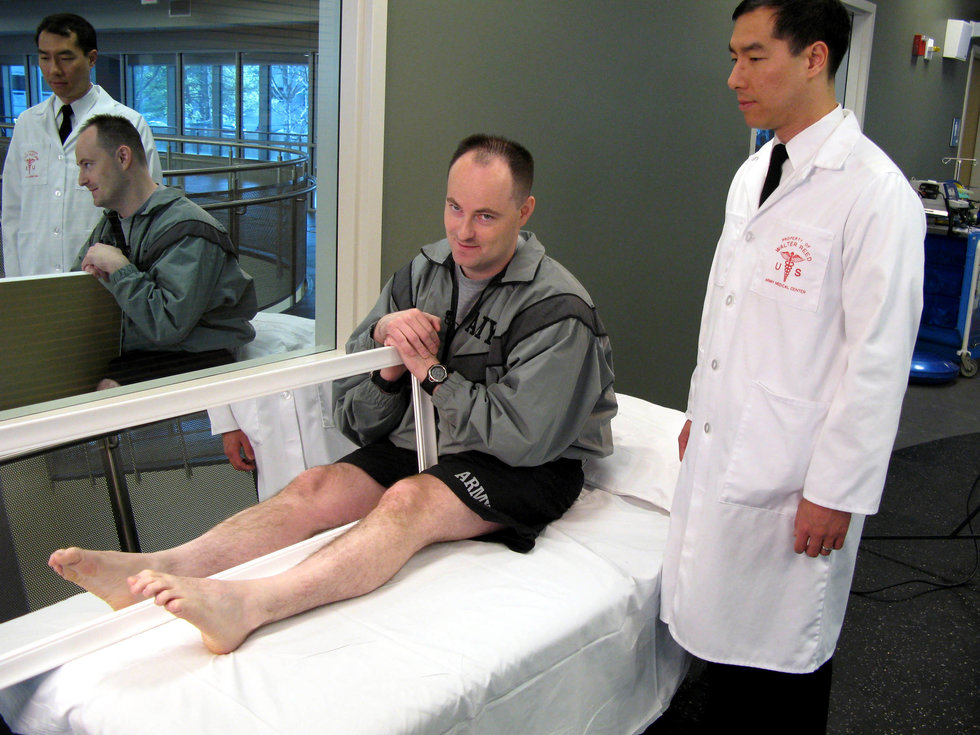
Phantom limb pain is one of those conditions that people outside the field completely misunderstand. They think you're imagining the pain because the limb is gone. You're not. The nerves are still firing. The brain map is still there, and it's screaming. I spent years working with amputee patients on exactly this, and I can tell you that getting it right changes lives. Getting it wrong just wastes everyone's time. The mirror box technique was developed by V.S. Ramachandran in the 1990s and it remains the single most effective non-invasive intervention we have. The setup is simple: you sit at a table with a vertical mirror dividing the surface. You place your intact limb on one side and your residual limb on the other. You look into the mirror so that the reflection of your intact limb appears where the missing limb should be. When you move the intact limb, the reflection moves in perfect symmetry, and the brain receives visual feedback that the missing limb is moving without pain. Here's what most guides don't tell you about the actual experience. The first session rarely produces dramatic results. That's normal. What you're doing is basically retraining a deeply entrenched neural pathway. The brain has been receiving nociceptive signals from a limb that no longer exists for months or years. Asking it to accept a new visual input on day one is optimistic at best. Most patients report some reduction in pain intensity after about six to eight sessions, and the effect compounds over time. I've seen patients go from a baseline pain level of 8 out of 10 down to around 4 after consistent practice over several weeks.
The protocol I use and recommend is fairly structured. The patient sits comfortably with the mirror positioned vertically between the limbs. The intact limb performs slow, deliberate movements — gentle flexion and extension, rotation, opening and closing the hand. The key is that the movements should be slow enough that the reflection perfectly matches what the brain expects. Speed matters more than people realize. Fast movements create a mismatch between proprioceptive feedback and the visual reflection, and that mismatch can actually trigger or worsen the pain spike. Thirty minutes per session, twice daily, is the standard I work with. Anything less and you're not giving the neural recalibration enough repetition to take hold. One thing that trips people up consistently is the positioning of the mirror. If the mirror isn't perfectly perpendicular to the table surface, the reflection tilts and the brain registers an immediate anomaly. I've had patients abandon the therapy entirely because they set the mirror at a slight angle without realizing it. Use a protractor if you need to. A thirty-second check saves weeks of frustration.
Common Mistakes That Undermine Results
Patients often push through pain during a session thinking it means the therapy is working. It doesn't. Pain during mirror therapy usually means one of two things: either the movement you're performing on the intact limb reproduces the same motor pattern that triggers the phantom pain, or the visual feedback isn't convincing enough and the brain is rejecting the illusion. In both cases, you stop and adjust. The goal is gentle exposure, not endurance. Another issue I encounter regularly is that patients expect the pain to disappear completely after a few sessions. That's not how this works. Mirror therapy reduces the frequency and intensity of pain episodes. It doesn't erase the condition. Some patients benefit significantly. Others see modest improvement. A small subset sees little to no benefit, and that's a real limitation of the approach that nobody likes to discuss openly. If you've completed twelve sessions over three weeks with no change whatsoever, it's worth discussing alternative interventions with your provider rather than continuing to push the same protocol indefinitely. I remember one patient specifically — a veteran who'd lost his right leg below the knee. He had severe phantom pain that hadn't responded to medication. We started him on mirror therapy and he was disciplined about it, doing his sessions every day without fail. After about four weeks, he reported that the pain had shifted from constant to intermittent, which was a meaningful improvement. But then he hit a wall. The mirror box stopped producing results. What finally helped him was combining the mirror therapy with graded motor imagery — first imagining left and right foot movements, then progression through explicit imagery tasks. The mirror box alone had gotten him most of the way there, but the combination pushed him over the edge. That's an important nuance: mirror therapy works best as part of a broader protocol, not as a standalone solution.
Get the Full Details

What You Need to Get Started
You don't need expensive equipment. A full-length mirror, a sturdy table, and some tape to secure the mirror in place will work. I've seen patients use bathroom mirrors and wooden crates with surprisingly good results. The mirror needs to be tall enough that you can see the full reflection of your intact limb while seated. If you're missing an arm, for example, the mirror should show your entire arm and hand clearly. If you'd like a pre-built option, there are several commercial mirror therapy boxes available online. The basic models run between forty and eighty dollars. They're functionally equivalent to a DIY setup but save you the effort of constructing one. For patients who are serious about this therapy, I'd suggest investing in a proper box rather than trying to improvise for too long. The alignment and stability matter more than the aesthetics. There's also software-based alternatives now. Some VR applications simulate the mirror box experience digitally, and early research suggests comparable outcomes for certain patients. I haven't used them extensively enough to recommend one over the other, but they're worth exploring if you've plateaued with traditional mirror therapy or if finding a physical setup is impractical for you.
The Realistic Timeline and Expectations
Most patients should expect to commit to at least eight to twelve weeks of consistent practice before evaluating whether the therapy is working for them. The first two weeks are often the least productive. Your brain is still processing the new sensory information. Between weeks two and six, you may start noticing subtle changes — pain episodes become shorter, the intensity drops slightly, the space between flare-ups widens. After six weeks, the trend usually becomes more obvious if it's going to happen. Pain medication doesn't interfere with mirror therapy in a harmful way, but it can mask the feedback you need to calibrate your sessions. If you're taking strong analgesics, note your baseline pain level before starting and track changes weekly rather than relying on moment-to-moment perception during sessions. The numbers don't lie the way your mood does. I should also mention that mirror therapy isn't appropriate for everyone. Patients with certain types of residual limb neuromas, active infection at the amputation site, or severe cognitive impairment may not benefit or could potentially be harmed by the approach. A brief consultation with a physical therapist or pain specialist before beginning is standard practice and honestly just smart. The last thing anyone needs is to waste months on something that won't work for their specific condition when other options exist.