The Three Pillars Of Evidence Based Practice
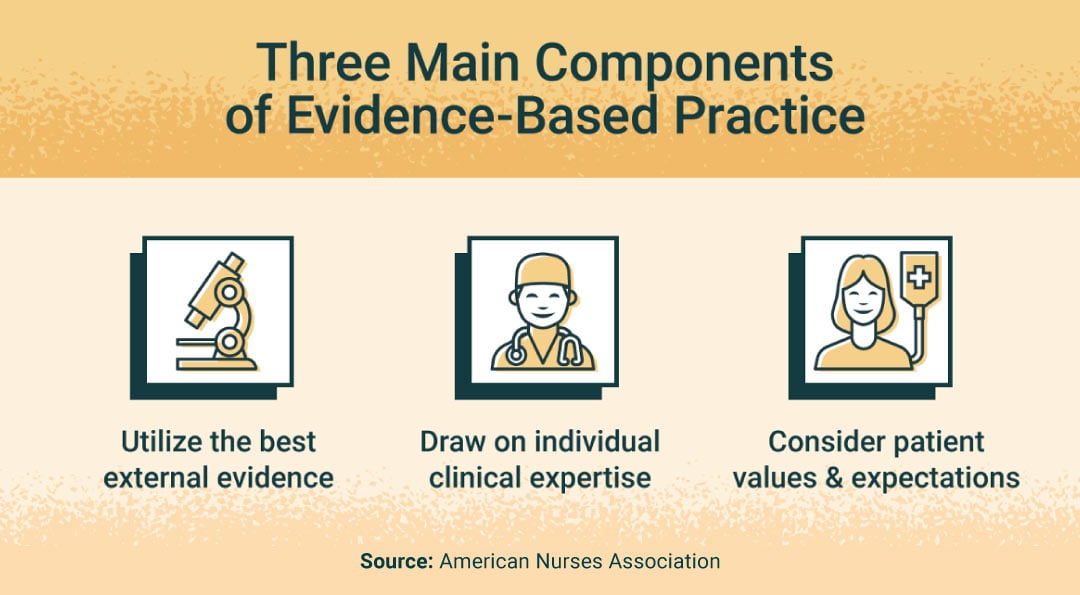
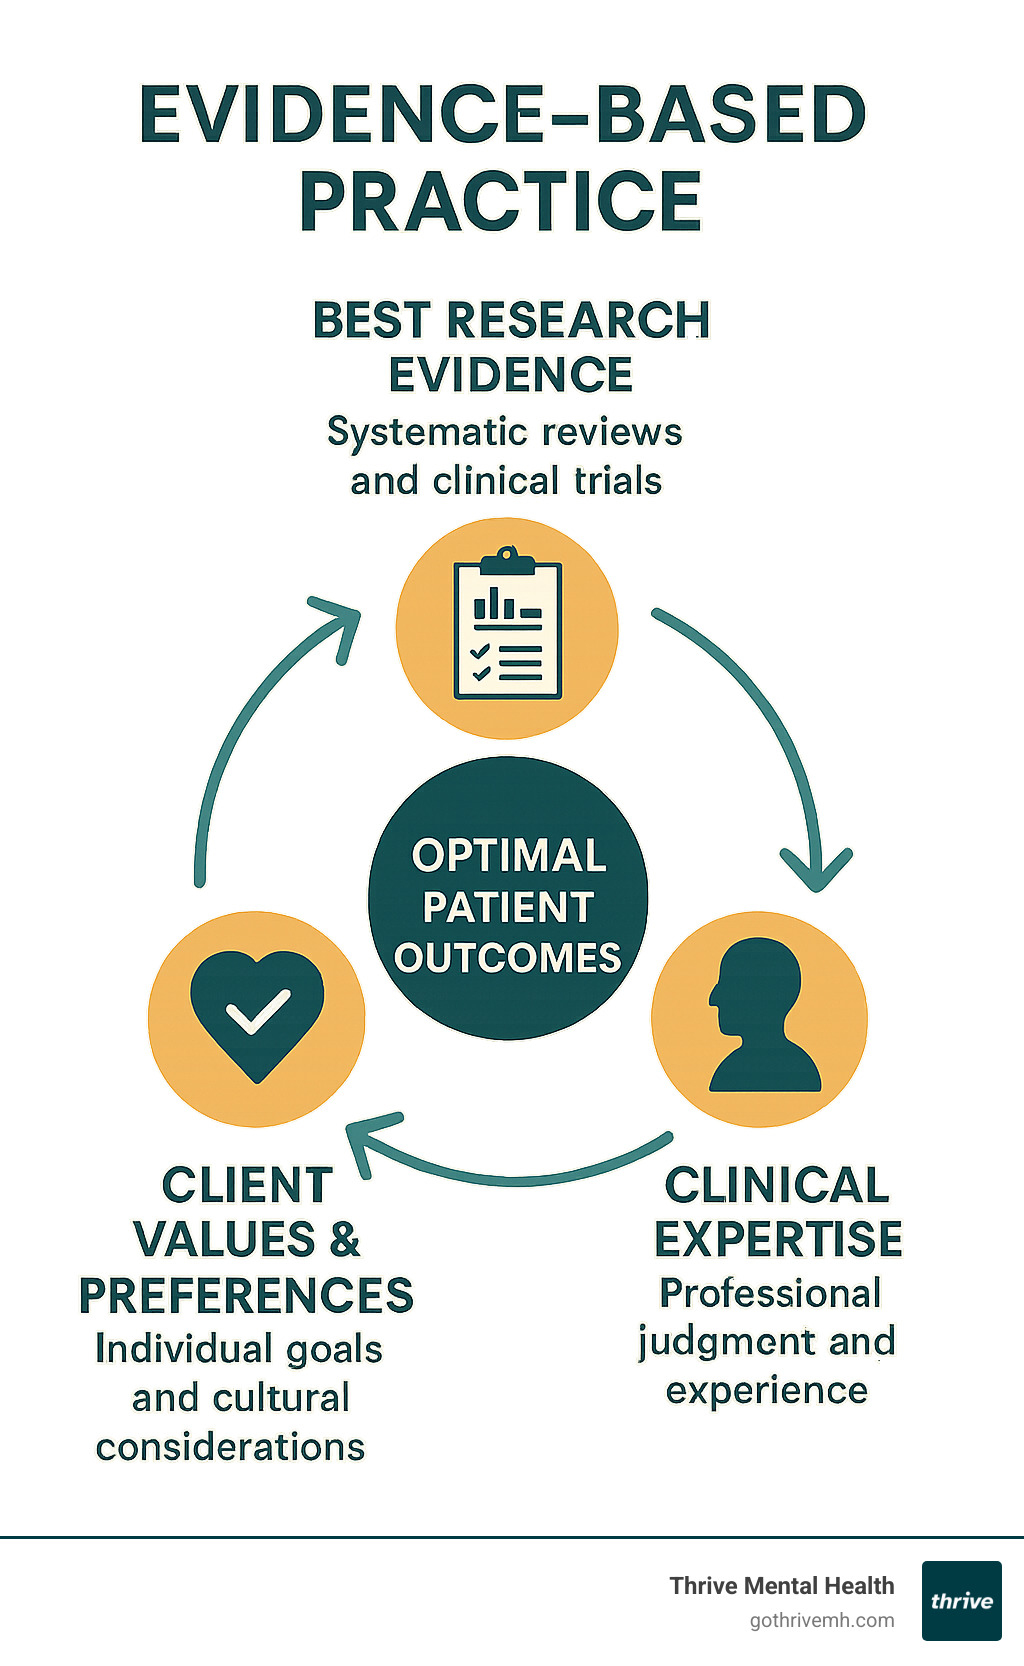
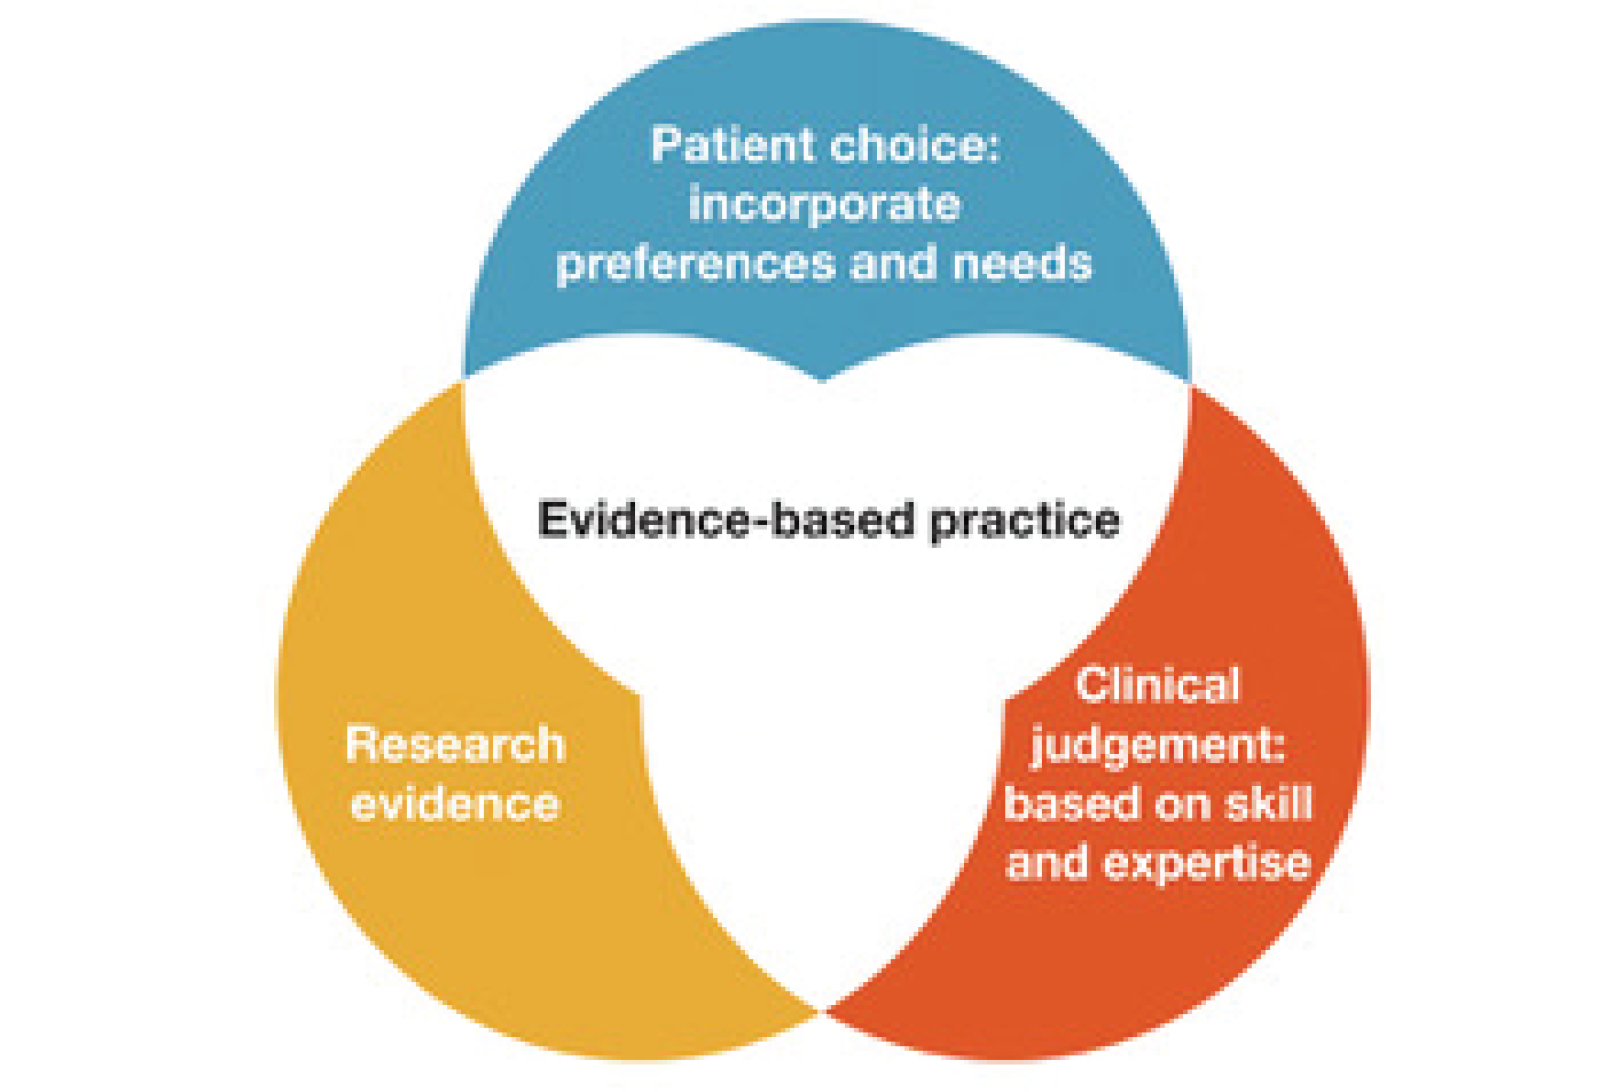
I spent about four years in clinical research before moving into practice management, and I watched plenty of people get this concept wrong. The Three Pillars Of Evidence Based Practice is usually taught as a clean triangle in PowerPoint slides, but in reality it is more like juggling three objects while someone keeps changing the rules. Most introductory courses break it down into three buckets. Research evidence sits at the top because it is easiest to measure. Your own clinical experience forms the second pillar. The third pillar is patient or client values and circumstances. That part sounds simple until you deal with a case where the research says one thing, your experience contradicts it, and the client wants something else entirely. I saw a situation last year where a standard protocol for lower back pain involved a six-week physical therapy course before considering imaging. The research supports that approach for non-specific back pain. My experience told me the particular patient was not improving because of a different underlying cause. The patient wanted an MRI because their neighbor had one and it helped. All three pillars were pulling in different directions. I ended up ordering the imaging anyway after documenting the rationale and getting informed consent. That is how it usually works.
How to actually use this in practice
The first thing you need to do is stop treating the three pillars as equal weights. They are not. Research evidence should carry the most weight when the evidence is strong and recent. When the evidence is weak, older, or conflicts with other studies, your clinical experience and the client's situation take over more of the decision-making load. Here is how I structure a decision. I start by looking at the best available research for the specific condition or problem. I check the date of the studies, the sample sizes, and whether the findings come from systematic reviews or single small trials. A Cochrane review published two years ago is worth more than five individual studies from fifteen years ago. Then I compare that to what I have seen in my own practice. Finally, I bring in the client's context, which includes their preferences, their resources, their schedule, and their goals. This process usually takes me about twenty to thirty minutes for a routine case. A complicated case with conflicting evidence can take two to three hours of literature review alone. There is no shortcut around that part.
Common mistakes that wreck the process
The biggest mistake I see is relying too heavily on one pillar and ignoring the others. Some practitioners treat research as gospel and skip the client conversation entirely. They prescribe exactly what the guideline says without asking whether it fits the person in front of them. That approach fails frequently because guidelines are written for populations, not individuals. The reverse mistake happens too. Experienced clinicians sometimes trust their own intuition over solid research and dismiss well-conducted studies as irrelevant. Personal anecdotes are not data. I have corrected my own bias several times after reviewing newer evidence that contradicted my long-held assumptions. It is uncomfortable but necessary. A third pitfall is treating the client pillar as simply doing whatever the client asks. It is not. Client values matter, but they also need to be educated. Sometimes the best outcome comes from explaining why a certain approach has better support and guiding the client toward a decision that aligns with both the evidence and their preferences.
Get the Full Details
A detail most guides leave out
One thing rarely discussed is how the pillars interact when evidence is missing. In many real-world situations, there is no strong research for the exact scenario you are facing. You might have general guidelines for a condition, but your client has comorbidities or unique circumstances that the studies did not cover. In those cases, you lean harder on clinical expertise while remaining transparent with the client about the uncertainty. You document the reasoning clearly. You monitor outcomes closely and adjust based on what you observe. This is where the model becomes more art than science, and it is also where good practitioners separate themselves from the rest. I should be honest about the limitations. This framework assumes you have access to current research, which is not always true in underfunded settings or rural practices. It also assumes you have the time to review evidence properly, and that is a luxury many clinicians do not have. When you are seeing thirty patients a day, you cannot conduct a full literature review for every case. You develop heuristics and rules of thumb, which is practical but introduces its own risks. Another issue is that patient values are difficult to standardize. Two clients with the same diagnosis can have completely different priorities. One might value avoiding medication side effects over maximum effectiveness. Another might want the most aggressive treatment available regardless of risk. The framework handles this in theory but requires skill and patience to execute well in practice.
If you find the research component overwhelming, start with systematic reviews and clinical practice guidelines from reputable organizations. They do the heavy lifting for you. Filter them through your experience. Discuss the options openly with your client. Repeat the process with each new case. The method is straightforward. Execution is where the work actually happens.