Understanding What Actually Moves Your Body
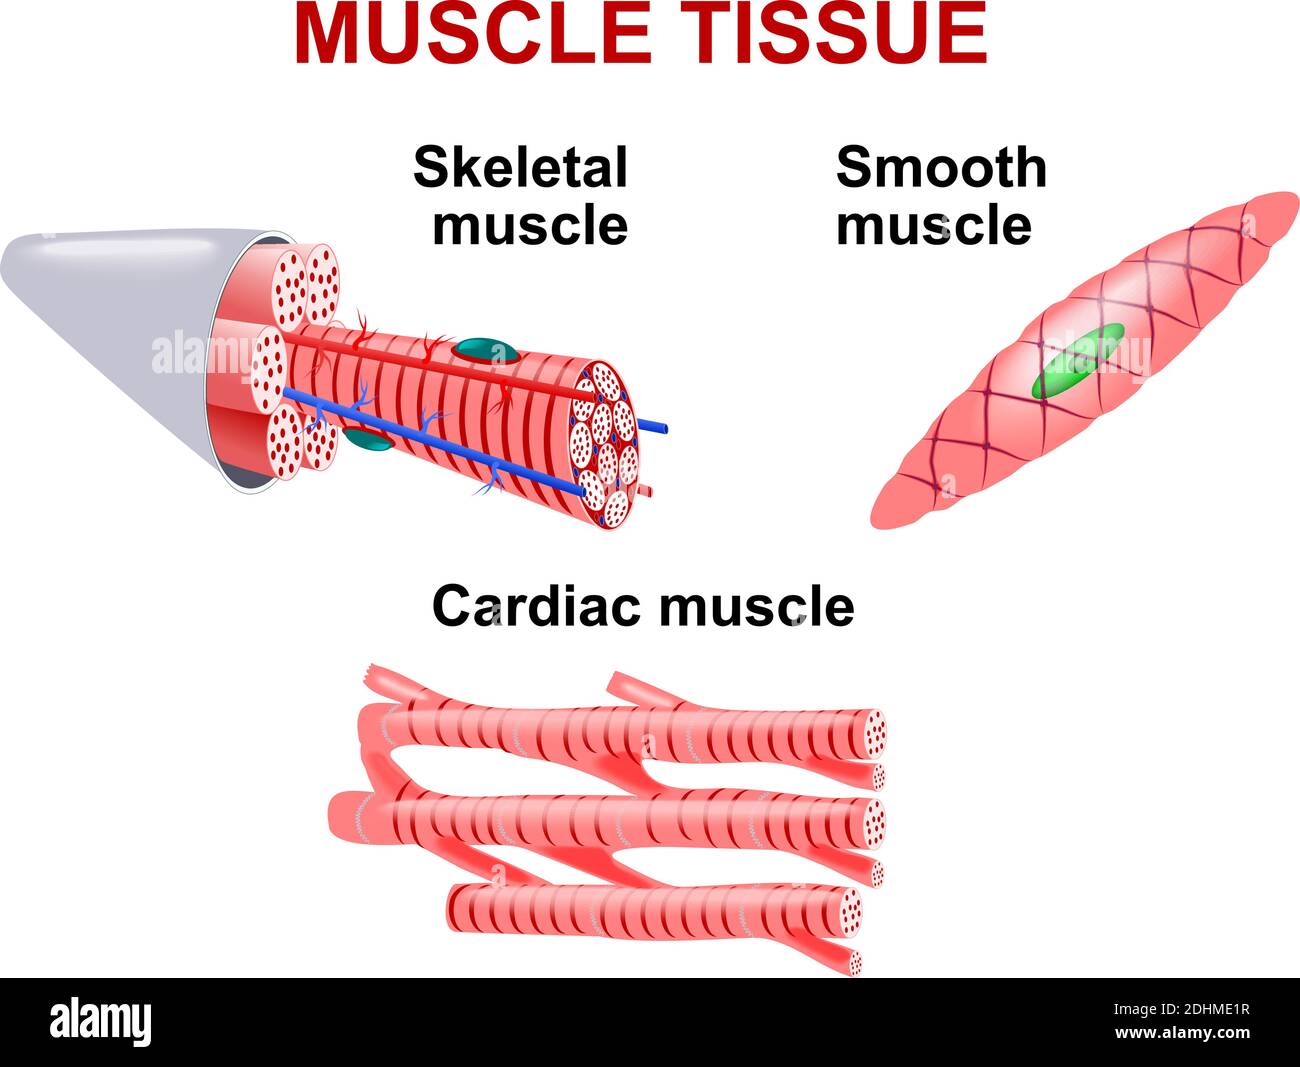
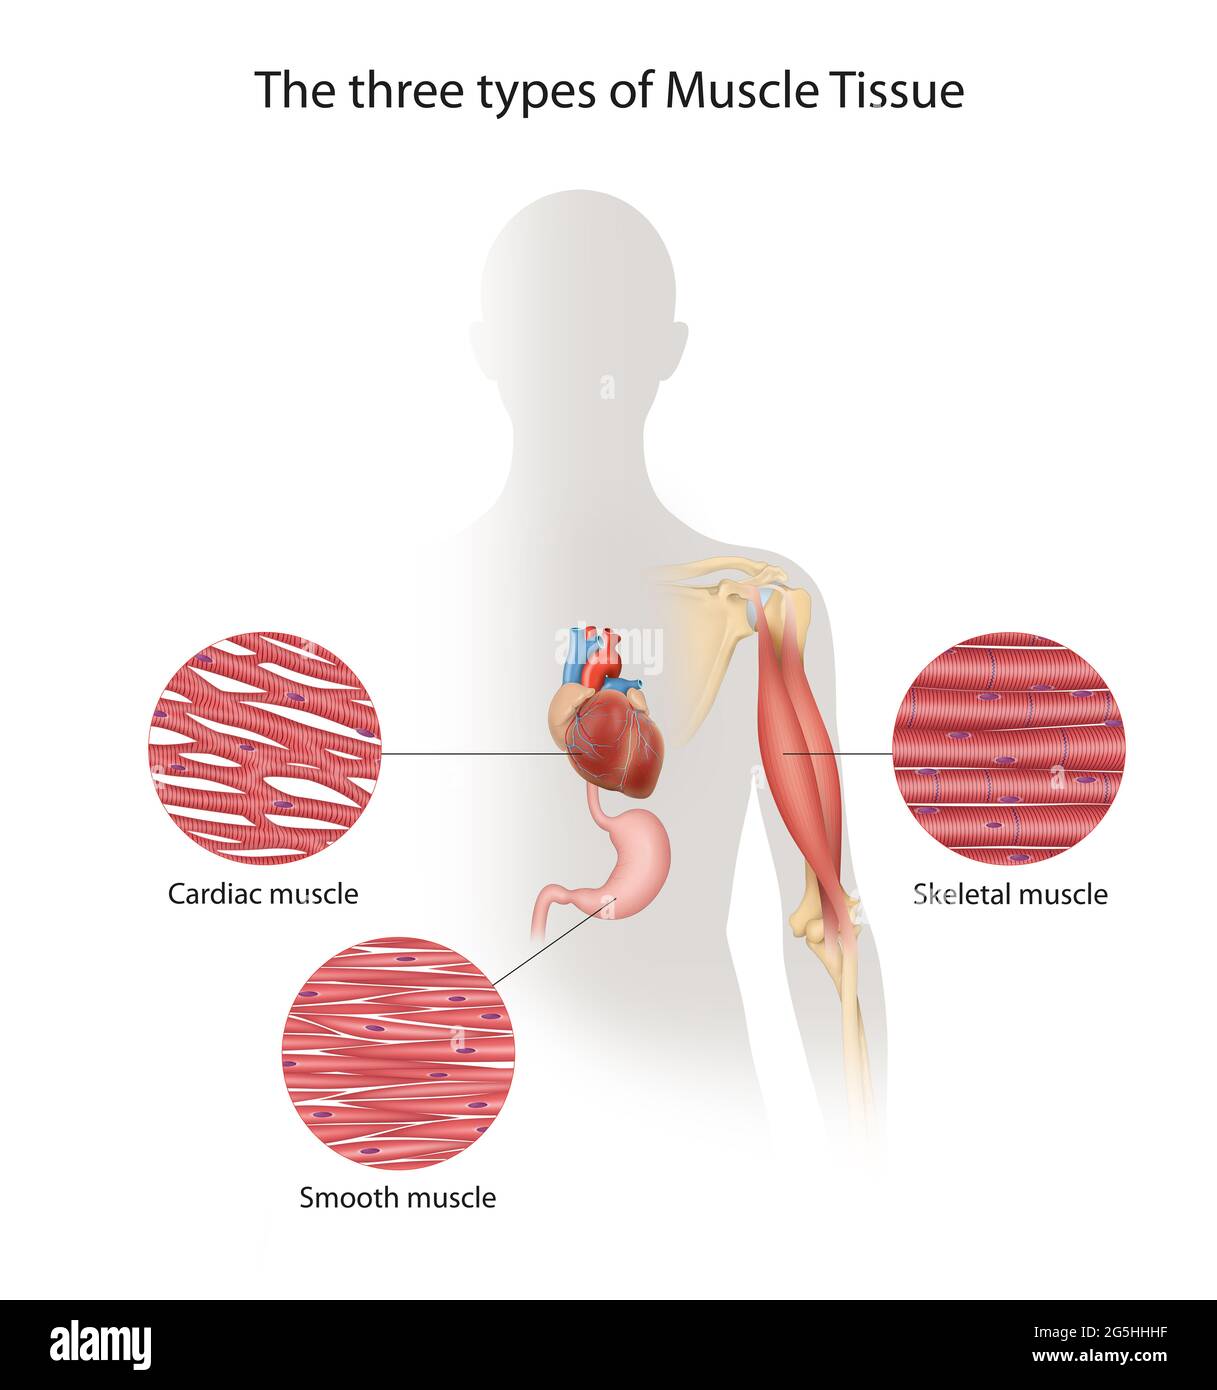
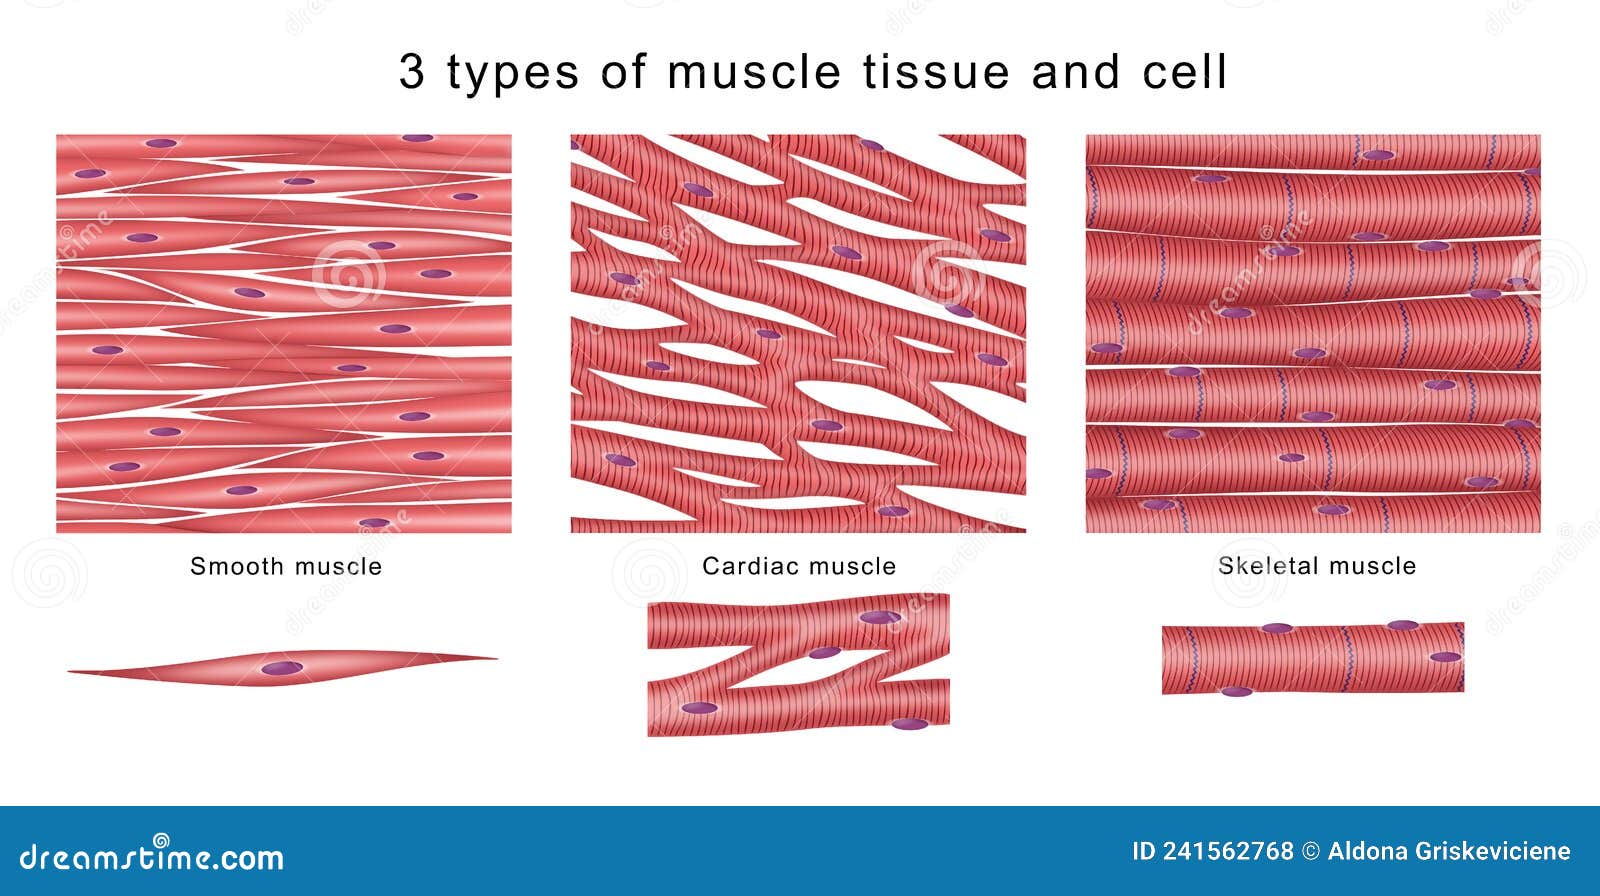
Most people learn about the three types of muscle tissue in a single biology lecture and never think about it again. That is a mistake if you are studying movement, recovery, or anatomy at any practical level. The three types of muscle tissue are skeletal, cardiac, and smooth, and each operates on completely different principles. Getting confused between them leads to real errors in how you interpret training adaptations, medical symptoms, and even basic physiology questions. Skeletal muscle is what most people picture when they think about muscles. It attaches to bones, it is striated under a microscope, and it is under voluntary control. You can move it when you decide to. But that voluntary control is a relatively thin layer over something that is mostly automatic in daily operation. I spent months studying motor unit recruitment patterns and realized something most beginners miss: skeletal muscle fibers do not all fire at once. They recruit in size order, starting with the smallest, slow-twitch Type I fibers before recruiting the bigger, faster Type II fibers. This is called the Henneman size principle, and it matters for everything from endurance training to heavy lifting. If you are always training in the same rep range, you are only partially exercising these tissues. Cardiac muscle is its own separate category. It is also striated, which means it shares that banded appearance with skeletal muscle under magnification, but the cells are interconnected by intercalated discs. Those discs contain gap junctions that allow electrical signals to pass directly from one cell to the next. The heart contracts as a functional syncytium because of this arrangement. One cell firing triggers the rest. This is why cardiac tissue has such remarkable automaticity. The sinoatrial node sets the rhythm without any conscious input from you. I once had a student argue that the heart could be "trained" to beat more slowly through sheer willpower. It cannot. Vagal tone influences heart rate, yes, but you cannot consciously override the pacemaker cells the way you can consciously move your arm.
Smooth muscle is the one people consistently underestimate. It lines hollow organs, blood vessels, the digestive tract, the airways, and the uterus. It is non-striated, meaning the actin and myosin filaments are arranged differently than in the other two types. There are no sarcomeres. Smooth muscle contracts more slowly but can maintain tension for much longer periods without fatiguing. This is why your blood vessels can constrict or dilate over hours and why your digestive tract keeps moving food along without you thinking about it. The enteric nervous system alone contains roughly 500 million neurons, which is more than the spinal cord. Some researchers call it the second brain for exactly this reason. Here is a practical problem I ran into that illustrates why the distinctions matter. A client came to me reporting persistent upper abdominal tightness and occasional nausea after intense core workouts. They assumed they had strained their rectus abdominis. When I asked more specific questions about meal timing and bowel habits, it turned out the issue was smooth muscle related, not skeletal. Their workout routine was creating significant intra-abdominal pressure right after eating, which was compressing the stomach and interfering with normal gastric smooth muscle contractions. The fix was simple: shift heavy core work to a separate session from meals, at least three hours apart. The abdominal pain resolved within a week. If I had just treated it as a skeletal muscle strain and recommended rest and ice, it would have lingered much longer. One counter-intuitive thing about smooth muscle that textbooks often gloss over is the length-tension relationship. In skeletal muscle, there is an optimal sarcomere length where force production is maximized, and deviating from that length reduces force. Smooth muscle does not work that way. It can maintain near-maximal tension across a much wider range of lengths. This is why your bladder can hold varying volumes and still generate effective contractions, and why blood vessels can constrict properly whether they are full or nearly empty. This property is called stress-relaxation response, and it is unique to smooth muscle among the three types.
Another nuance people miss involves the energy systems supporting each tissue type. Skeletal muscle fibers vary dramatically. Type I fibers rely heavily on aerobic metabolism with abundant mitochondria and myoglobin, which is why they appear red. Type IIx fibers are glycolytic, fatigue quickly, and appear paler. Cardiac muscle is almost exclusively aerobic. It cannot tolerate well, which is why coronary artery blockages are so immediately dangerous. Smooth muscle sits somewhere in between, using both aerobic and anaerobic pathways depending on the organ and the demand. If you are designing a rehabilitation protocol or a training program without considering which energy system each fiber type depends on, you are likely optimizing the wrong variable. The practical takeaway here is straightforward. When you study or assess any movement-related issue, the first question should not be "which muscle is involved." It should be "what type of muscle tissue is involved and how does that change everything about how it behaves." Skeletal muscle responds to progressive overload. Cardiac muscle responds to sustained aerobic demand. Smooth muscle responds to chemical signals, stretch, and autonomic input. Treat them as interchangeable and you will misunderstand a lot of what is happening in the body.
Get the Full Details