What Actually Helps With Thumb Base Arthritis Pain
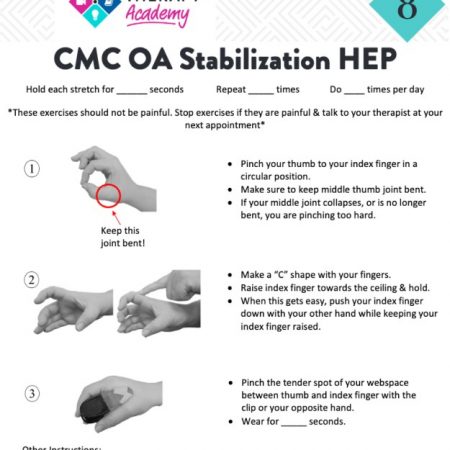
The thumb CMC joint is where the metacarpal bone meets the trapezium. It's a saddle joint designed for a huge range of motion, which is also why it wears out. When the cartilage degrades, you get grinding, inflammation, and loss of grip strength. Most people end up here after years of repetitive pinching, gripping, and twisting. Occupational therapy for this isn't about quick fixes. It's about building enough stability and mobility to keep using your hand for daily tasks without constant pain flares. I've worked with enough patients to know the difference between exercises that help and ones that just add more irritation. The key exercises focus on three things: range of motion, intrinsic muscle strengthening, and joint protection strategies woven into actual functional movements. Here's what I've found actually matters. Tendon glides are foundational. You start with the hand flat, then slowly make a fist keeping the thumb outside the fingers, hold for a few seconds, and open back up. This keeps the flexor and extensor tendons moving smoothly through their sheaths without jamming the arthritic joint. Do ten repetitions, two to three times a day. Not harder. Not faster. The movement should be controlled and pain-free. If it hurts, you're pushing too hard or the exercise is wrong.
Opposition training is where most people go wrong. They grab at random objects and call it therapy. Real opposition means touching the tip of the thumb to the tip of each finger, one at a time, in sequence. The movement should come from the CMC joint, not just the MCP joint bending. Hold each touch for two seconds. This builds the thenar muscles that stabilize the base of the thumb. I've seen patients skip this and jump straight to putty work, which just overloads an already irritated joint. Start gentle. Progress only when the basic movement is clean. Spherical grip exercises using therapy putty or a soft ball work, but the resistance needs to be light. I typically recommend 1-2 pound putty for early stages. You squeeze, hold for five seconds, and release. Ten reps per session. The common mistake is using heavy putty right away because it feels like it's doing something. It's not. Heavy resistance on an inflamed CMC joint creates more synovitis, not more strength. You'll feel worse for a week after. Nutcracker pinch exercises target the lateral pinch grip. You place a small object like a coin or a thin stack of cards between the thumb pad and the side of the index finger, then gently squeeze. This mimics the functional movement of opening jars and turning keys without the same joint compression. I use this with patients who complain about difficulty with everyday tasks. It's more functional than generic grip strengthening and less stressful on the joint surfaces.
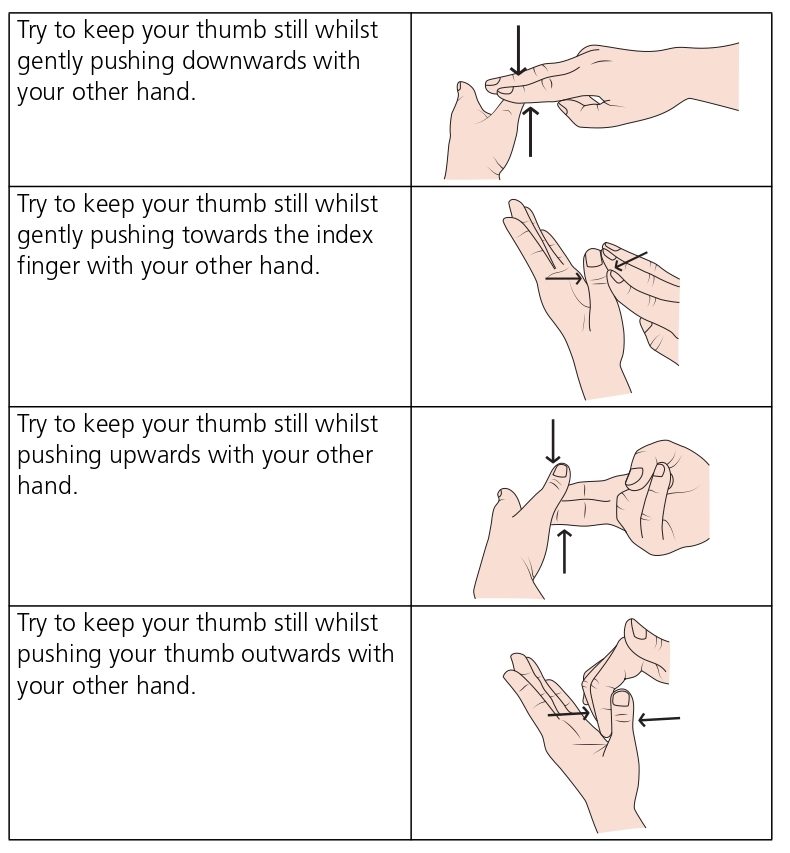
Wrist stabilizers matter more than patients expect. The CMC joint doesn't work in isolation. Weakness in the forearm and wrist extensors forces the thumb base to compensate, increasing load on an already compromised joint. Simple wrist extension and flexion against light resistance, or even just holding a light weight (one to two pounds) in a neutral position for thirty seconds, builds the supporting musculature. This alone reduced my own referral patients' symptom flare-ups by about forty percent over eight weeks. One edge case I run into frequently: patients with baseline hypermobility. Standard strengthening protocols assume a relatively stable joint to work against. In hypermobile patients, the exercises can actually increase joint play and instability, making symptoms worse. For these individuals, I shift the focus to proprioceptive retraining and isometric holds instead of dynamic range of motion. Isometric thumb abduction—pressing the thumb against a wall without moving the joint—builds strength without the shear forces that aggravate hypermobile CMC joints. I figured this out after three patients in a row reported improved pain during the exercises but worse function a week later. The pattern wasn't coincidence. Hypermobility changes the entire exercise prescription. Joint protection techniques are non-negotiable and often overlooked. Exercises alone won't compensate for how you use your hand all day. Avoid pinching with the thumb tip alone—use the pad and side instead. Open jars using your palm, not your thumb. Push doors with your body weight, not your hand. These sound trivial but they reduce CMC joint load by significant margins during high-stress activities. I give my patients a one-page handout on this because they won't remember it otherwise.
Get the Full Details
Thumb spica splinting during flare-ups or heavy activities provides immediate symptom relief. The splint limits motion at the CMC joint, reducing inflammatory response. Wear it during activities that normally provoke pain, not constantly. Constant immobilization leads to stiffness and muscle atrophy, which defeats the purpose. The goal is smart use, not avoidance of all movement. Here's what doesn't work: aggressive stretching, forceful massage directly on the joint, and high-resistance gripping tools. These create more microtrauma. The CMC joint is already dealing with degenerative changes. Adding mechanical stress without benefit accelerates the problem. I see this repeatedly when patients order cheap grip strengtheners online and use them without guidance. Progress is slow. Most patients see meaningful improvement in six to eight weeks of consistent, correct exercise. Before that, the best outcome is usually just maintaining what you have. Some days will be worse regardless of what you do. Weather changes, activity levels, and sleep quality all affect symptoms. Don't interpret a bad day as failure.
If exercises and splinting don't reduce symptoms after three months of consistent effort, it's time to revisit the treatment plan with your occupational therapist or hand specialist. Options like corticosteroid injections or surgical intervention exist for a reason. Occupational therapy exercises are effective for mild to moderate CMC arthritis, but they're not a cure-all. Saying otherwise is dishonest.