What Actually Happens With Trigger Thumb
Trigger thumb is a mechanical problem, not an inflammation problem the way most people think. The flexor tendon gets caught on the A1 pulley at the base of the thumb. When you bend your thumb, the nodule on the tendon slides through. When it gets stuck, you have to use your other hand to pop it straight. That click or catch is the tendon wrestling past a narrowed passage. Exercises won't cure a structural narrowing. They help when the issue is early stage, mild, or part of a broader overuse pattern. If you've been dealing with occasional catching for a few weeks without surgery or steroid injections, targeted movement can sometimes reduce symptoms enough that you avoid escalation. I wouldn't promise that, but it's the reality of where this sits in treatment hierarchy.
Thumb Exercises For Trigger Thumb: The Practical Routine
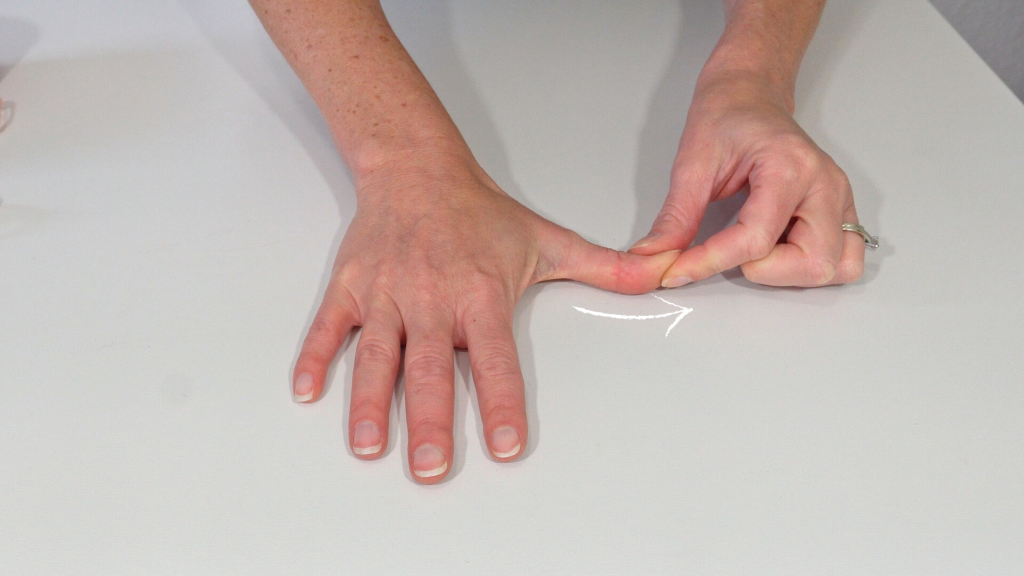
The exercises fall into three buckets. Extension work, gentle glide mobilization, and grip retraining. Do them in that order. Here's what I actually had patients do during the conservative management window. Use your other hand to gently pull the thumb back until you feel a stretch along the palm side at the base joint. Hold for 30 seconds. Repeat three times. The key detail most people miss is direction. Pull straight back, not out to the side. Lateral stretch just loads the ulnar collateral ligament and does nothing for the flexor tendon glide. This one comes from the original Veltri and Strickland work on finger tendon rehabilitation, and yes it translates to the thumb. Start with your hand flat. Curve just the tip into a hook. Then straighten to a full fist. Then make a tabletop position where the knuckles bend but fingers stay straight. Finally open flat again. Five reps, twice a day. Not hard. Not fast. The goal is teaching the tendon to track smoothly through the pulley system under low load.
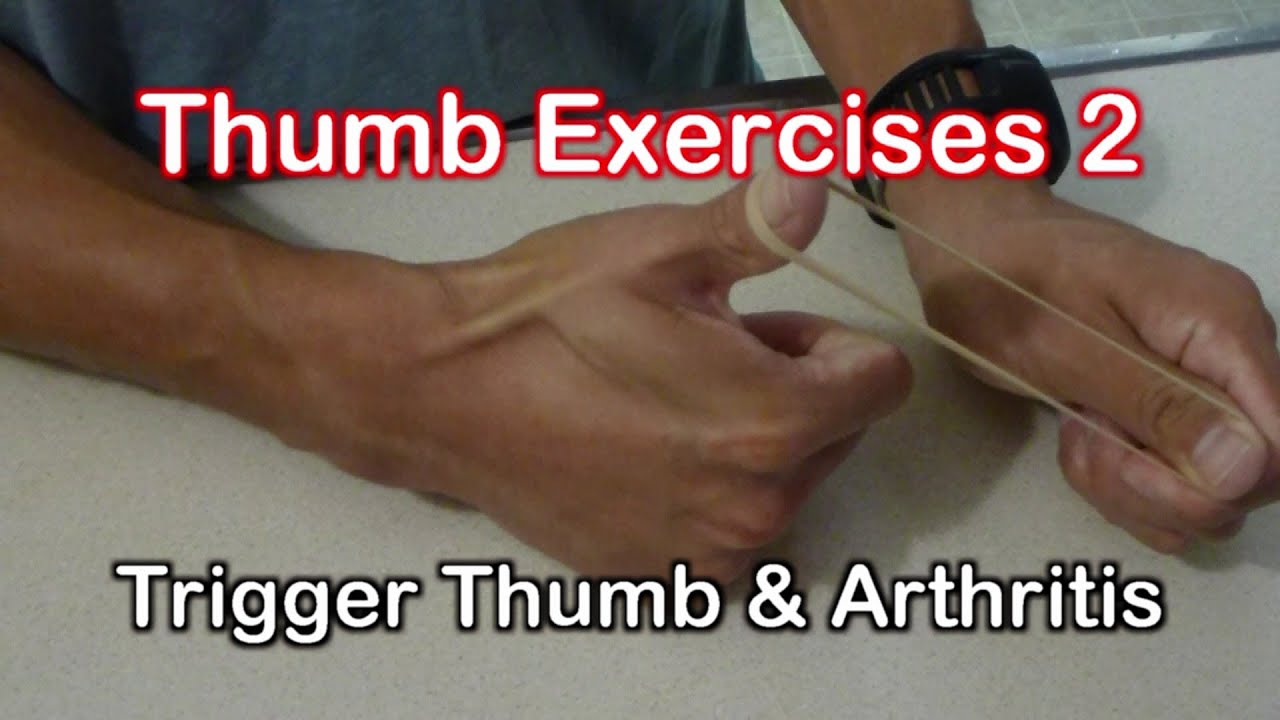
Therapeutic putty at two to four pounds of resistance works. Squeeze for five seconds, release slowly for five seconds. Ten repetitions. The slow release matters more than most therapists emphasize. Closing fast reloads the flexor mechanism without teaching control. The catching problem often comes from uncontrolled loading, not just structural narrowing. I ran into a case last year where a patient's symptoms were completely unresponsive to everything. Turns out they were doing the tendon glides aggressively, bouncing through the ranges with momentum. Once we switched to controlled tempo and stopped the extension stretch entirely for two weeks, the catching actually improved. Aggressive mobilization was making the nodule bigger by irritating the pulley area repeatedly.
Get the Full Details
What These Exercises Won't Fix
If you've had locking for more than six months, if the thumb is stuck in a bent position and you have to physically lever it straight every time, exercises are not going to resolve that. That's a mechanical block. You need a steroid injection or surgical release. Period. I've seen too many people waste three months on stretching routines before finally getting seen because they didn't want to go down that path. Night splinting is another conversation. Some clinicians swear by it. The evidence is mixed. Splinting keeps the thumb extended while you sleep, which prevents the tendon from resting in a shortened position. But it also means you're not loading it, and prolonged immobilization can actually contribute to adhesions. I usually recommend it only for the first two to three weeks of symptoms, then transition to the exercises above. One thing worth noting about the putty work. If you have diabetes, trigger thumb is more likely to be bilateral and more likely to recur after treatment. The connective tissue changes in diabetic patients respond differently to mechanical loading. I've had diabetic patients where the exercises helped marginally but the recurrence rate was essentially 100 percent within a year without additional intervention.
When to Escalate
If you try the routine consistently for four to six weeks and notice zero improvement, or if the clicking becomes more frequent, stop and get evaluated. Don't push through pain. Pain means you're irritating the pulley, not rehabilitating it. The line between therapeutic discomfort and damaging irritation is thin and subjective. If it feels sharp or burning during any exercise, that's your answer. A proper diagnosis matters too. Not every thumb stiffness is trigger thumb. Carpometacarpal joint osteoarthritis presents similarly in the same location. Base of thumb arthritis hurts with pinch and rotation, not typically with a click. Getting the diagnosis wrong means doing the wrong exercises for months. An orthopedic hand specialist or a certified hand therapist can differentiate this in about five minutes with a physical exam.
Summary of the Routine
Extension stretch hold, three sets of thirty seconds. Tendon glide sequence, five reps twice daily. Putty squeezes, ten reps with five-second holds. Rest between sets. Stop if pain spikes. Four to six weeks of consistent effort before reassessment. If it doesn't budge, move to injection or surgery discussion rather than continuing the same protocol hoping for different results. The exercises are low risk and cost nothing but time. They won't fix advanced cases. They might buy you enough relief in early stages to avoid more invasive treatment. That's an honest assessment of where this sits clinically.



