Working Through Thyroid And Parathyroid Histology
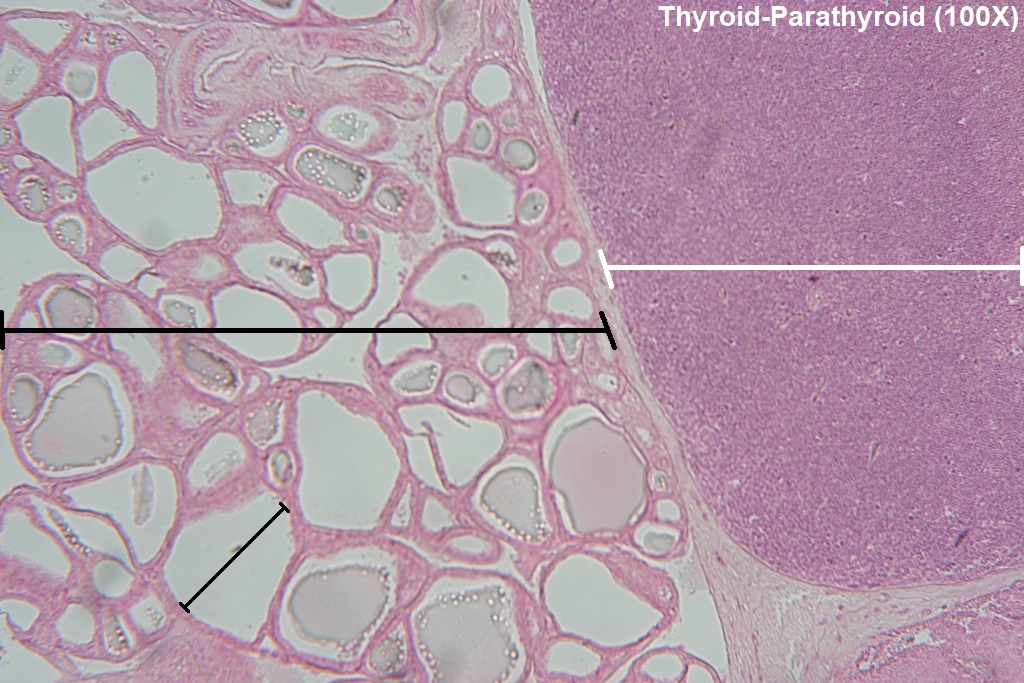
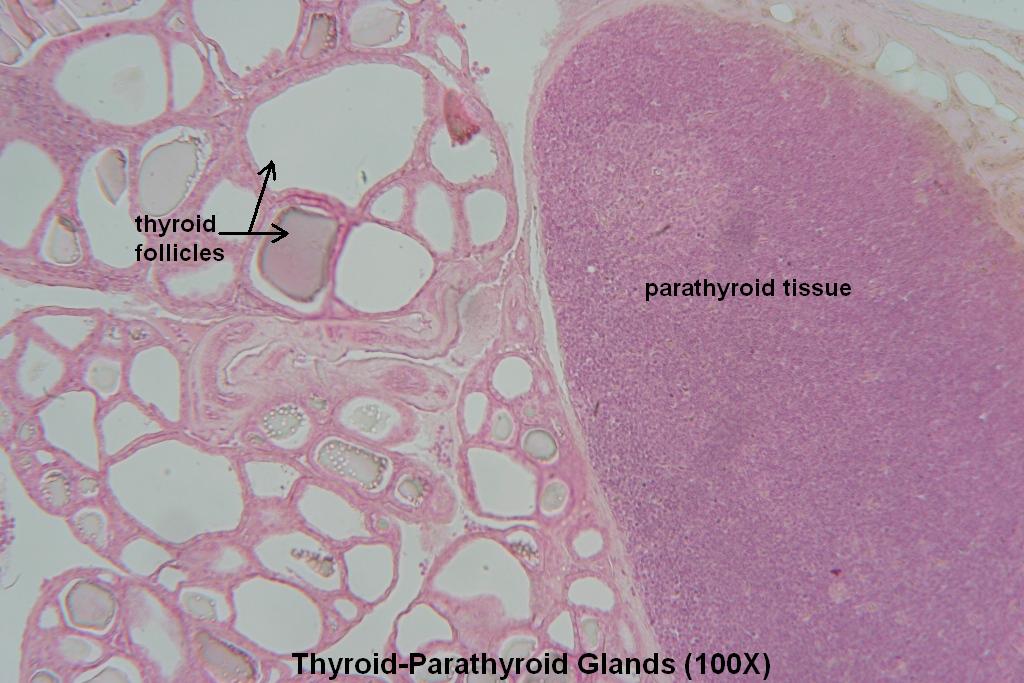
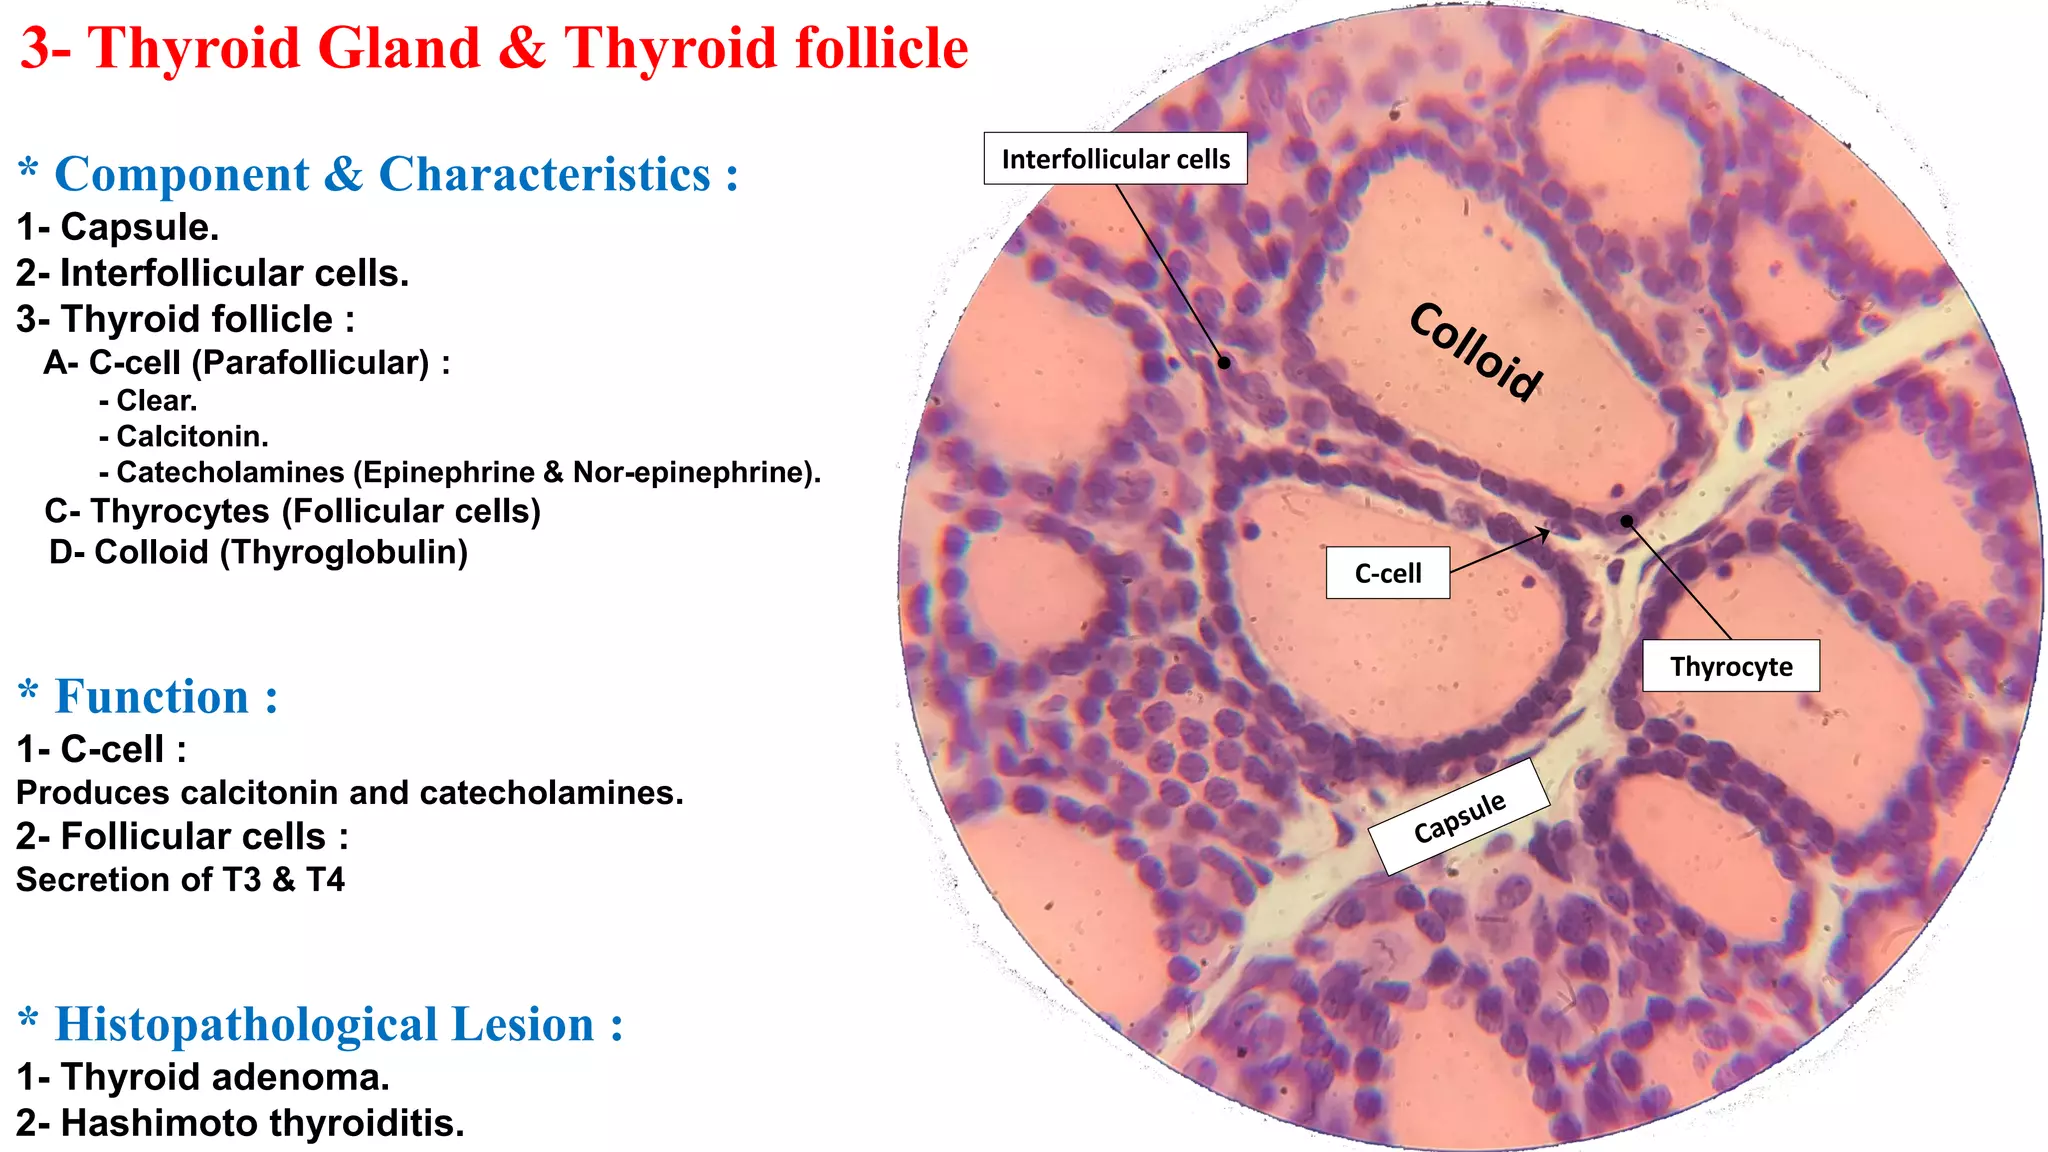
Thyroid And Parathyroid Histology is one of those topics where the textbook diagrams look clean but real tissue sections never cooperate the way they should. The thyroid has follicles, lots of them, packed with colloid. The parathyroid sits tucked against the thyroid capsule and looks completely different under the scope. That much is standard. What usually trips people up is distinguishing parathyroid tissue from thyroid tissue when the sections are thick, the stains are old, or the architecture is disrupted by pathology. The thyroid follicles range from barely visible to almost too large to fit the field of view. Follicular epithelial cells line them, and their height changes depending on whether the gland is active or resting. When the thyroid is hyperactive, those cells flatten out and the colloid takes on a pale, honeycomb appearance with tiny resorption vacuoles near the epithelial border. When it is suppressed, the cells become tall and columnar and the colloid looks dense and homogenous. This is basic but it matters because you will encounter thyroid tissue in both states during routine practice. The parathyroid is harder to spot initially. It does not have follicles. It has chief cells that are small with dark nuclei and relatively little cytoplasm. There are also oxyphil cells scattered throughout, larger with granular eosinophilic cytoplasm, and they tend to increase in number with age. Adipose tissue makes up a significant portion of the adult parathyroid, sometimes as much as thirty percent. A slide that looks predominantly fatty is not necessarily pathological, especially if the patient is over forty.
I ran into a specific problem last year with a thyroidectomy specimen that included adjacent parathyroid tissue. The pathologist on call was marking areas of parathyroid involvement as ectopic thyroid tissue. The chief cells had compressed the surrounding follicles and the architecture was distorted by surgical trauma. I re-stained a serial section with a fresh Harris hematoxylin and eosin batch and used a higher magnification to look for the characteristic nuclear features of parathyroid chief cells versus follicular cells. The key difference is that parathyroid nuclei tend to be more uniform and round, while thyroid follicular nuclei can show clearing and grooving if there is any papillary change. We resolved it by running a PTH immunohistochemistry stain on a representative area. The PTH-positive cells confirmed parathyroid origin. That process added roughly twenty minutes to the workup but it prevented a misdiagnosis.
Staining Choices That Actually Matter
Standard H&E works for most routine identification but there are situations where it falls short. If you need to demonstrate parafollicular C cells within the thyroid, chromogranin or calcitonin immunostains are necessary because C cells do not have a reliable morphological signature on H&E alone. They sit between follicles or within the follicular epithelium but blend in with regular follicular cells. For parathyroid tissue, PAS can highlight the basement membrane around cell nests and help distinguish parathyroid from thymic rest tissue, which can appear in the same anatomical region during embryological migrations. One counter-intuitive point that beginners miss is that parathyroid tissue does not always sit adjacent to the thyroid. During development, the inferior parathyroids migrate from the third pharyngeal pouch and the superior ones from the fourth. That means ectopic parathyroid tissue can end up in the mediastinum or along the carotid sheath. If you are evaluating a resection that includes lymph nodes or mediastinal fat, finding parathyroid tissue there is not automatically a sign of invasion. It could simply be an ectopic gland that was removed en bloc. Another practical issue is artifact. Thyroid tissue is delicate and freezing artifacts, folding, and crushing during sectioning are common. Crushed follicles can release colloid into the surrounding stroma and mimic invasive carcinoma at low power. The workaround is straightforward: go to higher magnification and look for true capsular or vascular invasion rather than relying on architectural disruption alone. True invasion shows tumor cells penetrating through a defined capsule or endothelial-lined space with desmoplastic reaction. Crush artifact does not have those features.
Get the Full Details
Limitations and Where This Approach Breaks Down
Not every case resolves with H&E and a couple of immunostains. Medullary thyroid carcinoma arises from C cells and produces amyloid stroma that can look similar to the hyalinized material found in long-standingHashimoto thyroiditis. Both can be mistaken for each other if you are not careful. The distinction requires calcitonin staining for medullary carcinoma and thyroid transcription factor-1 plus thyroglobulin for differentiated follicular lesions. Even then, some poorly differentiated cases will not express thyroglobulin reliably. Parathyroid carcinoma is another area where histology alone is insufficient. The distinction between parathyroid adenoma and carcinoma is based primarily on capsular and vascular invasion, which can be subtle and difficult to confirm without examining multiple levels and extensive sampling. Some surgeons and pathologists still rely on clinical parameters like serum calcium levels and palpable neck masses alongside the histological findings. Relying solely on morphology in these cases has led to underdiagnosis in published series. The biggest bottleneck in thyroid and parathyroid histology is the variability in fixation. Formalin fixation time affects antigen retrieval for immunohistochemistry and nuclear detail for morphological assessment. Under-fixed tissue produces poor nuclear staining and unreliable IHC results. Over-fixed tissue becomes brittle and sections poorly, which is why you will often see pathologists requesting re-biopsy when the original specimen is inadequately processed. There is no workaround for bad fixation other than noting it in the report and recommending repeat sampling.
If you are studying this material for exams or laboratory work, the most useful approach is to compare side-by-side slides of normal thyroid, hyperplastic thyroid, parathyroid adenoma, and normal parathyroid. The differences in cellularity, stromal fat content, and follicular size are more obvious when you have all four in the same viewing session rather than trying to memorize descriptions. Digital slide libraries from institutions like the CDC or CAP provide decent reference sets if you do not have access to a teaching microscope collection.