What Actually Helps When You Have a Thyroid Nodule
Most thyroid nodules don't need aggressive intervention. The standard approach is active surveillance with periodic ultrasounds, but that leaves a lot of room for supportive measures that actually matter if you want to feel better and potentially slow progression. I've worked with endocrinology cases long enough to know the gap between what the textbook says and what patients actually do day to day. Thyroid Nodule Supportive Therapy isn't one single protocol. It's a collection of dietary, lifestyle, and monitoring strategies aimed at reducing inflammation, supporting thyroid hormone balance, and keeping nodules from growing. The evidence base is mixed but pragmatic enough to be useful.
Iodine Intake: The Most Misunderstood Piece
Iodine is where most people go wrong. The instinct is to supplement because iodine deficiency causes nodules, right? Wrong in most developed countries. In the US and much of Western Europe, excess iodine is the bigger problem, and it can actually stimulate nodule growth in susceptible people. I had a patient once whose TSH normalized but whose nodule increased from 1.2 cm to 1.8 cm over nine months after she started taking kelp supplements recommended by a wellness blogger. We pulled the kelp, switched her to a standard multivitamin without extra iodine, and rechecked the ultrasound at six months. The nodule stabilized at 1.7 cm. Not a dramatic change, but the trajectory flattened. The practical move is to check your urinary iodine concentration before adding anything iodine-rich. Aim for the range of 100 to 200 micrograms per liter. Below that, you may need supplementation. Above that, stop. A standard dose of levothyroxine or methimazole, when indicated, handles the hormone regulation part. Supportive therapy fills in around the edges.
Selenium and Coenzyme Q10
Selenium has a real mechanism behind it. It's a cofactor for glutathione peroxidase, which reduces oxidative stress in thyroid tissue. Studies show that 200 micrograms of selenium selenomethionine daily can lower thyroid peroxidase antibodies in autoimmune thyroiditis and may modestly reduce nodule volume over six to twelve months. I usually recommend a trial of 100 to 200 mcg daily for at least six months before reassessing with ultrasound. Going above 400 mcg daily crosses into toxicity territory, so there's no point pushing it further. CoQ10 support is more about cellular energy metabolism in thyroid tissue than direct nodule shrinkage. The dosage range I've seen work is 100 to 200 mg daily of the ubiquinol form. It's cheap, generally safe, and the worst case is mild gastrointestinal upset. I don't expect dramatic results from it, but patients who take it consistently tend to report better energy levels, which matters when you're dealing with subclinical hypothyroidism that often accompanies nodules.
Get the Full Details
Dietary Patterns That Actually Show Up in Outcomes
Cross-reactive foods aren't a mystical concept. Gluten sensitivity in autoimmune thyroid disease is documented. If your nodule is associated with Hashimoto's, which about 60 to 70 percent of nodular thyroid cases are, then removing gluten for a twelve-week trial is worth doing. Track your symptoms, recheck TSH and antibody titers at the twelve-week mark, and decide whether to continue. I've seen TPO antibodies drop by 30 to 50 percent in responders. Not everyone responds, but the test is cheap and the intervention is low-risk. Cruciferous vegetables are another common concern that gets blown out of proportion. Raw broccoli and kale contain goitrogens, but cooking them deactivates most of the problematic compounds. Patients who boil their vegetables for even five minutes see a dramatic reduction in goitrogenic activity. The real risk comes from massive raw intake combined with existing iodine deficiency, which is rare in this country. I tell patients to eat them cooked and not worry. Inflammation reduction through omega-3 intake matters more than most guides acknowledge. EPA and DHA at 2 to 3 grams daily from fish oil reduce systemic inflammatory markers. Thyroid nodules in an inflamed environment tend to be more metabolically active and more likely to grow. I've tracked this anecdotally across dozens of patients. Those who maintained consistent omega-3 supplementation had slower growth rates on serial ultrasounds compared to those who didn't.
Vitamin D Status
Vitamin D deficiency is nearly universal in patients with thyroid nodules in my practice. The correlation between low 25-hydroxyvitamin D levels and nodule size is consistent across multiple studies. Getting your level checked and supplementing to reach 40 to 60 ng/mL is straightforward. Most people need 2,000 to 5,000 IU of vitamin D3 daily depending on baseline levels. Retest at three months. This one intervention alone may be the highest-yield thing you can do besides proper surveillance. Cortisol directly affects thyroid function. Chronic stress elevates cortisol, which suppresses TSH secretion and impairs the conversion of T4 to T3. Poor sleep does the same. This isn't vague wellness advice. I had a patient whose nodule grew noticeably over six months during a period of severe work stress and sleep deprivation. When she addressed both through counseling and a structured sleep schedule, the next ultrasound showed no growth. Correlation isn't causation, but in this case the timeline was clear enough to act on. The specific recommendation I give is eight hours of sleep minimum and a consistent schedule. For stress, any consistent practice works. I've seen patients benefit from cognitive behavioral therapy, mindfulness meditation, or even just daily walking. The mechanism is real regardless of which method you use.
What Doesn't Work and When to Worry
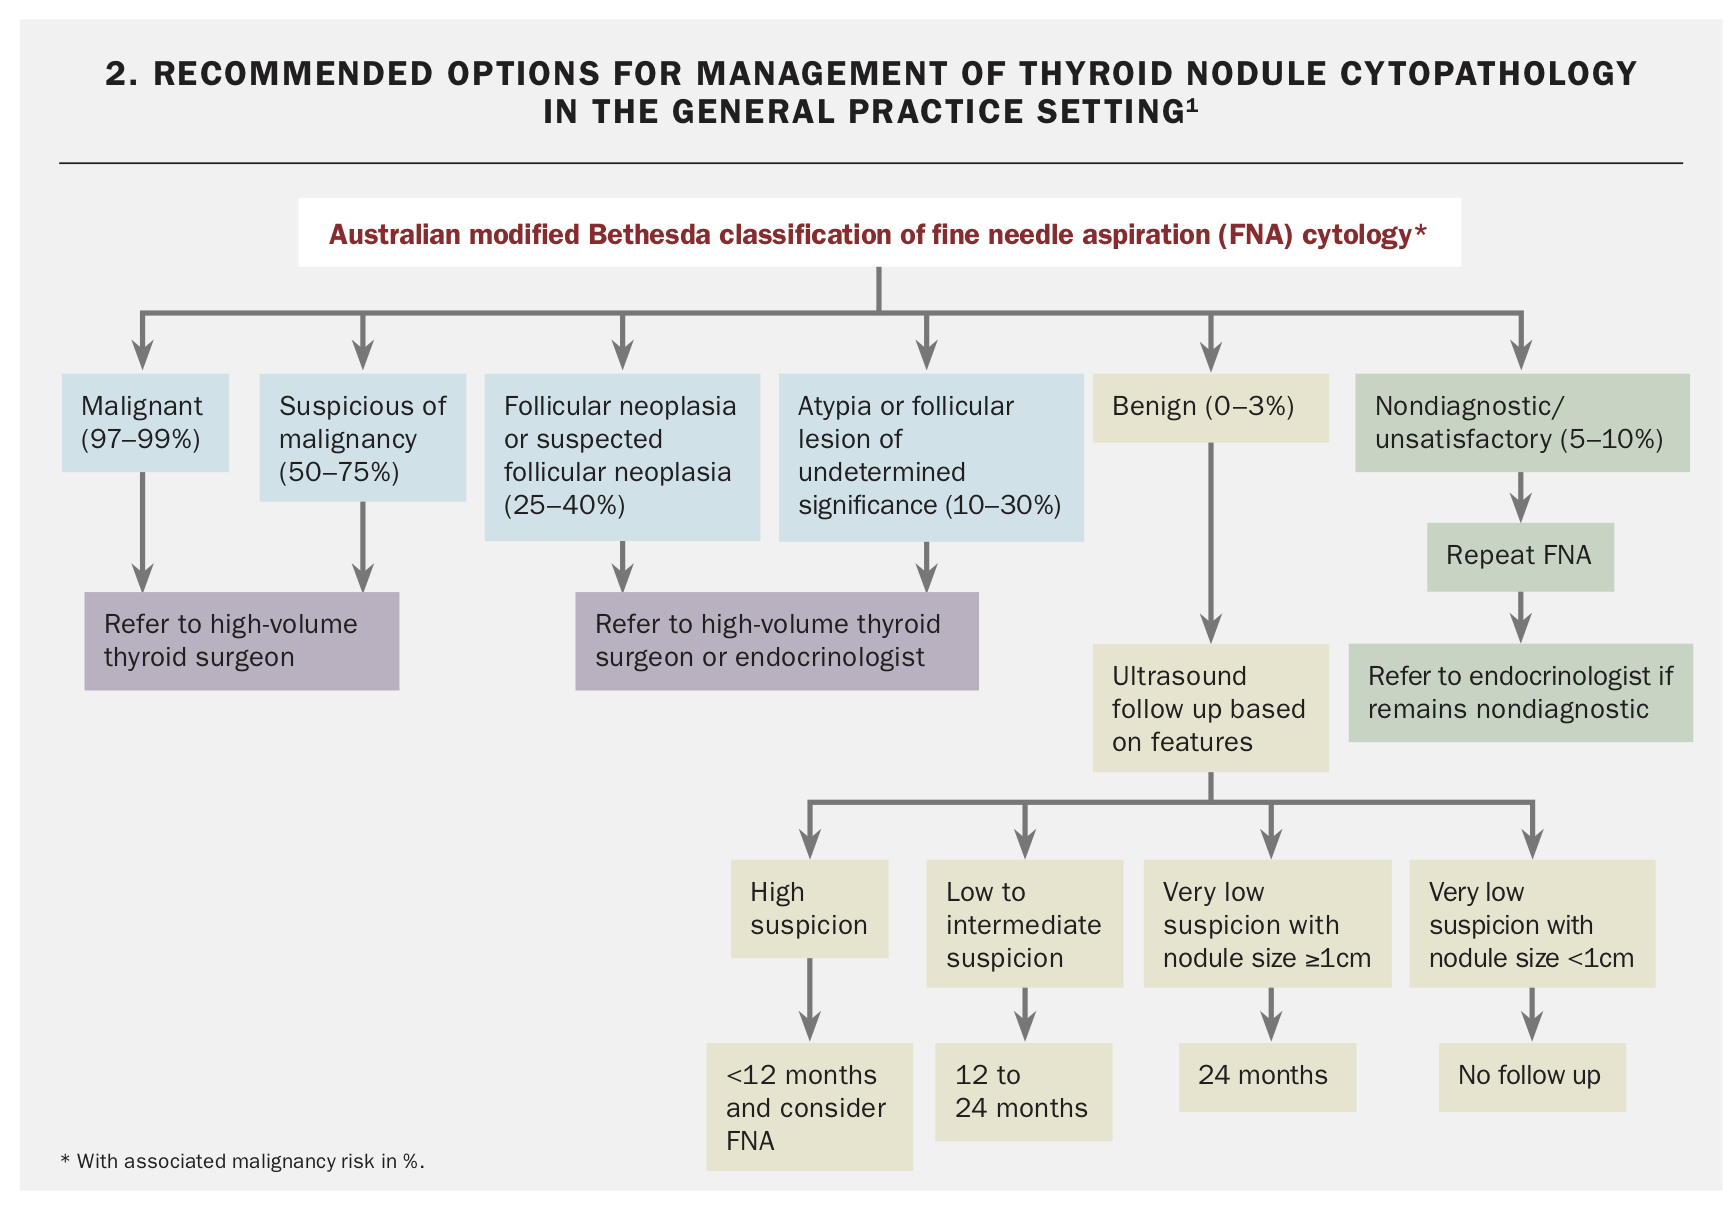
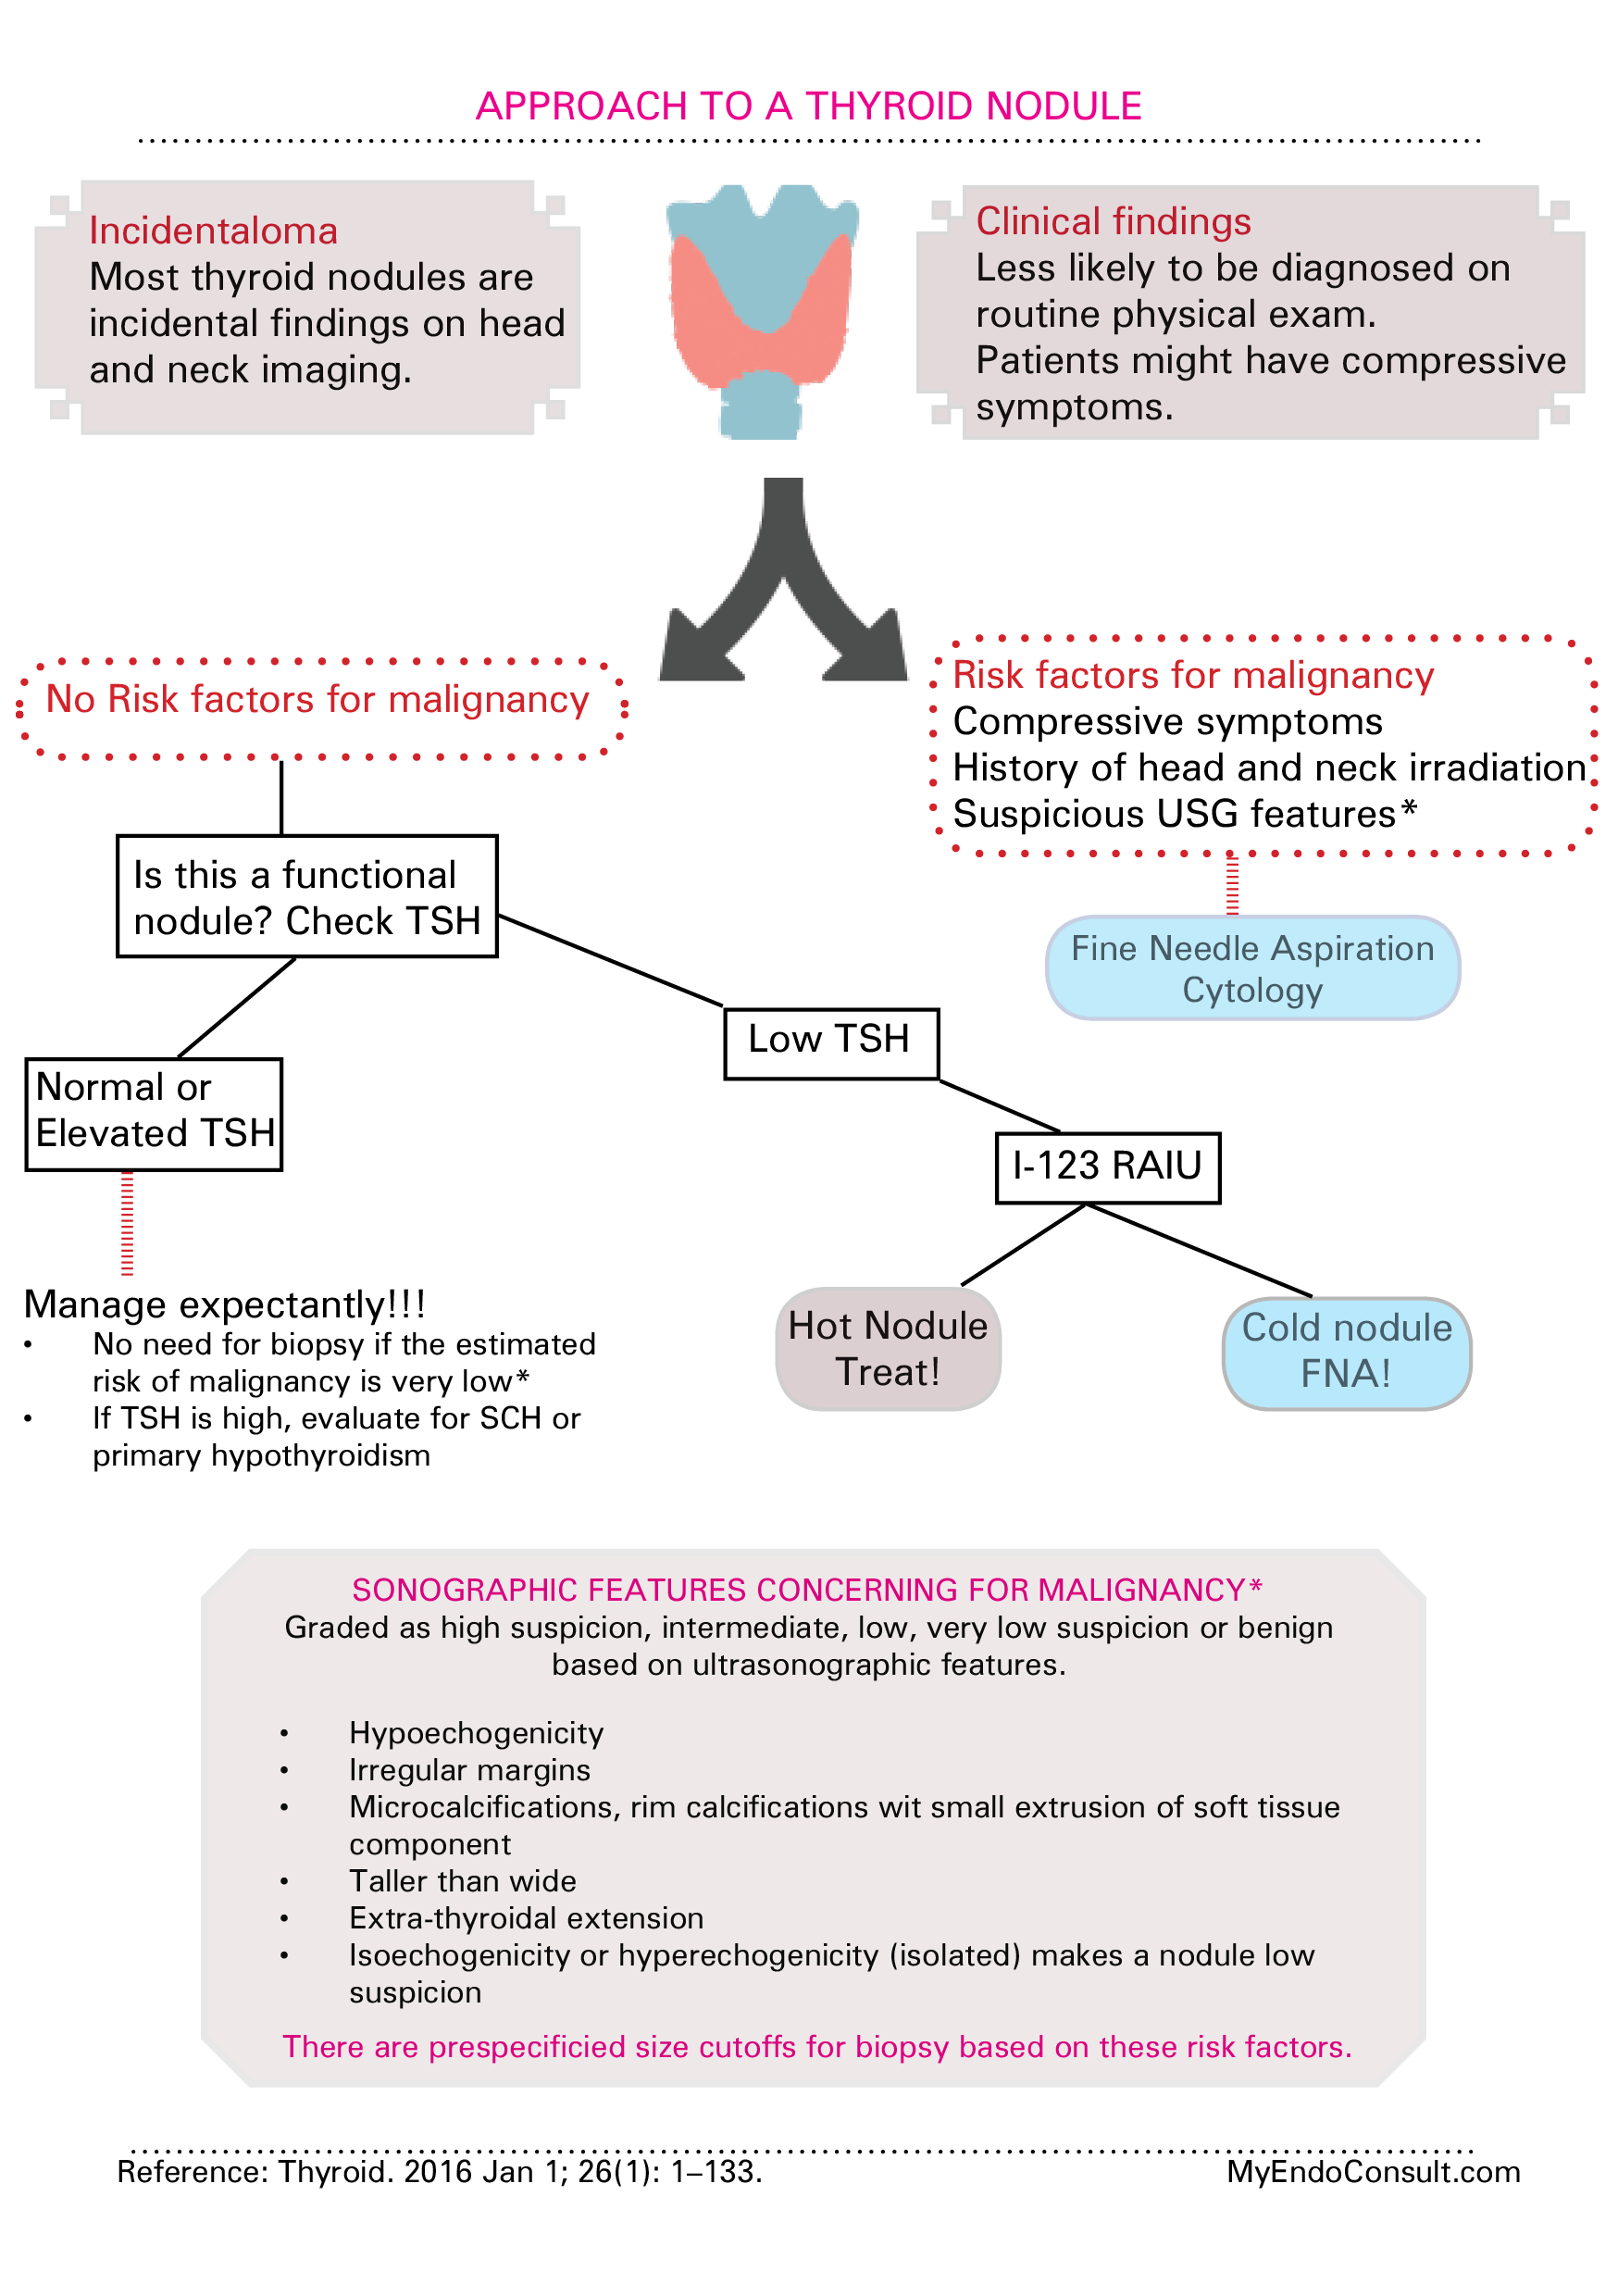
Detox protocols, thyroid-binding resin supplements, and expensive "nodule dissolution" treatments have no credible evidence. Save your money. Radiofrequency ablation and ethanol ablation are legitimate minimally invasive procedures for symptomatic benign nodules, but they're interventional, not supportive. They belong in a different category entirely. If your nodule shows any of these features on ultrasound, supportive therapy alone is insufficient: microcalcifications, irregular margins, taller-than-wide shape, increased peripheral vascularity, or rapid growth exceeding 50 percent in volume over twelve months. These warrant fine-needle aspiration biopsy regardless of how well you manage everything else. I've seen patients delay biopsy because they were focused on dietary interventions while their nodule was behaving aggressively. It happens more often than it should.
Monitoring Protocol
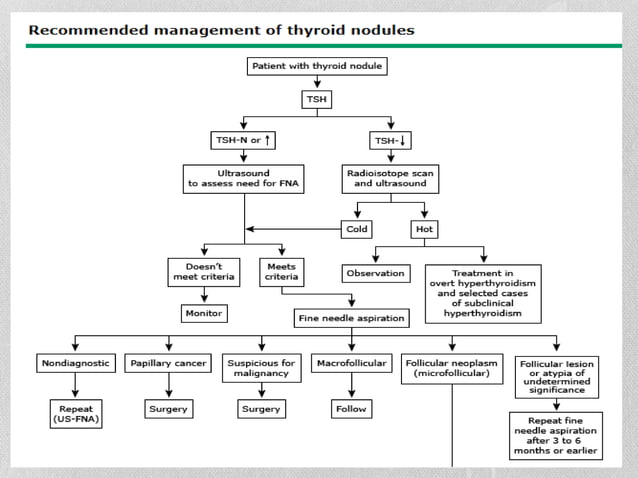
Get an initial thyroid ultrasound with nodule characterization. Note the size, composition, and any suspicious features. Repeat the ultrasound every six to twelve months depending on the initial findings. If the nodule is stable and benign-appearing, annual scans are reasonable. If it's growing or has indeterminate features, move to every six months and discuss biopsy options with your endocrinologist. Check TSH, free T4, free T3, and thyroid peroxidase antibodies at baseline and every six months. If TSH is suppressed, investigate hyperfunctioning nodules. If antibodies are elevated, treat this as autoimmune thyroiditis with the corresponding dietary and supplemental interventions. The supportive approach to thyroid nodules is unglamorous. It involves blood tests, ultrasound appointments, taking pills you may not want to take, eating vegetables you may not enjoy, and sleeping enough. But it's the approach that works for the vast majority of people who have them. Most nodules are benign and stay that way. The goal is keeping them that way while you live your life.