The Door-to-Needle Clock
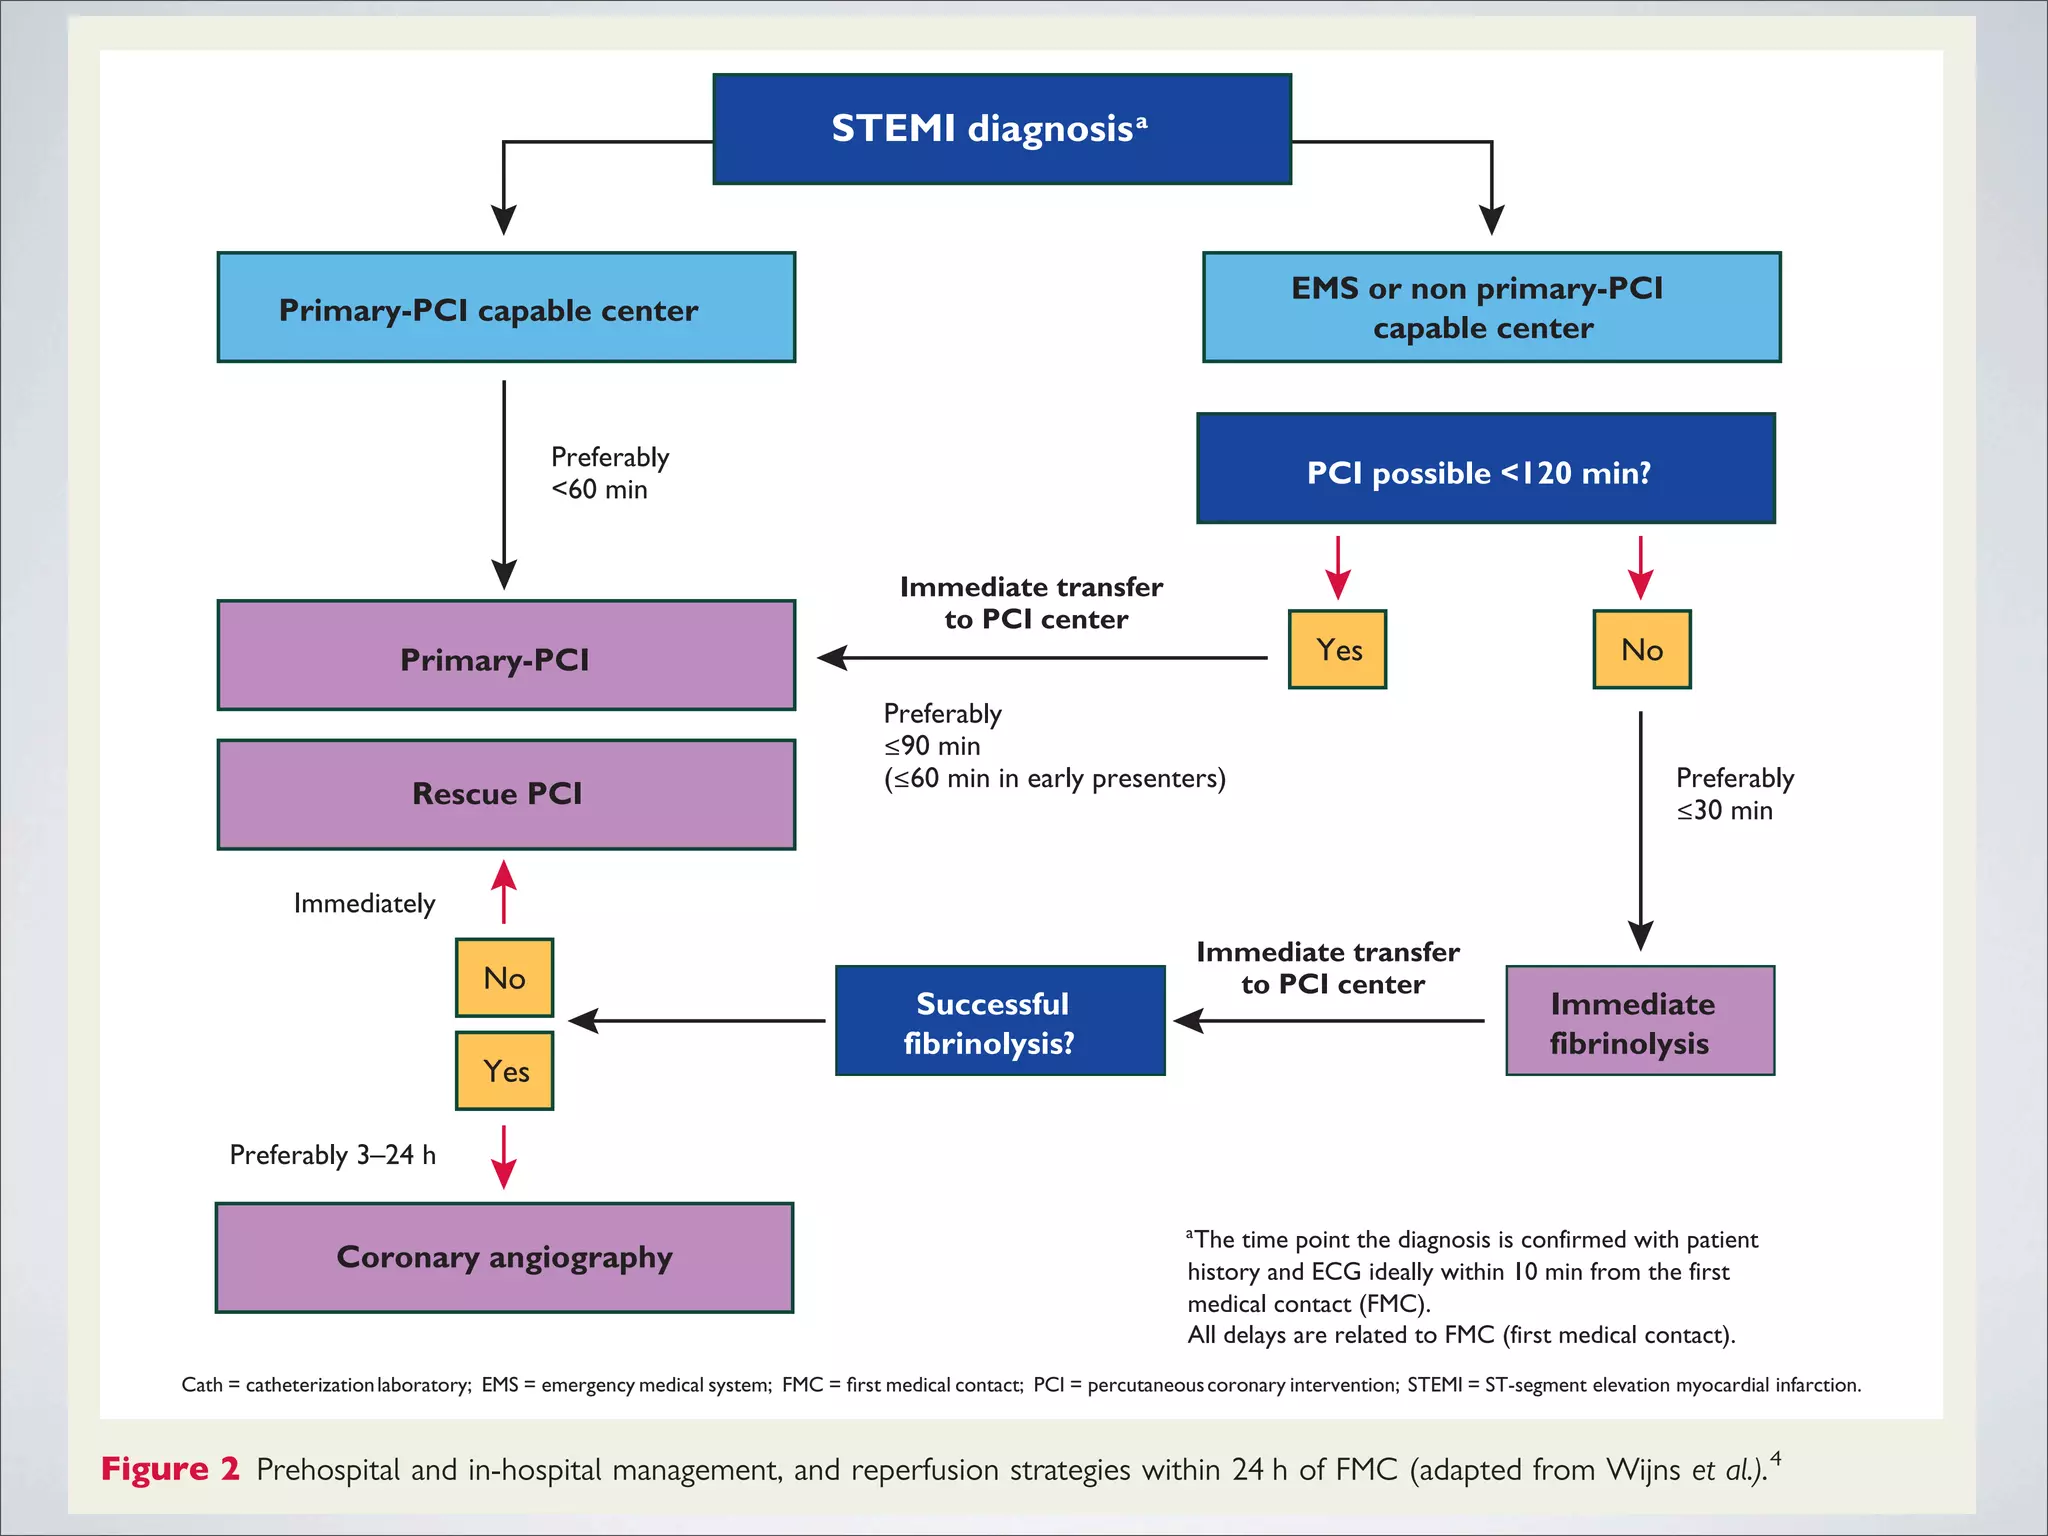
The target is 30 minutes or less from hospital arrival to needlestick for fibrinolytic therapy in ST-elevation myocardial infarction. That's the guideline number, and it has been for a long time. In practice, hitting it consistently is harder than the algorithm makes it look. The problem isn't knowing the goal. It's the friction between the ideal pathway and whatever your ER actually looks like at 2 AM on a Tuesday. I've watched teams that were genuinely good at this. They'd get needle-stick at 22 minutes, sometimes 18. I've also been on the receiving end of 55-minute delays and had to explain to a patient's family why we missed the window by a mile. The difference almost never comes down to medical knowledge. It comes down to workflow design and what people do when they're half-asleep and the phone keeps ringing. The first thing to understand is that 30 minutes starts at door time, not EMS arrival time, not when the doctor walks into the resus bay, and definitely not when you finish writing the note. Door time is when the patient's feet hit the floor inside the hospital. EMS can pre-notify. That helps. But the clock is already ticking before anyone in your building even knows there's a STEMI coming in.
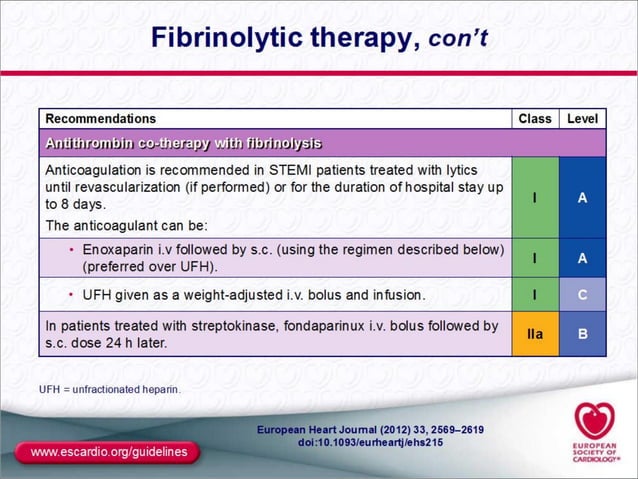
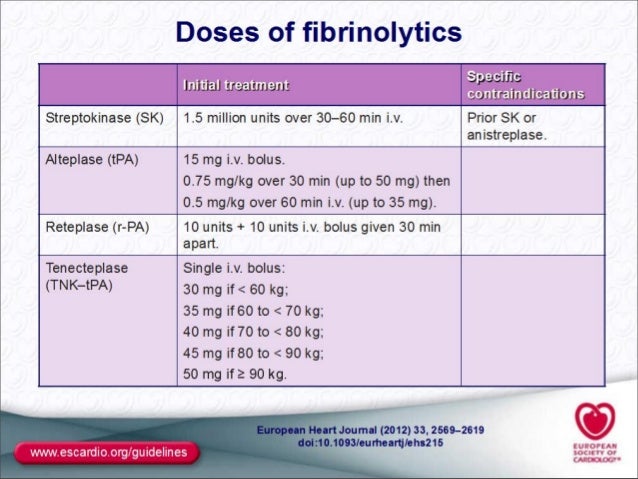
The standard pathway goes something like this. EMS calls ahead with a 12-lead. The ER receives the ECG within five minutes of arrival. A physician interprets it, decides on fibrinolysis, writes the order, nursing gets the drug from the pharmacy or the crash cart, and the needle goes in. Each handoff is a place where time leaks out. What actually saves time is treating the ECG interpretation as parallel work, not sequential. I used to wait for the 12-lead to be "read" formally before I started moving. That was stupid. If the pre-hospital ECG shows clear ST elevation and the patient has compatible symptoms, you don't need a second pair of eyes before you begin the activation sequence. In my department, we switched to a pharmacy-direct protocol where the paramedics' ECG finding alone triggers the pharmacists to pull the tenecteplate while the patient is still being transferred. That alone shaved eight to twelve minutes off our median door-to-needle time over six months. The other thing people get wrong is the medication choice. Alteplase requires a weight-based infusion with boluses over an hour. Tenecteplate is a single bolus. If you're using alteplase and still missing 30 minutes, you're fighting a structural disadvantage. Switching to tenecteplate when your formulary allows it is one of those low-effort, high-impact changes that nobody argues about until their metrics improve.
Contraindications are where things get real. I had a patient last year who looked like a textbook STEMI on the surface ECG — diffuse ST elevation, reciprocal changes in aVL. Quick thrombolytics, right? Then I noticed the PR depression and the spotty J-point elevation pattern that suggested pericarditis rather than infarction. I sent them for a CT instead of giving tenecteplate. We spent another twenty minutes going back and forth with cardiology, and the door-to-needle time became irrelevant because the diagnosis changed mid-stream. This happens more often than you'd think, especially in younger patients or those with early repolarization patterns. The guideline assumes the diagnosis is certain. It doesn't always is. Another pitfall that catches people: the PCI transfer scenario. Some hospitals treat transfer time as part of the door-to-needle calculation when it shouldn't be. If your facility doesn't do PCI and you're transferring, the fibrinolytic should ideally be given at the referring hospital before the patient leaves. If you wait until they arrive at the tertiary center, you've already burned 60 to 90 minutes in transit. The 30-minute goal only makes sense if the drug is going in at your door, not after a five-hour ambulance ride. Here's the part that nobody puts in the algorithms. The moment between "doctor says give it" and "nurse pulls it" is where most delays happen, and it's usually because someone assumes someone else made the call to pharmacy or the supply closet. Write down exactly who gets the order, who retrieves the drug, and where it lives. In my experience, keeping tenecteplate in a secured but visible location in the resus area itself — not down the hall in the pharmacy — cuts retrieval time from three minutes to forty-five seconds. Forty-five seconds doesn't sound like much until you're trying to beat thirty minutes across fifteen different steps.
Get the Full Details

The monitoring after administration is another area where people lose time without meaning to. You need blood pressure checks, repeated ECGs, and observation for bleeding. These are necessary. But they shouldn't block the needle stick. Get the drug in, then sort out the post-thrombolytic checklist. Doing them in the reverse order just adds artificial delay. If you're running a service that consistently hits 35 minutes or more, the fix isn't more training. It's removing steps. Audit your last twenty cases. Count every stop between door and needle. Usually you'll find two or three stops that are purely administrative — a signature that isn't needed, a phone call that could be a text, a medication preparation that could be pre-packed. Eliminate those and the median drops fast. There's also the issue of weekend and nighttime staffing. Our data showed a clear jump in door-to-needle times from Friday 6 PM to Monday 8 AM. Not because the doctors were worse, but because the pharmacists covering those shifts had to walk farther to retrieve the drug and the junior residents were still figuring out the order entry system. We solved it by creating a dedicated STEMI activation page that bypassed the standard residential pager chain and went straight to the on-call pharmacist and the nurse most with the protocol. Weekend times dropped to match weekday performance within three months.
The ceiling on this metric is also worth mentioning. Fibrinolytics aren't going to save every STEMI patient, and the 30-minute goal isn't meaningful if the patient has absolute contraindications that require a longer workup. I've seen teams rush to hit the clock and miss aortic dissection as the real diagnosis. Time matters, but correct diagnosis matters more. If the ECG is ambiguous and the clinical picture isn't clear, take the extra twenty minutes to figure it out. A missed bleed from a dissecting aneurysm given tenecteplate is a lot harder to explain than a slightly late lytic dose. Ultimately, the 30-minute goal is a target, not a law. It works when your system is set up for it. It falls apart when you try to force a complex patient through a simple protocol. Know the number, build the pathway, but keep enough sanity left over to recognize when the pathway itself is the problem.