What a Head To Toe Assessment Actually Looks Like in Practice
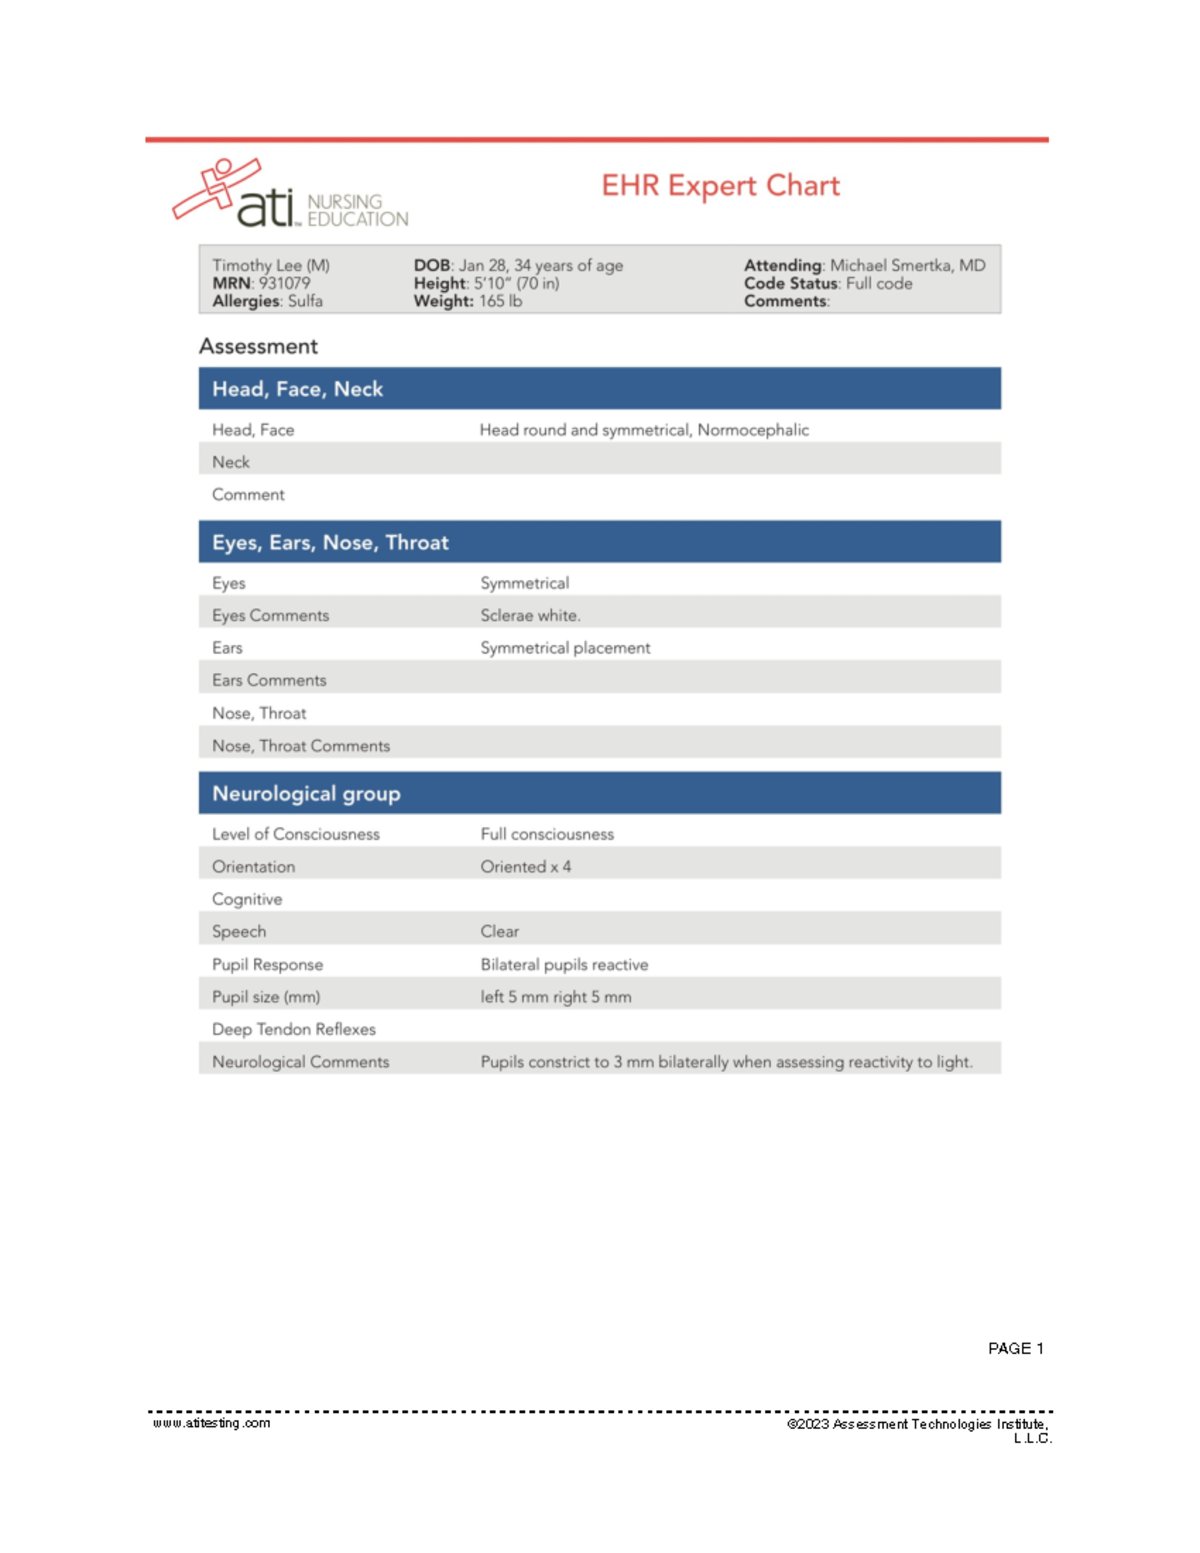
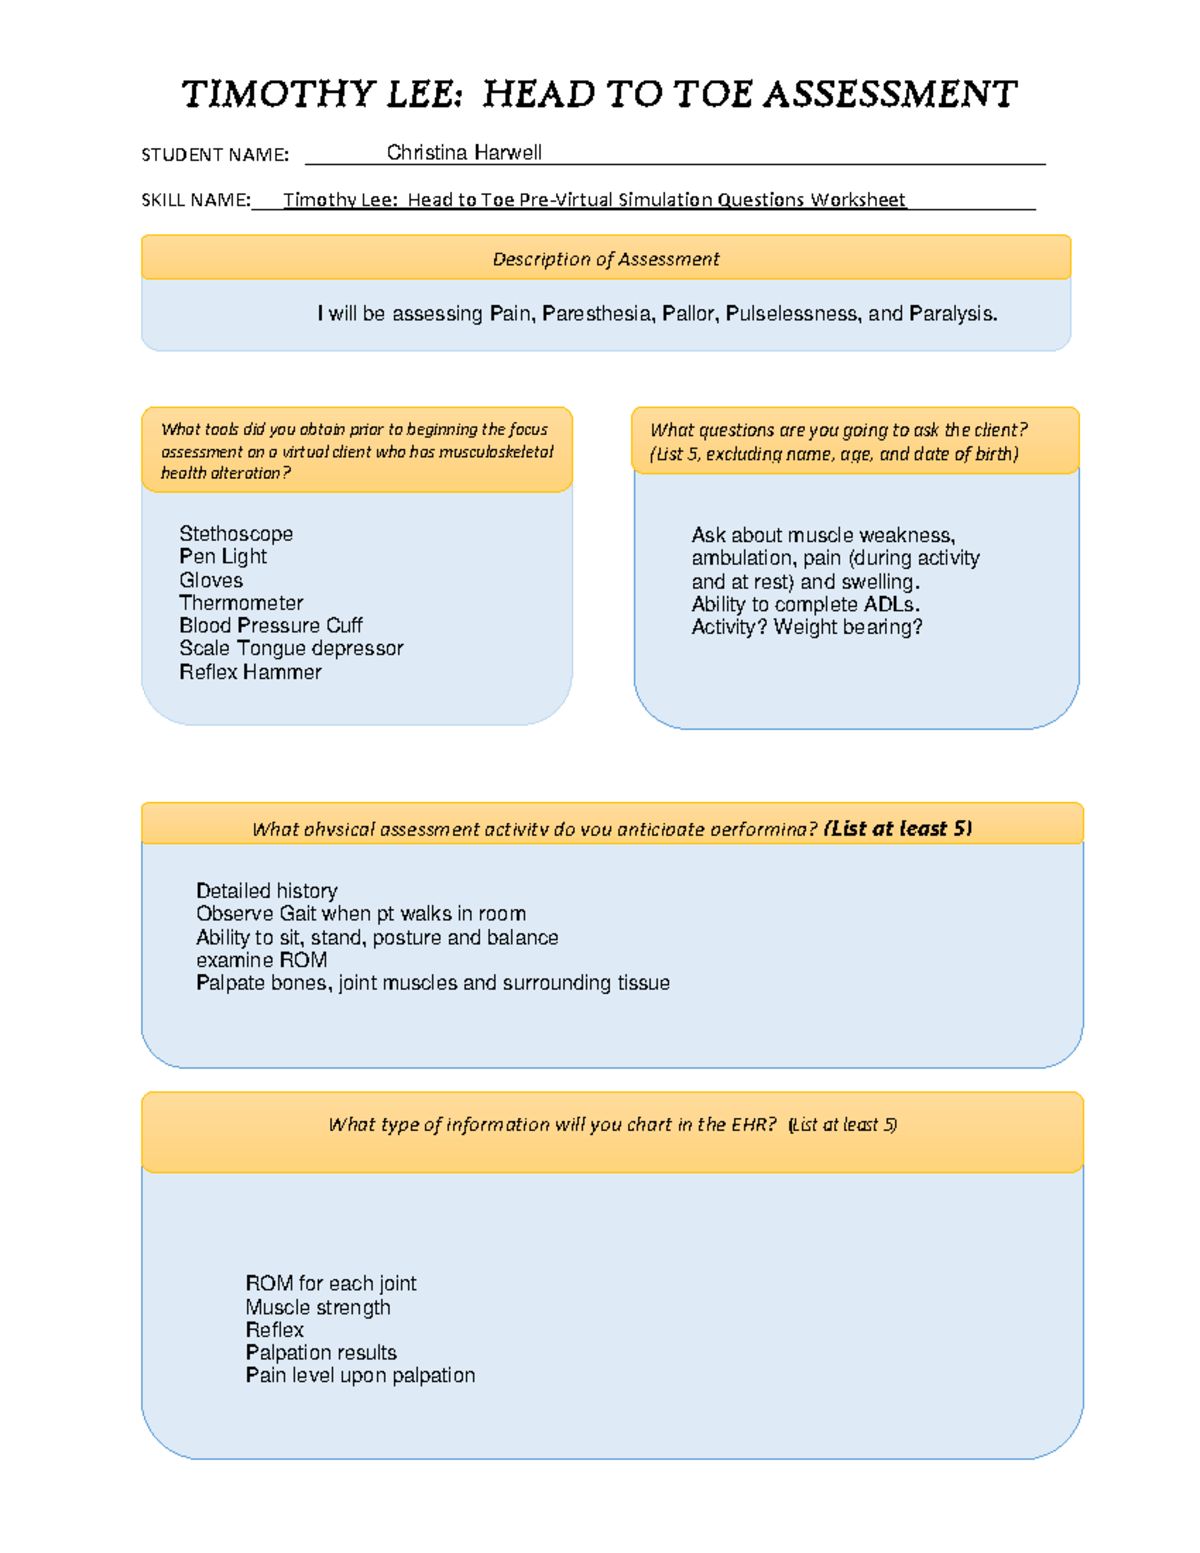
Most people learn the head-to-toe assessment in nursing school and then spend years figuring out how to actually use it efficiently in a real clinical setting. The framework itself is straightforward — you work systematically from the top of the body down, documenting findings as you go. But the execution is where things get messy. The standard sequence runs through mental status and general appearance first, then moves into the head, eyes, ears, nose, and throat, followed by the neck, chest and lungs, heart and cardiovascular system, abdomen, extremities, neurology, skin, and finally the back. Each section requires specific inspection, palpation, percussion, and auscultation techniques depending on the region. You have to know which tools to reach for and when. A tuning fork belongs in the neuro section. A otoscope goes in ENT. A reflex hammer shows up later. If you're scrambling to find equipment mid-assessment, you're losing time and breaking your own rhythm. I keep this guide because the original Timothy Lee Head To Toe Assessment materials have been hard to track down in their updated forms over the years. Different programs have adopted and adapted his approach at various institutions. The core structure remains consistent across most versions: a systematic sweep with defined checkpoints at each anatomical region, built around both screening efficiency and thoroughness. The downloadable forms typically include space for vitals, system-by-system notes, and an overall impression section.
Getting Started With the Timothy Lee Head To Toe Assessment
If you're looking for the actual forms or templates associated with this assessment method, you'll want to search your institution's library portal or nursing education resources first. Many programs host their own versions. External searches for "Timothy Lee Head To Toe Assessment PDF" or the full title will turn up departmental pages and educational repositories. Always verify you're using the latest version because assessment criteria shift as clinical guidelines change. The setup takes about five minutes if you're organized. Gather your tools before you walk into the room — light source, stethoscope, otoscope with Speculums, tuning fork, reflex hammer, penlight, BP cuff, thermometer, pulse oximeter, and a measuring tape for things like pupillary response or wound dimensions. Lay them out in the order you'll use them. I keep a kit bag that already has everything arranged systematically so I'm not hunting during the exam. This usually cuts the process down from twenty minutes to about eight to ten for a routine screening assessment, assuming the patient is cooperative and the environment is quiet enough for auscultation. Begin with the patient's general appearance and mental status before touching anything. Observe posture, gait, level of distress, speech patterns, and responsiveness. Note skin color and condition at a distance. These initial observations often reveal more than you expect before you even pick up the stethoscope. A patient who is tachypneic and leaning forward is already telling you something about their respiratory status before you listen to their lungs.
Working Through the Systematic Sequence
The head section checks scalp, skull, facial symmetry, and sinuses. Palpate the frontal and maxillary sinuses for tenderness. Check temporal arteries for pulsation and any thickening. Inspect the conjunctiva and sclera for pallor or icterus. This takes about two minutes if you're thorough but efficient. For eyes, check pupillary reaction to light and accommodation. PERRLA is the standard shorthand but documenting the actual response times and symmetry matters more than checking a box. Use the penlight from the side to observe direct and consensual response. I once missed a subtle relative afferent pupillary defect because I was rushing through the pupillary check with a bright room light instead of dimming the area. The Marcus Gunn pupil didn't show up properly under those conditions. Now I always dim the lights or turn off overheads when doing a proper CN II and CN III check. Ears and throat follow naturally. Otoscopic exam requires straightening the canal appropriately for adults — pull the pinna up and back. Inspect the tympanic membrane for color, landmarks, and fluid levels. Throat inspection uses tongue depressor and good lighting. Check for exudates, erythema, and tonsillar size. Document uvular deviation because that's a midline structure and asymmetry can indicate deeper pathology.
Get the Full Details

Neck assessment covers tracheal position, thyroid palpation, carotid pulses, jugular venous pressure, and lymph node chains. Palpate the thyroid behind the patient while they perform a slight swallowing motion. Check for cervical, supraclavicular, and axillary nodes systematically. JVP assessment requires the patient at thirty to forty-five degrees. If you're checking JVP with the bed flat, you're going to get unreliable readings every time. Chest and lung assessment is where auscultation discipline matters most. Breath sounds need to be compared side to side at corresponding levels. Anteriorly check upper lobes at the clavicular and midclavicular lines. Posteriorly cover the apices through the bases. Every segment gets heard. I've seen people skip the posterior lower lobes because the patient can't sit up fully, but those are the most dependent portions and the most common site for atelectasis and consolidation in bedbound patients. If you can't get them fully upright, roll them to the side and access the posterior bases from there. Cardiovascular assessment requires listening at all four valve areas plus the apex. Aortic, pulmonic, tricuspid, mitral, and the point of maximal impulse. S1 and S2 should be identified clearly. Note any murmurs, rubs, or gallops. If you hear a murmur, characterize it — timing, location, radiation, intensity, and what maneuvers change its audibility. A crescendo-decrescendo systolic murmur that increases with standing and decreases with squatting points toward hypertrophic cardiomyopathy rather than aortic stenosis. The maneuver response is diagnostically significant and students consistently skip it.
Abdomen and the Things People Get Wrong
Abdominal assessment follows inspection, auscultation, percussion, and palpation. The critical detail most people miss is the sequence. You auscultate before you palpate or percuss because manipulating the abdomen changes bowel sound patterns. If you palpate first, you'll be listening to artificially stimulated peristalsis and your assessment loses value. This is one of the most consistently violated steps in my experience as an evaluator reviewing student assessments. Percussion helps determine organ size and detects masses or fluid. Dullness over the liver span should be noted. Shifting dullness and the fluid wave test assess for ascites. Palpation distinguishes between light and deep techniques. Light palpation detects surface tenderness and guarding. Deep palpation assesses organomegaly and deeper masses. Rebound tenderness indicates peritoneal irritation but test it carefully and document the specific location precisely. Extremity assessment covers pulses, edema, capillary refill, and range of motion. Compare bilateral pulses — rate, rhythm, and strength. Grade edema on the standard scale from one to four. Capillary refill should be under three seconds in a warm environment. Cold hands invalidate this test regardless of circulatory status. I've corrected plenty of charting where the patient's fingers were visibly cold and the documented cap refill was three seconds — that's not a normal finding, that's an artifact of the testing conditions.
Neurological screening includes cranial nerves, motor strength, sensation, reflexes, and gait. Motor strength should be graded on theMedical Research Council scale from zero to five. Document exact numbers rather than just checking "normal." A four-plus is meaningfully different from a five, and that distinction matters for tracking progression or improvement over time.
Documentation and the Common Pitfalls
Documentation quality determines whether your assessment is clinically useful or just a paperwork exercise. Vague entries like "lungs clear" without specifying breath sound quality, symmetry, and any adventitious sounds are insufficient. Write what you heard. "Clear to auscultation bilaterally" tells someone nothing about whether you actually listened systematically or just held the stethoscope to the chest briefly. I went through an assessment where a patient had a documented head-to-toe that read "abdomen soft, non-tender, normoactive bowel sounds" across four different visits spanning three weeks. On the fourth visit, the patient presented with acute abdominal pain and was found to have a perforated ulcer. Looking back at those previous assessments, the bowel sounds were never described by quadrant and the palpation technique was never specified as light versus deep. The documentation was technically correct but clinically incomplete. This is the single most common failure mode I see — assessments that satisfy a checklist without capturing diagnostically useful detail. Another issue is the over-reliance on technology. Pulse oximeters and blood pressure monitors are useful but they don't replace manual assessment. A normal SpO2 reading doesn't tell you about work of breathing. A normal blood pressure doesn't rule out early shock in a young healthy patient who is compensating. I had a trauma case where the vitals looked fine on the monitor but the patient had a tense abdomen and delayed cap refill that pointed to internal bleeding. The numbers would have reassured someone who wasn't doing the physical exam.
When This Assessment Falls Short
The head-to-toe approach has real limitations that aren't always discussed in training programs. It assumes a stable patient who can tolerate a full examination. In emergency situations, you're doing a focused assessment, not a comprehensive head-to-toe. Attempting a full systematic exam on an unstable patient wastes time and may miss the critical intervention. The method also depends heavily on examiner skill and experience. A beginner can go through every step in the correct order and still miss subtle findings that an experienced clinician would catch in seconds. Things like slight unilateral wheezing, a minimally displaced trachea, or a grade one versus grade two murmur require practiced ears and developed pattern recognition. No form or template compensates for that skill gap. Patient factors also limit usefulness. Obese patients make abdominal and cardiovascular assessment significantly more challenging. Patients with cognitive impairment or language barriers require adaptation of communication techniques. Acutely dyspneic patients may not tolerate supine positioning needed for certain exam components. In these scenarios, a modified focused assessment is more clinically appropriate than forcing a complete head-to-toe.
The Timothy Lee Head To Toe Assessment remains one of the more structured and widely referenced frameworks for comprehensive physical examination in clinical training programs. Its strength lies in forcing systematic coverage rather than cherry-picking the sections you feel comfortable with. The weakness is the same as any standardized approach — it can become a ritualized checklist exercise if you're not actively thinking through each finding rather than just moving through the steps. Use the form as a safety net, not a replacement for clinical reasoning. For current versions of the assessment forms and any updated documentation templates, check with your program coordinator or search your institution's clinical skills lab resources. Some versions are available through nursing education publishers and clinical skills workbooks. The underlying methodology hasn't changed substantially — the examination sequence and documentation standards remain consistent across the various iterations.