Working Through the Tina Jones Comprehensive Assessment
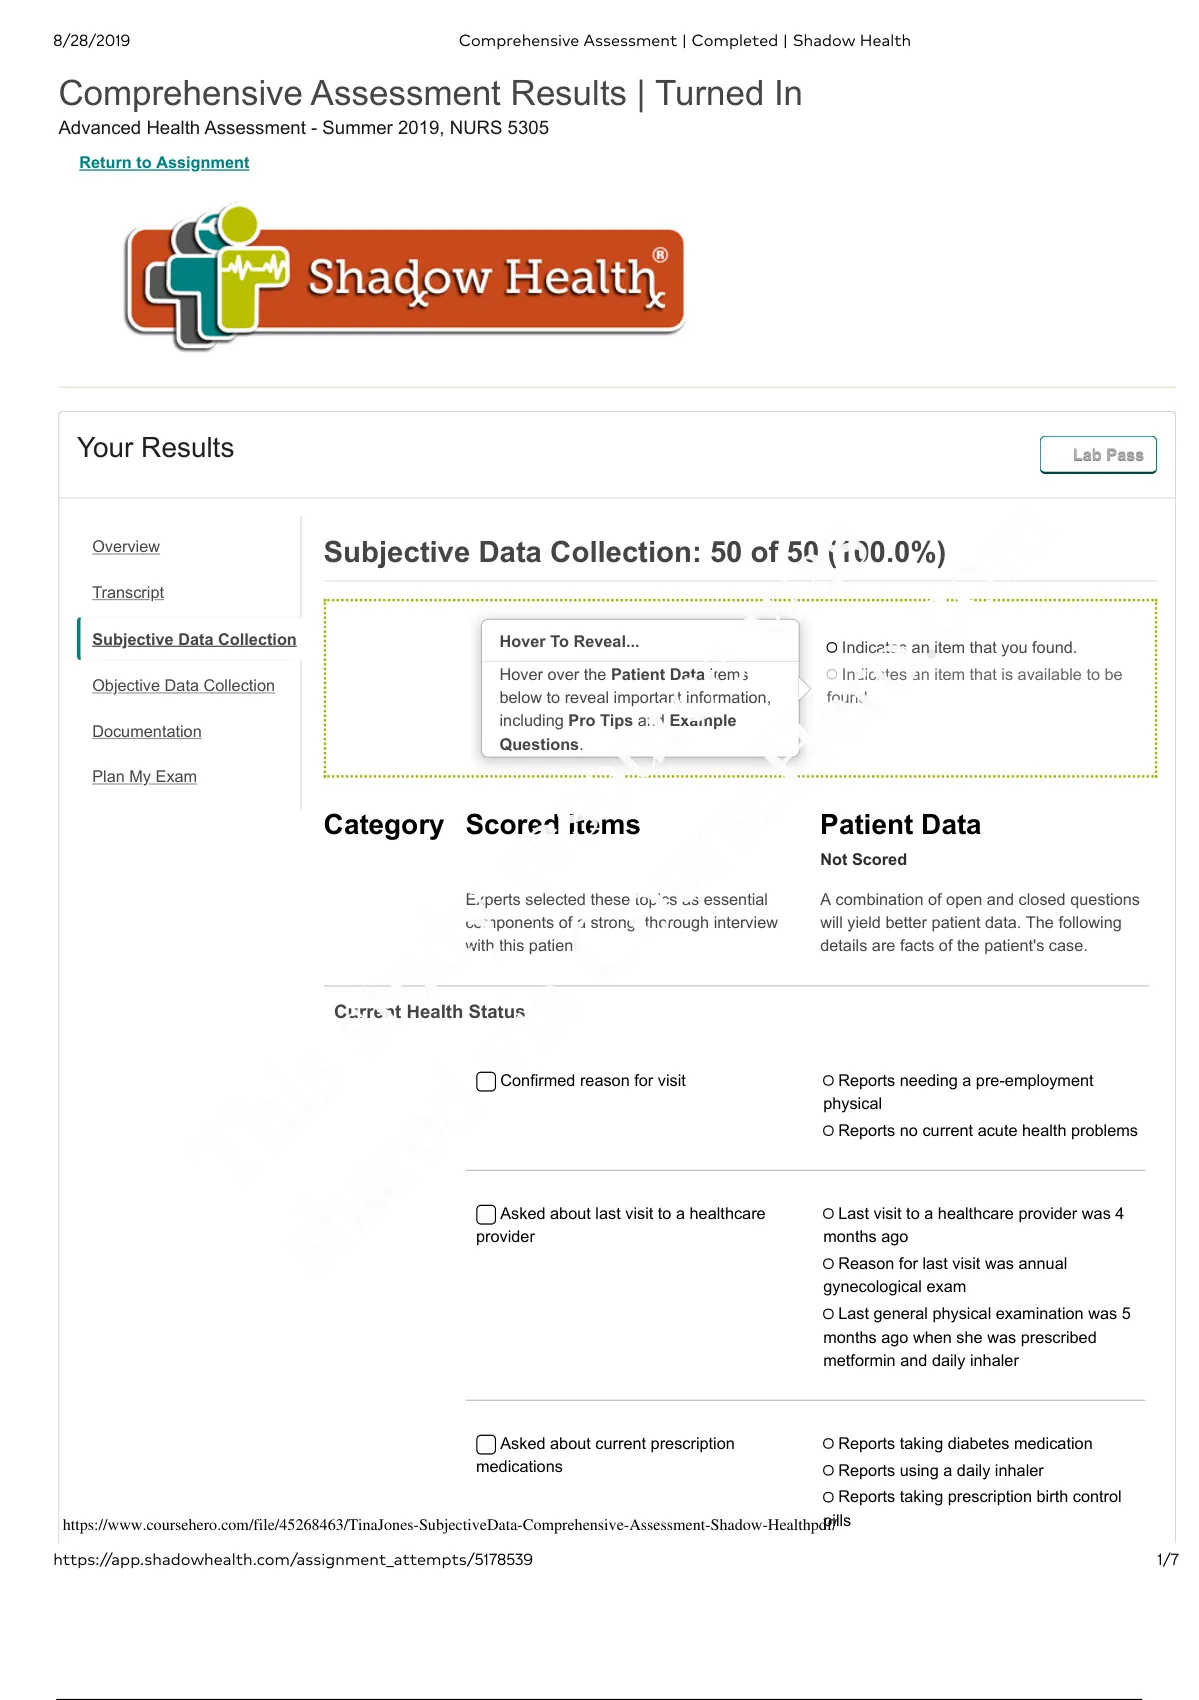
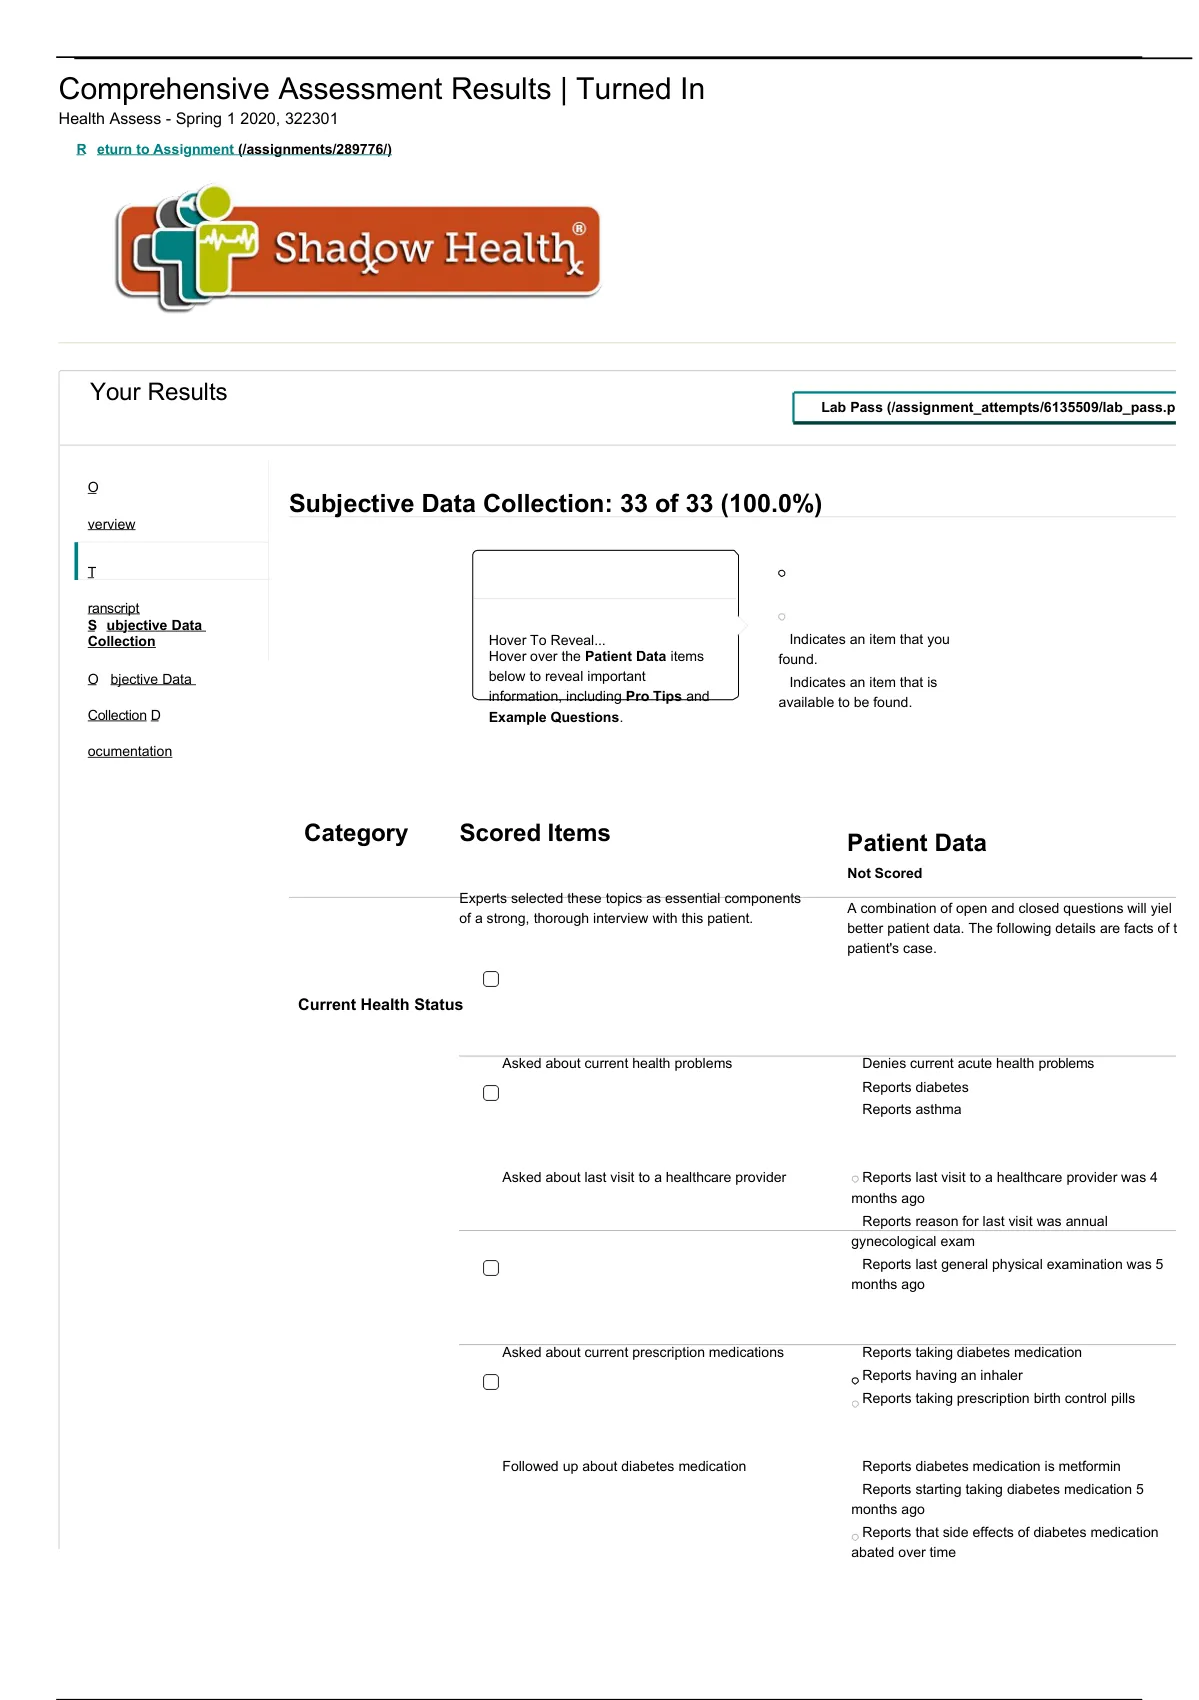
Comprehensive assessments in nursing school are the bane of third-year students everywhere. You sit across from a simulated patient—sometimes a real person in a simulation lab, sometimes an actor—and you have to pull together subjective and objective data into something coherent. Tina Jones comes up a lot because her case is dense. Diabetes type 2, hypertension, some psychosocial complexity, and enough medication history to make your head spin if you aren't organized. Subjective data is what the patient tells you. It's not measured by instruments. It's her words, her complaints, her history as she recounts it. With Tina, you're looking at her chief complaint first. She's presenting with increased polyuria, polydipsia, and unexplained weight loss over the past few weeks. She also reports fatigue that interferes with her daily activities and some numbness in her feet. These are the classic diabetic symptoms, but the key is documenting them in her own words where possible, then translating. I remember doing this assessment during my clinical rotation and freezing up when Tina started describing her foot symptoms. She said her socks left marks and she couldn't feel the texture of the carpet when she walked barefoot. I wanted to write "decreased sensation" immediately, but the chart review showed I needed to capture her exact description first before interpreting. That's the difference between good subjective documentation and weak documentation. Students rush to translate. Don't.
Her medical history includes a diagnosis of type 2 diabetes roughly five years ago, managed initially with metformin. She has hypertension diagnosed about three years prior. There's a family history of diabetes on her mother's side—her mother required insulin at one point. That detail matters because it shapes her health beliefs. When I asked about her understanding of the disease, she mentioned her mother's insulin injections and expressed fear about needing the same treatment. That fear showed up in her medication adherence patterns and should be noted explicitly in your assessment. Social history is where Tina's case gets interesting. She works as a cashier at a grocery store, which means she's on her feet most of the day. She lives alone in an apartment on the second floor with no elevator. Her diet consists largely of convenience foods because she claims she doesn't have the energy to cook after work. This is clinically significant—not just for nutrition counseling, but because it reveals a barrier to self-management that isn't obvious from lab values alone. Review of systems pulls in additional subjective complaints. She reports occasional blurred vision, particularly in the mornings. She's noticed her wounds taking longer to heal—a small cut on her hand from work took nearly three weeks to close. She denies chest pain, shortness of breath at rest, or palpitations. She reports some anxiety about her health status but denies depressive symptoms. These negative findings are just as important as the positive ones because they help rule out complications.
The challenge with subjective data is that it's inherently biased. Tina may minimize her symptoms because she doesn't want to seem like a difficult patient. She may exaggerate certain complaints because she's genuinely worried. My approach is to ask open-ended questions first, then follow up with specific clarifying questions. When she mentioned feeling tired, I asked whether that was physical fatigue or mental exhaustion. The distinction changed how I documented her complaint and what I flagged for the provider. One edge case I encountered that beginners miss involves timing. Subjective data changes depending on when you assess. Tina's blood glucose readings were higher in the afternoon than in the morning, and her reported symptoms mirrored that pattern. If you only assess once during a simulated shift, you're getting a snapshot. I learned to document the time of assessment alongside each subjective finding so the trajectory becomes clear. This also matters when you're comparing pre- and post-intervention data. Another practical tip that isn't in the textbooks: document exactly where Tina was sitting, what she was doing, and her affect when she reported each symptom. She described her foot numbness while actively rubbing her calves. She reported her anxiety with visible hand wringing. These behavioral cues add credibility to your subjective data and show clinical observation skills that professors notice.
Get the Full Details
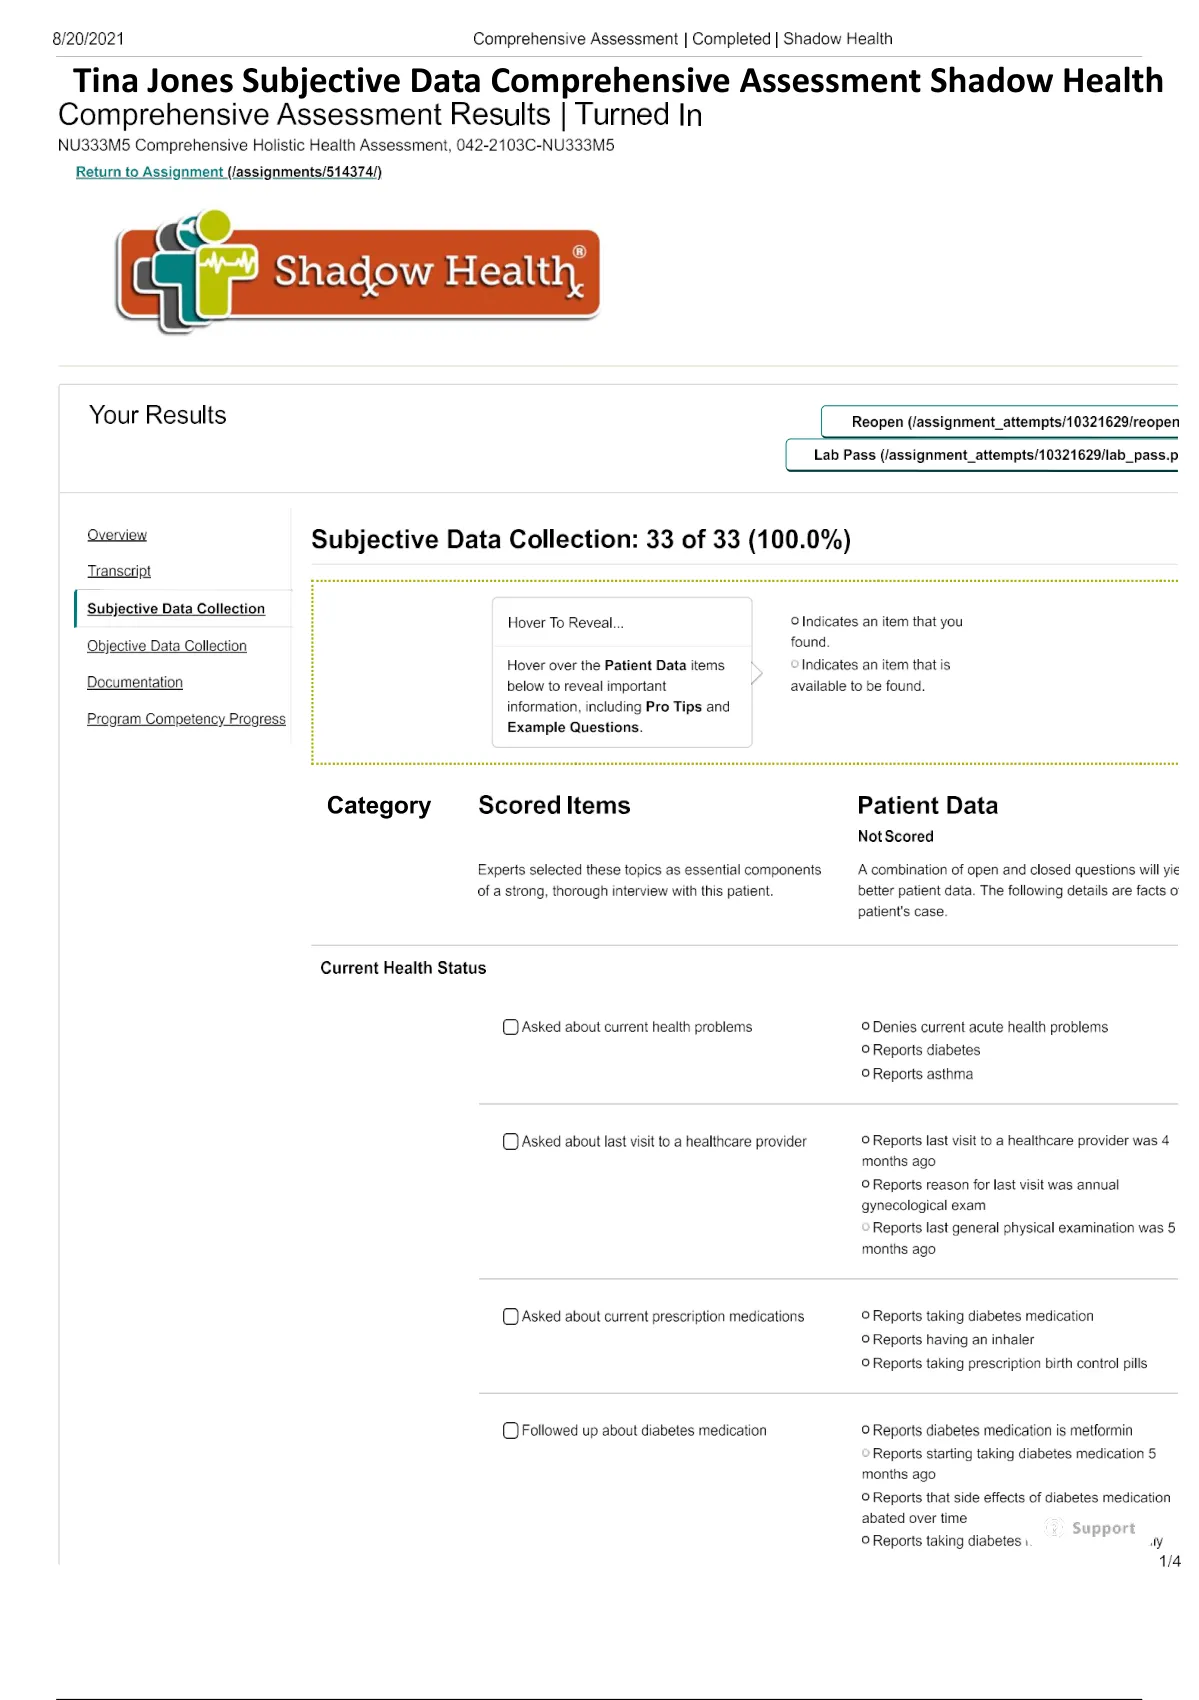
The subjective data collection for Tina Jones typically takes 20 to 30 minutes if you're thorough. Rushing through it produces incomplete assessments that miss psychosocial factors. Taking too long without structure produces repetitive documentation that adds no new information. The sweet spot is asking your core questions in the first ten minutes, then spending the remaining time exploring the areas that emerge as significant. When you compile everything, organize by system but cross-reference where symptoms overlap. Tina's polyuria and polydipsia are endocrine-related, but her fatigue could be cardiovascular, endocrine, or psychiatric. Documenting those possibilities explicitly in your subjective section shows clinical reasoning rather than simple data collection. That distinction separates B-grade assessments from A-grade ones. One thing to watch for: students often confuse subjective and objective data when working with standardized patients. If Tina tells you her blood sugar has been running high, that's subjective even though it references a measurement. The measurement itself—the actual glucose reading—is objective. Her report of the reading is subjective. Keep those boundaries clear in your documentation or your instructor will dock points.
The full assessment also requires you to synthesize subjective data with whatever objective findings you collect—vital signs, lab results, physical exam observations. But the subjective portion stands on its own as a narrative of the patient's experience. If that narrative is accurate, detailed, and organized, the rest of the assessment builds on solid ground.