Pharmacology doesn't have to be the nightmare everyone says it is.
I've sat through too many first-year med students drowning in drug names and mechanisms, and I've been there myself. The volume is brutal. But the way most people approach it is backwards from the start. They try to memorize everything at once, which is why they burn out by week three. The real problem isn't intelligence or work ethic. It's that pharmacology has a layered structure, and if you build on the wrong foundation, everything after that becomes exponentially harder. Kinetics first. Then mechanisms. Then the drugs themselves. People do it backwards every single time.
Tips For Pharmacology Easy
Here's what actually works in practice, not what some textbook says should work. Half the people I see struggling never truly internalize half-life, clearance, volume of distribution, or bioavailability. They memorize formulas for a test and forget them two weeks later. That gap comes back to haunt them when they hit clinical pharmacology. If you can explain what happens when you change a patient's renal function to the half-life of a drug, you already understand more than most residents. I learned this the hard way during my pharmacy rotation. A patient on phenytoin had his albumin drop to 2.0 from malnutrition. The total phenytoin level looked therapeutic at 12 mcg/mL. But the free fraction was nearly 40% instead of the normal 10%. He was showing signs of toxicity. I recalculated the free level using the Sheiner-Tozer equation and realized the dose needed to be cut by a third. That was the moment I understood why kinetics matters beyond exam scores.
The workaround I use now is simple. Don't memorize the equations. Understand what they represent physically. Volume of distribution is just how widely a drug spreads out in your body relative to the blood concentration. If it's huge, the drug is hiding in fat or tissue. If it's small, it's staying in the blood. That's it. The math follows from that intuition.
Get the Full Details

Group drugs by mechanism, not by brand name
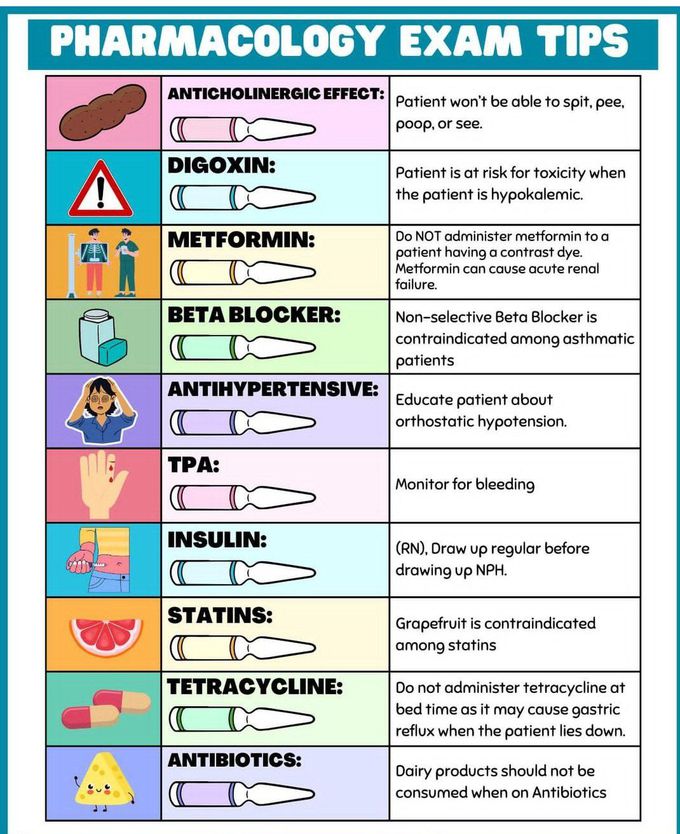
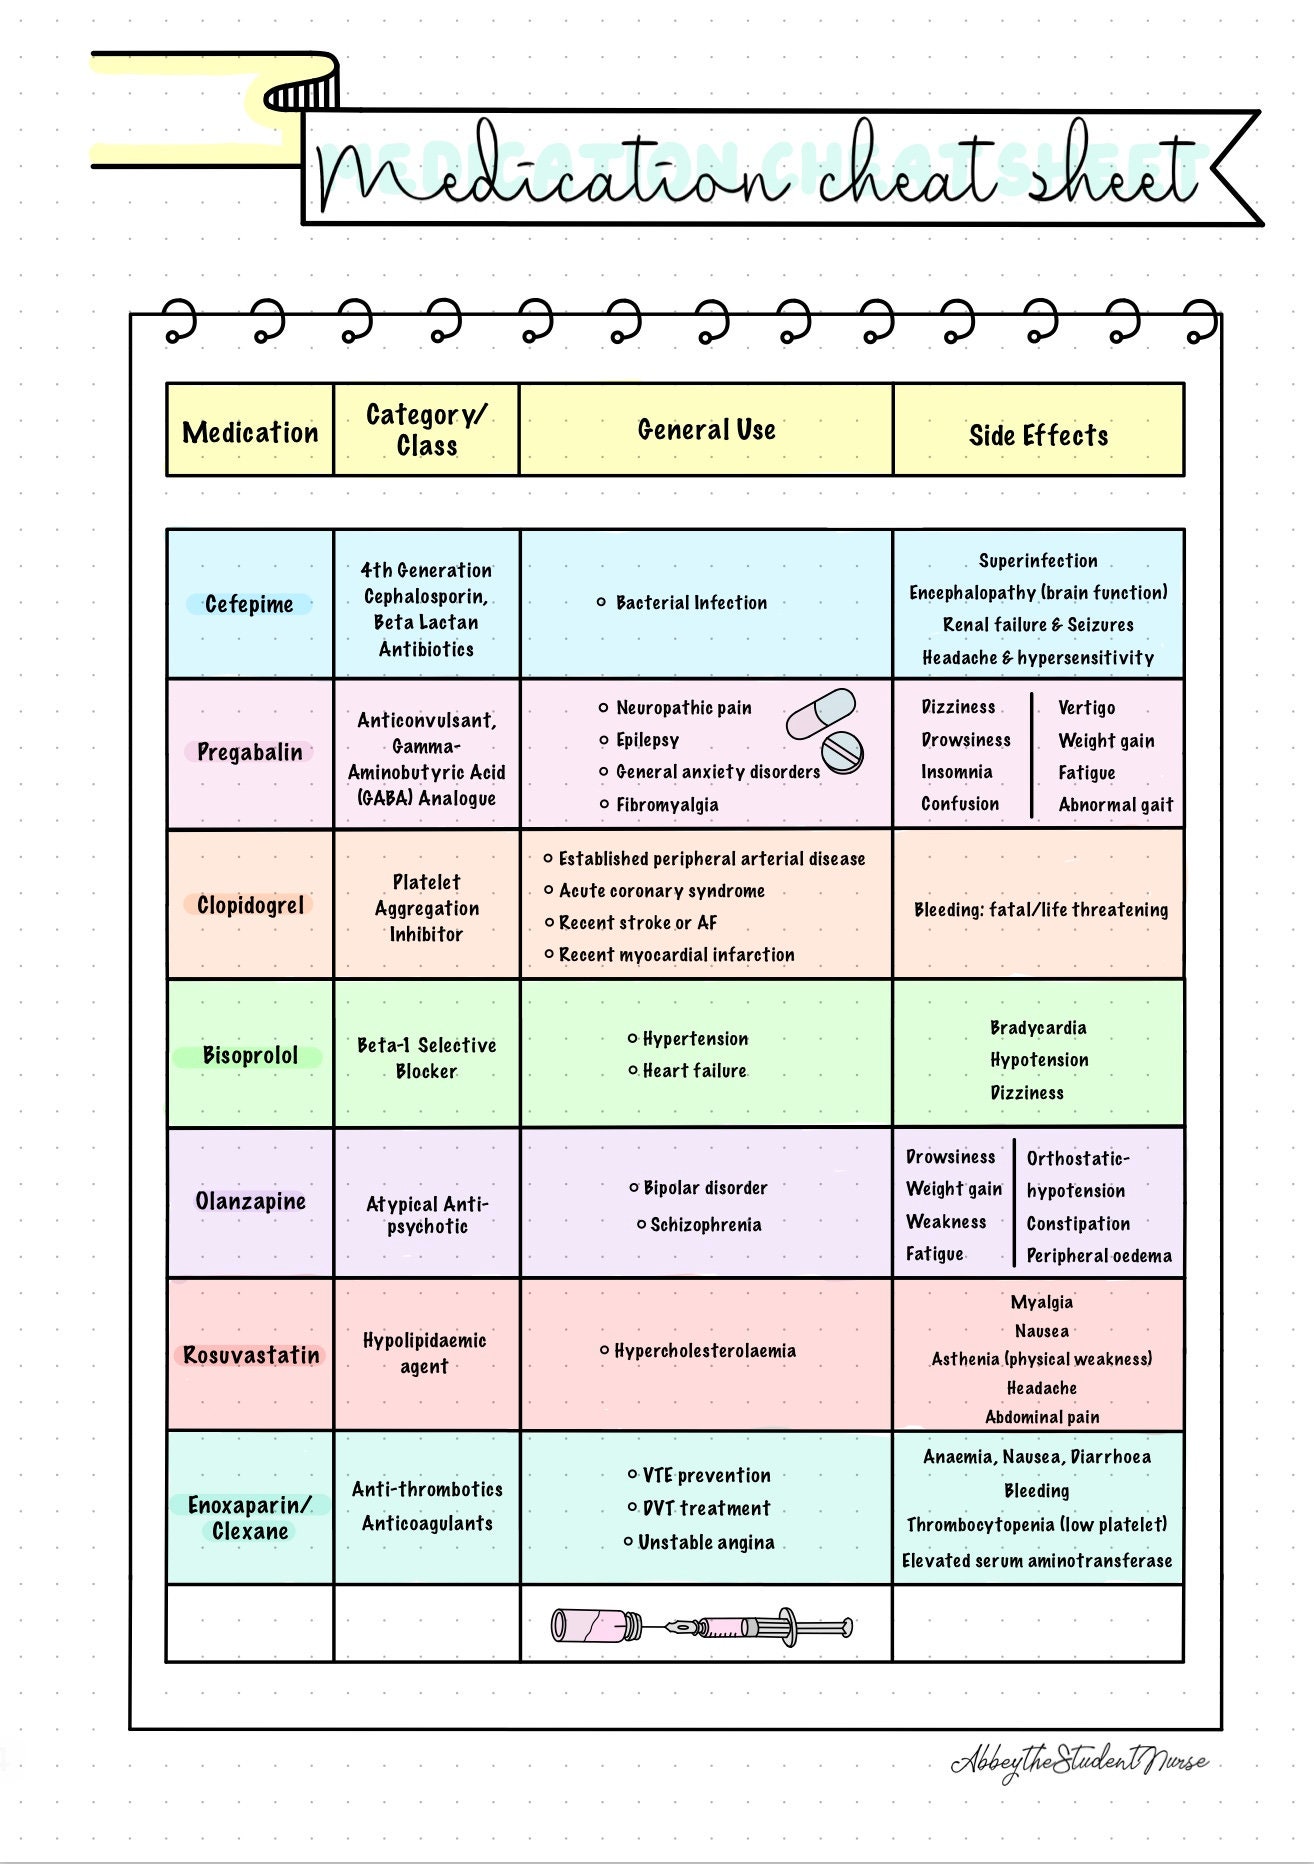
This is where most study guides fail you. They'll give you a list of beta-blockers with trade names and ask you to memorize them alphabetically. That's noise. What actually sticks is understanding that metoprolol, atenolol, and bisoprolol are all cardioselective beta-1 blockers at therapeutic doses, while propranolol blocks both beta-1 and beta-2, which is why it can trigger bronchospasm in asthmatics. One concept replaces ten individual facts. When I was studying for boards, I made a habit of drawing out the receptor pathways first. ACE inhibitors block angiotensin-converting enzyme, so less angiotensin II, less aldosterone, more bradykinin. The cough side effect comes from bradykinin buildup, not from anything to do with blood pressure. Connect that to the mechanism and you don't need to memorize that cough separately. It's a direct consequence.
Use the side effect as a memory anchor, not a separate list
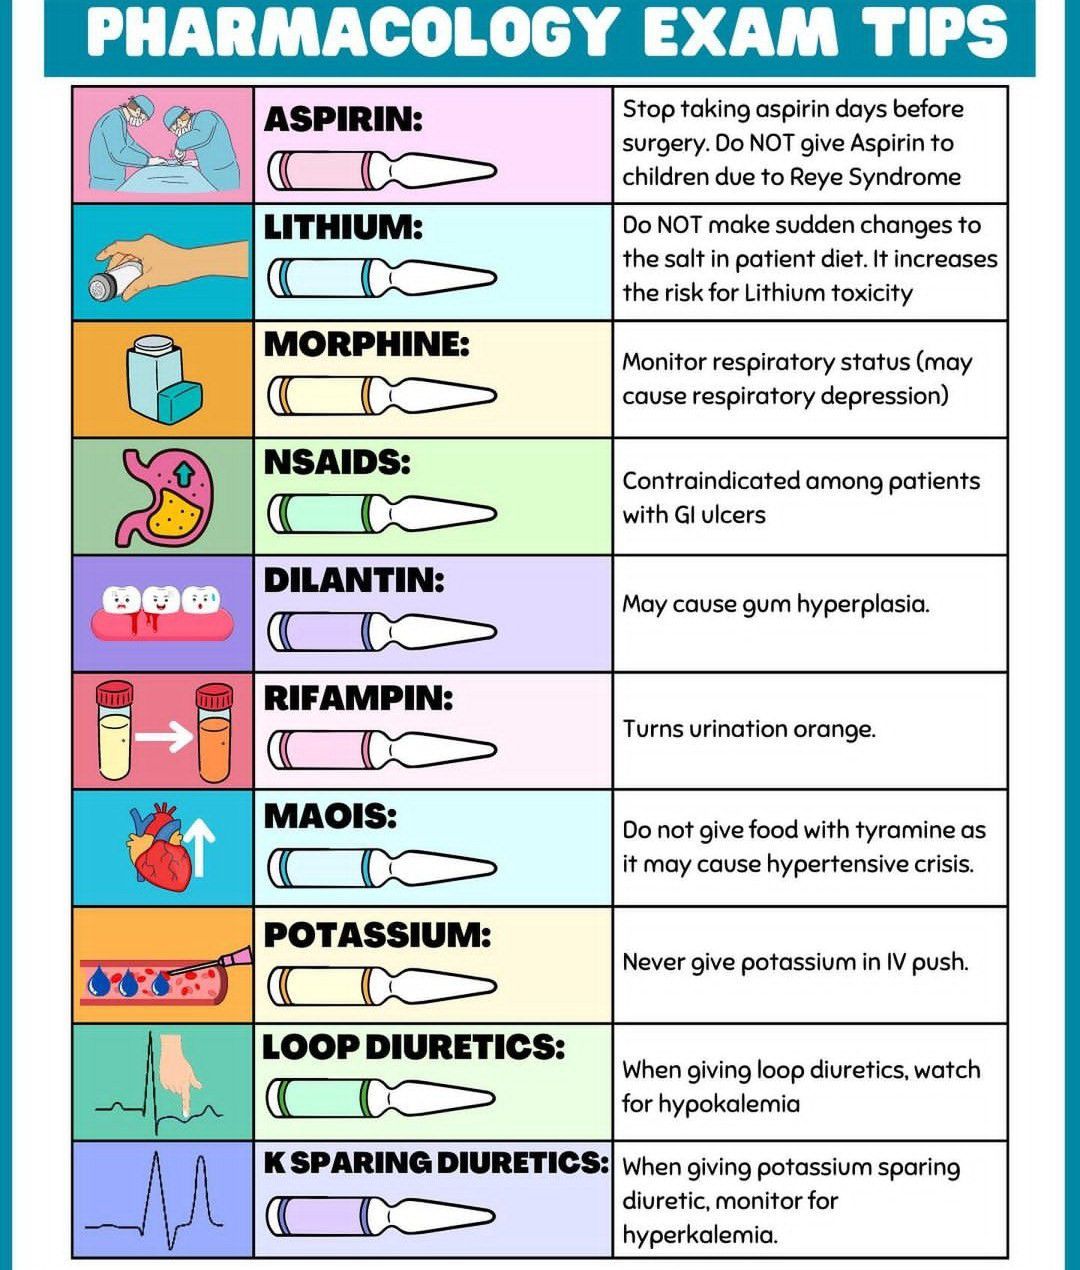
People make the mistake of treating side effects as trivia. They're not. Side effects are the mechanism working in the wrong place. Amiodarone causes pulmonary fibrosis because it concentrates in lung tissue and has a massive volume of distribution with a half-life measured in months. That half-life isn't just a number. It's why you can't stop the drug quickly when toxicity appears. It's why you monitor pulmonary function tests before and during treatment. One thing I wish someone had told me earlier: thyroid dysfunction from amiodarone happens because the drug is 37% iodine by weight. Each tablet contains about 75 mg of iodine. Your thyroid can handle maybe 150 micrograms a day. The organ is getting exposed to 500 times its daily requirement. That's not a coincidence. That's chemistry. Knowing this makes the endocrine side effects feel inevitable rather than random.
Active recall beats passive reading every time
I watched people highlight entire chapters of Goodman & Gilman and call it studying. That's not studying. That's decoration. The technique that actually moves information into long-term memory is retrieval practice. Close the book. Write down everything you remember about a drug class. Then open the book and fill in the gaps. The struggle you feel during that exercise is the learning happening. Comfort means you're not actually retaining anything. Spaced repetition software like Anki works here, but only if your cards are well-designed. A card that asks "What is the mechanism of lisinopril?" and expects "ACE inhibitor" is too shallow. A better card would show a clinical scenario: a patient with heart failure and bilateral renal artery stenosis is prescribed a new medication and develops acute kidney injury within days. The answer involves understanding why ACE inhibitors are contraindicated in that specific anatomy. That forces you to connect mechanism to clinical decision-making.

Know the limits of this approach
This system doesn't work if you're trying to cram four weeks of material into three days. No method does that. Pharmacology requires repeated exposure over time. The spaced repetition component exists because forgetting is inevitable without it, not because you can avoid it entirely. Another honest limitation: this approach assumes you have foundational knowledge in physiology and biochemistry. If you don't understand how the renin-angiotensin-aldosterone system works or what G-protein coupled receptors do, jumping into pharmacology mechanics will feel like reading a foreign language. I had a student once who spent six weeks on drug mechanisms before going back and actually learning cardiovascular physiology. The second pass through pharmacology took her half the time. She wasted those first six weeks. If you're severely behind on prerequisites, spend two weeks on the basics first. It sounds counterintuitive to slow down, but it's faster overall. Trying to layer pharmacology on a cracked foundation just makes the whole thing collapse later.
A practical weekly structure that actually holds
Here's what a realistic schedule looks like when you're juggling other coursework. You don't need five hours a day. You need focused ninety-minute blocks with clear objectives. Monday: pick one drug class. Draw the mechanism pathway from memory. Check what you missed. Do twenty active recall questions. Tuesday: review Monday's class using only your notes from memory. Add one clinical case or side effect you connected to the mechanism.
Wednesday: spaced repetition review of everything from the past two weeks. Nothing new. Just maintenance. Thursday: second drug class. Same process as Monday. Friday: review both classes together. Find the overlaps. ACE inhibitors and ARBs both affect the same pathway at different points. Writing that comparison down cements both drugs.
Saturday: practice questions. Clinical vignettes. This is where you test whether you can apply knowledge, not just recognize it. Sunday: rest. Your brain consolidates memory during sleep, not during extra study sessions. I've seen people skip this and then wonder why they blanked on everything during exams. It's not a willpower problem. It's biology.
The drugs that always trip people up
Warfarin deserves extra attention because it's notoriously messy. The narrow therapeutic index, the drug interactions, the vitamin K antagonism mechanism. I found that drawing out the coagulation cascade and marking exactly where warfarin hits versus where heparin hits made the comparison clicks instantly. Warfarin affects factors II, VII, IX, and X by blocking vitamin K epoxide reductase. Heparin activates antithrombin III, which inactivates thrombin and factor Xa directly. Two completely different paths to the same clinical goal. That distinction matters when a patient on warfarin needs emergency surgery and you have to decide between vitamin K, FFP, or PCC for reversal. Antibiotics are another trap. The naming conventions alone are designed to confuse you. Penicillins, cephalosporins, carbapenems, monobactams all hit cell wall synthesis but at different points and with different spectra. The shortcut is to group them by generation for the cephalosporins and by spectrum for the penicillins. Don't try to memorize every individual antibiotic. Memorize the patterns. If you know that third-generation cephalosporins have better gram-negative coverage and can cross the blood-brain barrier, you can predict properties of ceftriaxone and cefotaxime without memorizing them separately.
One thing most people get wrong about dosing
Renal dosing adjustments aren't arbitrary. They follow directly from clearance. If a drug is primarily renally excreted and the patient's creatinine clearance drops to 30 mL/min, you either reduce the dose or extend the dosing interval. The choice depends on whether the drug has a narrow therapeutic index. Gentamicin is once-daily dosing by design because of its concentration-dependent killing and post-antibiotic effect. Lowering the CrCl means you extend the interval, not halve the dose. Digoxin is different. Narrow therapeutic index, so you reduce both the dose and watch the interval carefully. Knowing why the adjustment works matters more than memorizing which drugs need it. Exam questions will test the reasoning, not the table. I've seen students who could recite the adjustment for vancomycin but couldn't explain why trough levels matter more than peak levels for this particular drug. That gap shows up fast in clinical rotations.
Bottom line
Pharmacology is learnable if you stop treating it like a memorization task and start treating it like a logic system. Every drug property traces back to chemistry or physiology. When you follow that thread, the amount of raw memorization drops significantly. You still have to put in the work. There's no shortcut around that. But the work becomes more efficient when you understand what you're doing instead of just pushing information through your brain and hoping it sticks. The students who end up comfortable with pharmacology aren't the ones who studied the hardest. They're the ones who studied the right way from week one. Start with kinetics. Build mechanisms. Connect everything back to physiology. Review on a schedule that respects how memory actually works. Avoid the temptation to prioritize volume over understanding. Do that and the rest follows.