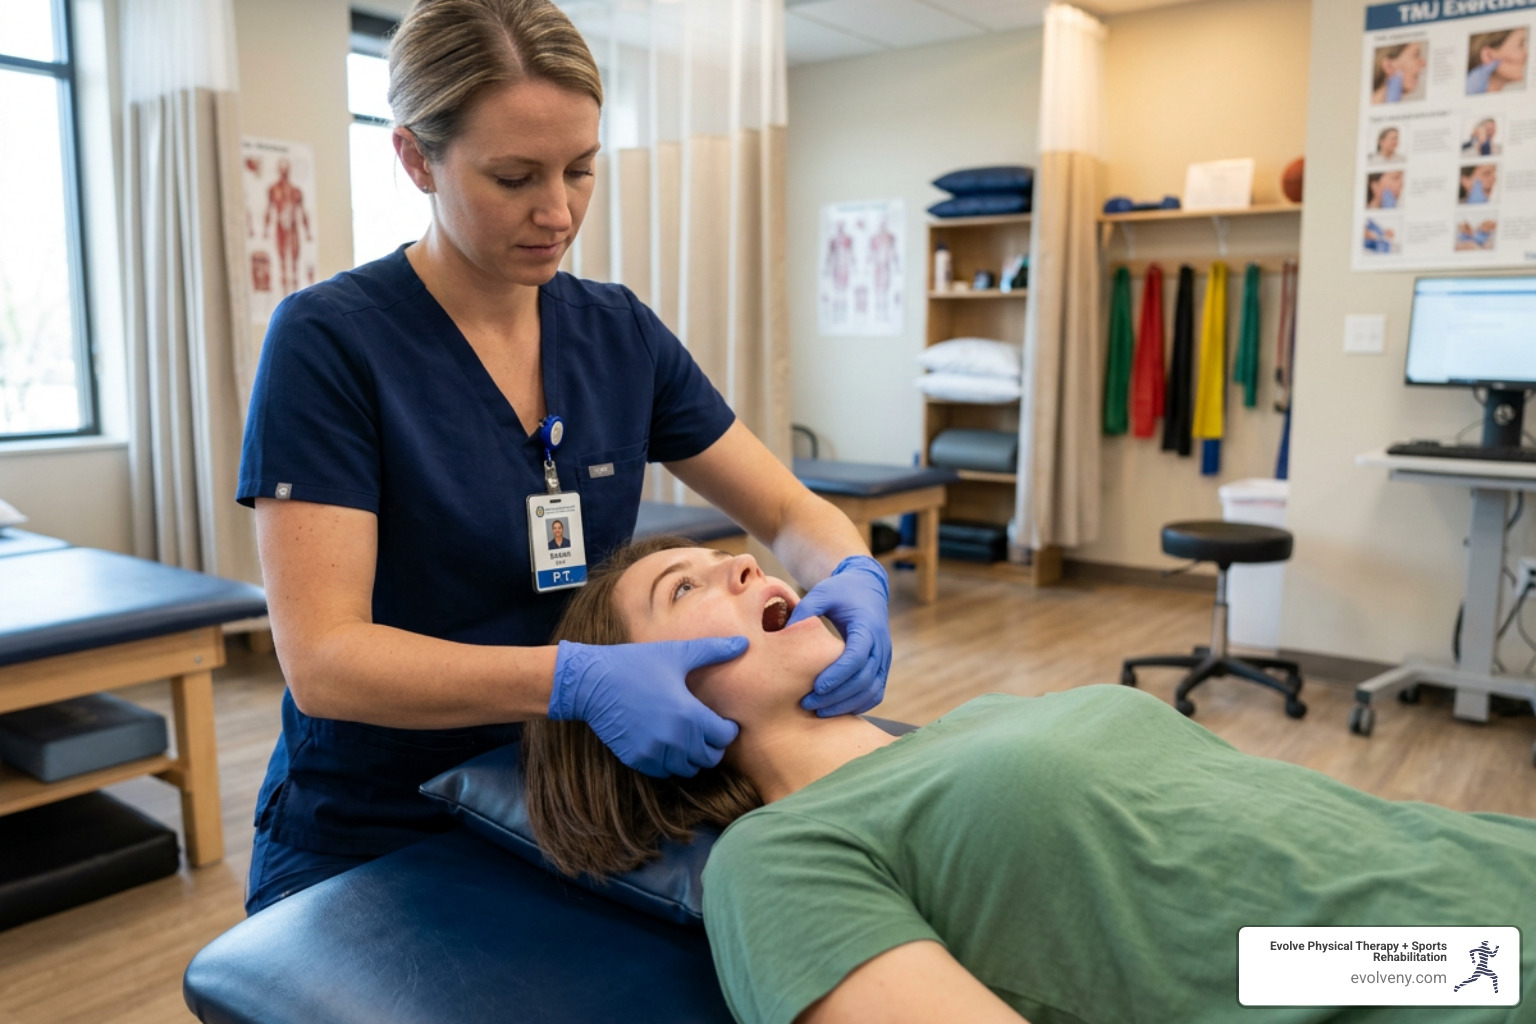
What Actually Happens During a TMJ Physical Therapy Evaluation
Most people walking into a clinic expect someone to press on their jaw and call it a day. A proper evaluation takes longer than that and involves a lot more than palpation. You are looking at roughly 45 to 60 minutes for a thorough initial assessment, sometimes more if the patient has a complex history. The reason is straightforward: the temporomandibular joint does not exist in isolation. It connects to the cervical spine, the scalenes, the suboccipitals, and the diaphragm through fascial and neural pathways. Ignoring any of those regions produces an incomplete picture.Tmj Physical Therapy Evaluation: What It Actually Looks Like
I start with the subjective interview. This is where most evaluations succeed or fail before you ever touch the patient. I ask about sleep position, chewing habits, stress levels, dental work, and whether they clench during the day or grind at night. I also ask about headaches, ear fullness, and whether opening wide causes any deviation or locking. One detail that trips up a lot of clinicians is asking about voice changes or fatigue with prolonged talking. That points toward suprathyroid and infrahyoid muscle involvement, which most people overlook entirely.Then comes the objective portion. I measure resting mouth opening using a caliper, usually looking for 40 to 50 millimeters in healthy adults. Deviation during opening tells me which side has a restriction. If the chin drifts left on opening, the left condyle is likely delayed or stuck. I note whether the deviation corrects itself as the mouth opens wider, which suggests a capsular issue rather than a disc displacement with reduction.
Palpation follows. I check the lateral pterygoids by pressing through the oral vestibule while the patient resists opening. I evaluate the masseter, temporalis, and medial pterygoid externally. The sternocleidomastoid and trapezius get a hard look because trigger points there refer pain directly into the jaw. I also assess cervical range of motion, particularly rotation and lateral flexion, since C1 through C3 dermatomes overlap with trigeminal referral patterns.The Assessment Steps Most Clinicians Skip
Here is where the counter-intuitive part comes in. A lot of providers stop after checking jaw movement and joint sounds. That misses the bigger problem in roughly half of chronic TMJ cases. I test the hyoid bone mobility. If the suprahyoid and infrahyoid muscles are hypertonic, the hyoid will not glide smoothly during swallowing or during active mouth opening. I also assess thoracic outlet positioning and upper thoracic mobility. Poor thoracic extension forces the head forward, which increases compressive load on the TMJ by altering the position of the entire mandible. I use specific terminology that beginners miss. Active constrained arc testing helps distinguish between articular and myofascial sources of pain. With articular restrictions, pain spikes at the end range. With myofascial contributors, the pain is mid-range and often replicates with resisted movements. Reciprocal clicking without pain usually indicates disc displacement with reduction, which may not need aggressive manual therapy at all. Painful clicking, locked jaw, or a sudden change in bite alignment changes the entire treatment approach.I recall a patient who presented with what looked like classic bruxism-related TMJ pain. Masseter trigger point work and a night guard produced zero improvement over three sessions. The breakthrough came when I tested her cervical spine and found severe restriction at C5-C6 with significant scalene hypertonicity. The actual driver was a compressed C5 nerve root referring pain into the jaw region. Treating the cervical segment and releasing the scalenes reduced her symptoms by about seventy percent in two weeks. The jaw was the symptom, not the source.
Where This Evaluation Falls Short
An in-person physical therapy evaluation cannot diagnose internal derangement of the disc without imaging. Palpation and movement tests suggest problems, but they do not confirm them. MRI or CBCT imaging is necessary for that level of detail. If a patient has a known disc displacement with reduction and no other contributing factors, aggressive manual therapy may actually worsen symptoms in the short term. In those cases, a more conservative approach focusing on neuromuscular re-education and postural modification produces better outcomes. Imaging also matters when there is degenerative joint disease present. Arthritic changes in the condyle or fossa respond poorly to aggressive mobilization. Soft tissue work and gentle arthrokinematic movements are appropriate, but high-velocity techniques or forceful stretching should be avoided entirely. This is not a minor distinction. Pushing a degenerative joint too hard can accelerate cartilage breakdown.Another limitation is patient compliance. The evaluation provides a snapshot. Real improvement depends on consistent home exercise, sleep posture changes, stress management, and often dietary modifications like reducing chewy or tough foods for a period. Without those, even a perfectly executed treatment plan will plateau quickly. I see this repeatedly. Patients who commit to the full protocol typically see meaningful reduction in pain and improved jaw function within four to six weeks. Those who skip the home components often stall out around week three and then discontinue therapy entirely.
Get the Full Details