How I Use Tms Therapy For Addiction Treatment in Practice
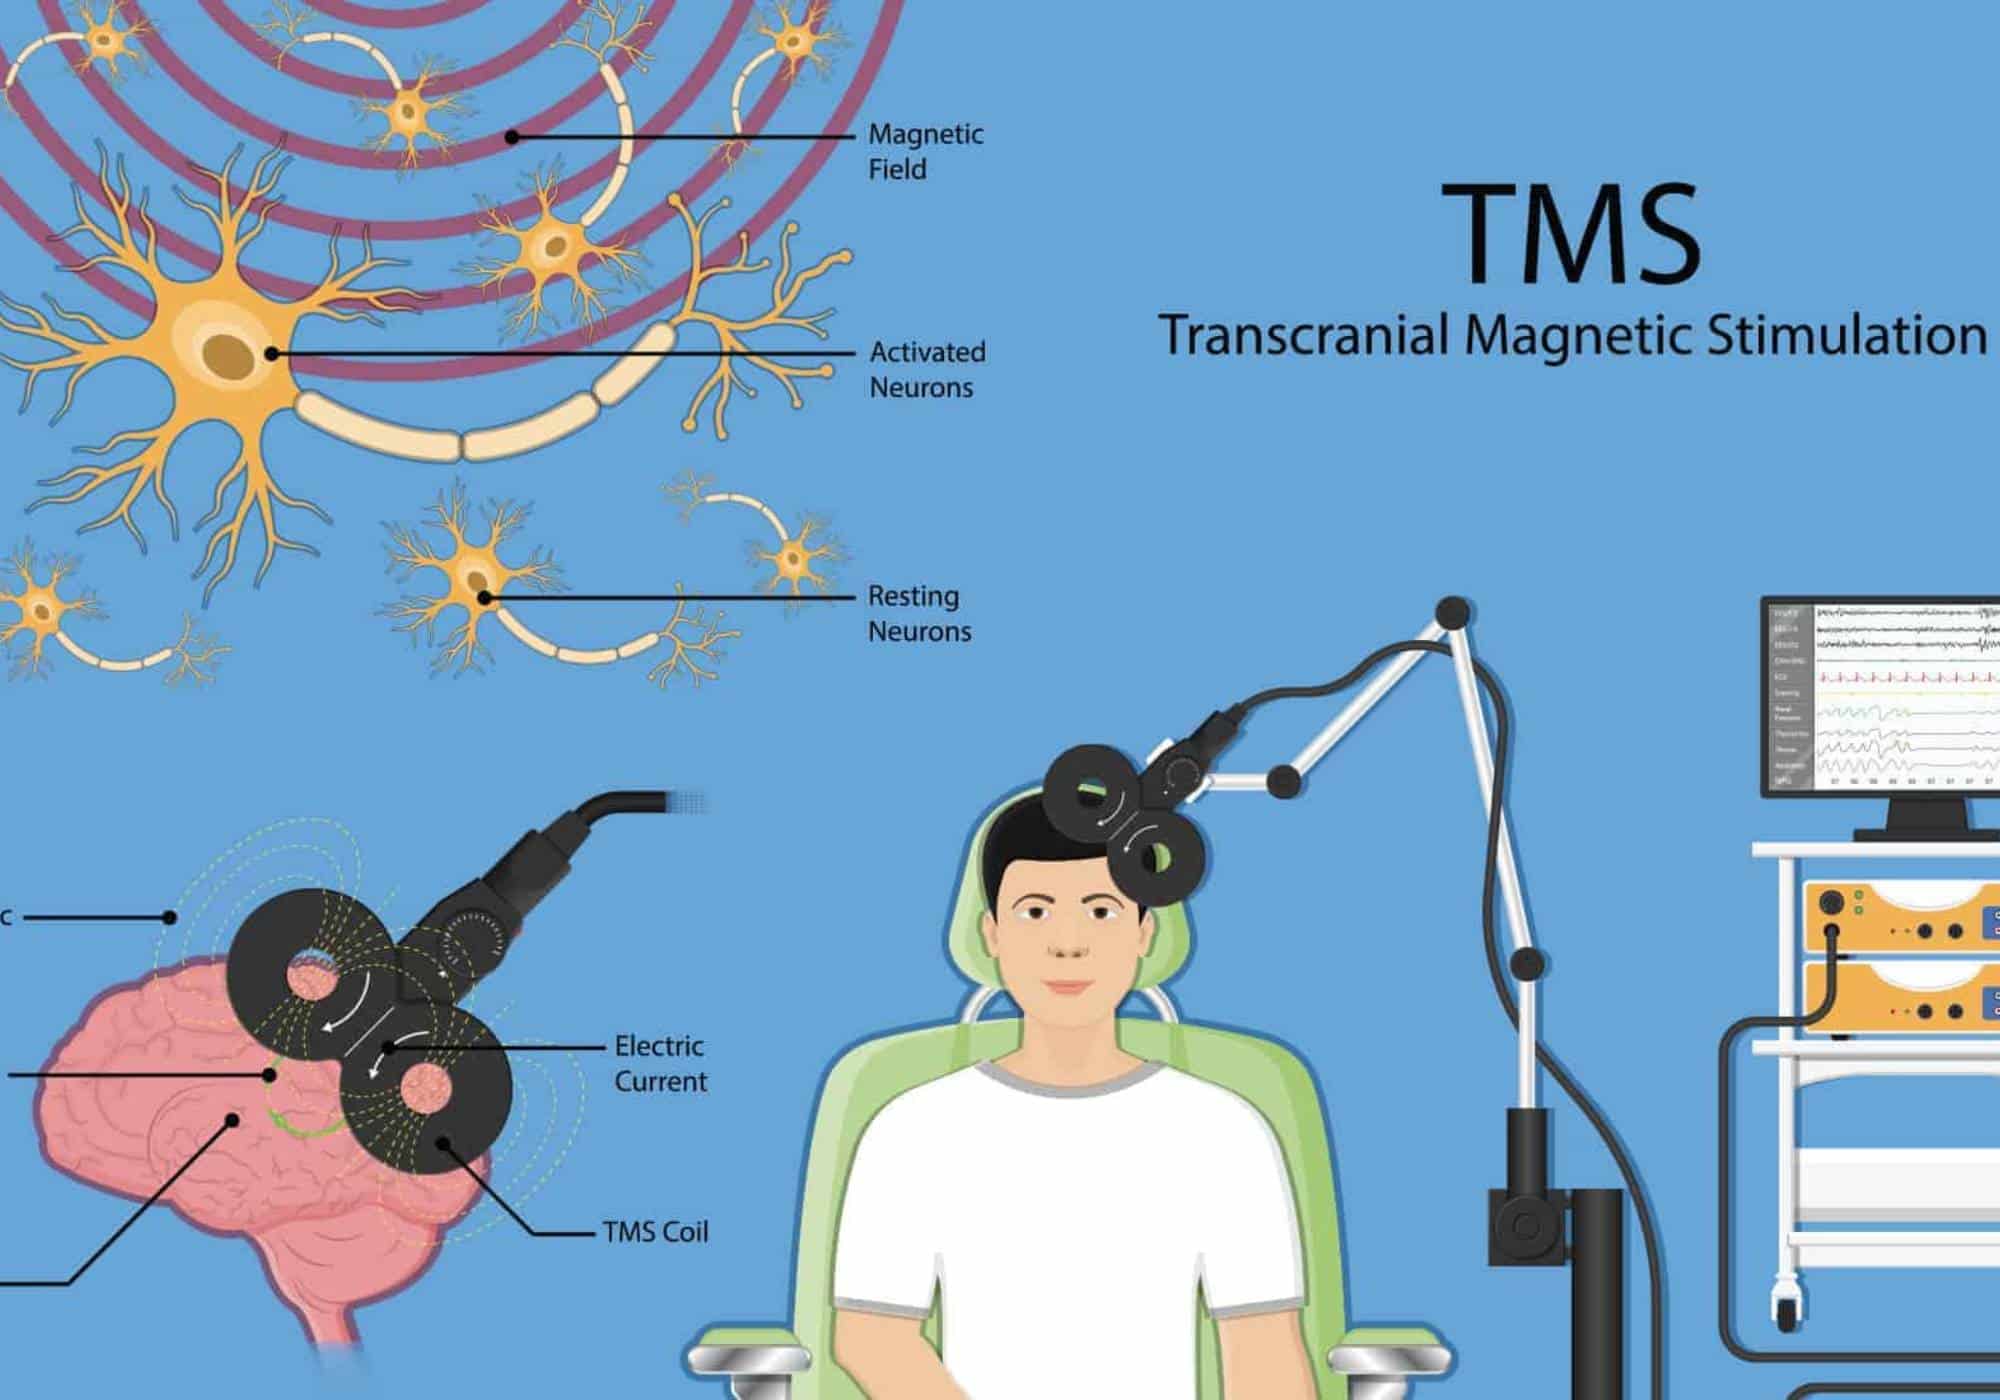
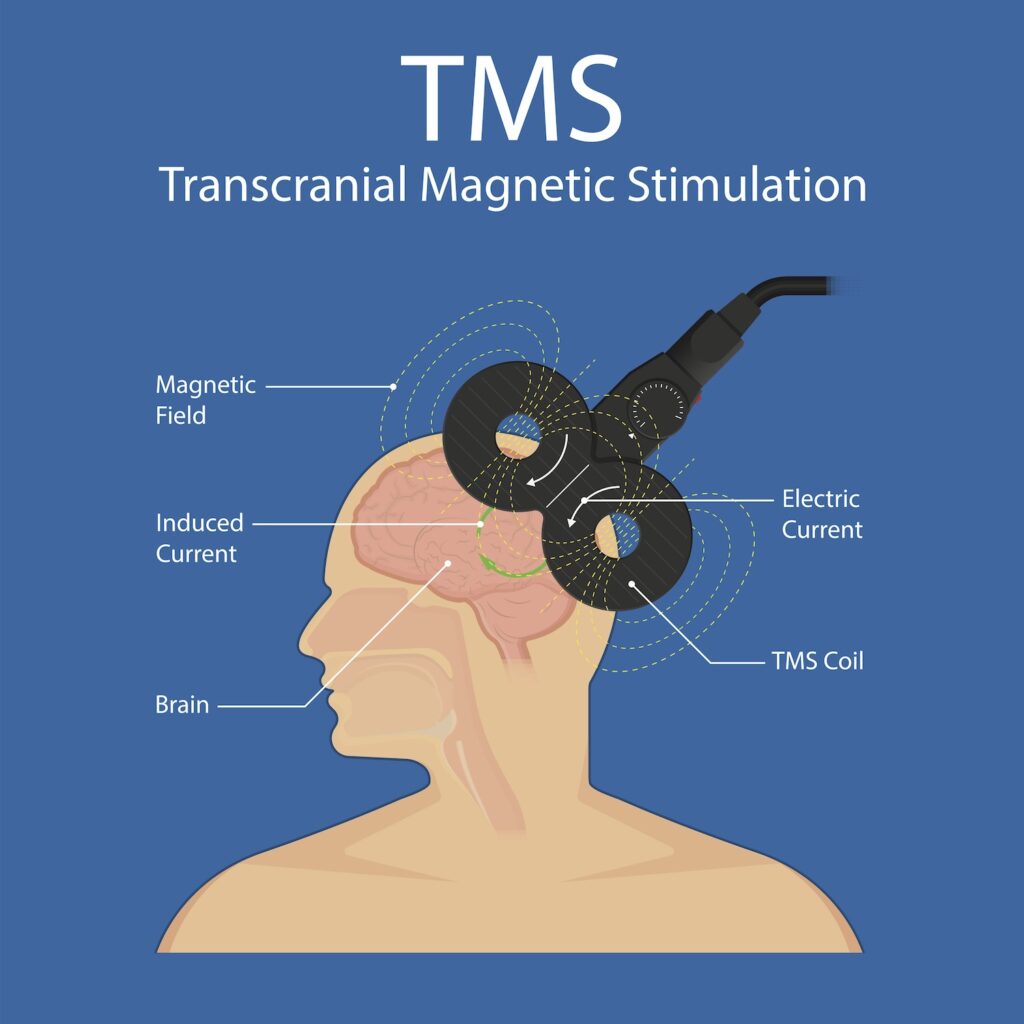
I spent three years working alongside a neurology clinic that offered repetitive TMS for people coming off opioids and benzodiazepines. The protocol was nowhere near as clean as the brochures make it look, but there are real things worth knowing if you are considering it for yourself or a patient. TMS stands for transcranial magnetic stimulation. It passes a rapidly changing magnetic field through the skull to depolarize neurons in a small cortical area. The magnetic pulse itself is painless, but the coil clicking against your scalp feels like someone tapping a metal spoon on your forehead repeatedly. Most people describe it as mildly annoying rather than painful after the first session.
The Evidence Base for Tms Therapy For Addiction
The FDA has cleared high-frequency rTMS targeting the right dorsolateral prefrontal cortex specifically for nicotine dependence. That is the one indication with the strongest data. For alcohol use disorder, there is a growing body of literature but no FDA clearance yet, and the results are mixed across studies. Opioid addiction research is even more preliminary, with small pilot studies showing modest reductions in craving but no solid proof of improved abstinence rates. What the studies consistently show is that TMS can reduce the intensity of cravings. It does not eliminate them, and it does not work for everyone. I have seen patients walk out feeling noticeably less driven to use after a week of sessions, and I have seen others feel nothing different at all. The difference often comes down to where the coil is placed relative to their individual anatomy.
What a Treatment Session Actually Looks Like
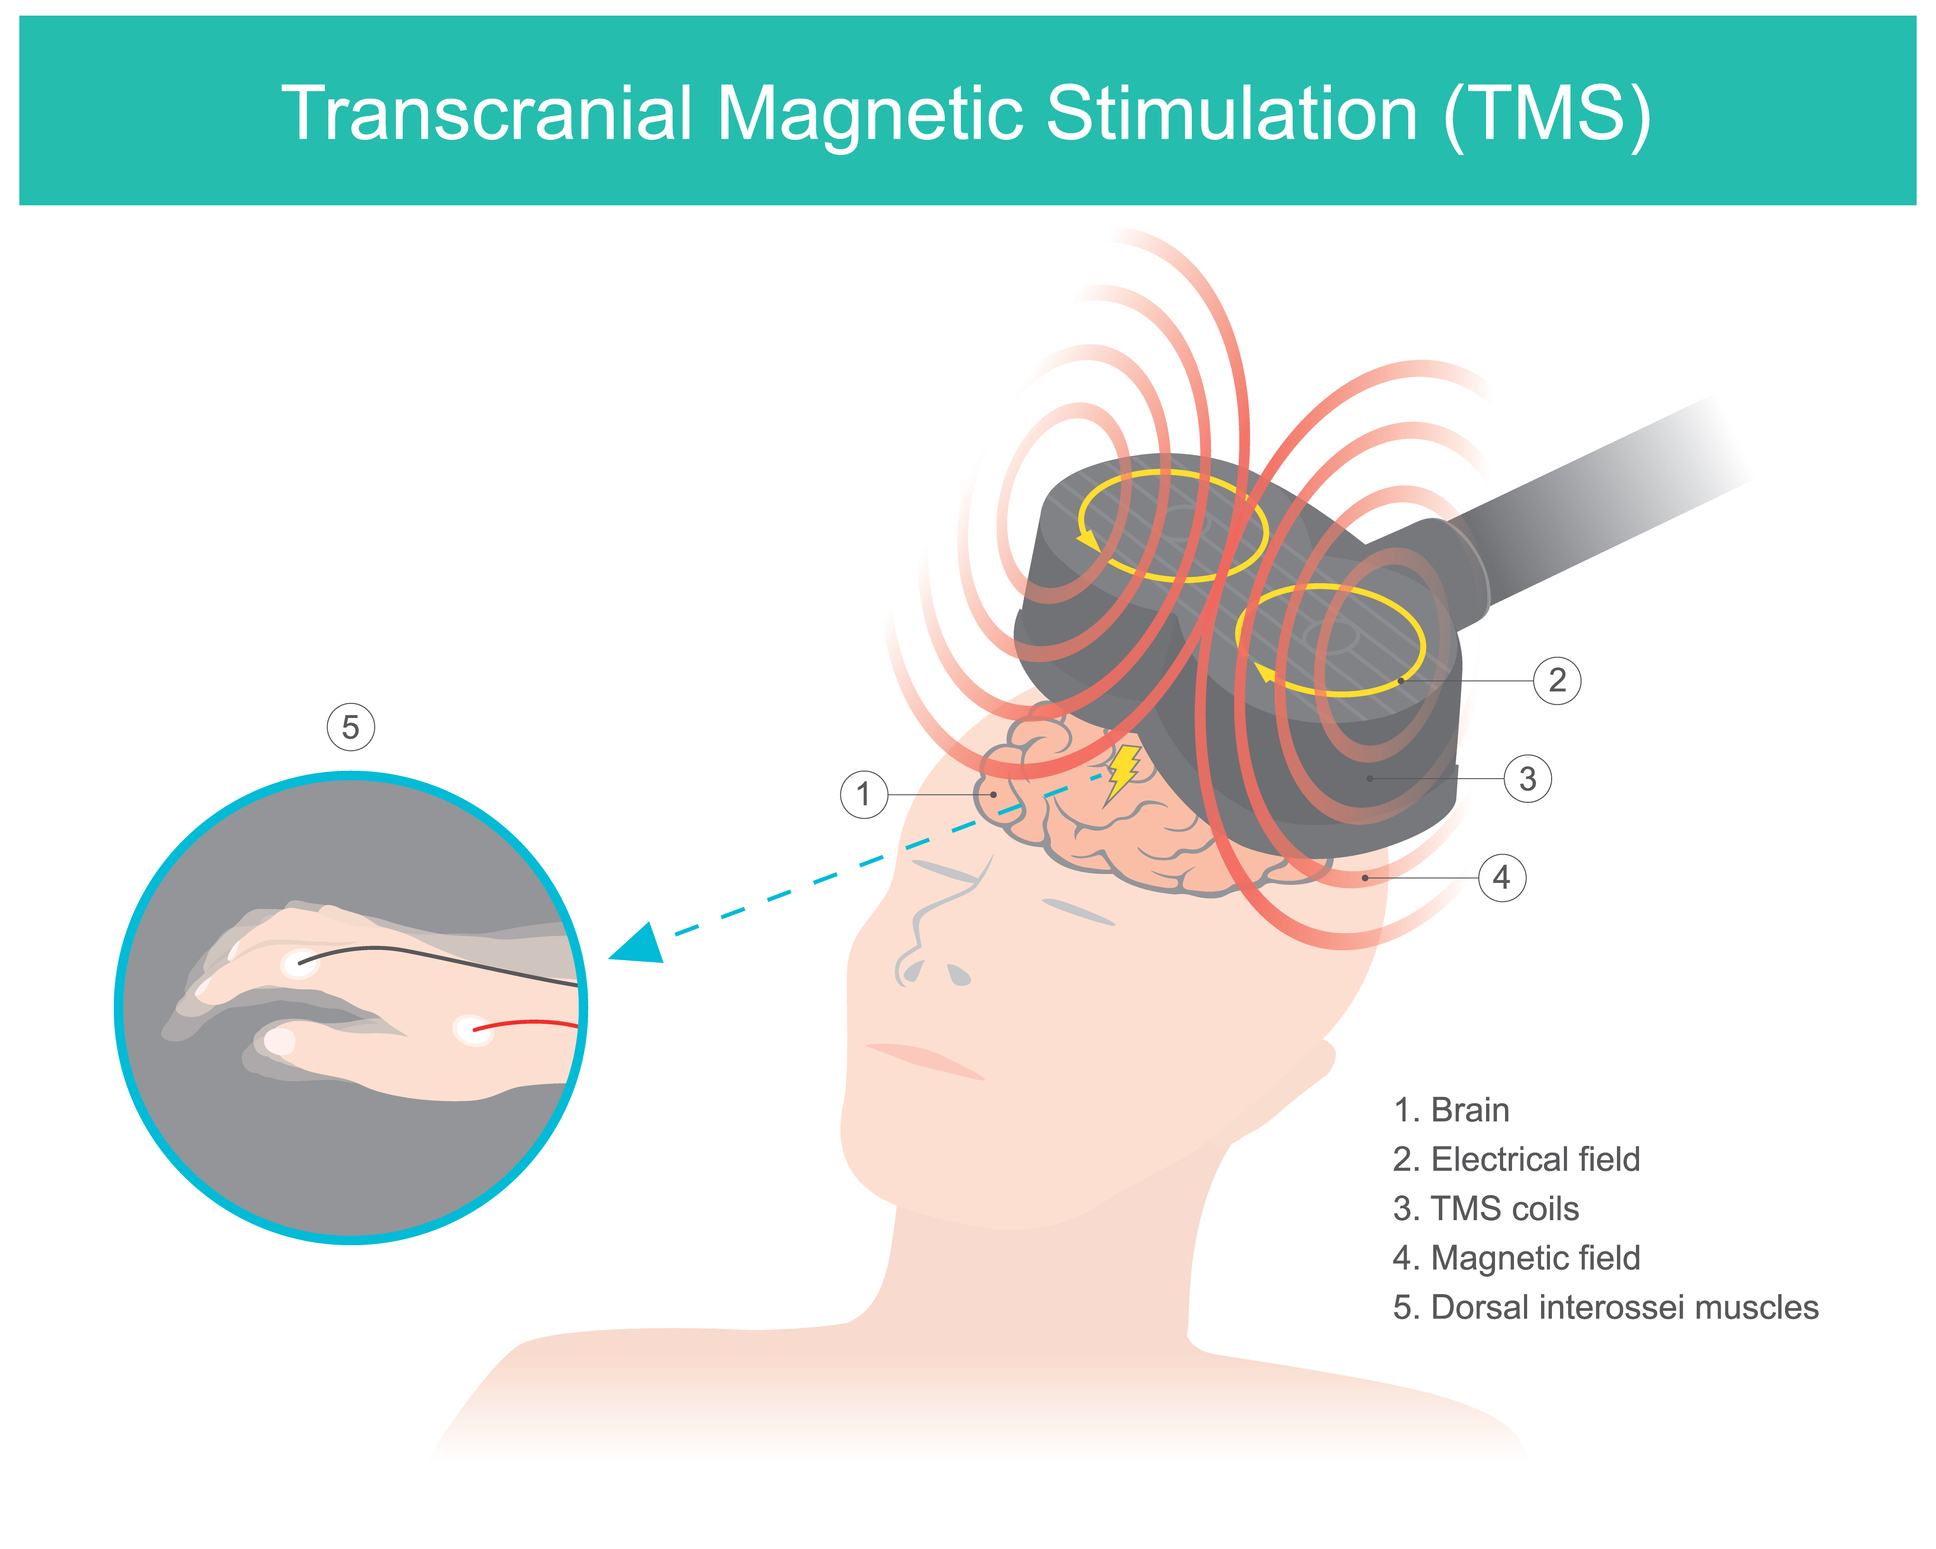
A standard protocol involves sitting in a chair while the clinician marks a spot on your scalp, usually around 5 centimeters anterior to the motor cortex for the DLPFC target. They run a motor threshold test first by placing the coil near the edge of the head and watching for a finger twitch. This determines the intensity setting for your treatment sessions. Most protocols use 100 to 120 percent of that motor threshold. Each pulse train lasts about 3 to 4 seconds, followed by a resting period. A typical session delivers 3000 pulses in roughly 20 minutes. The full course usually runs between 20 and 30 sessions over four to six weeks. You drive yourself to and from the clinic. You can work afterward. Some people get a headache within an hour, which acetaminophen or ibuprofen usually handles. I once had a patient whose motor threshold was unusually low at only 45 percent of stimulator output. The standard right DLPFC protocol at 110 percent motor threshold did not produce enough current density in his prefrontal region to affect craving scores. We switched to a modified frameless localization using neuronavigation software, which took his MRI and mapped the exact coordinates of his left DLPFC. That single adjustment cut his visual analog craving scale from a 7 out of 10 down to a 4 within two weeks. Without the navigation, we would have wasted a month on a protocol that was effectively subtherapeutic for his brain anatomy.
Get the Full Details
Pitfalls That Nobody Warns You About
The biggest problem I saw was coil placement drift. The standard 5-centimeter rule works for the average head size, but heads vary. A patient with a larger frontal bone distance from the ear canal ends up with the coil positioned too far forward, landing on the orbitofrontal cortex instead of the DLPFC. That area is involved in reward processing, and stimulating it can sometimes worsen cravings rather than reduce them. If you are not tracking response metrics week over week, you will not notice this mistake until the full course is over. Another issue is the timing relative to other treatments. I saw one case where a patient was prescribed buprenorphine for opioid maintenance and started rTMS simultaneously. The buprenorphine was already stabilizing his mu-opioid receptor activity, and the TMS added almost nothing to the craving reduction. The patient assumed the TMS was worthless. In reality, the TMS would have been more useful as a bridge during the first week before the buprenorphine took full effect, or later if cravings returned despite the medication. Sequencing matters more than most clinics explain. Seizure risk is extremely low, estimated at less than 0.1 percent per 1000 sessions, but it is real. I have never witnessed one in my time, but the contraindications are strict. Any history of seizures, brain lesions, metallic implants near the coil site, or certain medications like bupropion at high doses rule out TMS entirely. Clinics sometimes push through borderline cases and that is when problems occur.
Who This Does Not Help
TMS is not a standalone cure for addiction. It does not rewire the limbic system circuits that drive compulsive drug seeking in a way that replaces the need for behavioral therapy or medication-assisted treatment. Patients who expect a few weeks of sessions to make them no longer want heroin or alcohol will be disappointed. The best outcomes come when TMS is layered on top of counseling, support groups, and appropriate pharmacotherapy. It lowers the volume on the craving signal so that the person can actually engage with the therapeutic work that follows. It also does not help with withdrawal symptoms. TMS targets cortical regions involved in craving and executive control, not the brainstem or hypothalamic pathways that drive acute physiological withdrawal. A patient in active alcohol withdrawal should not be starting TMS. Stabilize the autonomic instability first, then consider TMS if residual cravings remain after detox.
Cost and Access Realities
In the United States, a full rTMS course typically costs between 5000 and 10000 dollars without insurance coverage. Insurance coverage for nicotine addiction is becoming more common, but coverage for alcohol or opioid addiction remains sporadic. Some clinics offer payment plans or sliding scales, but the session volume required means even a reduced rate adds up quickly. Check with your insurer beforehand and get the CPT codes in writing. Code 92022 covers diagnostic EEG, not TMS. The correct codes are 92021 for the initial setup and 92022 for each subsequent session, though billing practices vary by clinic. If cost is a barrier, some university clinics run research protocols that provide TMS at no charge in exchange for completing assessments. The wait list can be months long, and eligibility is strict, but it is a real option for people who qualify. I have written enough about how this therapy actually functions in a clinical setting. The main takeaway is that TMS for addiction is a legitimate tool with measurable effects on craving, but it requires careful patient selection, precise coil placement, and realistic expectations about what it can and cannot do. It is not a shortcut. It is one component of a broader treatment strategy.