What Actually Happens During a TMS Session
Most people walk into their first transcranial magnetic stimulation appointment thinking it is some kind of brain surgery or electroshock therapy. It is neither. You sit in a chair that looks like a dental recliner, a neurostimulator hums behind you, and a figure-eight coil gets pressed against your scalp. Then it clicks. Fast. Click click click click. The magnetic pulse passes through your skull and induces a small electrical current in your prefrontal cortex. That is it. No anesthesia, no recovery time, no needles. I spent three years working at a neuromodulation clinic before the whole industry got swamped by telehealth startups and drop-shipped brain devices. One thing I learned early: the actual Tms Therapy For Depression Success Rate is nowhere near as clean as the pharmaceutical companies want you to believe. The published numbers are real, but they come from narrowly defined patient populations that would not represent the person sitting in your waiting room.
Tms Therapy For Depression Success Rate In Real Practice
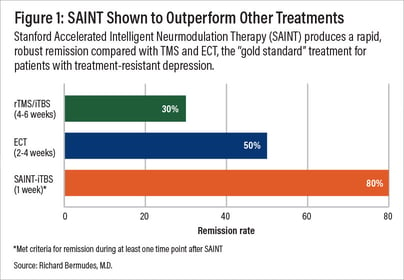
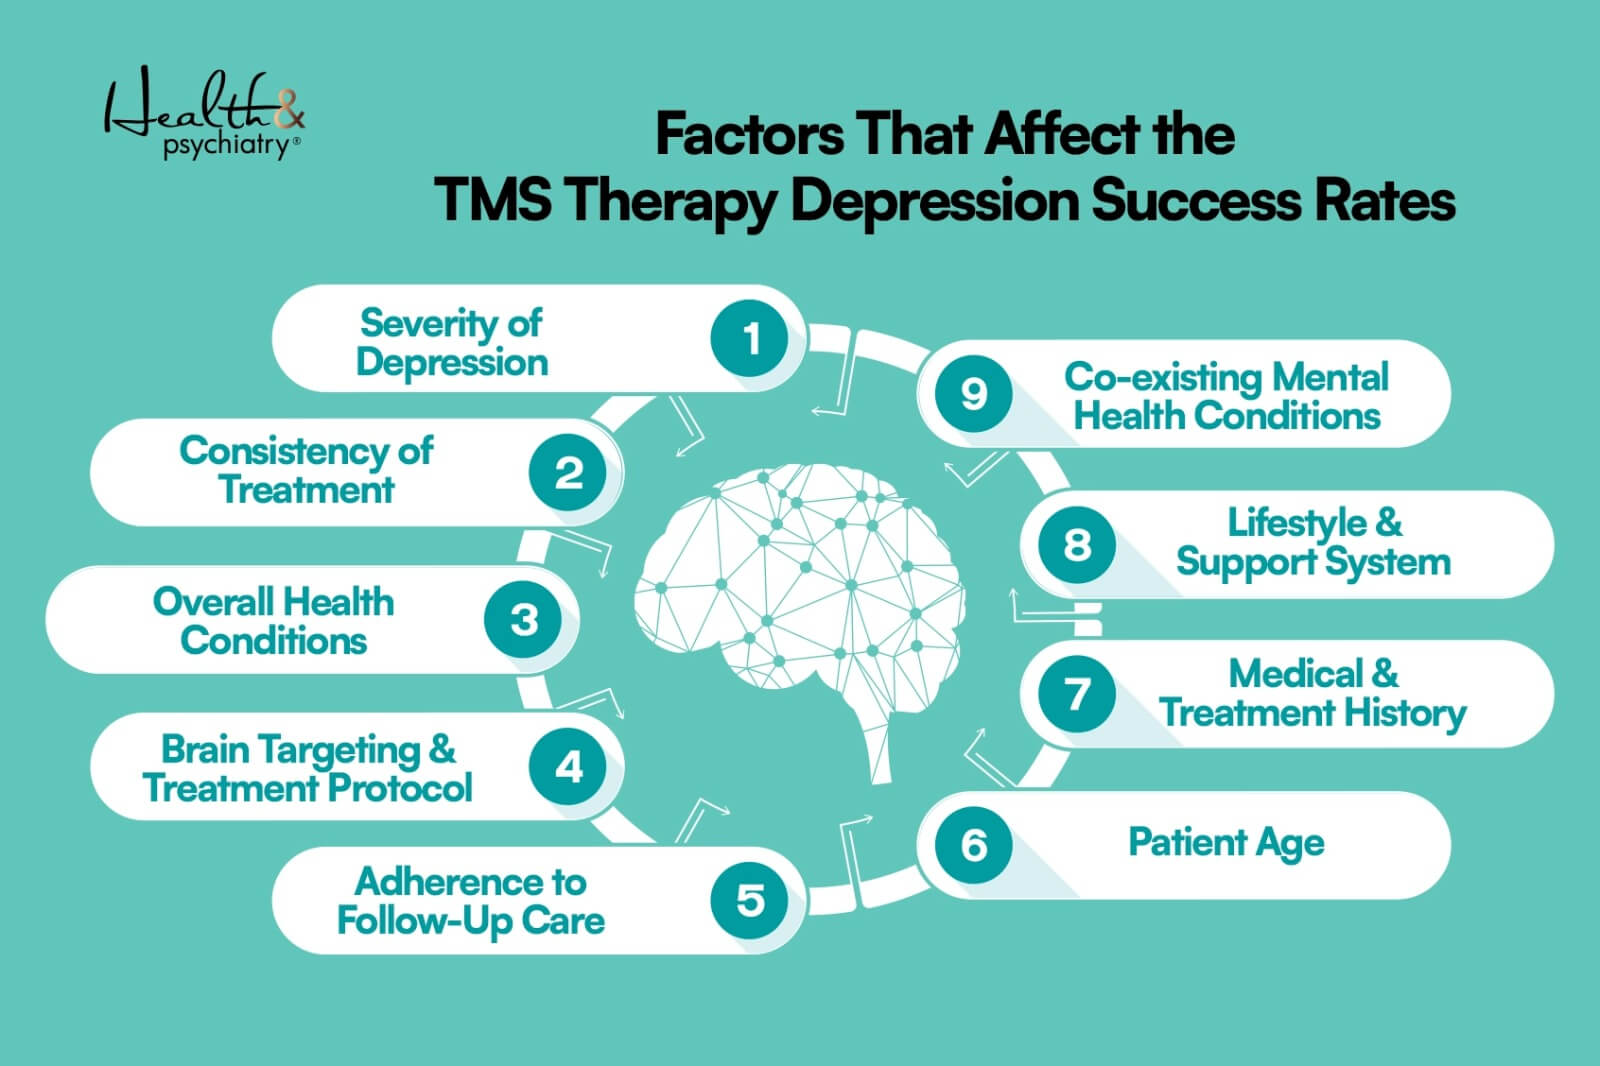
The landmark SEQUENTIAL ACUTE trial and the broader FDA clearance data consistently show response rates between 50 and 62 percent for patients who have tried at least one antidepressant without success. Remission rates hover around 30 to 35 percent. That means roughly one in three people who complete a full course of standardTheta Burst Protocol will have a clinically meaningful reduction in their PHQ-9 score, and about half will respond to the treatment at all. Here is the part nobody puts on a flyer: those numbers assume you are getting genuine theta burst stimulation at 5 Hz or intermittent Theta Burst Stimulation at 10 Hz, delivered to the left dorsolateral prefrontal cortex with proper coil positioning and adequate dosage. Miss any of those variables and your results degrade fast. I had a patient once, mid-forties, treatment-resistant to two different SSRIs and an SNRI. We ran her through standard TMS for six weeks, twenty-five sessions total, and she showed absolutely zero change. Not even a single point on the Hamilton scale. When I pulled her records and reviewed the session logs, the coil position had drifted three centimeters posterior on approximately forty percent of her treatments. The clinic was using a manual mapping method instead of neuronavigation, and the technician was not rechecking landmarks between sessions. We switched her to MRI-guided navigation, repositioned the coil to exactly the PAM50 coordinate for her individual anatomy, and within four additional sessions she began reporting sleep improvement. That is not a rare edge case. That is the difference between protocol adherence and protocol guesswork, and it accounts for a significant portion of the false-negative failures I saw in clinical practice.
The coil positioning error margin is usually two to three centimeters in manual TMS without navigation. The prefrontal cortex is not a large target. Move the coil even slightly and you are stimulating either the motor cortex, which causes jaw clenching and teeth aching, or you are hitting nothing of therapeutic relevance at all. That is why I always insist on individualized motor threshold mapping before starting the treatment course, and why I stopped accepting any clinic that does not use stereotactic or neuronavigation systems after the initial session.
Get the Full Details

The Protocol Details Most People Skip
Standard intermittent theta burst stimulation uses 50 pulses per train, repeated every 8 milliseconds, for three seconds on and seven seconds off. A typical course runs twenty to thirty sessions over four to six weeks. The total treatment time per session is about nineteen minutes, plus fifteen minutes for motor threshold testing at the beginning, which you cannot skip. Motor threshold testing determines your individual stimulation intensity. The standard prescription is 120 percent of resting motor threshold for the left DLPFC. Some clinics run at 100 percent for tolerability, but the evidence base weakens noticeably below 110 percent. I have seen response rates drop by roughly ten percentage points when clinics cut intensity to reduce headaches. The right DLPFC is sometimes used as an alternative target, particularly when patients have prominent anxiety comorbidity or cannot tolerate left-sided stimulation. The success rate for right-sided protocols is slightly lower, around 40 to 45 percent response in most studies. Deep TMS with the H-coil has somewhat different metrics. The FDA clearance data shows roughly 50 percent response, but the coil sits further from the cortical surface, which means the current density is lower and the mechanism is less well understood.
One counter-intuitive finding from the literature: patients who have previously failed antidepressant medication actually respond better to TMS than medication-naive patients. This contradicts the assumption that drug resistance means all treatment pathways are blocked. The proposed mechanism involves neuroplasticity priming, where the prior pharmacological exposure has altered receptor sensitivity in a way that makes the cortex more responsive to magnetic stimulation. I saw this pattern repeatedly in my clinic. The hardest patients to treat were the ones who had never taken any psychotropic medication at all.
When TMS Does Not Work And What To Do Instead
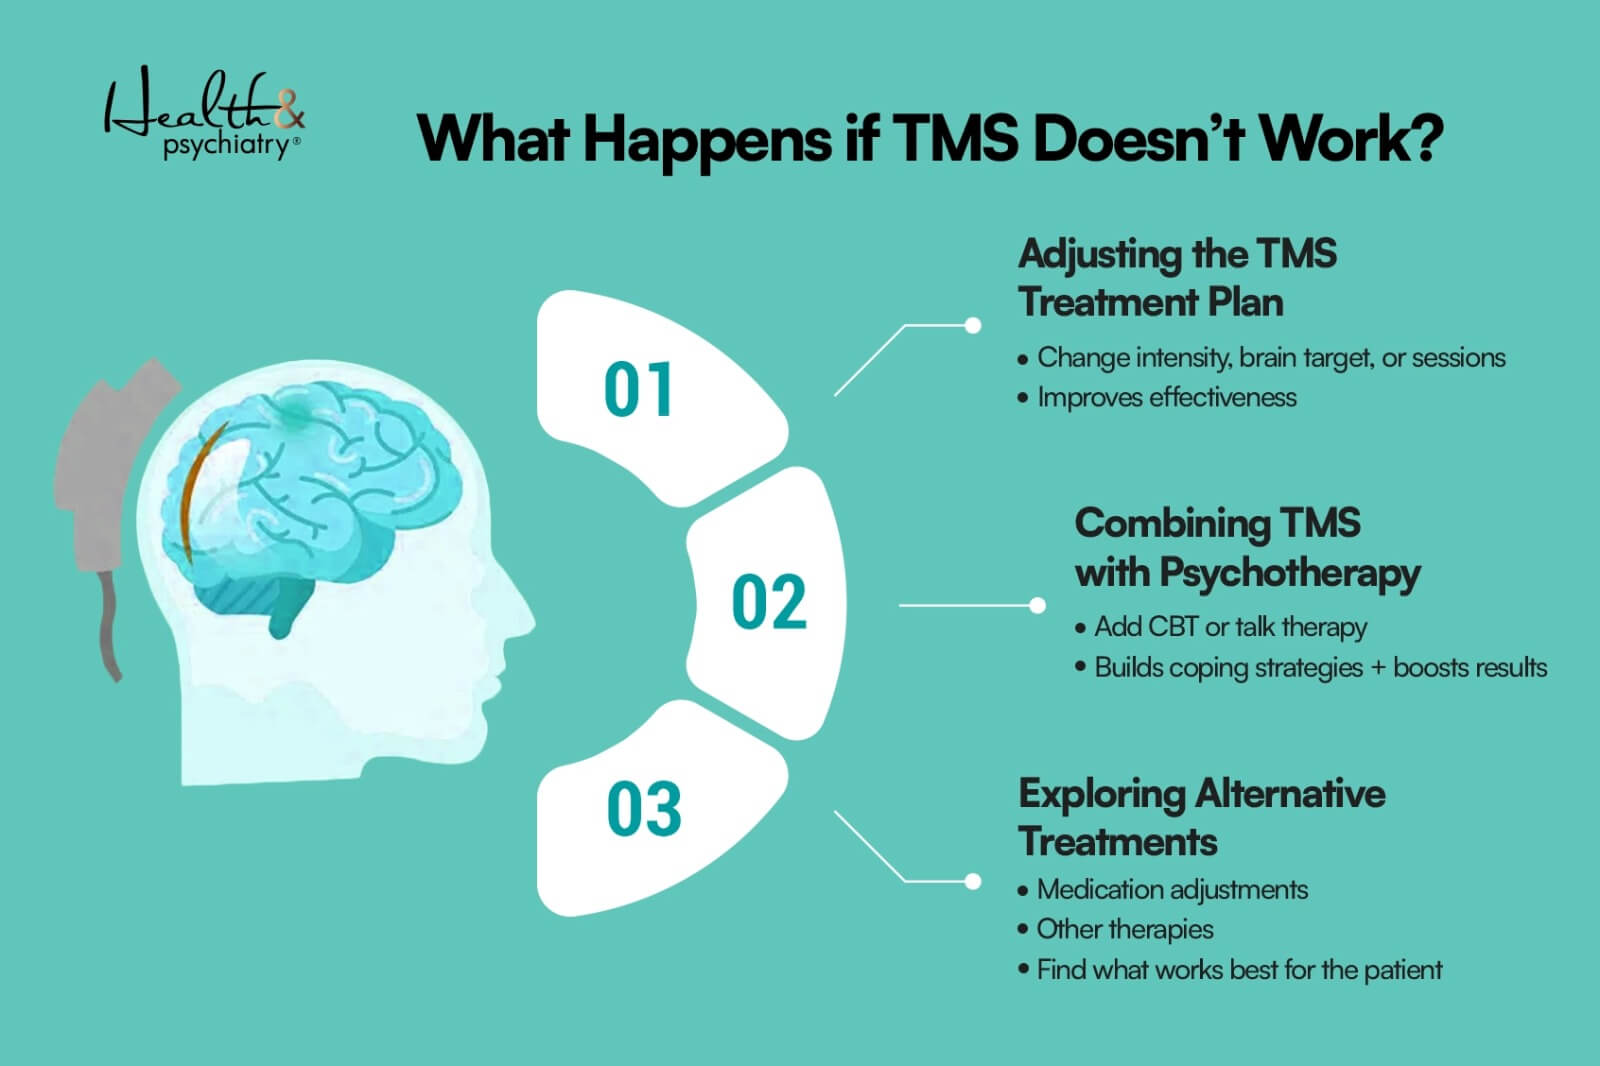
TMS fails completely in roughly 35 to 45 percent of treatment-resistant cases. The strongest predictors of non-response include: bipolar disorder rather than unipolar depression, prominent psychotic features, severe trauma-related comorbidity without mood stabilization, and structural brain lesions in the stimulation target region. If you have tried TMS at adequate dosage and it failed, switching to the contralateral hemisphere or using ECT is the standard next step. Ketamine infusion therapy shows comparable or superior response rates for acute treatment-resistant depression, usually within hours rather than weeks. The downside is the dissociative side effects and the cost access barrier. Intranasal esketamine has FDA approval and insurance coverage in most plans, but it requires clinic administration and monitoring for at least two hours post-dose. Augmentation with lithium or thyroid hormone (T3) remains effective for patients who partially respond to TMS but do not reach remission. I typically add T3 at 25 micrograms daily and titrate based on free T4 levels. About a third of partial responders convert to full remission with this combination.
Practical Logistics Before You Commit
You need a minimum of four to six weeks of commitment to know if TMS is working for you. Do not stop after twelve sessions because you feel no change. The cumulative dose matters more than the acute effect. Most patients report initial side effects like scalp discomfort, forehead tension, or mild headache during the first week. These usually resolve by session ten. Hearing protection is mandatory because the coil clicking is genuinely loud, around 100 decibels at the ear. Seizure risk is extremely low, estimated at one in thirty thousand to one in fifty thousand sessions, but it is real. The main contraindications are metallic implants in the head, history of seizures, and certain aneurysm clips. Bring your full medical history and medication list to the initial consultation. Do not skip the neurological screening. If you are considering this treatment, verify that the clinic uses neuronavigation or at minimum the 5 centimeter rule for coil positioning, tracks motor threshold individually, and has a psychiatrist overseeing the protocol. The difference between a properly run TMS program and a walk-in clinic version is the difference between the 60 percent success rate and the 30 percent you will see if the protocol is loose.
I still see patients who were abandoned by TMS after a single inadequate trial and written off as treatment-resistant for life. Most of them would have responded if the protocol had been done correctly from session one.