Why TMS Therapy Gets Bad Reviews (And What People Are Actually Complaining About)
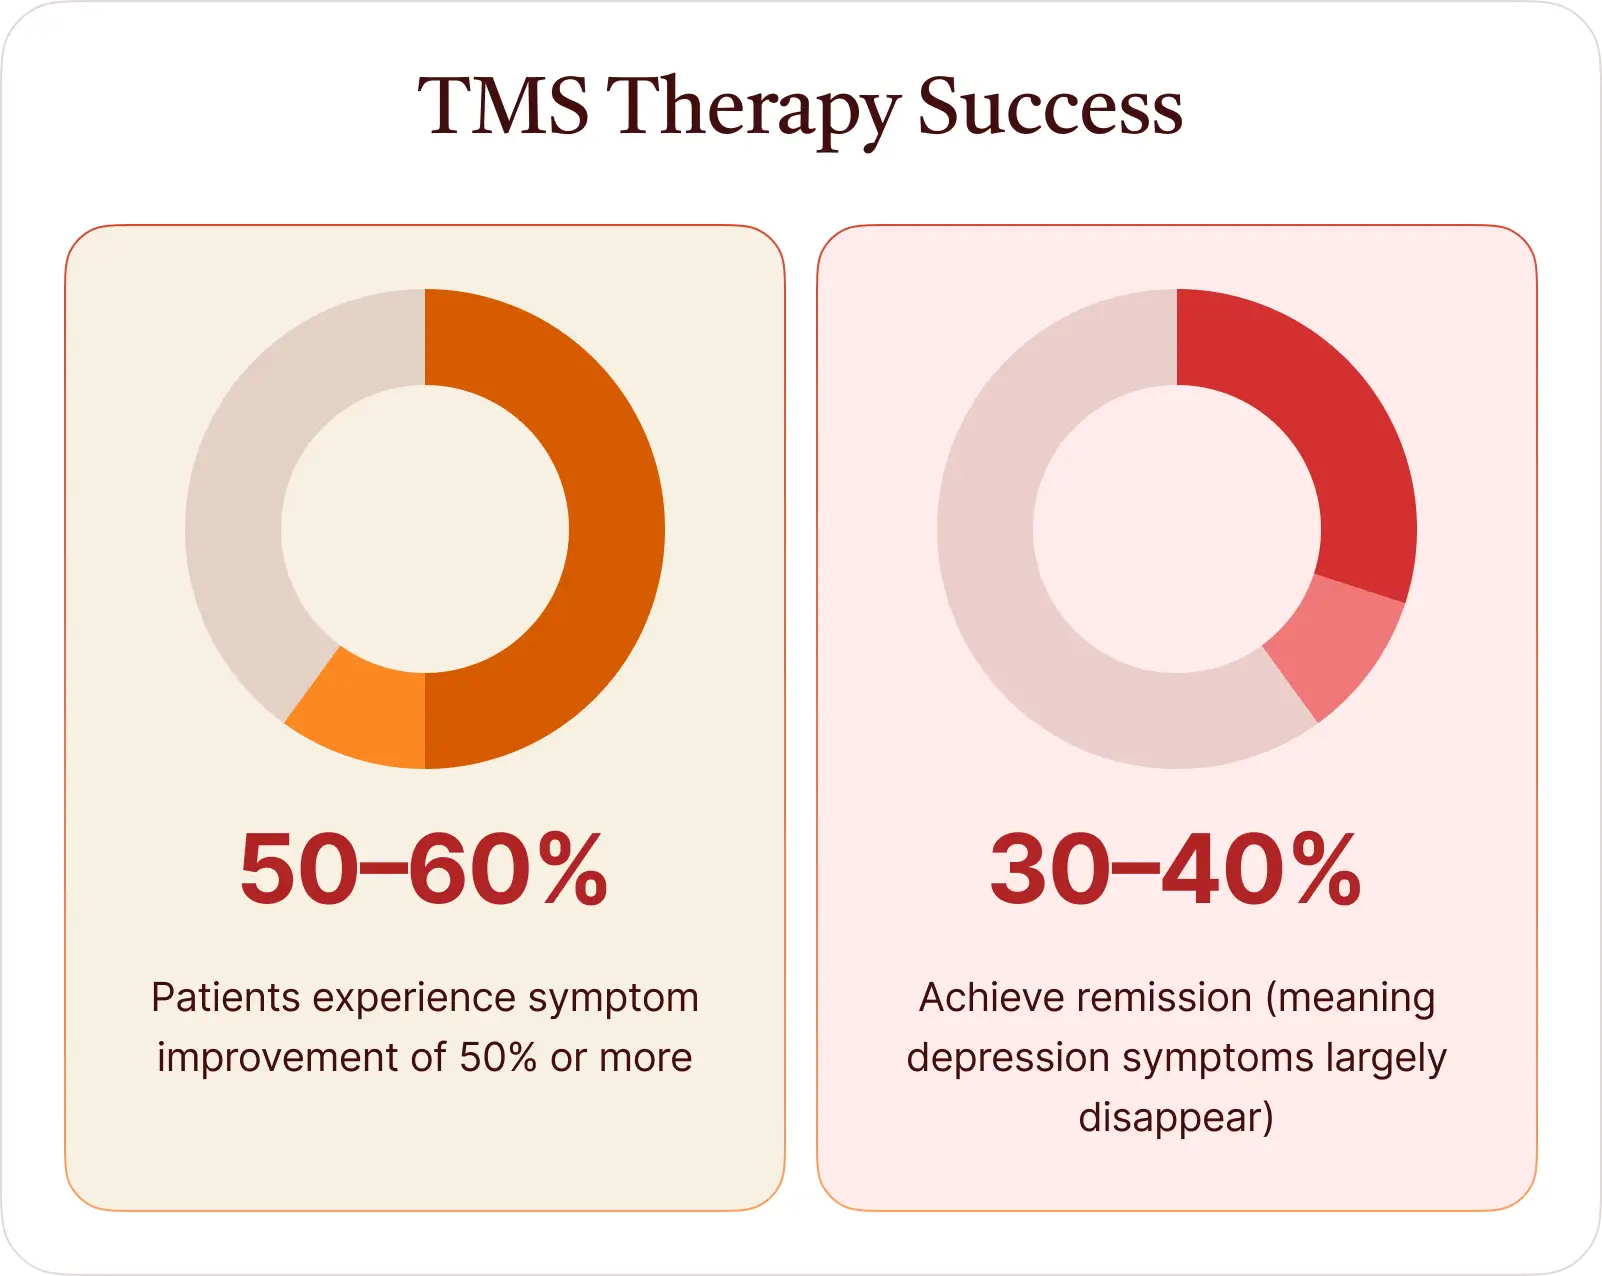
TMS therapy negative reviews are everywhere if you know where to look, and most of them come from the same handful of issues that show up repeatedly. I spent several years working with neuromodulation clinics before moving into a different role, and I've seen patients come in furious after someone else's TMS experience made them doubt it entirely. The problem isn't that TMS doesn't work - it's that people go in with zero context about what realistic outcomes actually look like. The standard TMS protocol for depression is 36 sessions over six weeks, 10 Hz stimulation at the left dorsolateral prefrontal cortex. That's the FDA-cleared protocol, the one most clinics use. But here's what the brochure won't tell you: response rates hover around 60 percent for that protocol. About a third of people don't get meaningful relief. And then there's the non-responder group who somehow improve anyway, which happens frequently enough that researchers still argue about why.
Tms Therapy Negative Reviews
The headache complaint is the single most common grievance, and it's almost always a technical issue rather than a flaw in the therapy itself. The coil needs to be positioned at the correct motor threshold, usually around 110 percent of the resting motor threshold for standard protocols. When technicians rush the mapping process or skip the motor threshold calculation entirely, patients get treated too hot or too cold, and headaches become nearly guaranteed. I had a patient once who came in after three failed TMS courses. Each clinic had different protocols, different intensities, different coil types. We mapped her properly, found her motor threshold was unusually high at 130 percent, and adjusted accordingly. She finished her sixth week with zero headaches and a PHQ-9 drop from 18 to 7. The auditory side effects get less attention than they deserve. The clicking sound from the magnetic pulse can reach 100 decibels or more at the coil site. Most clinics provide earplugs, but foam plugs aren't the same as the custom-molded options some places offer. A lot of people skip the hearing protection because they feel silly wearing earplugs during a 20-minute session. They regret it later. Tinnitus from TMS is rare but well-documented, and it tends to show up in people who didn't use proper ear protection across a full protocol course. Here's something most reviewers don't consider: TMS doesn't work the same way for everyone, and the timing of your treatment relative to other medications matters more than people realize. SSRIs can actually blunt the response to TMS in some cases. I've seen this repeatedly with patients on high-dose sertraline or escitalopram who show minimal improvement during their first course. Switching to a different medication class or tapering the SSRI under their prescriber's guidance before starting TMS often makes the difference between a non-response and a solid response. Clinics rarely mention this upfront because it requires coordination between the psychiatrist and the TMS provider, and that coordination is something most standalone TMS centers aren't set up to handle well.
Deep TMS versus traditional TMS is another source of confusion that fuels negative reviews. The older H-coil deep TMS devices reach further into the brain but have less focused stimulation. The newer figures-of-eight coils used in standard TMS target more precisely but don't penetrate as deeply. Some conditions like OCD or nicotine addiction seem to respond better to deep TMS, while treatment-resistant depression has stronger evidence for the focused coil approach. Patients reading reviews often compare experiences across different device types and conclude the therapy itself is inconsistent, when really they're comparing two different technologies for different conditions. Insurance coverage is another landmine. Most plans require documented failure of at least two antidepressant trials before approving TMS. People who find out about this requirement mid-treatment often feel blindsided, especially when they've already completed several sessions without knowing coverage might get denied retroactively. I've watched patients abandon otherwise reasonable treatment plans because the administrative side of TMS caught them off guard. Check your coverage in writing before your first session. Not a phone call, not a chatbot - a written confirmation from the insurance company. Session logistics are surprisingly punishing for some people. You're lying still for 20 to 40 minutes per session, fully clothed, with a metal coil pressed against your scalp. For people with claustrophobia, mobility issues, or severe anxiety about medical procedures, this is genuinely difficult. Some clinics offer more comfortable positioning options or shorter protocols, but the standard setup doesn't accommodate everyone. The fatigue that follows sessions is real too, especially in the first two weeks, and people who work full-time often need to schedule morning sessions to minimize disruption.
Get the Full Details

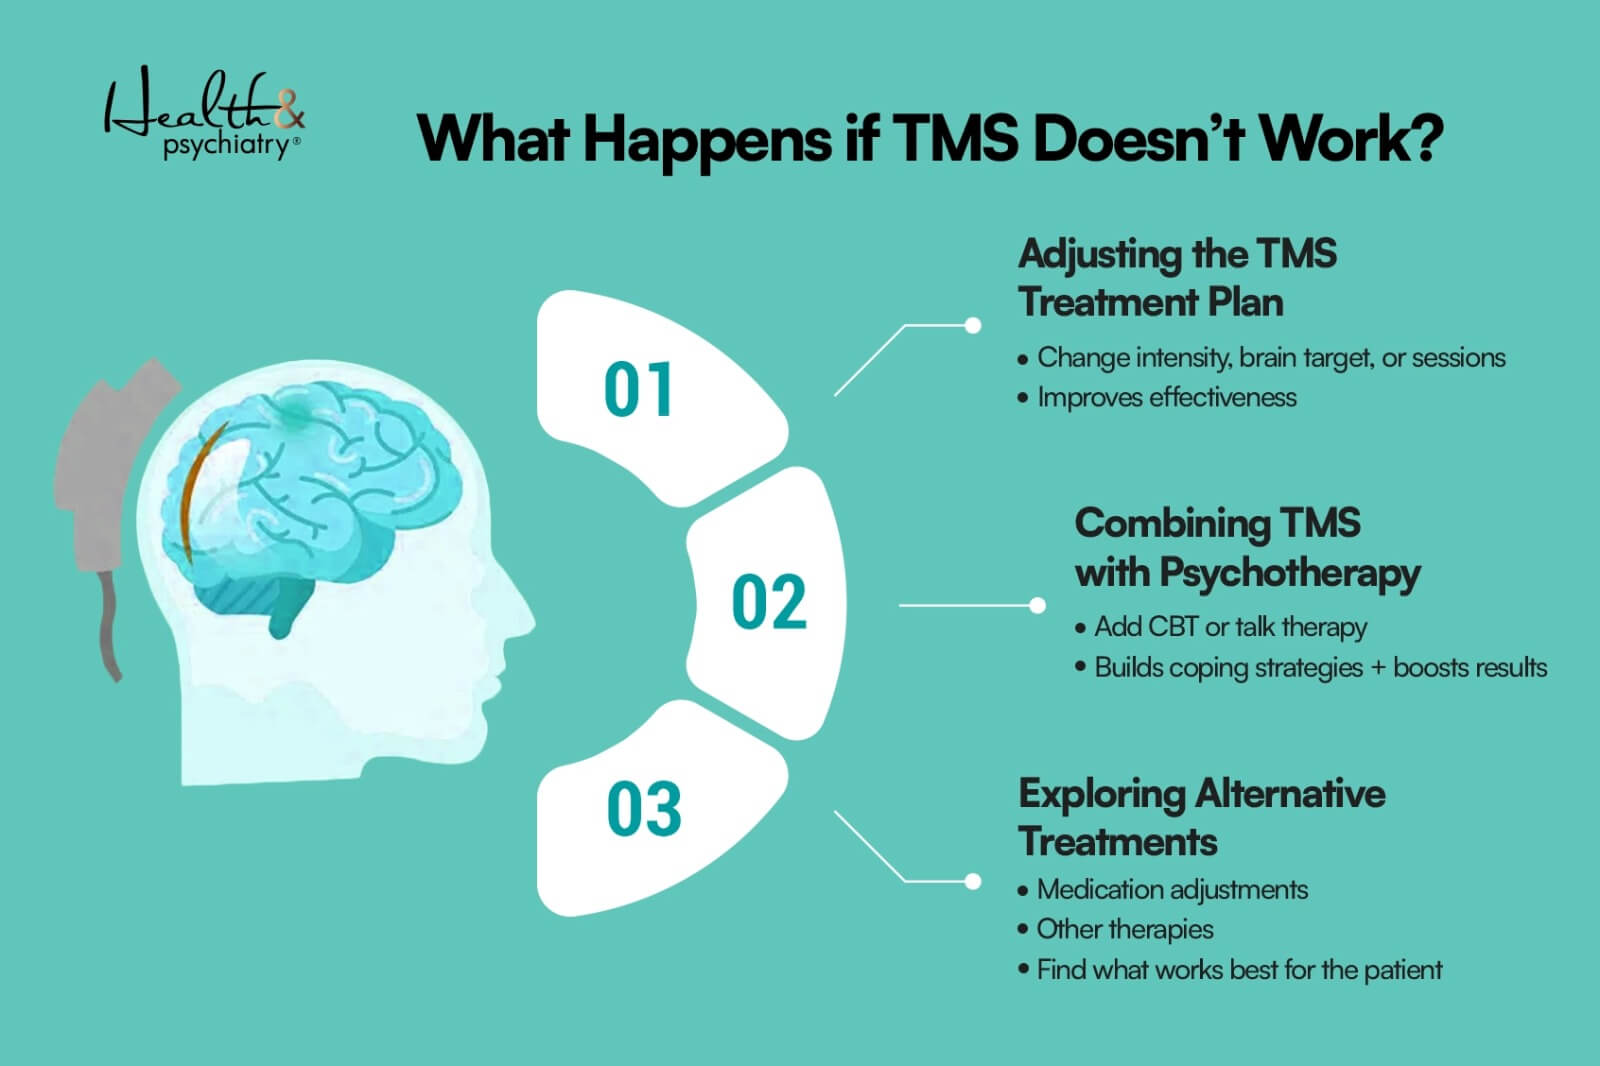
If TMS isn't working after 20 sessions with proper technique, switching protocols sometimes helps. There's emerging evidence that theta burst stimulation - three pulses per burst at 50 Hz, repeated in trains - can achieve similar results in fewer sessions for some patients. It's not universally better, but it's worth asking about if your standard protocol is showing minimal progress by the midpoint. Some clinics have the equipment, some don't. The bottom line is that TMS works well for the right patient with the right protocol and the right expectations. The negative reviews mostly come from mismatched expectations, technical errors during treatment, or people who weren't good candidates in the first place. If you're considering it, go in knowing that a third of people won't respond to the first protocol they try, that headaches and fatigue are normal early side effects that usually fade, and that communication with your prescribing psychiatrist about medication timing is something you should initiate yourself rather than waiting for the clinic to remind you.