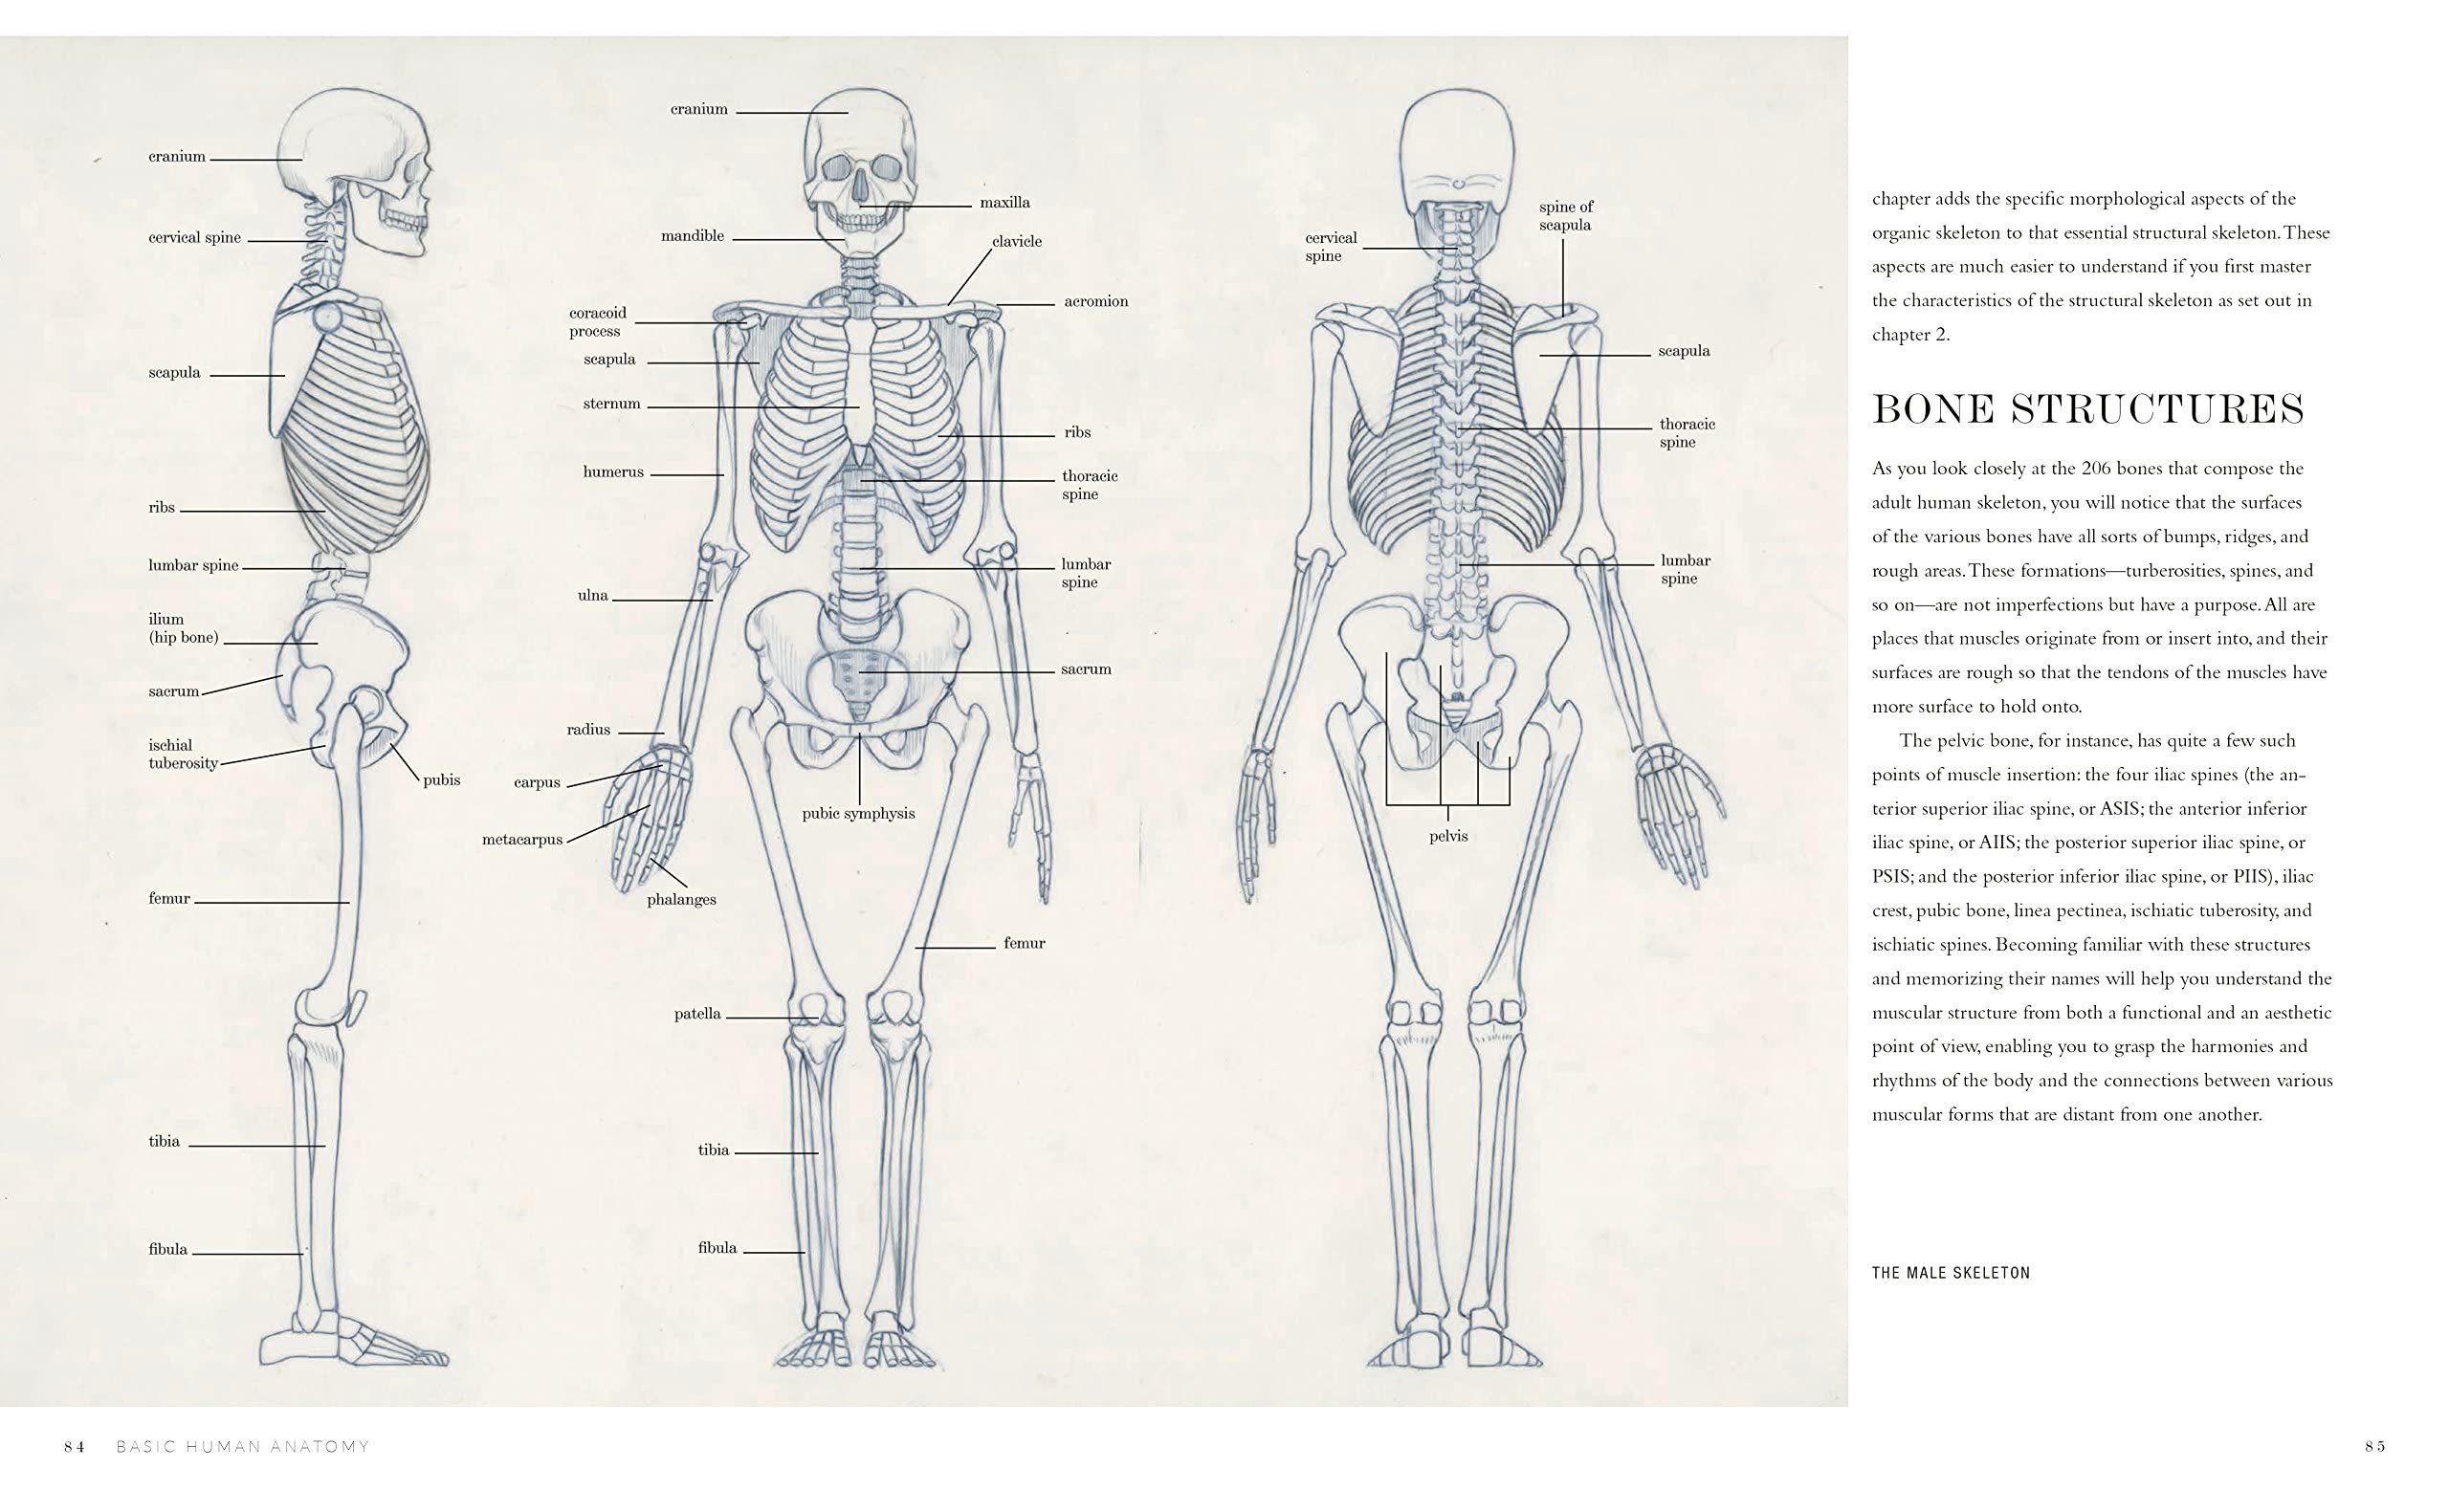
Learning anatomy properly is mostly about spatial relationships, not memorizing lists.
Most beginners start by trying to memorize every structure they read about. It does not work for long. The brain discards information it cannot locate in a three-dimensional framework. The better approach is building mental models first, then attaching names to places you already understand. A Top 10 Anatomy For Beginners list will always be a starting point, not a destination. Here is what I actually recommend beginning with. This order matters because each system builds on the one before it. 1. Axial skeleton — skull, vertebral column, rib cage. This is your central framework. Learn the major landmarks: foramen magnum, spinous processes, sternal angle. If you skip this, everything else floats without reference points.
2. Appendicular skeleton — pectoral girdle, upper limb, pelvic girdle, lower limb. Focus on articulations first. The shoulder joint and hip joint are fundamentally different in stability and range. Understand why before naming bones. 3. Muscular system overview — start with muscle compartments of the limbs and the major muscle groups of the trunk. Learn origin and insertion as directional relationships, not just points. A muscle does not just "attach here and there." It crosses a joint to produce a specific movement. 4. Nervous system: gross anatomy — brain, spinal cord, major peripheral nerves. Do not get lost in nuclei tracts yet. Learn the brachial plexus, lumbosacral plexus, and dermatomes. These are the structures that actually matter clinically.
5. Cardiovascular system: heart and great vessels — chambers, valves, coronary circulation, venous return. You need to understand flow paths before you can understand pathologies. Trace blood from the vena cava through to the aorta without looking at a diagram. If you cannot do that smoothly, you do not know the anatomy yet. 6. Cardiovascular system: major arteries and veins of the limbs and trunk — arterial supply follows logical patterns. The subclavian becomes axillary becomes brachial. The femoral becomes popliteal. Learning these transitions reduces the volume of material you need to memorize by roughly half. 7. Respiratory system — larynx, trachea, bronchi, lungs, pleura. The bronchopulmonary segments are where most beginners get stuck. They matter for localized pathology and imaging interpretation.
Get the Full Details

8. Digestive system: abdominal organs and peritoneum — this is one of the most confusing topics for students. The peritoneum is not a single sac. It is a series of reflections, mesenteries, and ligaments that create potential spaces. Learning it as a flat diagram rather than a 3D arrangement guarantees confusion later. 9. Urinary and reproductive systems — kidneys, ureters, bladder, and the pelvic organs. Keep the retroperitoneal structures separate from the intraperitoneal ones. That distinction explains so much about surgical access and spread of disease. 10. Neuroanatomy: internal structures — ventricles, brainstem cross-sections, basal ganglia, thalamus. This is the hardest section. It requires solid foundations from everything above it. Do not rush into this until the previous nine areas feel routine.
The actual method that works
Study anatomy in cycles. First pass: orient yourself. Look at a whole-structure image, identify the boundaries, understand what it does functionally. Second pass: label everything. Third pass: relate it to adjacent structures. Fourth pass: test yourself without any references. Active recall beats passive reading every time. Close the book and redraw the brachial plexus from memory. Draw it badly. The act of producing the diagram, even imperfectly, creates stronger memory traces than re-reading a textbook page ten times. I have seen students who spent three hours highlighting notes fail a practical exam, while another student who spent one hour drawing structures from memory passed easily. Use 3D atlases. Complete Anatomy, Visible Body, or even free options like BioDigital Human give you spatial context that cadaver images and textbook diagrams cannot replicate. Textbook illustrations are two-dimensional abstractions. Real anatomy is layered, overlapping, variable. A structure you think you know from a diagram often looks completely different when rotated in three dimensions.
Cadaver lab or prosection images are non-negotiable at some point. There is a gap between idealized illustrations and real tissue that no amount of studying aatlas will close. Fresh cadavers are yellowed and stiff in many teaching collections. Expect color variations. Expect asymmetry. Expect anatomical variants that your textbook did not mention. Do not panic when you find something "not in the book." That is normal. Variation rates in real populations are high.

A specific problem I ran into and how I fixed it
When I was working through nerve anatomy, I kept confusing the branches of the median nerve in the hand. Textbooks show a clean, idealized pattern. Real dissections and clinical cases do not follow that pattern consistently. I was unable to localize a sensory deficit after a wrist laceration because my mental map was too simplified. The workaround was to stop treating the median nerve as a single trunk and start thinking about it as three distinct digital branches with their own territories. I drew the palmar cutaneous branch separately from the proper palmar digital branches. I traced each branch to its exact skin supply. Once I shifted from a tree diagram to a territory map, everything clicked. Clinical localization became straightforward. This is a pattern that repeats throughout anatomy. Named structures on a chart are not the same as functional territories in a living body.
Counter-intuitive things beginners miss
Memorizing Latin names without understanding etymology or function is largely wasted effort. The name often describes what the structure does or where it is. "Brachioradialis" tells you it is in the forearm and acts on the elbow. "Flexor digitorum superficialis" tells you it flexes fingers and sits above the deeper flexors. Learning the roots saves you from treating every term as arbitrary. Another thing: relationships matter more than definitions. Knowing what the pancreas sits against is more useful than knowing every cell type in the islets of Langerhans at the beginner stage. The pancreas lies anterior to the superior mesenteric vessels, the left kidney, and the splenic vein. That spatial information tells you more about surgical risk and spread of disease than a histology table does. Imaging literacy should start early. Cross-sectional anatomy is the language of clinical practice. A CT scan does not look like a textbook illustration. Learning to navigate axial, coronal, and sagittal planes alongside gross anatomy compresses the time gap between classroom learning and clinical application significantly. Most programs introduce imaging in the second year or later. Starting earlier gives you a substantial advantage.
What does not work and why you should avoid it
Flashcard-only study fails for anatomy because cards are designed for discrete facts. Anatomy is relational. A card that says "sternocleidomastoid: rotates head to opposite side" does not teach you why, how, or what happens when it is damaged. You can memorize the fact and still be unable to identify the muscle on a specimen or interpret a clinical presentation. Reading textbooks passively is equally ineffective. Highlighting is not studying. Re-reading is not learning. Both create a false sense of familiarity. You recognize the text when you see it again and mistake recognition for retention. Testing yourself without the book in front of you is the only reliable way to know what you actually know. Watching videos without pausing to draw or label is mostly entertainment. The passive consumption loop feels productive because information is flowing, but retention without active engagement is very low. Ten minutes of drawing and labeling beats an hour of unpaused video watching.

Honest limitations of this approach
Spatial modeling and active recall are efficient, but they require time upfront. The first pass through any new region will feel slow. You might spend forty-five minutes on the brachial plexus and still feel uncertain. That is normal. The alternative—cramming facts the night before an exam—feels faster initially but collapses under practical testing conditions where you need to identify structures on a real specimen or interpret an image. This method also assumes access to good visual resources. If you are studying from a single outdated textbook with black-and-white line drawings, your spatial understanding will have a hard ceiling. Even free 3D atlas apps and YouTube dissection channels provide enough visual material to make this approach viable. The barrier is usually availability, not cost. There is no shortcut through neuroanatomy. The brain and spinal cord demand repetitive exposure. Even experienced clinicians and anatomists keep coming back to cross-sections of the brainstem. Accept that some regions require more cycles than others. The muscular and skeletal systems usually stabilize faster. Visceral anatomy, especially the abdomen and pelvis, tends to resist memorization longer because of the density of overlapping relationships.
Practical resource guidance
Gray's Anatomy for Students is the standard introductory text. It is thorough without being overwhelming. Clinically Oriented Anatomy by Moore is denser but has better clinical correlations if you want that connection early. Netter's Atlas remains the gold standard for illustrations. If you use Netter, draw over the images yourself. Tracing alone is not active enough. For 3D visualization, Complete Anatomy is expensive but comprehensive. Elsevier's Complete Anatomy offers layer-by-layer dissection with clinical annotations. Free alternatives exist. Kenhub has a free tier that covers enough for beginners. YouTube channels like The Noted Anatomist and Sam Webster provide dissection walkthroughs that are genuinely useful when you need to see how structures look in real tissue rather than in idealized illustrations. Anki decks exist for anatomy and can supplement your study, but they should not be your primary tool. They are best used for quick recall of classifications, foramina, and named relationships after you have already built the spatial foundation through drawing and labeling. Using Anki as a first exposure method leaves you with facts you cannot locate in three dimensions.
The whole process from zero to competent in basic human anatomy usually takes between six and twelve months of consistent study, depending on your schedule and prior exposure. A dedicated medical student covering all systems intensively might compress that to three or four months. If you are studying part-time alongside other commitments, expect the longer end of that range. Consistency matters more than intensity. Forty minutes a day beats five hours on Saturday when you have been avoiding the subject all week.