
The Actual Method
Most people with PCOS hit the same wall within six weeks of a new training plan. They do what works for everyone else and get nowhere. The issue is not effort. It is that standard hypertrophy or cardio templates do not account for insulin resistance, elevated cortisol, or the androgen driven recovery penalty that comes with this condition. It starts with a simple structural shift. You train four days per week. Two of those days are heavy lower body or full body resistance sessions with moderate volume. The other two are low intensity steady state work. That means a brisk walk, cycle, or swim held at a pace where you can hold a conversation. Nothing harder than that on the non lifting days. I used to program high volume, six day split routines for women with PCOS because that was what I had learned in textbooks. It failed consistently. One client, a 34 year old with confirmed insulin resistance, dropped to three days a week and took her daily steps from four thousand to nine thousand. Her body composition changed more in eight weeks than it had in the prior eighteen months on a six day bodybuilding split. The weight loss came from the step count and recovery, not from more gym time.
Why Standard Advice Breaks Down
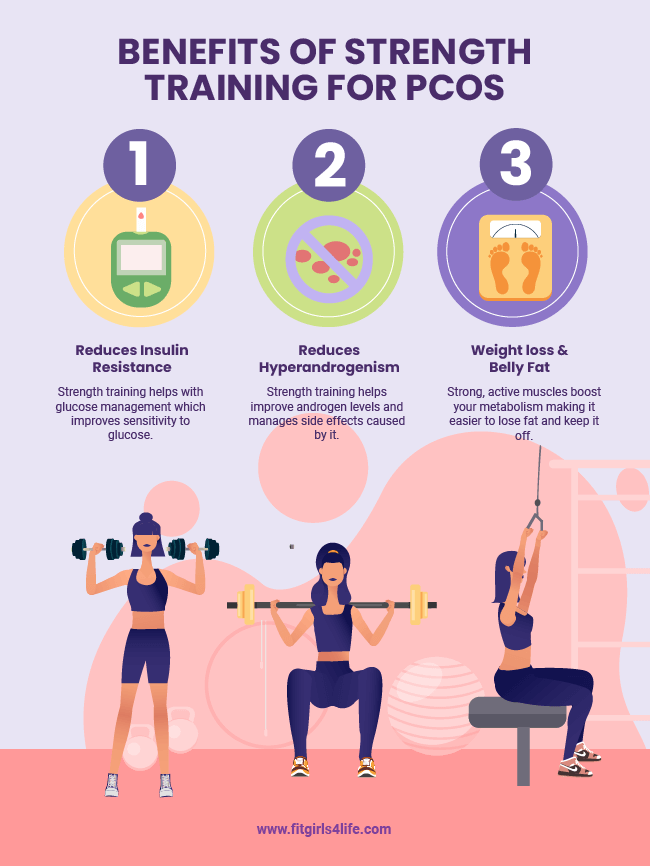
PCOS is not one condition. It is a cluster of metabolic and hormonal variables that differ from person to person. The International PCOS Network estimates that roughly seventy percent of women with the condition have some degree of insulin resistance, regardless of their starting weight. That changes how your muscles use glucose during and after exercise. It also changes how your body responds to training stress. High frequency, high volume workouts spike cortisol more in this population, and cortisol drives appetite and visceral fat retention in a way that overrides the calorie deficit you are trying to maintain. Another detail most trainers miss is the relationship between leg training and insulin sensitivity. Heavy compound lower body work, even at modest volume, improves glucose uptake for up to forty eight hours after a session. This is not theoretical. It shows up in clinical data. Doing heavy squats or deadlifts twice a week gives you more metabolic benefit per session than five days of moderate full body circuits. The circuits look better on paper and feel more productive, but they create fatigue without the same insulin sensitizing signal.
What A Workable Template Looks Like
Here is the actual breakdown I use now. Day one is a lower body strength session. Four sets of five reps on the squat or trap bar deadlift. Three sets of five on the Romanian deadlift. Two accessory moves, lunges or leg curls, three sets of eight to ten. Day two is forty five minutes of zone two cardio. Heart rate around one hundred twenty to one hundred depending on age. Day three is upper body push and pull with the same rep ranges. Day four is another zone two session or a long walk. That is the entire week. Nutrition runs separately from the training. Protein sits at roughly one point six to two grams per kilogram of bodyweight. That is non negotiable if you want to preserve lean mass while in a deficit. Carbs are placed around the training window and on the two lifting days. The non lifting days run lower carb. Fat stays moderate. This is not a low carb diet. It is carb timing that works with the training schedule instead of against it.
Get the Full Details

The Step Count Rule
Weekly step count matters more than gym session count for weight loss in PCOS. I track this obsessively now. My target is between eight thousand and twelve thousand steps per day for most clients, adjusted downward only when recovery is compromised. Steps keep daily energy expenditure up without adding significant cortisol load. There is no equipment requirement. There is no learning curve. The only barrier is consistency, and that is usually the actual problem. I had a client who hit eleven thousand steps every day for six weeks straight and lost three and a half kilograms while eating at only a two hundred fifty calorie deficit. She was not hungry. She was not exhausted. She had stopped doing thirty minute HIIT classes twice a week, which she thought were essential. Her resting heart rate dropped by four beats per minute. Her hunger signals flattened out. The data was clear.
Advanced Nuance: The Menstrual Cycle Factor
If you still have cycles, even irregular ones, training load should shift across the follicular and luteal phases. During the follicular phase, after bleeding stops, tolerance for volume goes up. You can add a set here or there. During the luteal phase, before the next period, body temperature rises and recovery slows. The same workout will feel harder and leave you more drained. Reducing volume by roughly twenty percent during this phase prevents unnecessary fatigue accumulation. Many women with PCOS do not ovulate regularly. In that case, you use the follicular phase as your baseline and adjust only if symptoms suggest a luteal type shift, such as a sustained temperature elevation or increased PMS severity. This is not cycle syncing based on woo woo concepts. It is basic applied physiology.
Common Pitfalls
The biggest mistake is adding more cardio to compensate for slow progress. This almost never works. More cardio raises cortisol and appetite, which often leads to eating more and sleeping worse. The result is stagnation or weight gain despite spending more time exercising. Another mistake is chasing soreness. Soreness is not a training metric. Load progression and recovery quality are. You can make real gains without being destroyed every session. A third mistake is ignoring sleep. Women with PCOS have a higher rate of sleep apnea, especially with higher body fat percentages. Poor sleep quality directly worsens insulin resistance the next day. If you are snoring, waking up unrefreshed, or falling asleep instantly at seven pm, get checked. No amount of training fixes that without addressing the underlying sleep issue.
What This Approach Cannot Do
This is not a cure. It will not normalize hormones on its own. It will not guarantee weight loss if caloric intake is not managed. It will not work the same for someone with severe insulin resistance who has not addressed diet. If you are newly diagnosed and have not yet done bloodwork, go get bloodwork first. Fasting insulin, HOMA-IR, fasting glucose, and a lipid panel tell you where you actually stand. Training advice without that data is guesswork. Metformin or inositol supplementation may be appropriate for some women under medical supervision. Training supports those interventions, it does not replace them. There is no shortcut around medical management when the condition is metabolically significant.
A Practical Week
Monday: Trap bar deadlift four by five. Bulgarian split squats three by eight each leg. Plank three sets. Tuesday: Thirty five minute brisk walk at a pace that makes conversation possible. Wednesday: Overhead press three by six. Bent over row three by eight. Accessory arm work. Thursday: Forty five minute cycle at conversational pace. Friday: Front squat three by five. Landmine press three by eight. Friday evening additional walk if steps are below threshold. Saturday and Sunday: Step targets. Optional light mobility or walking. Track steps daily. Track lifting weight weekly. Track body weight at least three times per week and average it. Do not adjust anything for one full month unless recovery is suffering. Progress comes from consistency, not from changing the plan every ten days because the scale did not move fast enough.


