Why Most Pregnancy Training Programs Miss the Mark
I spent three years consulting for a prenatal fitness platform and ended up leaving because they kept pushing the same recycled routines that were designed in a vacuum, not on actual pregnant bodies. A proper Training Program For Pregnancy needs to account for physiological shifts that happen between the first and fourth month alone, and most commercial programs barely scratch the surface of that. Core principles matter more than specific exercises. The fundamental shift during pregnancy is the release of relaxin, a hormone that softens ligaments across the entire pelvic girdle and beyond. This means joint stability degrades noticeably after week twelve, and exercises that were safe in month one can become risky by month three if you aren't adjusting load and range of motion. I've watched people tear sacroiliac ligaments doing what they considered "light squats" because nobody told them their connective tissue was essentially underwater at that point. The most effective programs I've seen structure training around four phases rather than trimesters, because trimesters are arbitrary calendar divisions while hormonal impact is continuous and individual. Phase one runs roughly weeks one through ten, where intensity can remain near pre-pregnancy levels for someone who was already training consistently. Phase two covers weeks eleven through twenty, when cardiovascular strain increases due to expanded blood volume and the center of gravity begins shifting. Phase three spans weeks twenty-one through thirty-two, requiring significant modification of any exercise involving supine positioning or high impact. Phase four, from week thirty-three onward, focuses almost entirely on maintaining mobility and preparing the pelvis for delivery rather than building capacity.
Common Pitfalls That Cost People Progress
One issue that comes up constantly is the breathing pattern. Pregnant clients tend to hold their breath during exertion, which spikes intra-abdominal pressure and puts stress on the already compromised linea alba. I had a client at week twenty-six who was doing modified deadlifts and developed noticeable diastasis awareness after six weeks of training. The fix wasn't stopping exercise — it was teaching her to exhale throughout the concentric phase and maintain a 30 percent lower load than she was using pre-pregnancy. She returned to near-baseline strength by week thirty-four without worsening the separation. Another mistake I see repeatedly is programming based on perceived exertion alone. The modified Borg scale works differently when your resting heart rate is already elevated by fifteen to twenty beats per minute. What feels like moderate effort at week eight can register as vigorous by week twenty-four because the same absolute workload now requires significantly more cardiac output. I switched my recommendations to using rate of perceived exertion alongside a stricter heart rate ceiling of no more than 140 beats per minute for anyone in their second or third trimester, and the compliance was better because it removed the ambiguity.
Exercise Selection That Actually Holds Up
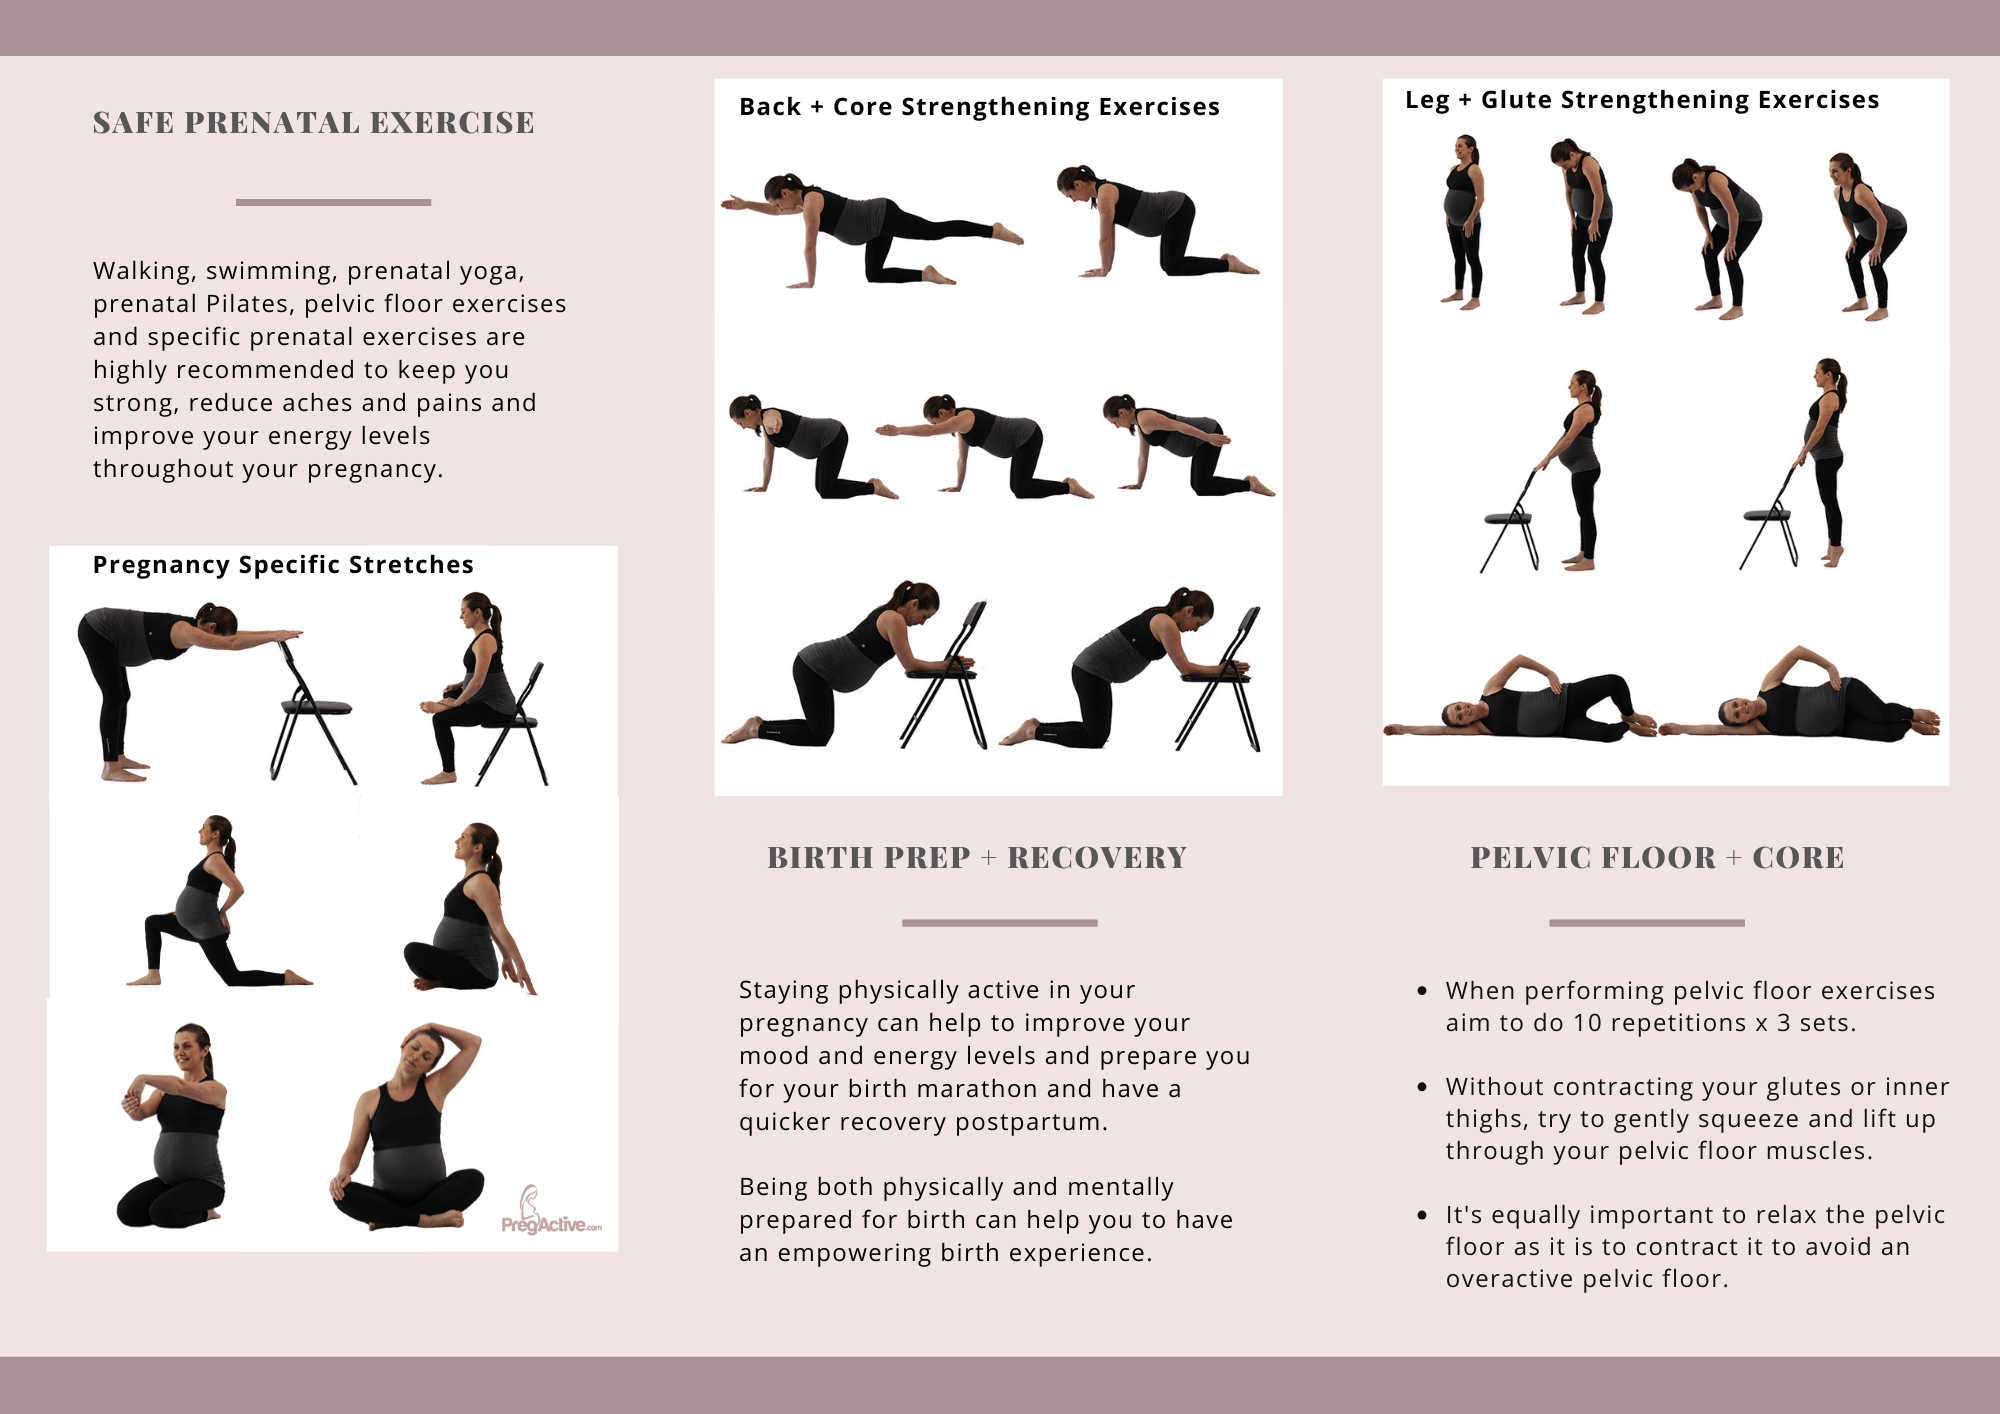
Weight training during pregnancy is not only safe but beneficial when programmed correctly. The evidence base supports resistance work at sixty to seventy-five percent of pre-pregnancy one-rep maximum through most of the second trimester, dropping to fifty to sixty-five percent as balance becomes a factor. Compound movements like goblet squats, hip hinges, and seated rows remain appropriate with modification. Overhead pressing should be approached cautiously after week twenty due to the postural changes from lumbar lordosis increasing; I had a client who complained of shoulder impingement symptoms that resolved simply by switching from barbell overhead press to landmine press, which altered the plane of motion just enough. Cardiovascular training follows a similar logic. Low-impact modalities — cycling, swimming, elliptical — carry the lowest risk profile across all phases. Running can continue if the person was a runner before pregnancy, but most programs I've reviewed don't account for the fact that foot arch collapse during pregnancy changes running biomechanics enough to cause knee and hip compensation patterns. I've seen former marathon runners develop patellofemoral pain syndrome around week twenty-eight simply because their training didn't adapt for the new structural alignment. Pelvic floor work is where most programs fail hardest. There's a persistent myth that Kegels alone solve everything, but the reality is that pelvic floor training during pregnancy needs to include both strengthening and lengthening components. The muscles need to be able to contract under load and also relax fully to accommodate delivery. A client of mine at week thirty was doing aggressive Kegels throughout the day because her trainer told her to, and she ended up with hypertonic pelvic floor symptoms that caused significant pain during the pushing stage of labor. We shifted to diaphragmatic breathing with pelvic floor drops and coordination drills, and her symptoms improved over three weeks.
Get the Full Details

Red Flags That Should Stop Any Training Program Immediately
Vaginal bleeding at any point. Dizziness or fainting sensations. Regular contractions before term. Calf pain or swelling that doesn't resolve with elevation, which could indicate a deep vein thrombosis. Shortness of breath that is disproportionate to the activity level. These aren't suggestions for backing off, they're hard stops. I've heard stories from other trainers about clients who pushed through vaginal spotting in the first trimester thinking it was normal implantation bleeding, when in fact it was a sign of subchorionic hematoma. The person was fine in the end, but the training needed to have stopped the moment that symptom appeared. Another limitation worth noting is that a Training Program For Pregnancy is not something you should adopt if you have a high-risk pregnancy diagnosis. Placenta previa, cervical insufficiency, preeclampsia history, multiple gestation with complications — these require clearance from an obstetric provider and often call for modified or restricted activity plans that go well beyond what any general program can address. The programs available online and in gyms are built for low-risk pregnancies, and applying them blindly to higher-risk situations is where real harm happens.
Where to Find a Solid Program
There isn't a single downloadable file that covers this adequately because the variability between individuals is too high. What works for a person who was strength training regularly before pregnancy looks very different from what works for someone who was sedentary. The best approach is finding a certified prenatal fitness professional — look for certifications like those from ACOG-aligned programs or the National Strength and Conditioning Association's specialization in maternal health — who can build an individualized plan. If cost is a factor, some physical therapy clinics offer prenatal exercise programming at reduced rates, and a few university kinesiology departments run community clinics with supervised programs. The bottom line is that a pregnancy training program needs to be flexible enough to adjust weekly, not a fixed twelve-week plan you commit to on day one. Your body is doing something physiologically extreme, and treating exercise as a rigid checklist ignores that reality. The programs that produce the best outcomes are the ones that treat pregnancy as a dynamic state requiring ongoing assessment rather than a condition to power through with the same routines you used beforehand.