The Actual Path Through Respiratory Therapy School
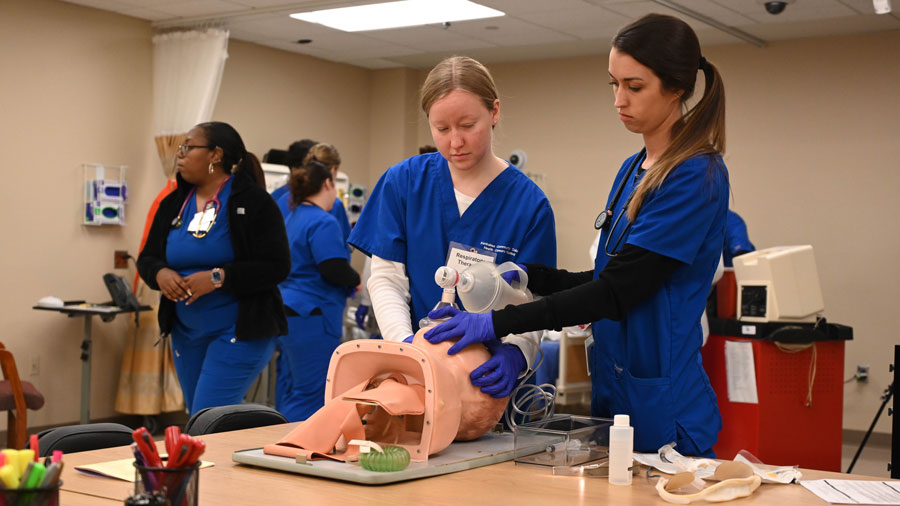
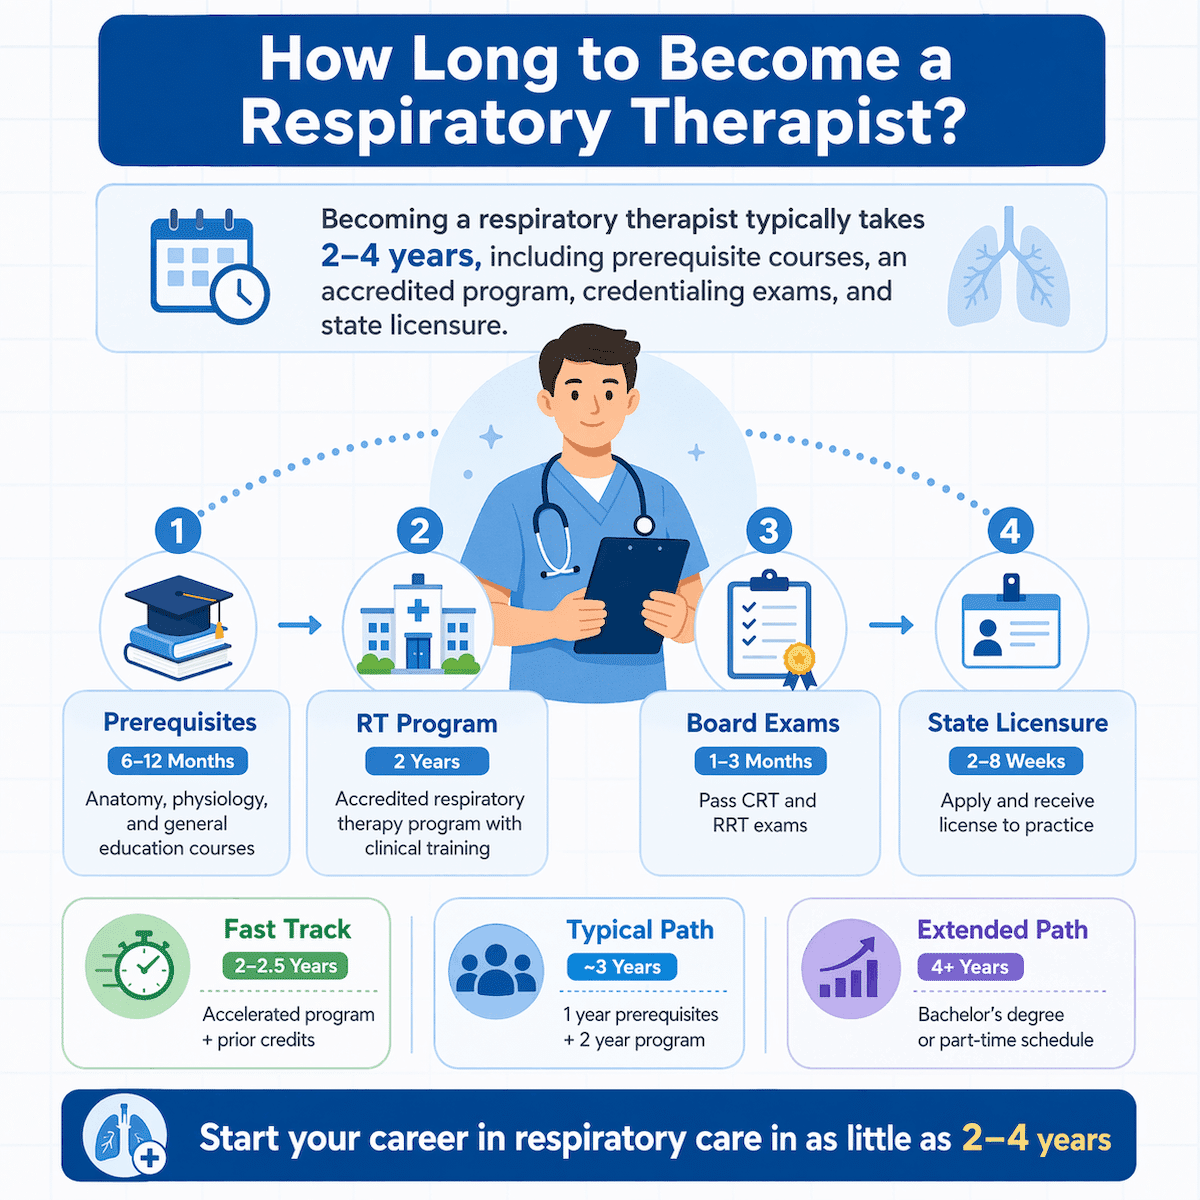
Most people think you need a four-year degree to become a respiratory therapist. That used to be true. Now, the majority of programs are two-year associate degrees offered through community colleges and technical schools. I watched several classmates graduate with just an Associates and land jobs at major hospital systems within three months. The gap between two-year and four-year programs has shrunk significantly, mostly because hospitals are desperate for qualified staff and can't afford to be picky about degree length anymore. The coursework is heavier than most students expect. It is not just anatomy and physiology repeated three times. You will spend weeks on ventilator mechanics, working through troubleshooting scenarios where the ventilator alarms won't stop and you need to figure out whether the problem is the circuit, the patient, or the machine itself. Blood gas interpretation takes up an entire semester, and honestly, that is where a lot of people stall out. Understanding partial pressures and buffer systems is one thing. Applying that knowledge when a patient's pH drops to 7.15 in the middle of the night is another. Clinical rotations are the real filter. You will complete somewhere between 400 and 800 hours across different settings—ICU, pneumology, neonatal ICU, sleep labs, and home care. I had a rotation in a cardiac ICU where I was paired with a preceptor who refused to let me touch anything until I could demonstrate lung sound identification blindfolded. Not literally blindfolded, but he would read auscultation findings and I had to identify the location and type of abnormal sound. It felt ridiculous at the time. Three weeks later, during a real code, I identified a tension pneumothorax by breath sound asymmetry before the attending did. That exercise saved a life. Your program might not include something that intense, but that is the standard you are being measured against.
What Actually Happens During Training To Be A Respiratory Therapist
The NBRC exam process is where most programs separate the people who will work clinically from the people who will not. You first take the Certified Respiratory Therapist exam, commonly called the CRT. This is the entry-level credential and it is required for state licensure in nearly every state. The exam covers patient assessment, therapeutic interventions, and equipment management. The writing portion requires you to compose full clinical narratives, not bullet points. I have seen students who ace the multiple-choice sections fail the writing exam because they wrote fragmented answers instead of complete clinical explanations. After passing the CRT, you typically take the Registered Respiratory Therapist exam, or RRT. This is the higher credential and it opens up more specialized positions. The RRT is notably harder because it assumes you already know the basics and tests your ability to apply that knowledge in complex scenarios. The pass rate hovers around 65 to 70 percent for first-time test-takers, which means roughly one in three people who sit for the RRT on their first attempt do not make it. I know this because several of my classmates did not pass and had to retake the exam months later while working their first jobs. State licensing is a separate step. You apply through your state's health board after passing the NBRC exams, and some states have additional requirements. California requires a state-specific jurisprudence exam. Texas mandates a background check that can take six to eight weeks to process. Florida has a clinical hour verification form that your program must complete and submit directly. These are bureaucratic hurdles, but they are real and they can delay your employment if you do not plan for them.
The Skills You Will Actually Use On Day One
Airway management is the first skill. You will perform endotracheal intubations on mannequins for months before you do one on a real patient. When you finally do your first intubation on a living person, it does not feel like a victory. It feels like surviving something. The laryngoscope blade feels heavier in your hand than it does in simulation. The patient's anatomy is never where the textbooks say it should be. I remember my first real intubation—a trauma patient with facial fractures. The standard approach was impossible. I had to use a video laryngoscope and adjust my angle by about 15 degrees from what I was trained to do. The textbook does not cover that scenario because textbook scenarios assume normal anatomy. Ventilator management is the second critical skill. You need to understand how to switch between modes, interpret waveforms, and respond to patient-ventilator dyssynchrony. The common pitfall here is relying too heavily on the ventilator's auto-mode. Modern ventilators have automatic programs that adjust settings based on patient effort. These are useful tools, but they are not infallible. I worked a night shift where the auto-mode kept cycling the patient into prolonged inspiration because it misread diaphragmatic contractions as patient effort. The patient was fighting the ventilator and becoming hypoxic. I had to override the auto-mode and switch to a controlled mode with sedation adjustment. The ventilator thought it was helping. It was making things worse. Blood gas analysis is the third area that determines whether you can function independently. You need to read an arterial blood gas and immediately understand the acid-base status, oxygenation level, and ventilatory adequacy. This is not optional. You cannot call a nurse and wait for an answer. The physician will ask you what the ABG shows and you need to respond with a complete interpretation. I had a patient whose pH was 7.28, PaCO2 was 55, and HCO3 was 26. A quick interpretation tells you acute respiratory acidosis. But the next question is why. Was it a medication effect? An exacerbation? A pulmonary embolism? The numbers alone do not tell you. You have to correlate with the clinical picture, which is something programs rarely emphasize enough.
Get the Full Details
What Programs Do Not Tell You About This Field
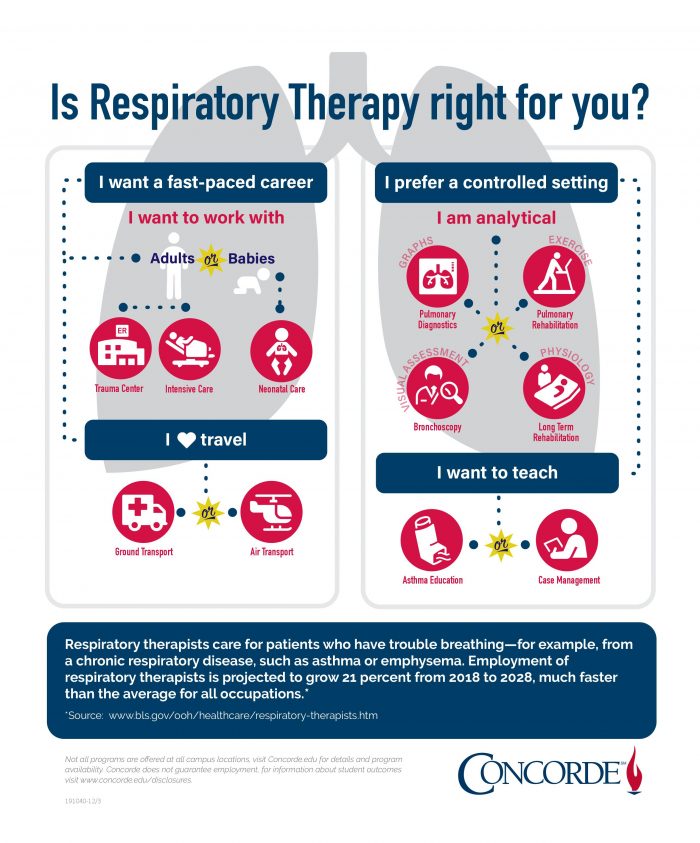
The job market for respiratory therapists is currently very strong. The Bureau of Labor Statistics projects growth well above average through 2032, driven by aging populations and chronic respiratory diseases. Hospitals are offering sign-on bonuses ranging from five thousand to fifteen thousand dollars in many markets. That sounds attractive, but you should understand what you are signing up for. Shift differentials for nights and weekends can add ten to twenty dollars per hour to your base pay. Travel respiratory therapy contracts can pay sixty to ninety dollars per hour. But these positions come with instability and constant relocation. Burnout is real and it is not discussed enough in program marketing materials. Respiratory therapists work in some of the most acute care environments. You will be present for codes, intubations, and palliative decisions. The emotional load accumulates. I had a colleague who left the profession after eighteen months because she could not cope with repeatedly resuscitating pediatric patients. That is not weakness. That is a legitimate occupational hazard and no program prepares you for it. There is also the physical demand. You will be on your feet for twelve-hour shifts. You will lift and reposition patients who cannot move themselves. You will work in confined spaces during emergencies. Your back and knees will ache. I have seen therapists develop chronic lower back issues within their first five years. Ergonomic training is minimal in most programs. You learn the clinical skills, but nobody teaches you how to protect your body while doing the work.
A Scenario That Standard Textbooks Miss
During my advanced clinical rotation, I had a patient with severe COPD who was placed on non-invasive ventilation, commonly called BiPAP. The standard protocol says to set initial pressures at 10 for inspiration and 5 for expiration. This patient failed that setting within forty-five minutes. He was agitated, his oxygen saturation was dropping, and he could not tolerate the mask. The textbook answer would be to increase the pressures gradually. I tried that and it made things worse—he was air swallowing and becoming more distended. The workaround was counter-intuitive. I decreased the expiratory pressure to 3 and added a heated humidifier setting that was not being used. The humidification reduced his mucosal irritation, which reduced his agitation, which improved his tolerance of the mask. The lower expiratory pressure helped him exhale more completely, which was critical because COPD patients trap air. The combination of these adjustments stabilized him within an hour. The standard algorithm would have kept increasing the pressures until it failed. Sometimes the problem is not the numbers on the machine. It is the comfort factors that the algorithm cannot measure. This is the kind of thing you learn through experience, not through classroom instruction. Programs teach you the protocols. You learn the exceptions by getting into situations where the protocols do not work and having to figure out what to do next.
A Practical Roadmap If You Are Considering This Path
Start by identifying accredited programs. The Commission on Accreditation for Respiratory Care, or CoARC, lists all accredited programs in the United States. There are approximately one hundred and fifty accredited programs. Do not enroll in a program that is not accredited. You will not be eligible to sit for the NBRC exams if your program lacks accreditation, and you will not be employable in most hospital systems. Prepare for the math component early. The NBRC exams include calculation questions on ventilator settings, oxygen therapy, and drug dosages. If your quantitative skills are weak, take a remedial math course before or during your first semester. I know someone who failed the CRT on her first attempt because she could not calculate the correct FiO2 adjustment for a patient moving from 40 percent to 50 percent oxygen flow. That is a basic calculation and it should not be this hard, but exam anxiety makes simple math feel impossible. Build your clinical skills outside of required rotations. Volunteer at free breathing clinics if your program allows it. Practice pulmonary function test administration on classmates. The more time you spend with equipment, the less nervous you will be during high-stakes situations. I spent three hours a week in the lab during my second year practicing nebulizer setups and ventilator circuits. When exam day came, those procedures felt automatic rather than stressful.
Network with practicing respiratory therapists before you graduate. Join the American Association for Respiratory Care as a student member. Attend local chapter meetings. These connections will help you find mentors and job opportunities. The respiratory therapy field is small, and most positions are filled through referrals rather than posted job listings. I got my first job offer from a preceptor I worked with during a rotation. She knew I was graduating and called her clinic manager before I even finished my final exam.
The Honest Limitations Of This Career Path
Respiratory therapy is not a high-paying profession at the entry level. Starting salaries typically range from forty-five thousand to sixty thousand dollars per year, depending on location and setting. Magnet hospitals in major cities may offer more, but the cost of living in those areas often absorbs the difference. Senior therapists with specialized certifications in critical care or sleep disorders can reach seventy to eighty-five thousand dollars, but that requires additional credentials and several years of experience. The career ceiling is lower than many healthcare professions. You cannot advance into management without additional education or a willingness to leave clinical work. Some respiratory therapists transition to sales roles with ventilator and equipment manufacturers, which can double their income. Others pursue a bachelor's or master's degree and move into education or administration. These are viable paths, but they require investment beyond the initial training. Automation is gradually changing the scope of practice. Some hospitals are reducing respiratory therapy staffing by implementing automated ventilator weaning protocols and expanding the role of nurses in airway management. This trend is not widespread yet, but it is growing. Programs should be teaching students to adapt to changing scopes of practice, but most curricula remain focused on traditional responsibilities. Being aware of this trend will help you plan your career trajectory more strategically.
If you are serious about this profession, the training is manageable but demanding. The programs are rigorous. The exams are difficult. The work is physically and emotionally taxing. But the field needs more competent therapists, and there is genuine job security for people who do the work well. The question is not whether you can handle the training. It is whether you can handle the reality of the job after you finish it.