What Botox Training Actually Looks Like
Most people think you just show up to a weekend workshop and suddenly you can do it. It doesn't work that way. The real path to competency involves structured didactic hours, supervised live injections, and a significant amount of reading anatomy between sessions. I went through three different programs over two years before I felt confident enough to take on my own patients without a preceptor standing over my shoulder. The core components are consistent across reputable programs. You need to understand the pharmacology — how onabotulinumtoxinA and the other formulations differ in protein complex size, diffusion characteristics, and reconstitution requirements. You need landmark-based and ultrasound-guided injection technique. And you need complication management training that isn't just a five-minute slide about ptosis.
Training To Give Botox Injections: Where Most Programs Fall Short
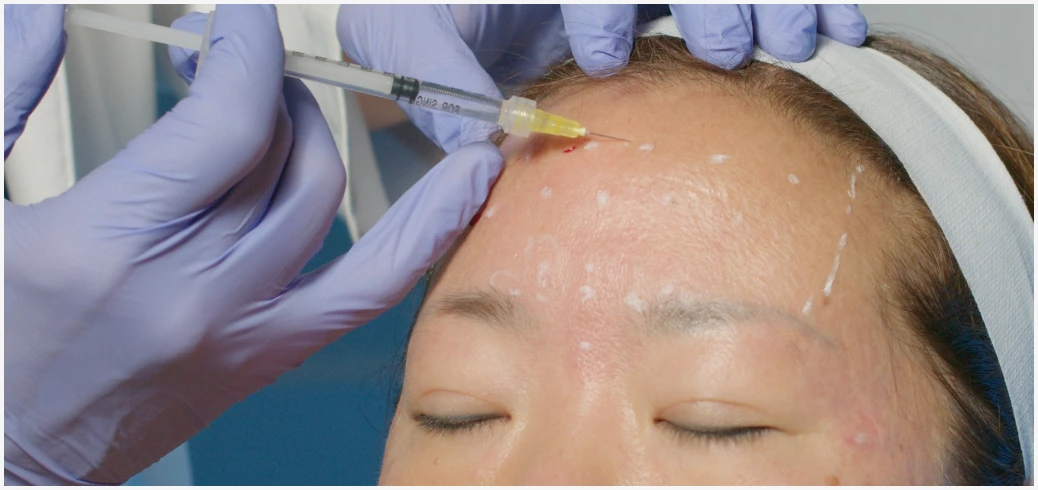
I attended a course that billed itself as comprehensive. It covered the glabellar line protocol, which is the FDA-approved indication with the most published data. Good. They also touched on crow's feet and forehead lines. What they did not cover was what to do when a patient has asymmetric frontalis function or when the brow sits differently on each side. I ran into this within my third month of independent practice. A patient came in for glabellar work and I placed standard 4-unit dots bilaterally. Three days later, her left brow had dropped noticeably while the right stayed normal. The asymmetry was subtle but obvious to her. The workaround was straightforward once I understood the mechanics. I injected 2 units of diluted toxin into the left lateral frontal belly at a higher position than the standard forehead map, which allowed the depressor action to pull that side back down into symmetry. It took another two weeks for the full effect to show. That kind of problem-solving doesn't come from a PowerPoint. It comes from seeing the complication and figuring out the physics of why it happened. Here is what I wish every training program emphasized more than they do: reconstitution volume matters more than the total unit count. A lot of instructors tell you to add 2.5 mL of saline to a 100-unit vial and call it done. That gives you 40 units per mL. But if you are doing delicate work around the eyes with a 30-gauge needle, that concentration is too thick. You will see tracking and bruising. I switched to a 1:1 ratio — 1 mL saline to 100 units — giving 100 units per mL. The lower viscosity means cleaner deposition, less tissue trauma, and more precise diffusion control. It also means you are drawing up more volume per injection, which sounds inefficient until you account for the reduction in retry sticks and the better cosmetic outcome.
Another thing that never gets enough air: the temporal fossa injection is where most beginners cause problems. The temporal artery runs right through the mid-portion of that space. If you are depositing toxin too deep or too lateral, you risk intravascular placement or unnecessary bruising. The safe zone is the superomedial quadrant, roughly two finger widths above the orbital rim and one finger width medial to the lateral orbital tail. Go deeper than 5 mm and you are playing with structural anatomy you should be avoiding entirely in a beginner context. Ultrasound guidance for the temporal and masseter regions is genuinely useful but underutilized in training programs. I would recommend seeking out a course that includes live ultrasound demonstration. Not a video. Live. You need to see how the beam identifies the masseter border in real time and how that changes your injection plane. Programs that skip this are leaving you blind for any work beyond the standard three-glabellar-line sites. Not every training path is worth your time. The red flags are easy to spot. Courses that guarantee certification after six hours with no hands-on patient contact. Programs that don't include a formal assessment on facial anatomy before letting you touch a syringe. Anything that promises results in a single day without supervised clinical practice is selling you a credential, not competence.
Get the Full Details

The legitimate routes are through professional medical societies — the American Academy of Cosmetic Surgery, the American Society for Dermatologic Surgery, and state-level medical society continuing education tracks. Many of these require you to hold an active MD, DO, NP, or PA license in good standing. Some offer observation-only tracks for students who are still in training. If you are not yet at the point where you can independently manage complications, stick to the observer role until your preceptor signs off on your technique. Botox training is not a checkbox. It is a threshold. Once you cross it, the complications keep coming in forms you did not anticipate. The better prepared you are going in, the less damage you do when things go sideways. Focus on programs that emphasize complication recognition and anatomical reasoning over protocol memorization. The protocols will stick. The reasoning is what you need to build.