Transference And Countertransference In Psychotherapy
Verma
2026-09-24
What actually happens when a client projects onto you
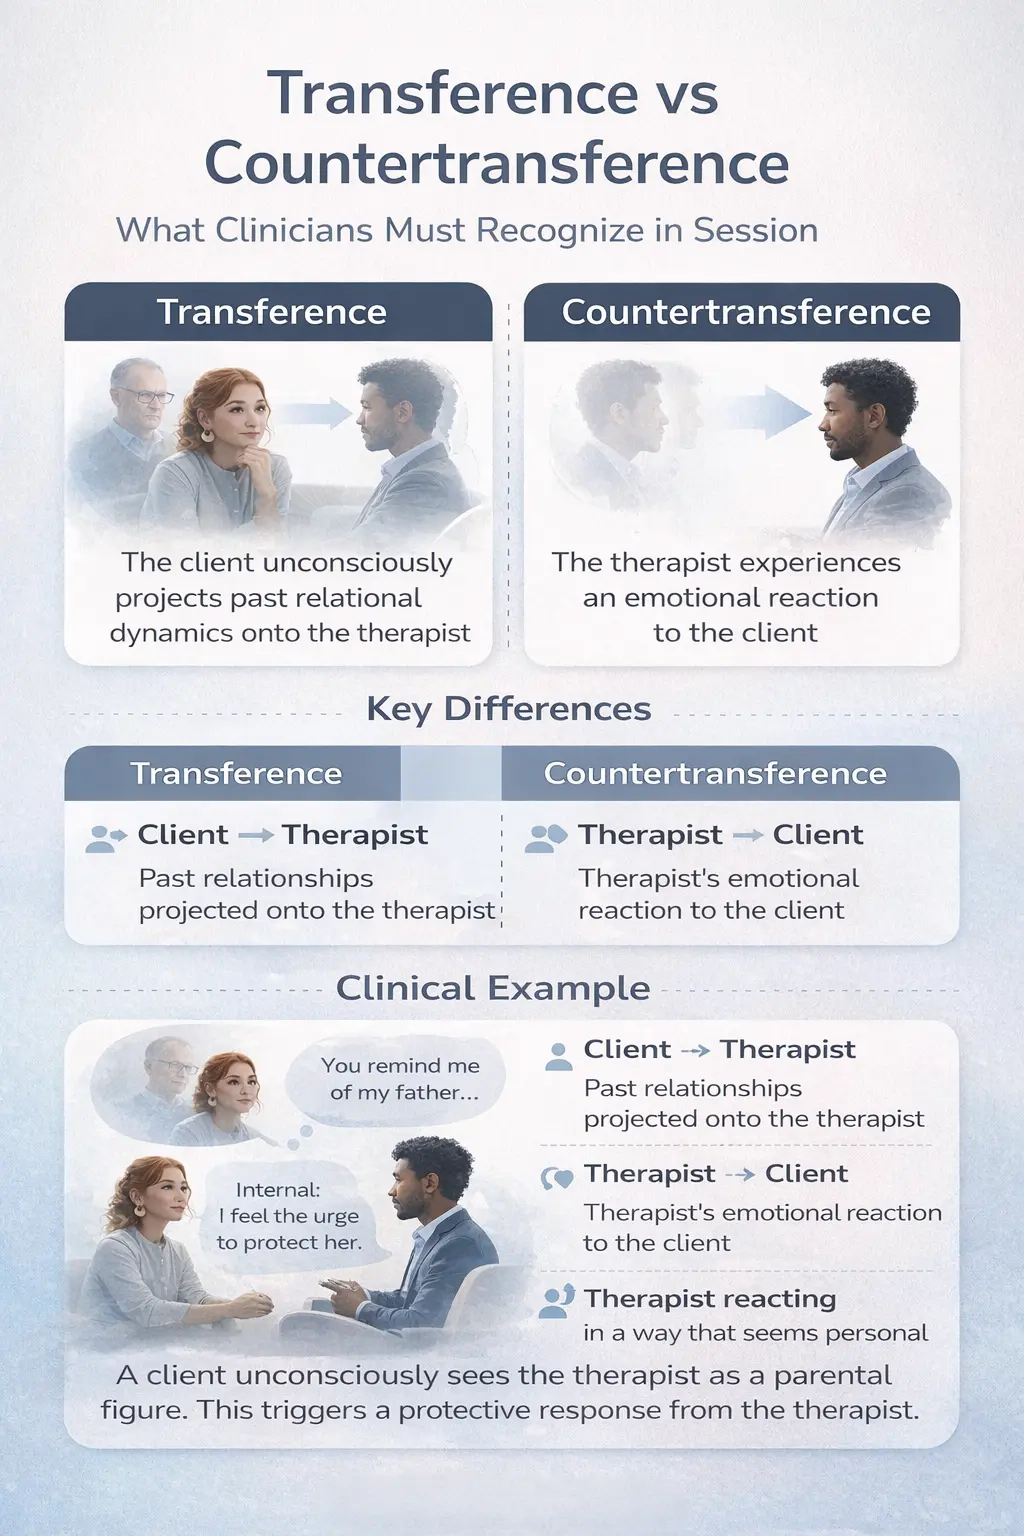
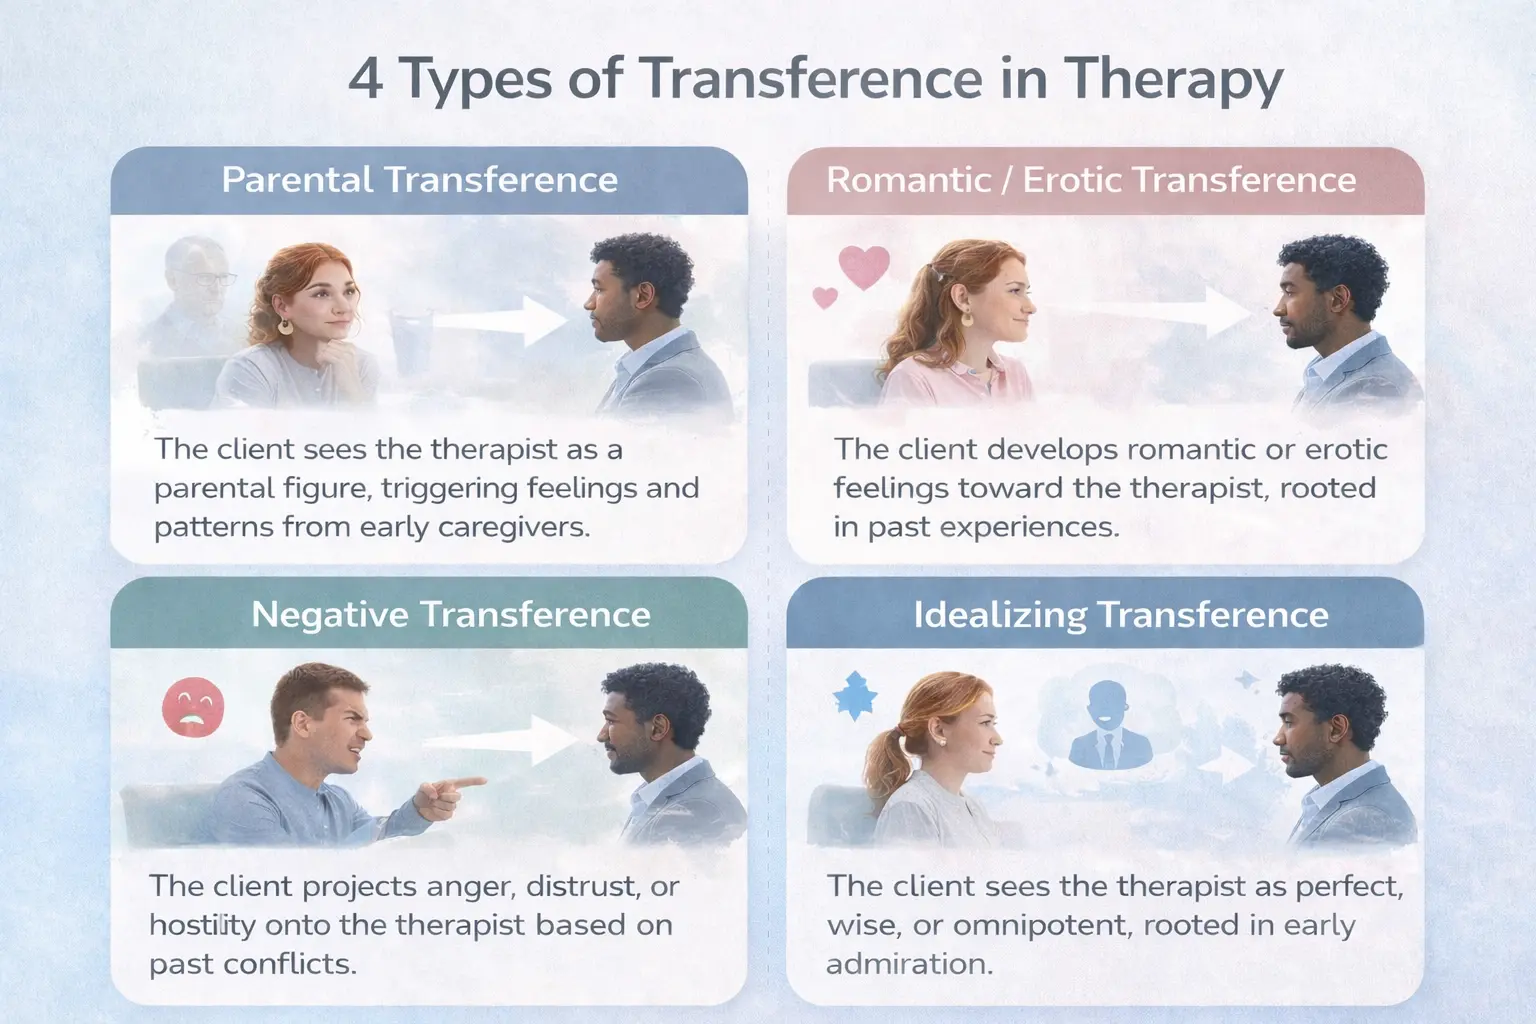
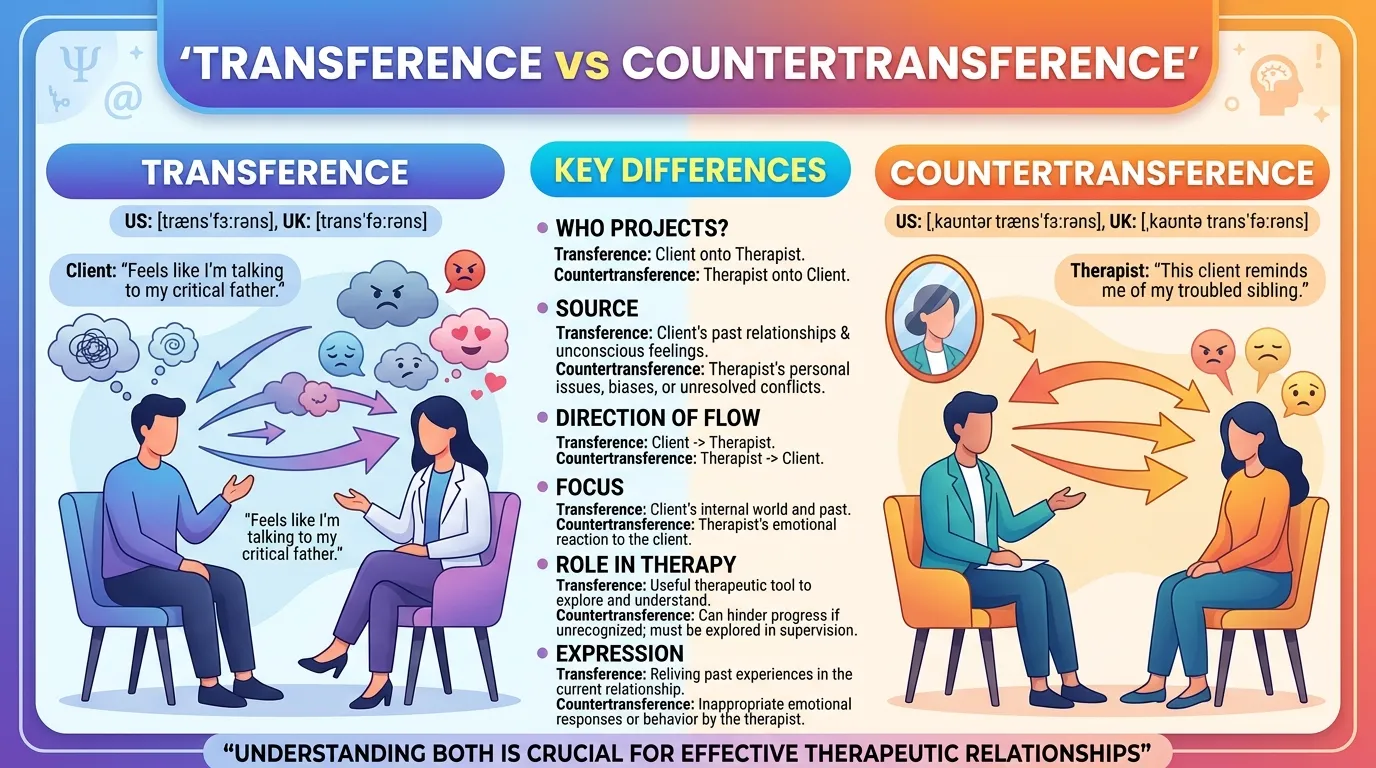
Most new clinicians get tripped up by transference because they think it looks dramatic. It almost never does. A client doesn't suddenly declare they hate you like their father. They cancel three sessions in a row, arrive exactly seven minutes late every Tuesday, or compliment your office decor with an intensity that makes you uncomfortable and you can't figure out why. The signal is usually buried under surface behavior. You catch it by tracking patterns across multiple sessions rather than trying to interpret a single moment.
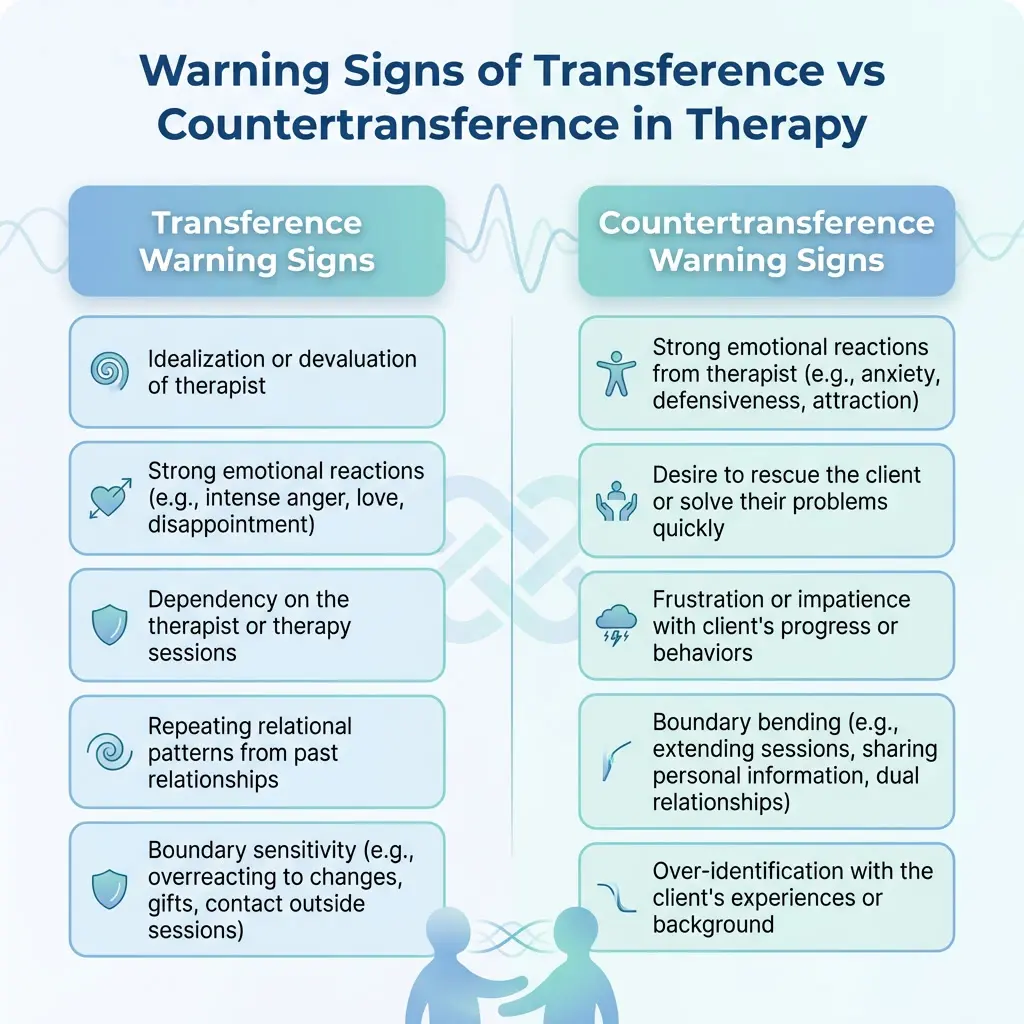
Countertransference is the reciprocal system. Your own reaction to the client becomes data. If you find yourself feeling unusually sleepy during a particular client's sessions, irritated by their posture, or excessively eager to rescue them from a problem they're perfectly capable of handling, that emotional shift is worth examining. The mistake people make is assuming their feelings are purely personal. They're usually partially relational. Your brain is picking up cues your conscious mind hasn't processed yet.
I worked with a client in my late thirties who'd been in therapy for about eight months when the dynamic shifted noticeably. She started referring to me as "like a big brother" in a way that felt performative, almost testing whether I'd push back. When I didn't, she escalated. She began sharing increasingly traumatic material in rapid succession, as if hurrying past whatever guardrail she expected me to set. I felt this overwhelming urge to be accommodating, to let her pace things because I didn't want her to feel pressured. That feeling was the countertransference signal. My job wasn't to act on it. It was to notice it and use it. I recognized that I was unconsciously recreating the dynamic she had with authority figures in her life, where accommodation meant safety and boundaries meant abandonment. I addressed it directly in session by naming the pattern I was observing without attaching blame. She ended up crying, then got angry at me for "making it weird," and then stayed in therapy for another two years and made significant progress. The key was staying curious instead of defensive.
Transference And Countertransference In Psychotherapy: practical navigation
The standard model has you identify the transference, interpret it, and work through it. That works for neurotic-level dynamics in relatively stable clients. It breaks down completely with personality disorders, active psychosis, or clients in acute crisis. With BPD, transference can intensify to split idealization and devaluation within a single session. Interpreting that in the moment usually makes it worse. You need to contain the affect first, validate the experience, and only later explore the pattern. Timing matters more than technique.
One thing textbooks don't emphasize enough: countertransference isn't always about the client. Sometimes your reaction is genuinely about you, and you'll never know which until you've done enough personal therapy and supervision to calibrate your own triggers. A client who reminds you of your ex will elicit responses that have nothing to do with the present moment. That's not a failure of your skill. It's a failure of your self-awareness. The only real fix is honest supervision and ongoing self-examination, not a technique you can memorize.
Another counter-intuitive point: transference isn't something you eliminate. It's something you use. The therapeutic relationship is always filtered through the client's internal object relations. Trying to be a blank slate is both impossible and counterproductive. What matters is whether you can recognize when the filter is distorting the interaction and bring that into awareness, both for yourself and eventually for the client.
Here's where the method fails. Transference work assumes the client has some capacity for reflection. Clients with severe cognitive impairment, active substance intoxication, or fragmented ego structure simply cannot engage with it meaningfully. Forcing interpretation in those cases is just verbal noise. In those scenarios, you focus on containment, consistency, and basic emotional regulation support. The transference is still there, but your intervention needs are different.
I keep a small notebook beside my chair specifically for noting countertransference reactions between sessions. Not interpretations, just raw feelings. "Felt anxious today." "Wanted to give advice." "Bored but couldn't look away." That separation between feeling and analyzing is critical. If you analyze immediately, you're usually rationalizing. If you note it raw and revisit it later, often in supervision, you get closer to what's actually happening. Most people skip the raw notation and go straight to analysis, which is why their interpretations feel wrong even when they sound reasonable.
The other common failure mode is over-interpretation. Clients don't need you to map their transference in exhaustive detail. One clear, well-timed observation about the here-and-now pattern is worth more than a semester of structural analysis. The client's nervous system needs to feel understood before it can tolerate understanding. Push interpretation too early and you trigger defensiveness that looks like resistance but is actually overwhelm.
Supervision is non-negotiable for this work. Not the monthly check-in where you discuss caseloads. Actual process supervision where you bring recorded sessions or detailed notes and a supervisor who will challenge your self-assessment. You will consistently misread your own countertransference. This isn't modesty, it's a documented limitation of self-report. Even experienced clinicians miss the signal until someone else points it out.
A note on your own therapy
If you're not in regular personal therapy, you're flying partially blind. Your blind spots will show up in your clients' material. A therapist who avoids conflict will have a cluster of clients who never express anger and a growing sense of unease they can't name. A therapist with unresolved abandonment issues will over-invest in clients who show dependency and panic when those clients terminate. These aren't hypotheticals. This is the machinery working the way it always does.
The practical takeaway is straightforward. Notice your reactions. Don't act on them immediately. Bring them to supervision. Distinguish between your stuff and their stuff through pattern recognition over time. Use the transference as your primary diagnostic and intervention tool rather than treating it as an obstacle to the "real" work. And recognize when the situation calls for something else entirely instead of forcing this model where it doesn't fit.
Gallery Transference And Countertransference In Psychotherapy
Transference and Countertransference in Therapy: Examples & Tips
Transference and Countertransference in Therapy: Examples & Tips
Transference vs Countertransference in Psychology Explained
Transference & Countertransference in Psychoanalysis
Signs of Countertransference in Therapy