What actually happens when you look at bladder tissue under the scope
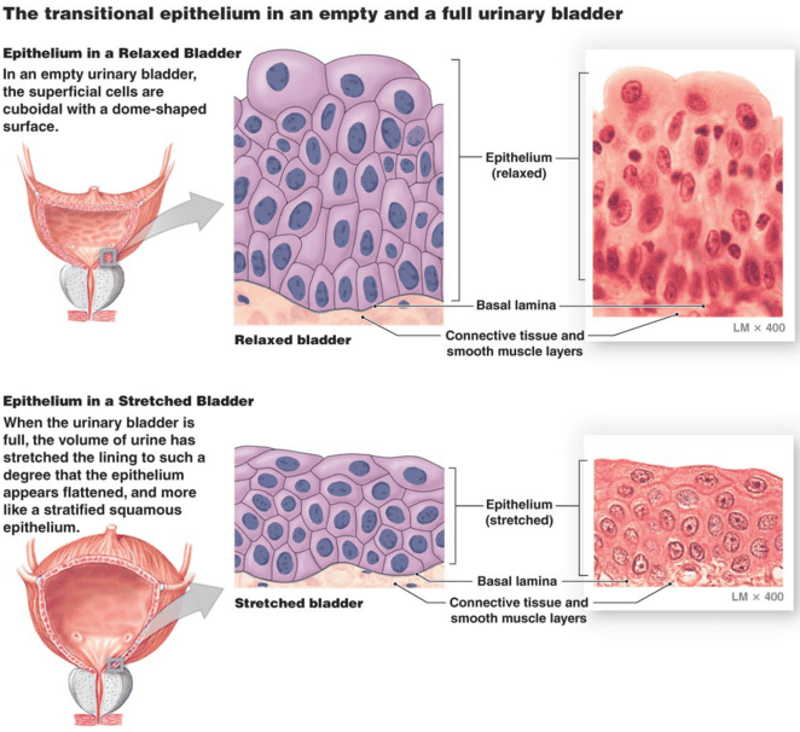
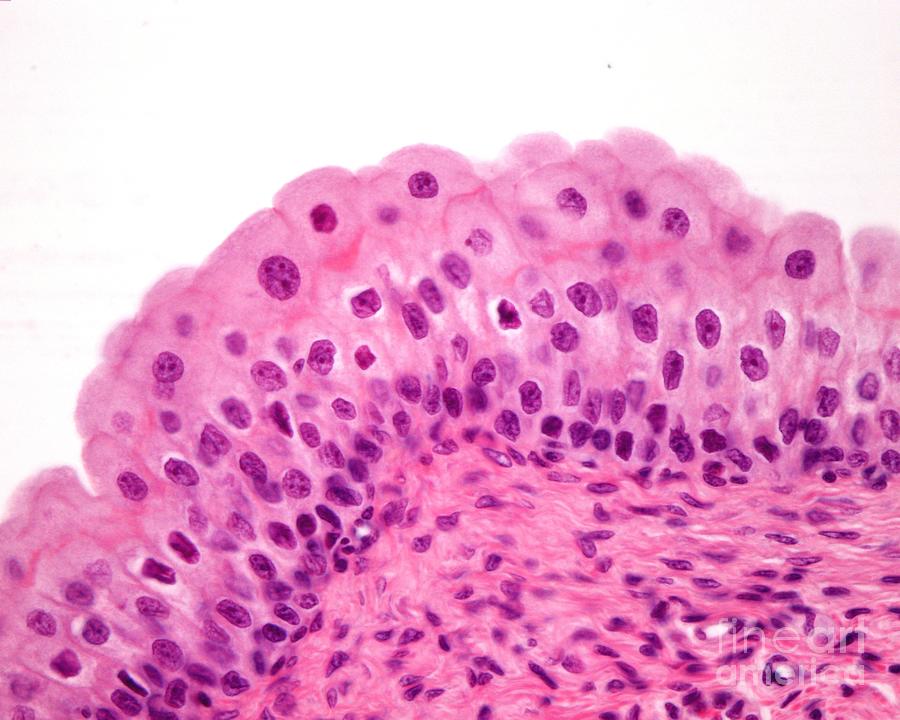
You grab a biopsy, fix it in formalin, section it at four microns, and run H&E. The surface layer looks like a stack of loose umbrellas, big domed cells sitting on top of smaller basal cells. If the bladder is relaxed, those umbrella cells are enormous and binucleated sometimes. If it was distended at the time of collection, they look squashed and flattened. This variability trips up pathology residents constantly. They call it urothelial dysplasia when it is really just a contracted specimen. The correct name for what most people call transitional epithelium is urothelium. It lines the renal pelvis, ureters, bladder, and proximal urethra. It is a stratified epithelium with a unique apical surface made of uroplakins, those protein-rich asymmetric unit membrane plaques that form the permeability barrier. Without those plaques, urine toxins would diffuse straight into the lamina propria and you would have a very sick person within hours. The layering goes from basal cells at the bottom to intermediate cells in the middle, then the superficial umbrella cells on top. In a fully distended bladder you might see only two or three cell layers visible. At rest you can count six or seven. That elasticity is the whole point of the tissue. Here is a practical problem I ran into a few years ago that took me way too long to figure out. We had a cystoscopy specimen where the surface looked subtly thickened with mild nuclear atypia in the lower half of the epithelium. The gross description said the bladder was poorly distended during the procedure. I almost signed it out as low-grade urothelial carcinoma because the nuclei were slightly enlarged and hyperchromatic. Instead of rushing, I went back to the original blocks, recut at three microns, and ran a p53 immunostain alongside Ki-67. The proliferation index was restricted to the basal third, not the full thickness, and p53 was wild-type pattern. Combined with the known contracted state of the specimen, it was reactive atypia from catheter trauma, not neopasia. Misreading that as cancer would have led to a unnecessary radical cystectomy workup in a real patient. The workaround was straightforward: always correlate the macroscopic distension state with the microscopic appearance, and when in doubt, use Ki-67 to check the proliferation distribution before committing to a dysplasia call.
Urothelium has a few quirks that nobody warns you about. One is that the lamina propria underneath can look deceptively inflamed even in completely normal bladders because the tissue is rich in mast cells and lymphoid aggregates. Calling that chronic cystitis without actual neutrophilic infiltration or ulceration is a common overcall. Another thing is karyomegaly. The umbrella cells regularly show nuclei that are two to three times the size of a basal cell nucleus, and that is entirely benign. Beginners see big nuclei and jump to malignancy. Size alone does not equal cancer in urothelium. Specimen handling matters a lot more than people admit. If you fix a bladder piece in neutral buffered formalin for less than six hours, the urothelial relief artifacts make the surface look artificially desquamated. The cells slough off during processing and you end up with a histology slide that mimics severe urothelial carcinoma in situ. Minimum fixation time is eight hours for mucosal surfaces. Don't skip it to save time. You will spend three hours fixing a mistake later. The permeability barrier itself is not something you assess on routine H&E. You need electron microscopy to properly visualize the uroplakin plaques, or at minimum immunohistochemistry for uroplakin III if you need to confirm the differentiation of a suspected urothelial tumor. Some labs use this when the morphology is ambiguous, especially in small biopsies where invasion is the question. Uroplakin staining is also useful in distinguishing metastatic urothelial carcinoma from other adenocarcinomas in the pelvis, which comes up more often than you would expect.
There are legitimate limitations to relying on transitional epithelium morphology alone for diagnosis. Schistosoma haematobium infection causes squamous metaplasia that completely obliterates the normal urothelial architecture. You cannot stage or grade anything meaningfully in that field of view. Cyclophosphamide-induced hemorrhagic cystitis produces massive apoptotic bodies and surface necrosis that look alarming but are treatment effects, not malignancy. Radiation cystitis does the same thing years later. In all three scenarios, the histologic appearance overlaps heavily with high-grade urothelial carcinoma, and the only reliable differentiator is clinical history. Without it, you are guessing. For clinical correlation, the most important thing is cystoscopic inspection before biopsy. A white plaque, a papillary frond, and a flat erythematous area each carry different probabilities for underlying pathology. Takahashi grading and the WHO 1973 versus 2004 classification systems both exist and pathologists still argue about which to use. The practical reality is that interobserver agreement among pathologists on low-grade papillary urothelial neoplasms is only around seventy percent. That is not a flaw in your technique. It is a reflection of how subtle the cytologic differences actually are between entities. If you are learning to read this tissue, start by identifying the contraction artifact. Look at the subepithelial collagen. In a well-distended specimen it forms delicate thin wisps beneath the epithelium. In a contracted specimen it collapses into dense irregular bundles that can mimic desmoplasia. Confusing the two has caused overstaging. Then practice distinguishing true nuclear atypia from the large pale nuclei of normal umbrella cells. The latter have prominent nucleoli but smooth nuclear membranes. Atypical nuclei have irregular contours and coarse chromatin. That distinction is everything.
Get the Full Details

I use a quick checklist when I process these slides: specimen distension state noted, fixation time recorded, lamina propria inflammation assessed for neutrophils not just lymphocytes, nuclear atypia evaluated for membrane irregularity not just size, and Ki-67 reserved for cases where the proliferation pattern changes management. That list usually cuts diagnostic uncertainty from about twenty percent of cases down to single digits. The remaining cases are the ones where you refer for a second opinion and document the ambiguity. That is acceptable. It is better than signing out the wrong diagnosis. The tissue is forgiving but it is not simple. It does exactly what it is supposed to do, which is stretch without leaking and shed without falling apart. The histology reflects that function in every layer. Understanding the mechanics makes the slides easier to read.