Why Most Behavioral Interventions Stall Out
The Transtheoretical Model Of Change broke a lot of ground when Prochaska and DiClemente first put it together in the late 1980s, but the way people talk about it online has mostly turned it into a cartoon version of itself. The stages get treated like a staircase. Step one, step two, step three, done. That's not how it works in any real application. It works more like a fan blade — people spin between stages constantly, sometimes within the same week. I ran into this explicitly about four years ago when I was working with a group of clinicians trying to implement a structured change program for chronic disease management. We had the standard motivational interviewing training, we had the stage-matching materials, everything looked perfect on paper. The problem was that roughly a third of our participants were stuck in a loop between contemplation and preparation that we couldn't crack no matter what we tried. They'd sign up for the weight loss program, they'd set goals, they'd come back to the next session and immediately undercut everything. It wasn't defiance or lying. It was a pattern I'd seen before in this model but rarely discussed clearly. What we were dealing with is called decisional balance imbalance. The person is weighing the pros and cons of changing, but the scale never actually tips because their internal counterarguments to change have a much more emotional anchor than their stated reasons for it. This isn't something that shows up on a basic transtheoretical stage assessment form.
How to Actually Use the Transtheoretical Model Of Change
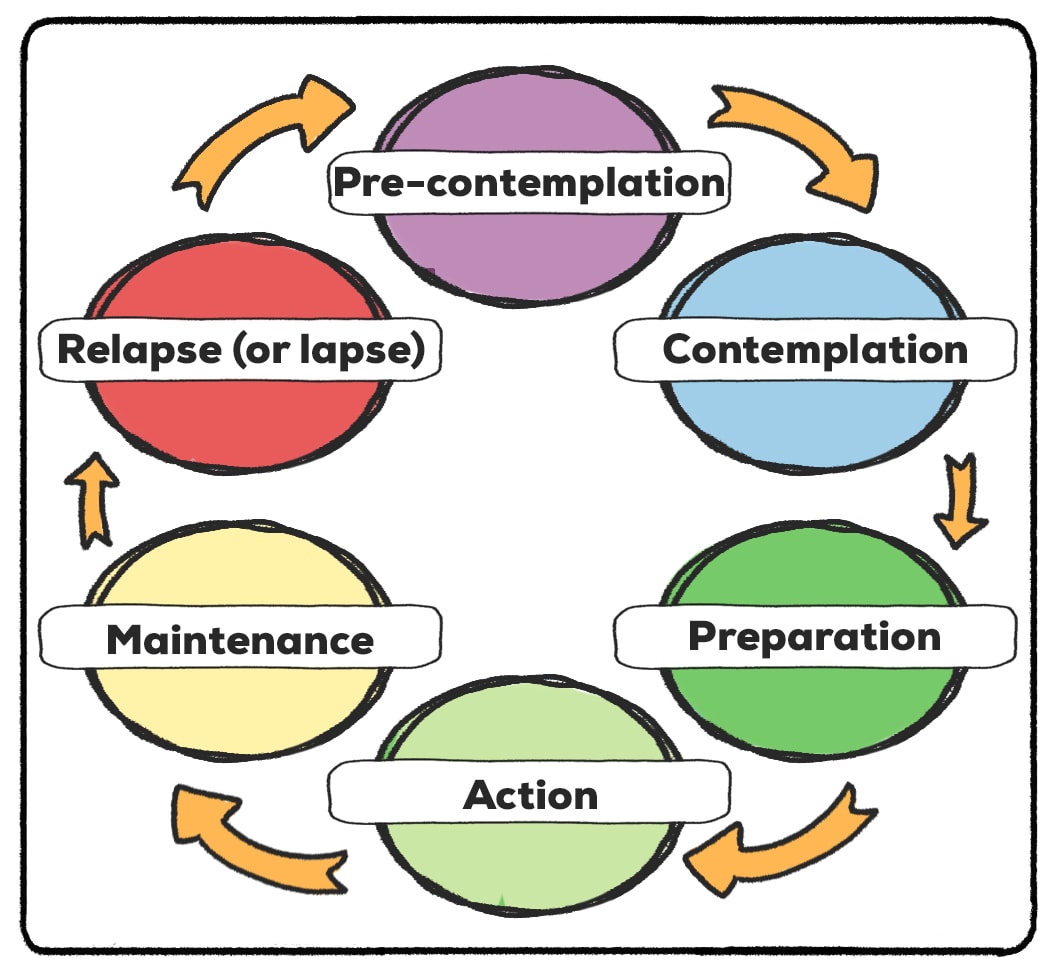
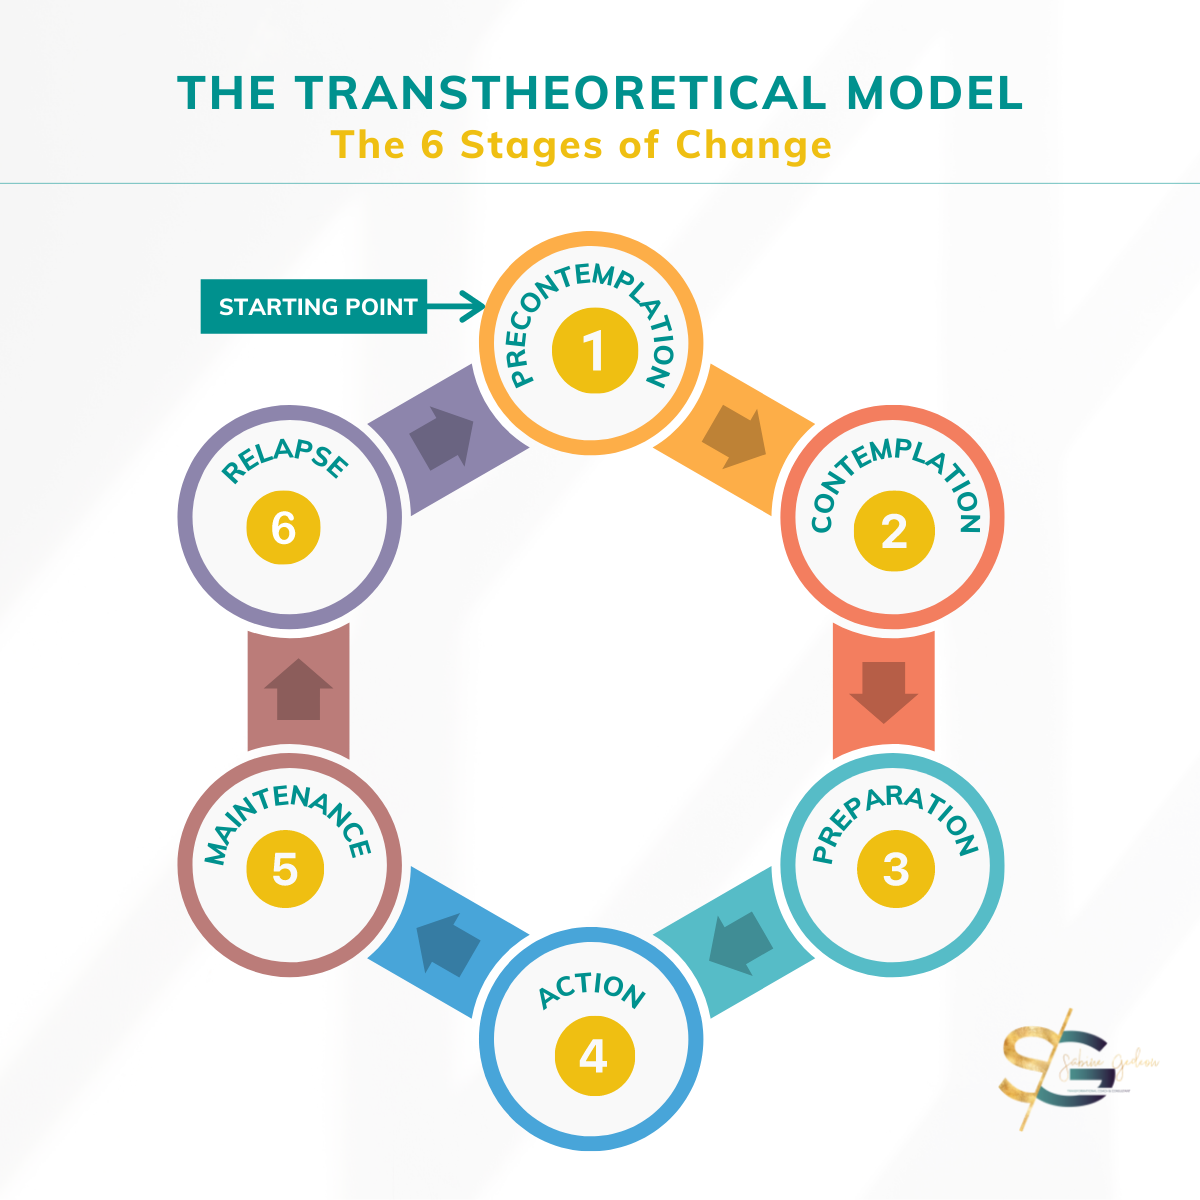
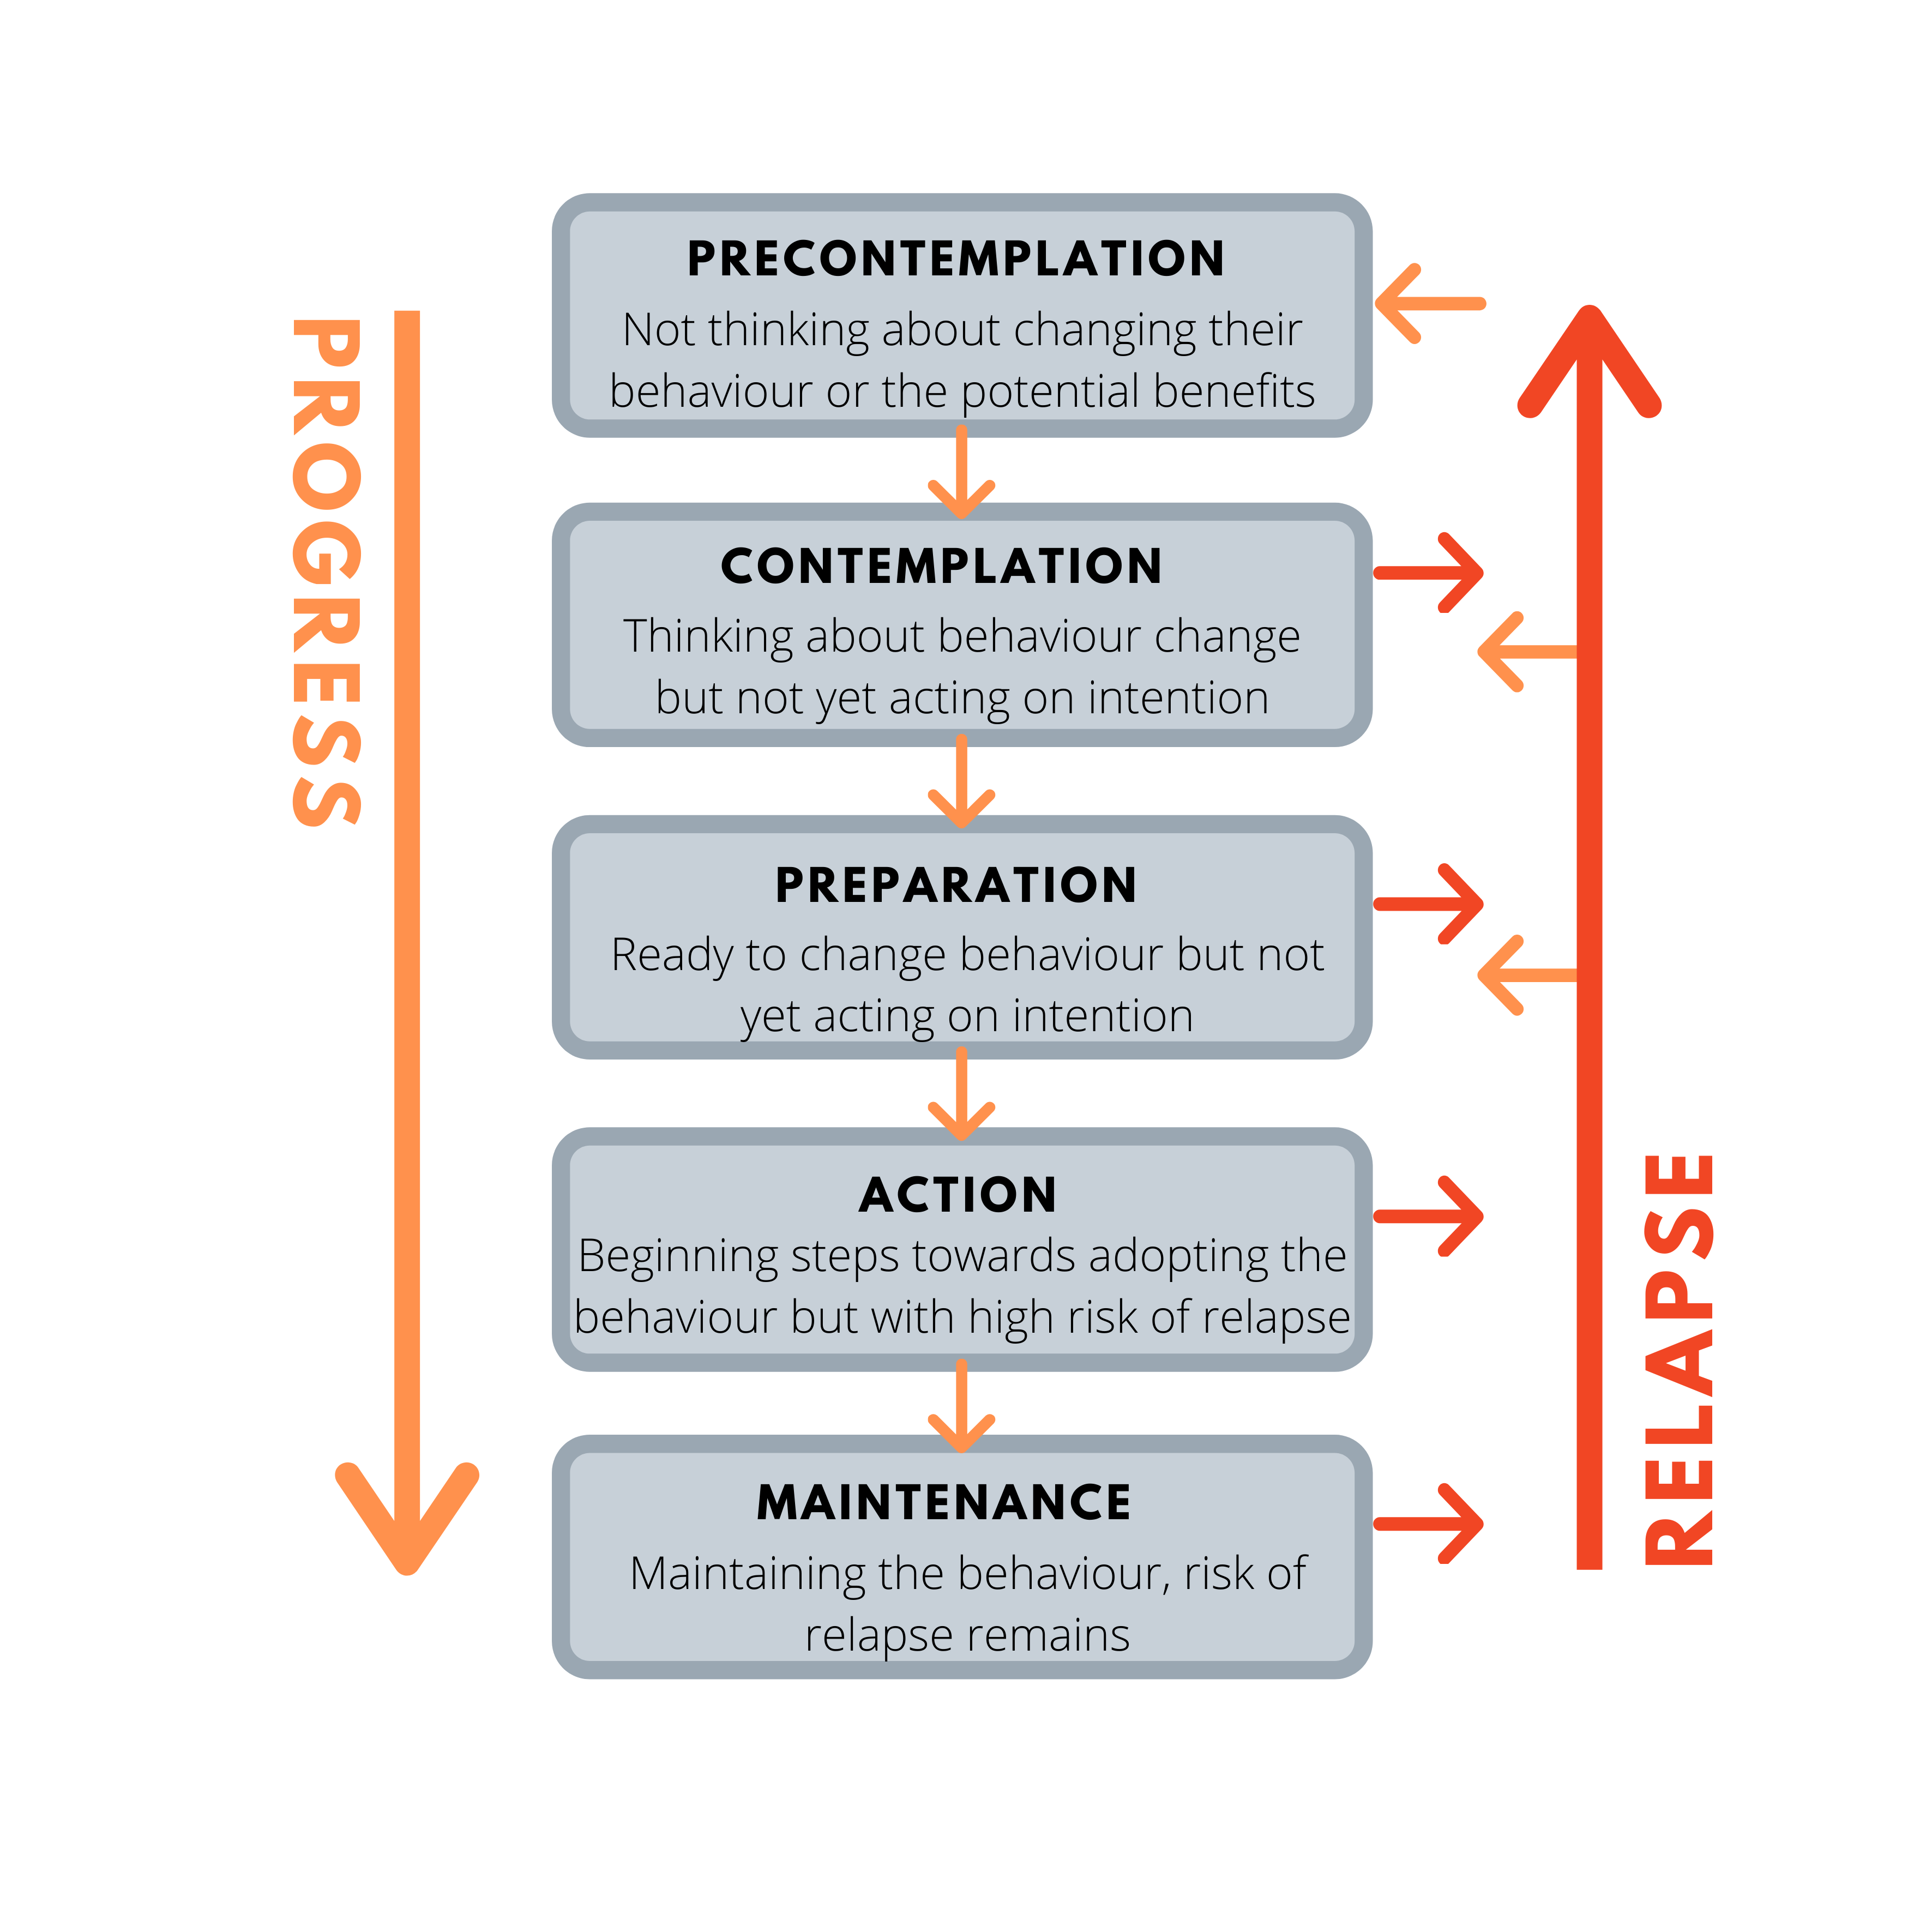
Start with the six stages. Precontemplation means the person doesn't see the behavior as a problem at all. Contemplation means they're aware but ambivalent. Preparation means they're planning action soon, usually within a month. Action means they've made visible changes. Maintenance means they're keeping the new behavior going beyond six months. Termination means zero temptation — this last one is rare and honestly overrated in most clinical applications. The key insight nobody emphasizes enough is that stage matching doesn't mean you just identify the stage and deliver the corresponding intervention like a vending machine. You identify where someone is, you understand what cognitive work needs to happen to move them, and then you intervene in a way that's proportionate to their current readiness. Pushing action-stage techniques on someone in precontemplation doesn't just fail, it actively damages the therapeutic relationship. People notice when you're trying to hurry them through something they're not ready for. It reads as pressure, even when you're being earnest about it. The processes of change are where this gets practical. There are ten of them, split into experiential and behavioral categories. Experiential ones — consciousness raising, dramatic relief, environmental reassessment — tend to matter more in the earlier stages. Behavioral ones — counterconditioning, reinforcement management, helping relationships — matter more once someone is actually doing something. A common mistake I see is people trying to deploy behavioral processes too early, which just confuses the intervention and slows progress.
Here's the part that matters in practice. If you're working with someone in contemplation and they're not moving, ask them to describe their typical day in detail. Write down every decision point where their behavior shows up. What actually triggers it? What stops them from doing something different in the moment? This is far more useful than any questionnaire. It takes about twenty minutes to do properly and it maps the actual terrain instead of relying on self-report that may be distorted by the person's own blind spots. I encountered a case last year involving a participant who kept cycling between contemplation and action with a smoking cessation program. Every time he committed, he'd quit for three weeks, then relapse hard. The issue wasn't lack of motivation or awareness. The issue was that his contemplation stage was built entirely on anticipated future benefits. He had no concrete plan for the actual first week of withdrawal. When we spent two sessions mapping out the exact physical symptoms he'd face hour by hour and built specific coping strategies for each one, his action-to-maintenance transition time dropped from about three weeks to sustained change in under two weeks. The stage model doesn't tell you this on its own. You have to do the granular work underneath it.
Get the Full Details

Where the Model Actually Fails
The Transtheoretical Model runs into real problems in several areas. The temporal aspect is the biggest one. There's no standard metric for how long someone should spend in each stage. Some people move through contemplation in days. Others sit there for two years. The model acknowledges this but doesn't give you a practical tool for handling it. Stage crossing is also poorly defined. Someone can move backward, forward, sideways, or skip stages entirely depending on the behavior in question and their personal history. There's no consistent framework for predicting which direction a specific person will move. Cultural applicability is another issue. The model was built largely on North American samples. It doesn't translate cleanly to collectivist cultures where individual behavioral change is framed differently, or to contexts where external constraints — poverty, discrimination, lack of access — dominate the decision landscape more than personal readiness. In these situations, the stage model can feel like victim-blaming dressed up as psychology. For certain behaviors, like substance dependence with physiological components, the model needs significant modification. Withdrawal management, medical detox, and pharmacotherapy often need to happen before any stage-matched psychological intervention makes sense. Throwing someone in early contemplation at a recovery program while they're physically dependent without addressing the biological reality usually just increases dropout.
If you're looking for a complementary framework, the Health Belief Model works well alongside the transtheoretical approach for initial assessment, and Self-Determination Theory provides a stronger foundation for understanding intrinsic motivation once someone is actively engaged in change. Using all three together tends to produce better outcomes than any single model alone. The model is still useful. It's not a cure-all, and it's not precise, but it gives you a vocabulary for understanding where someone is in a way that most alternative frameworks don't. The practitioners who get the best results are the ones who treat the stages as a descriptive map rather than a prescription, and who do the actual work of understanding each person's specific barriers and motivators behind the labels.