Pharmacological Treatment of Asthma PPT
I've been putting together slide decks on asthma medication for a long time. It sounds like something you'd find in any university library, but there's a specific problem with these presentations that most people gloss over. They're either too simplified for clinicians or so dense that nobody actually learns anything from them. The real value isn't in the PPT itself. It's in how you structure the pharmacological information so it sticks during a lecture or a quick review session. Let me walk through what works and what doesn't.
Tratamiento Farmacologico De Asma Ppt
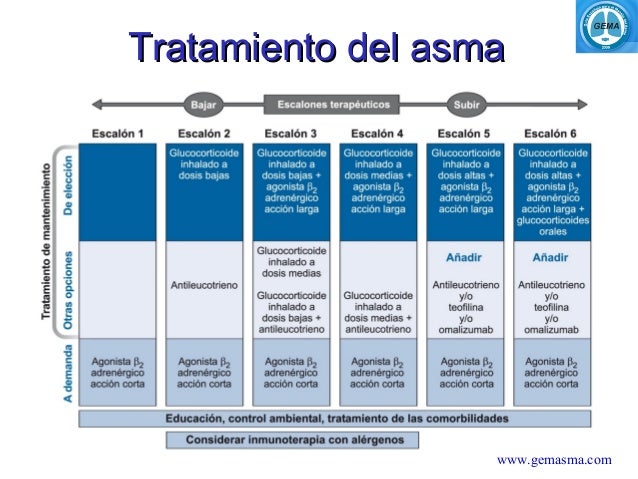
Start with the GINA guidelines. Everything else is just commentary on those guidelines. The 2023-2024 updates shifted the approach significantly. We moved away from SABA-only treatment as first-line for persistent asthma. That changed the whole framework of how these presentations need to be built. If you're creating or using a slide deck on this topic, the first thing I always check is whether it's still using the old stepwise approach where albuterol alone was considered sufficient for mild cases. It isn't anymore. Presenting outdated dosing or step recommendations will undermine your credibility immediately, especially with anyone who practices respiratory medicine. Here's what I include in my own materials. The first section covers quick-relief medications. Short-acting beta-agonists, mainly albuterol and levalbuterol. I make sure to note the dosing differences between the MDI with spacer versus the nebulizer. People conflate those two. The onset time is roughly the same, but the actual delivered dose varies considerably depending on technique and equipment.
The second section handles controller medications. Inhaled corticosteroids come first. Beclomethasone, budesonide, fluticasone. Then the combination ICS-LABA products like fluticasone-salmeterol and budesonide-formoterol. Formoterol deserves special attention because it has a faster onset than salmeterol, which means it can serve dual purpose as both maintenance and reliever therapy in certain regimens. This is the MART approach, and it's become standard in many protocols. I remember presenting this exact topic at a residency conference. An attending physician asked me point-blank about the optimal ICS dose for a teenager with moderate persistent asthma. The slide deck had a generic range. I had to admit that the evidence for pediatric dosing in this age group was thinner than I'd expected. The workaround was pulling the specific EPR-4 recommendations and showing a side-by-side comparison with adult dosing. That single slide turned into the most saved image from the entire presentation. Long-acting muscarinic antagonists belong in section three. Tiotropium bromide is the only LAMA approved for asthma add-on therapy in the United States. It's worth noting that while the evidence supports its use, particularly in adults who remain uncontrolled on ICS-LABA, it's a third-tier addition. It's not first-line for anyone. Several studies show modest improvement in FEV1 and exacerbation rates, but the effect size is smaller than switching to a higher ICS dose would typically provide.
Get the Full Details

Biologics get their own section now, and they should. Omalizumab for allergic asthma, mepolizumab and reslizumab for eosinophilic asthma, dupilumab for Type 2 inflammation, and tezepelumab as the most recent addition targeting both IL-5 and IL-13 pathways. These are expensive treatments. Any competent PPT on this topic needs a slide addressing patient selection criteria, not just mechanism of action. Prescribers need to know which biomarkers matter. Eosinophil count, IgE level, FeNO. Without those markers, the biologic discussion becomes theoretical rather than practical. The oral corticosteroid section is short because it should be. Prednisone and methylprednisolone for acute exacerbations. I emphasize the typical burst dosing protocol. Four to six milligrams per kilogram per day of prednisone, capped at 60 milligrams daily, for three to five days. Repeated courses are a problem. I've seen patients on quarterly oral steroid bursts who never got their controller therapy optimized. The slide deck should highlight this as a failure signal, not just list the drug. Montelukast deserves a warning slide. The FDA added a boxed warning in 2020 for neuropsychiatric events. Sleep disturbances, agitation, suicidal ideation. It's still prescribed routinely, but the risk profile changed significantly. Including this in a pharmacological treatment presentation isn't optional anymore. It's medically negligent to omit it.
Theophylline gets mentioned because it exists, not because it's commonly used. Narrow therapeutic index. Drug interactions. Monitoring requirements. Most general practitioners haven't dose-adjusted theophylline in years. If your audience includes primary care residents, a brief mention with a reference to checking levels is sufficient. If the audience is pulmonology fellows, expand it. One thing I've learned the hard way is that slide decks on asthma pharmacology tend to become medication catalogs rather than clinical guides. The fix is to anchor each drug class to a clinical scenario. Instead of listing every ICS available, show a case of a 42-year-old male with step three asthma and explain why you chose budesonide-formoterol over fluticasone-salmeterol. The reasons might include formoterol's faster onset allowing MAR T use, or cost considerations, or patient preference for a once-daily regimen. Context turns a list into a decision framework. The acute exacerbation section needs its own slides separate from chronic management. I've seen PPTs merge the two, and it creates confusion. Starting doses, escalation thresholds, when to add ipratropium bromide to albuterol in the ER setting, and disposition criteria. The distinction between home management and hospital admission is where these presentations typically fall apart for students. They can name the drugs but can't sequence them appropriately for an acute scenario.
If you're looking for existing resources, the GINA website offers freely available slide sets that get updated annually. The NHLBI EPR-4 document has the most current dosing tables. Pharmacology textbooks like Goodman & Gilman will have detailed mechanisms but less practical application. The Cochrane reviews on specific interventions are useful for supporting individual slides with evidence grades. The biggest mistake I see in these presentations is the lack of visual algorithms. A text-heavy slide on ICS-LABA combinations tells the audience nothing they can apply at the bedside. A flowchart showing the decision points from diagnosis through step escalation, with medication names at each branch, is what actually gets used after the lecture ends. I spend more time designing those decision trees than I do selecting the drug facts. Another overlooked element is the section on inhaler technique. No amount of pharmacological knowledge matters if the patient isn't delivering the medication correctly. A brief demonstration slide or embedded video showing proper MDI technique with a spacer, DPI technique emphasizing inspiratory flow, and nebulizer maintenance makes a noticeable difference in patient outcomes. It's also a liability issue. If a presentation on asthma treatment doesn't address delivery method, it's incomplete.

The cost and access slide is important in the US healthcare context. Insurance tiering for specialty biologics, prior authorization requirements, manufacturer assistance programs. These details affect whether a treatment plan is realistic. I include them because excluding them creates a disconnect between what the literature recommends and what patients can actually receive. For those building their own deck from scratch, I recommend structuring it around the treatment algorithm rather than by drug class. It mirrors how clinicians actually think through a case. Diagnosis, severity assessment, step selection, medication choice, reassessment. Each slide builds on the previous one in a logical clinical sequence rather than an encyclopedic category sequence. There's also the question of population-specific considerations. Pregnancy, pediatrics, elderly patients with comorbidities, patients with cardiovascular disease. These modify treatment choices significantly. A comprehensive presentation touches on at least the major modifiers. A minimal one doesn't, and that omission matters for anyone who will apply the information clinically.
Finally, the references slide should include the actual guideline documents, not just textbook citations. GINA 2024, EPR-4, ATS/ERS statements on biologic therapy. These carry more weight in academic and clinical settings than secondary sources. Anyone reviewing your work will check those first. Creating or evaluating a Tratamiento Farmacologico De Asma Ppt comes down to whether it reflects current guidelines accurately, presents information in a clinically usable format, and includes the safety and access information that determines whether a treatment plan works outside the classroom. Everything else is decoration.