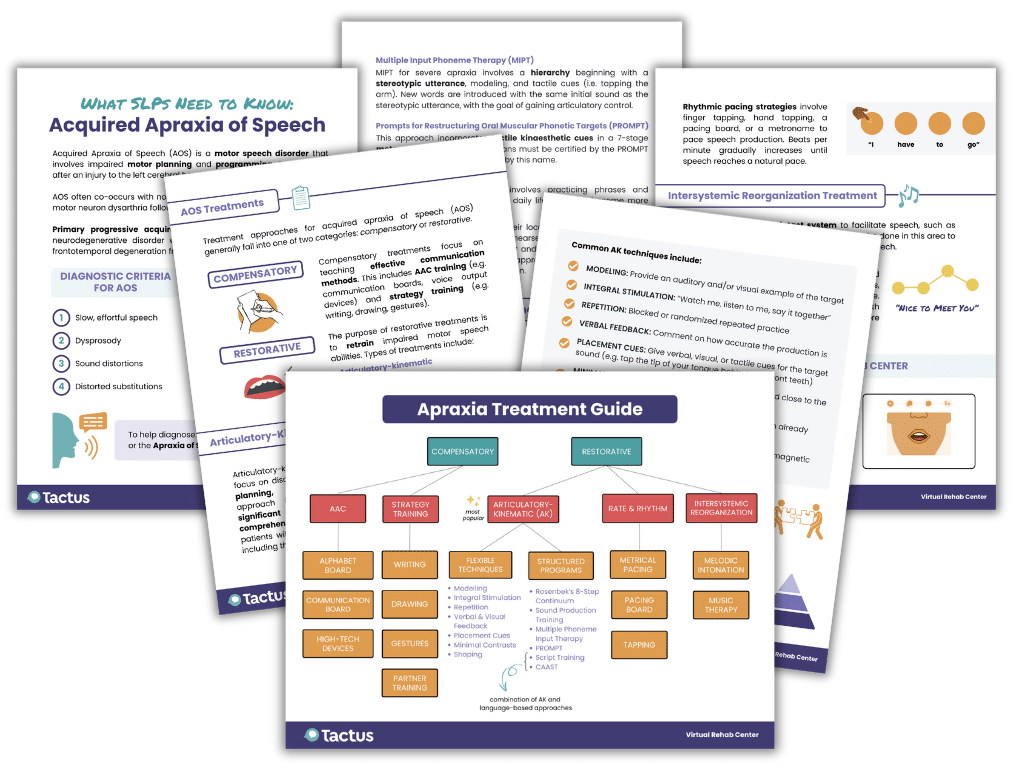
Apraxia of speech treatment isn't simple
I spent seven years running pediatric speech clinics before I started realizing that most of what we were doing wasn't actually moving the needle. The kids who improved fastest weren't the ones doing endless repetition drills. They were the ones whose nervous systems got different input — faster, weirder, more sensory than the standard cascade approach taught in grad school. Apraxia of speech is a motor planning disorder. That's the textbook definition. What it actually means in practice is that the brain can't reliably send the right commands to the speech muscles. The person knows what they want to say. Their mouth doesn't cooperate. It's not weakness. It's not laziness. It's a wiring problem between intention and execution.
The Treatment For Apraxia Of Speech question everyone avoids
Most people asking about treatment are looking for a shortcut. There isn't one. What works is consistent, high-intensity practice with immediate feedback. Three sessions a week minimum. Ideally four or five. Home practice alone gets you maybe a third of that progress because the therapist's real-time correction is the whole point. I learned this the hard way with a nine-year-old boy named Marcus. He'd been doing traditional oral-motor exercises for two years with zero improvement. His mother was convinced he was trying too little at home. Turns out the exercises were the problem. Oral-motor work doesn't transfer to speech production. The muscles are fine. It's the planning sequence that's broken. We switched to a cueing hierarchy approach — visual, then tactile, then auditory — and within six weeks he was producing three-syllable words without prompt cascades. Not all words. But enough to show the pathway existed.
What actually works in practice
Multiple examples therapy comes up first in the research. You drill the same word or phrase across different contexts until the motor plan stabilizes. "I want juice" becomes "I want juice" said to mom, then to dad, then while walking, then while holding the cup. The variation matters because apraxia isn't just about saying the sounds right once. It's about automating the sequence under different conditions. Prompts are your main tool. Visual cues — hand gestures, pictures, written words — reduce the cognitive load so the child can focus on the motor plan. Tactile cues — tapping the cheek, tracing syllables on the table — give proprioceptive feedback that helps the brain map where articulators should go. Auditory model first, then try it yourself, then get immediate correction. That's the basic loop. I had a kid, twelve years old, who couldn't say "strawberry" at all. Every attempt came out as "butterfly." We used tactile cueing — I tapped his cheek on the first syllable, his chin on the second, his throat on the third. Three distinct touch points mapped to three distinct muscle groups. After forty-five minutes he said it correctly. Once. Then we did it again. And again. By the end of the hour he had it. Two weeks later he used it in conversation without thinking. The tactile route bypassed the faulty planning pathway entirely.
Get the Full Details

Why most treatments fail
Frequency beats intensity. A twenty-minute session once a week is useless. An hour four times a week changes everything. The motor system needs repetition at a rate that matches how fast neural pathways strengthen. That's roughly three hundred trials per target word to see real consolidation. At one session a week with eight targets, you're doing maybe sixty trials per word per month. You'll be there six months before anything sticks. Another common failure point is focusing on single words in isolation. Apraxia isn't a sound error problem. It's a sequencing problem. "Cat" might come out wrong because the transition from /k/ to /æ/ to /t/ is unstable. Drill the word alone all day and you're not addressing the transition. Drill it in phrases. Drill it in sentences. Drill it until the motor plan for the whole sequence is solid. I burned through two years of a client's progress because I was obsessed with perfecting individual phonemes. She could say /s/ in isolation but couldn't hold it through "six silly sheep." We were treating the symptom, not the disorder. Once I shifted to phrase-level practice with stress and intonation patterns, her accuracy jumped from thirty percent to seventy in three weeks. The /s/ wasn't the problem. The motor plan for sustained articulation was.
Technology and augmentation
Speech-generating devices aren't giving up. They're buying time. A child using an AAC device while doing speech therapy isn't taking the easy way out. They're reducing cognitive load so the brain can focus on building motor plans without the frustration of constant failure. I've seen kids progress faster with devices than without because the anxiety barrier drops and practice volume increases. Apps help with home practice but they can't replace the therapist's feedback. Some programs track accuracy and give games. That's good for engagement. That's not the same as real-time tactile or visual cueing from someone who knows when a transition is breaking down. Use apps as supplement. Not as replacement.
The hard truths about timeline and outcome
Apraxia treatment is measured in months, not weeks. Real progress — the kind where new words carry over into spontaneous speech — usually shows up after three to six months of consistent therapy. Some kids improve significantly. Some plateau. A small percentage see continued gains into adolescence with ongoing work. Your goals need to match reality. The target isn't perfect speech. The target is functional communication. If your child can say "I want water" clearly even if "spaghetti" comes out garbled, that's a win. Work on the high-frequency words first. "More," "want," "help," "stop" — those matter more than "extraordinary" in daily life. I had a parent who brought her eight-year-old in after two years of no progress. The previous therapist was working on phonological awareness and rhyme recognition. The kid couldn't say his name consistently. We ignored everything else and focused on motor planning for high-frequency words. Eight months later he was reading aloud in class. Not fluently. But readable. That's the trajectory. Slow, uneven, but real if you stay on it.

When to reconsider your approach
If you're three months into therapy and seeing zero carryover to home environments, something is wrong. Either the intensity is insufficient, the cues aren't the right modality for that child, or the diagnosis needs reevaluation. Apraxia sometimes co-occurs with other disorders. Dysarthria, phonological disorder, language impairment. Mixed cases need mixed approaches. My rule of thumb: if a child can imitate a word when I model it slowly with tactile cues but can't produce it independently, the motor plan is forming but not consolidating. That's normal at that stage. If they can't imitate at all, we're back to square one and probably need to check hearing, oral structure, and rule out auditory processing issues before pushing harder on motor work. Treatment For Apraxia Of Speech works when it's consistent, intensive, and targeted at sequencing rather than isolated sounds. It doesn't work when it's weekly, passive, or focused on the wrong level of speech production. The difference between those two approaches is the difference between progress and waiting.