Setting Up Treatment Goals In Family Therapy
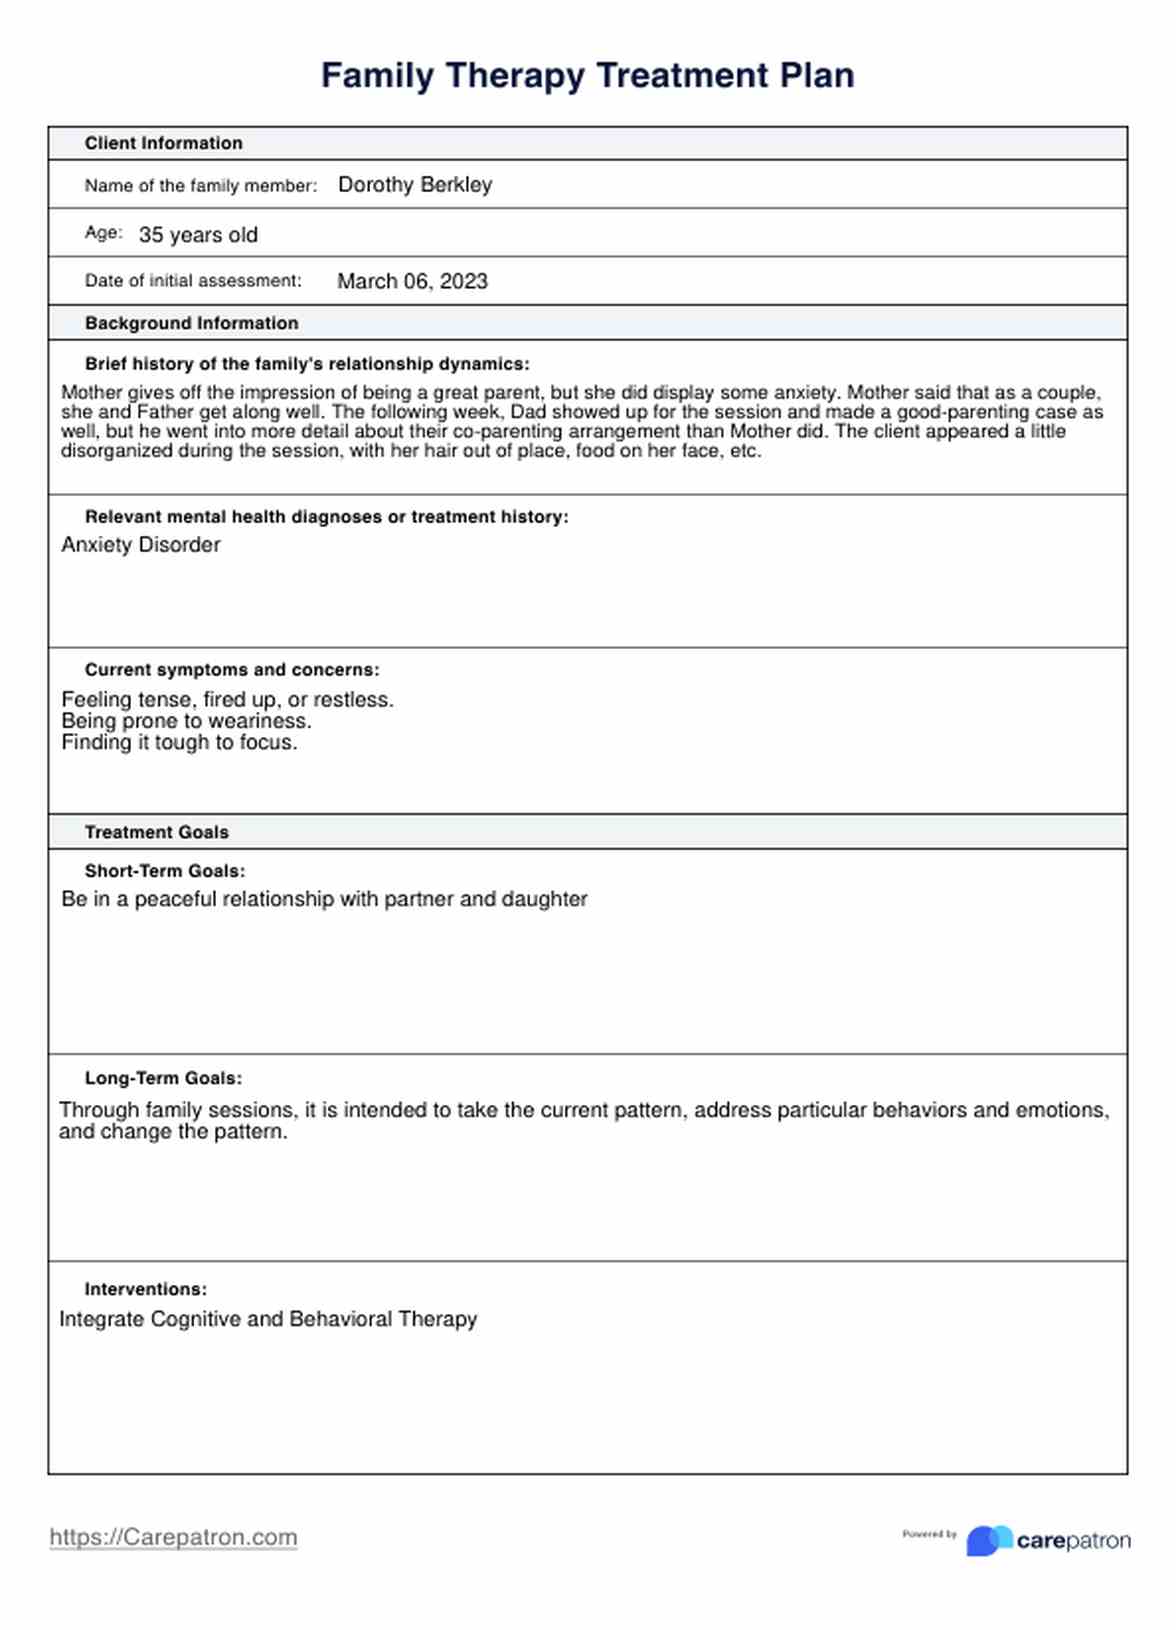
Most people assume family therapy is just talking until things get better. They're wrong. Without concrete treatment goals, sessions drift into complaining circles that nobody leaves feeling productive. I've sat through enough of those to know where they fail. Treatment Goals For Family Therapy function as the actual scaffolding for every session. They turn a vague "we need to communicate better" into measurable, trackable targets that both the therapist and the family can hold onto. Without them, you're just facilitating arguments with more structure.
Why Most Families Skip Treatment Goals And Regret It Later
Families walk in exhausted. The therapist walks in prepared. Usually, the therapist starts asking questions and the family answers them honestly. Two sessions in, everyone's tired of revisiting the same ground. This happens because no one wrote down what improvement actually looks like. I once worked with a family where the mother wanted "better respect," the father wanted "less backtalk," and the teenage son wanted "nobody nagging me for three seconds." These aren't conflicting goals. They're completely mismatched frames of reference. We spent four sessions trying to talk around each other before someone finally said: let's write these down separately and then find the overlap. The overlap was smaller than anyone wanted. It was also the only useful place to start.
How To Actually Build Treatment Goals
Start by pulling each member's individual want into the open. Don't synthesize yet. Write them verbatim on a board or a shared document. What you'll notice immediately is that families rarely describe problems in the same language. Next, convert each wish into behavioral terms. "Better communication" becomes "We will each state our frustration without raising our voice above a conversational volume." "More respect" becomes "When someone is speaking, the other person will wait until they finish before responding." These sound almost silly when written out. That's the point. Then find the intersection. Every goal needs to be something the whole family can agree moves toward, not just one member's victory dressed up as mutual benefit. If the mother's goal requires the father to change but doesn't include any observable behavior from him, it's not a family treatment goal. It's a demand.
Get the Full Details

I use a simple ranking system here. Each family member rates every proposed goal from one to five on how important it feels to them personally. Goals that score below a three from at least two members get dropped or revised. You'd be surprised how many "mutual" goals survive that filter. Usually about half don't. After that, attach a timeline and a measurement. "We will have zero raised-voice interruptions during dinner conversations for fourteen consecutive days." Not "we'll try harder." Days. Countable events. Specific settings. This is what turns a goal into something you can actually track week over week.
The Edge Case Nobody Warns You About
Abusive dynamics break the standard goal-setting model. I worked with a family where the stated goal was "improved conflict resolution." Halfway through the second session it became obvious that the "conflict" was unilateral intimidation from one parent. Standard collaborative goal-setting would have implicitly validated that person's framing as equally responsible. The workaround was straightforward but uncomfortable. I separated the safety assessment from the goal-writing exercise entirely. Safety came first, documented and non-negotiable. Only after that was established did we return to joint goals. The family initially pushed back hard on the separation. They called it unfair. It was. Fairness wasn't the priority here.
Common Pitfalls That Derail Progress
The biggest mistake is making goals too broad. "Improve relationships" gives you nothing to measure. "Reduce hostile exchanges during sibling conflicts from an average of six per evening to two or fewer within thirty days" gives you a metric. Use metrics. Another pitfall is letting the therapist define the goals alone. Families resist externally imposed targets far more than they admit. Even well-intentioned clinical language reads as authoritative and triggers the same resistance you'd see from any mandated change. Let them draft first. Refine after. A third one I see constantly: goals that target individuals instead of interactions. "Teenager will stop lying" is not a family therapy goal. It's individual behavior modification wrapped in family language. Family therapy goals describe patterns between people, not fixes applied to one person. "When information is shared in this house, all members will receive it without initial suspicion or accusation" is what you want.

What These Goals Look Like In Practice
Session one through two are almost always goal-setting and refinement. Expect that. If a family expects breakthroughs by week three with no written goals in place, they're setting themselves up for disappointment. I tell them upfront: the first two sessions are administrative. It feels slow. It is. By session three, you should have three to five written goals posted somewhere visible in the room or shared digitally. Each one has a baseline measurement, a target measurement, a timeline, and a defined setting. You revisit them every session. Not as inspiration. As data. Progress check-ins happen at the end of each session, not the beginning. Families report what happened during the week against each goal. You record the numbers. You adjust the next week's focus based on which goals are stalling and which are moving. The goals themselves rarely change once set. What changes is the intensity and the specific behaviors targeted within each goal.
When Goal-Setting Doesn't Work
Some families cannot participate in structured goal-setting due to acute crisis, substance abuse active in the home, or severe cognitive impairment in a member. In those cases, the therapy shifts to crisis stabilization first. Goals return once the immediate destabilizing factors are addressed. Pushing structured treatment goals into an active crisis usually produces compliance without engagement, which is worse than no goals at all because it creates the illusion of progress. Couples therapy often follows a different trajectory than whole-family therapy. Two people can reach agreement faster than five or eight. Don't force the whole-family model onto a couple's session. The goal-setting pace should match the number of stakeholders and their capacity for reflection. The work is tedious. It requires repeated cycles of drafting, rating, revising, measuring, and adjusting. Families who stick with it report higher satisfaction at the end. Families who skip it tend to terminate early and cite "nothing changed." Both outcomes are predictable if you understand what the goal-setting process actually does and what it doesn't do.
It doesn't fix dysfunction. It makes dysfunction visible enough to intervene on. That distinction matters more than most therapists admit.