
What actually happens when you build a treatment plan for depression and anxiety
A treatment plan for depression and anxiety is just a structured document that tracks what medication, therapy type, dosage, and lifestyle interventions are being used, when they're started or adjusted, and what the measurable targets are. Most people think it's something only psychiatrists write, but therapists, primary care doctors, and increasingly patients themselves draft these. The reason they exist is because both conditions tend to be chronic, relapsing, and highly individualized. Without a written plan, treatment decisions become reactive rather than coordinated. The essentials are straightforward. Diagnosis code from the DSM-5 or ICD-11. Current symptoms with severity ratings on standardized scales like the PHQ-9 for depression and GAD-7 for anxiety. Medication list with doses and start dates. Therapy modality — CBT, ACT, DBT, EMDR, or a combination. Frequency of sessions and expected duration. Lifestyle factors being addressed, which means sleep schedule, exercise, substance use, and social support. Baseline labs if blood work is relevant. Specific, measurable goals with timelines. A crisis or safety plan. What the plan does not need is every single detail of your life story. It needs enough to guide decisions without turning into a novel that gets lost in the electronic record. I built dozens of these over the years, mostly for patients who had been bouncing between three or four providers who never communicated with each other. The most common failure point is not the diagnosis. It's the goal setting. People write vague goals like "reduce anxiety" or "feel better." Those are not measurable. They should read like "PHQ-9 score below 5 within 8 weeks" or "panic attacks reduced from daily to fewer than twice per week within 4 weeks." Without numbers, you cannot tell if the treatment is working or if you need to pivot.
How to actually write one
Start with the assessment. Pull your most recent PHQ-9 and GAD-7 scores. If you do not have them, grab one now from the standard free versions online and take it honestly. These numbers are your baseline. Then list every medication and supplement you are currently taking, including the dose and how long you've been on it. Write down the therapy type and who provides it, how often you go, and what the therapist's stated approach is. Record any recent changes — a med adjustment, a new provider, a gap in treatment. Next, define the measurable targets. Each target needs a number, a timeframe, and a method of measurement. "Reduce insomnia" is useless. "Fall asleep within 30 minutes of going to bed, measured by sleep diary, within 2 weeks" is something you can track. Same with anxiety. "Decrease GAD-7 from 14 to under 8 in 6 weeks" is a real goal. Put the lifestyle components in here too, because they are often the difference between a plan that works and one that stalls. Then map the interventions to the goals. SSRI for moderate to severe depression, usually with a 4 to 6 week window to see the initial response. SNRI if SSRIs fail or if pain is a comorbid feature. Benzodiazepines only as a short-term bridge, not a long-term solution. CBT is first line for both depression and anxiety. ACT has shown comparable results for some patients and is worth considering if CBT feels like it is always fighting against you. Buspirone for generalized anxiety can help but takes 2 to 3 weeks to kick in. If you have comorbid ADHD, treating that often reduces the anxiety significantly. None of this is rocket science, but people skip the part where they match the intervention to the specific symptom profile.
One thing nobody tells you is that the timing of assessment matters. Checking your PHQ-9 right after a bad week will skew everything. Take it at a relatively stable point, or note the context so the provider knows what they are looking at. I had a patient once whose PHQ-9 read as severely depressed after a work crisis, but their baseline during normal weeks was barely mild. We reset the treatment plan with that context and avoided a medication change that would have been unnecessary.
Get the Full Details

Common pitfalls and what actually goes wrong
The biggest problem I see is that people treat the plan like it is static. It is not. You should revisit it every 4 to 6 weeks during the active treatment phase, or sooner if something changes. A second major issue is polypharmacy creep. Starting one med, not seeing results in 4 weeks, adding another med on top instead of adjusting the first. That happens constantly. The guideline-backed approach is to optimize the current agent before adding a second one, unless there is a clear rationale for combination therapy. Aripiprazole augmentation is one evidence-based option when SSRIs partially work. Vortioxetine or levomilnacipran are alternatives for SSRI non-response. These are specific, not random. Another pitfall is ignoring the anxiety side when treating depression. People will focus on the low mood and forget that the GAD-7 score is still at 15. The two conditions do not always improve together. An antidepressant might lift the depression while leaving the anxiety untouched, or in some cases making it worse initially. You need separate tracking for each condition in the plan. Lifestyle interventions are where most plans fall apart, not because they are wrong, but because people do not implement them. Exercise has a real effect size comparable to medication for mild to moderate depression in multiple meta-analyses. Sleep hygiene is not a fluffy suggestion, it is a clinical intervention. But writing "exercise 3 times per week" on a plan means nothing if you do not have a specific schedule attached. Write the day, the time, and the activity. Same for sleep. Set a target bedtime and wake time, not "sleep better."
When a treatment plan does not work
Let me be blunt about this. Treatment plans for depression and anxiety fail at a significant rate. Roughly a third of patients do not achieve remission with the first medication tried. That is called treatment-resistant depression, and the label gets thrown around loosely, but the technical definition is failing two adequate trials of different classes of antidepressants. When that happens, the options shift. MAOIs like phenelzine or tranylcypromine are older drugs that many clinicians avoid unnecessarily. They are effective for atypical depression and resistant cases but require dietary restrictions. TMS is a non-invasive option with good evidence for depression, though it does not address anxiety as directly. Ketamine and esketamine work faster than traditional options, which matters when someone is in acute distress. ECT remains the most effective treatment for severe, life-threatening depression, despite the stigma around it. For anxiety specifically, benzodiazepine dependence is a real problem that develops faster than most people expect. Even short courses of clonazepam or lorazepam can lead to tolerance within weeks in some individuals. Beta-blockers like propranolol can help with performance anxiety without the dependency risk. Pregabalin is used off-label for GAD in many countries and has a different mechanism than SSRIs. These are not headline options, but they are part of the real toolkit. The limitation I want to stress is that no treatment plan accounts for the full range of human variation. Genetics, life circumstances, socioeconomic stress, trauma history, and medical comorbidities all interact in ways that a paper document cannot fully capture. A treatment plan is a tool, not a guarantee. It works best when it is alive, updated, and discussed openly with your provider rather than treated as a one-time formality.
If you want a format to work from, the structure is simple. Diagnosis. Baseline scores. Current interventions with dates. Measurable goals with timelines. Next steps and review date. Crisis contacts. That is it. It does not need to be complicated. It needs to be accurate and current.

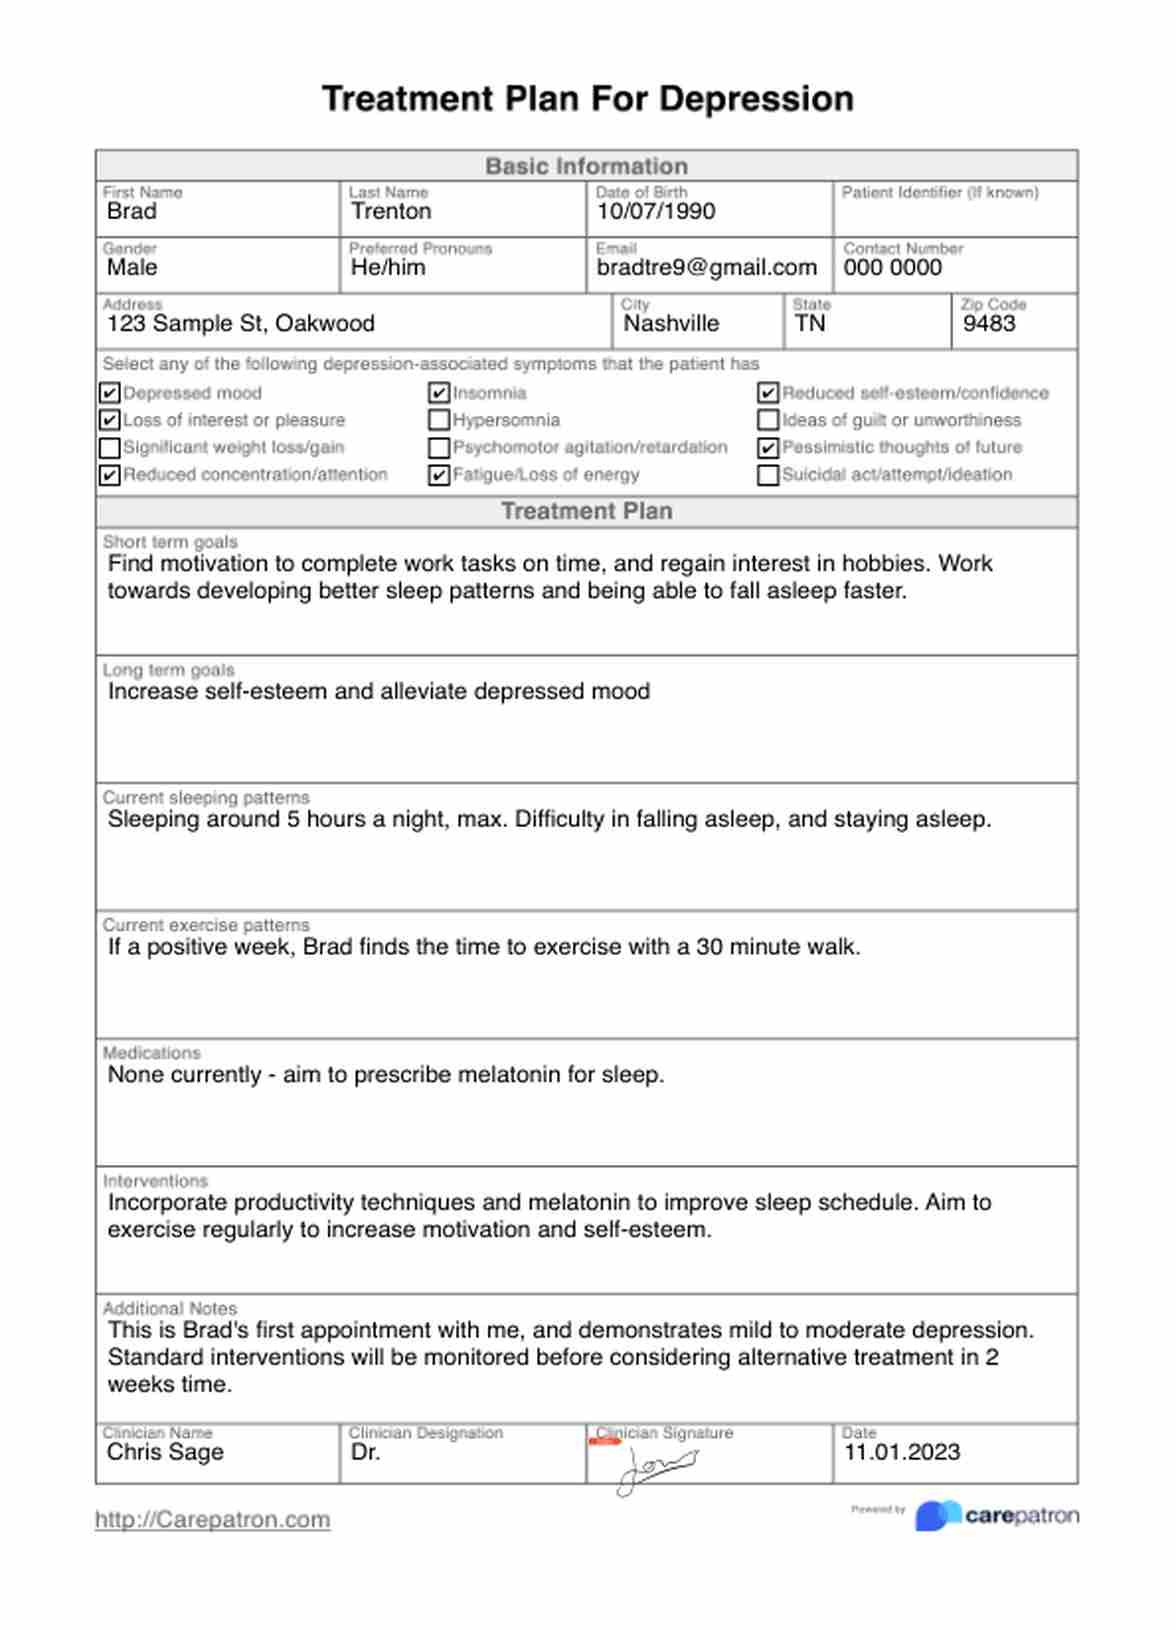
.png "Treatment Plan For Depression Template & Example | Free PDF Download")
