What actually happens when you sit down to plan a case
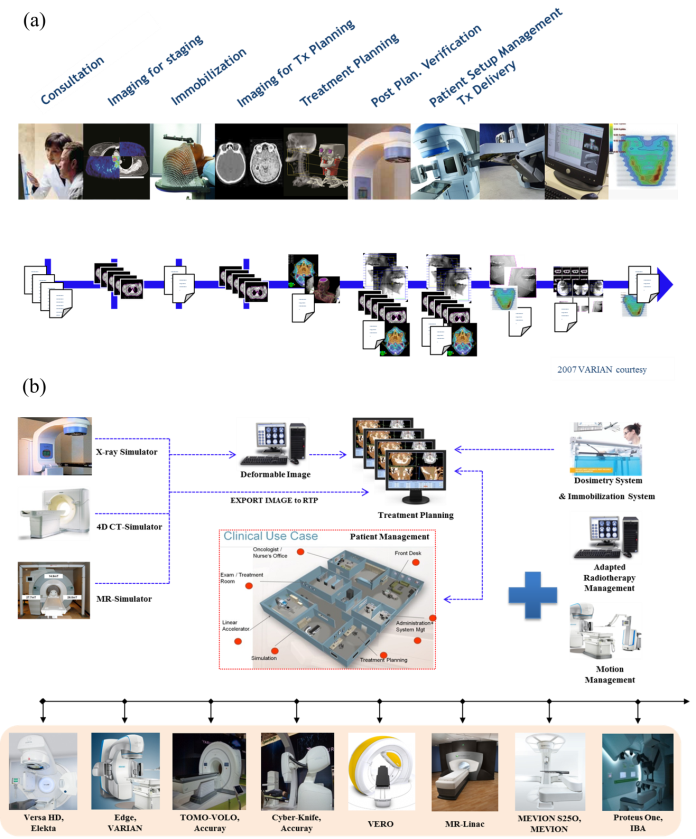
You open the TPS, load the CT, and realize the patient moved 4 millimeters between the scout and the scan. Again. That is where this whole process starts, not with some grand overview. It starts with deciding whether you are going to bother regenerating the contours or just work with what you have and flag it for the radiation oncologist. Treatment Planning In Radiation Oncology is less a single step and more a continuous negotiation between physics, anatomy, and the person who actually has to deliver the beams every day for three weeks. The dose calculation engine does its job fine. The part that eats your Tuesday is making sure the beam angles you picked make sense in the clinic, not just on the simulator.
Treatment Planning In Radiation Oncology
The workflow most people skip doing right
Contouring is where beginners burn the most time because they think a contour has to be perfect before they touch the planning beams. It does not. You need the major organs at risk roughly right so the optimizer does not hallucinate impossible dose distributions, but spending twenty minutes chasing the exact margin on a minor lymph node station while your MLC leaf speed settings are wrong is backwards priorities. Start with beam arrangement. Pick your angles before you lock in a VMAT arc or finalize a fixed-field setup. The reason is that the optimization landscape changes completely once you commit to 360 degrees of arc versus 5 static fields, and you will end up redoing work either way. I have seen planners spend forty minutes tuning objectives on an IMRT plan, only to realize the inverse square fall-off on a posterior field would have hit the cord harder than anything the optimizer could smooth out. Flip the beam orientation early and save yourself the heartburn.
Setting up the optimization problem
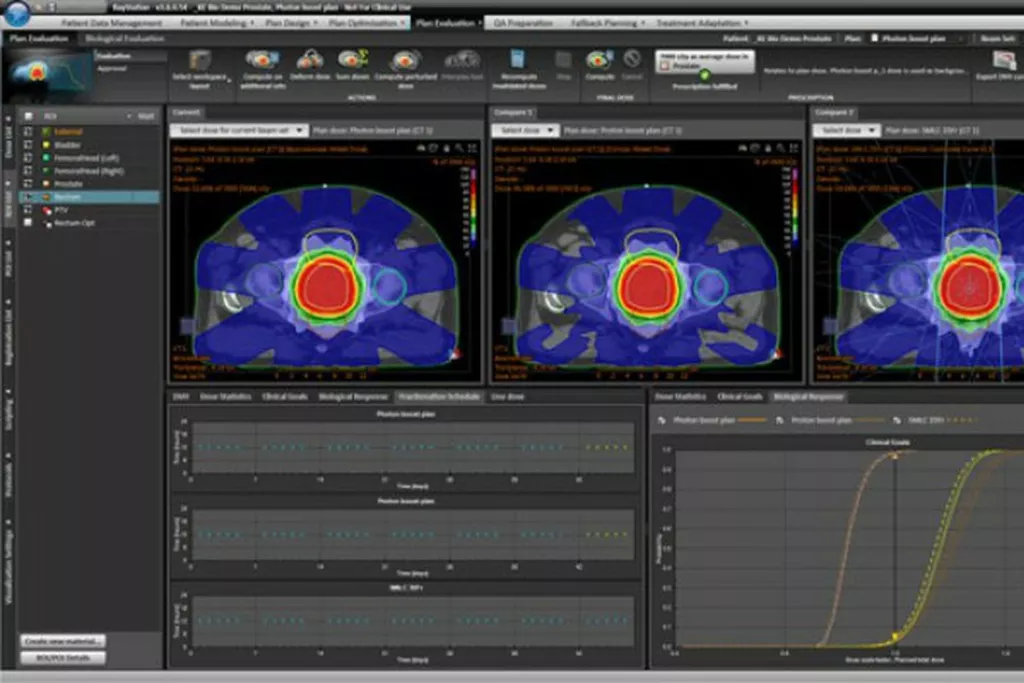
The optimizer is not a black box that produces a good plan by magic. It is a math solver that will absolutely maximize your target coverage if you let it, even if that means blasting the small bowel to 70 gray. You have to constrain it properly, and proper constraints mean understanding what the software is actually minimizing. For VMAT plans, DvN values matter more than people give them credit for. The difference between a plan that looks clean on the isodose lines and one that actually respects the OARs often comes down to whether you set your rectum constraint to D30% or Dmax, and whether that matches what the physician cares about clinically. Dmax for the spinal cord is non-negotiable, but for the rectum the volume-based metric usually tells a truer story about late toxicity. I learned that the hard way during a pelvis case where the physician rejected my plan because the rectal bleeding risk looked acceptable on paper but the dose histogram told a different story.
Get the Full Details
A specific edge case I dealt with recently
I had a head and neck patient with a metallic dental implant that caused streak artifact across the entire CT. The auto-segmentation tool labeled half the pharyngeal constrictors as bone because the HU values were corrupted. Instead of manually redrawing everything, which would have taken about ninety minutes, I switched to a fused PET/CT from the same simulation session, used the PET uptake to verify the GTV, and manually corrected only the constrictor contoured on the corrupted slice. Then I ran a separate dose calculation on a degraded CT generated by the TPS artifact reduction feature. The difference between the two calculations was approximately 3 percent in the target region, which is well within acceptable uncertainty for this site. I flagged the artifact in the chart and moved on. Monte Carlo calculations are not a silver bullet for heterogeneity corrections, despite what the marketing materials say. For lung cases they help, yes. For a parotid spare in a head and neck plan, switching from collapsed cone to Monte Carlo will change your results by less than 1 percent and add twenty minutes of computation time to a process that already takes too long. The bigger gain comes from using the correct electron density calibration curve for the specific CT scanner you are working on. A misregistered HU-to-density table can throw off your entire plan more than any algorithm choice ever will. Another thing nobody warns you about: the monitor unit check. Automatic MLC leaf sequencing can produce beam-on times that look reasonable but are actually physically impossible on your specific linac model due to tongue-and-groove effects or maximum leaf speed limits. Always run a manual MU verification for the high-dose regions, especially if you are treating a large field with many MLC segments. I caught one plan where the optimizer had created a segment that required a leaf speed of 5.2 centimeters per second on a machine rated for 4.0, which meant the fluence map would never deliver what the dose calculation predicted. The patient would have been significantly underdosed.
Quality assurance and delivery considerations
A plan that cannot be delivered is worthless. I have lost count of the number of times a plan looked brilliant on paper and then failed pretreatment QA because the gamma passing rate dropped below 90 percent with 3 percent/2mm criteria. The usual culprits are tight MLC leaves on steep dose gradients and high modulation complexity indices that your delivery machine cannot accurately reproduce. Keep your modulation complexity score below 1.5 when possible. Plans above that threshold tend to have QA failures that are difficult to fix without compromising the dosimetry. If you are struggling, reducing the number of control points or increasing the leaf bank separation slightly often resolves the issue without any meaningful clinical impact on the dose distribution. This is a practical tradeoff that most textbooks do not mention because they assume an ideal delivery system.
When to stop planning and send it for review
The plan is done when the dose objectives are met within the clinically acceptable range, the QA metrics pass, and the physicist has verified the MU and delivery parameters. It is not done when the isodose lines look pretty. I once spent an extra hour trying to reduce the PTV margin on a prostate case from 5 mm to 3 mm. The physician wanted it, the plan technically met the new criteria, and the dosimetry was fine. The physics reviewer rejected it because the setup uncertainty data from our daily image guidance program showed median shifts exceeding 3 mm in two out of five directions. The extra hour was wasted. Document your setup uncertainties and use them to justify your margins before you chase marginal improvements. The AAPM task group reports are not optional reading. TG-166 for VMAT QA, TG-150 for MLC QA, and TG-53 for overall system acceptance testing give you the framework that most commercial TPS documentation glosses over. The ASTRO guidelines for site-specific planning also provide objective and constraint recommendations that save you from negotiating with physicians every time you start a new case type. For automated contouring, deep learning tools have improved dramatically, but they still require manual review. A study from Johns Hopkins showed that auto-segmentation alone missed clinically significant organ boundaries in approximately 12 percent of head and neck cases when compared to expert consensus contours. That 12 percent is not abstract. It is the difference between a plan you sign off on and one that causes a complication you did not anticipate.
What this process still cannot handle well
Deformable registration between planning CT and repeat CT is useful but not reliable enough to use as a standalone tool for adaptive replanning. The deformation algorithms can produce anatomically impossible displacements in areas with large air-tissue interfaces or post-surgical changes. I had a breast case where the deformable registration suggested a 15 mm shift in the internal mammary nodes between fractions, which was clearly incorrect given the immobilization setup. Manually contouring the repeat CT took longer, but it was the only way to be confident the dose was accurate. Until the algorithms improve, treat deformable registration results as a suggestion, not a source of truth. Similarly, online adaptive planning with MRI-guided systems is powerful but introduces its own failure modes. The software can lock onto a moving structure like the bowel and treat around it instead of with it, creating geographic miss that is invisible on the planning CT but would have been caught during manual review. These systems require explicit safeguards and experienced operators. They are not plug-and-play solutions for sites with significant intrafraction motion.