What You Actually Need to Know About Tracking Trends Viral Physiology
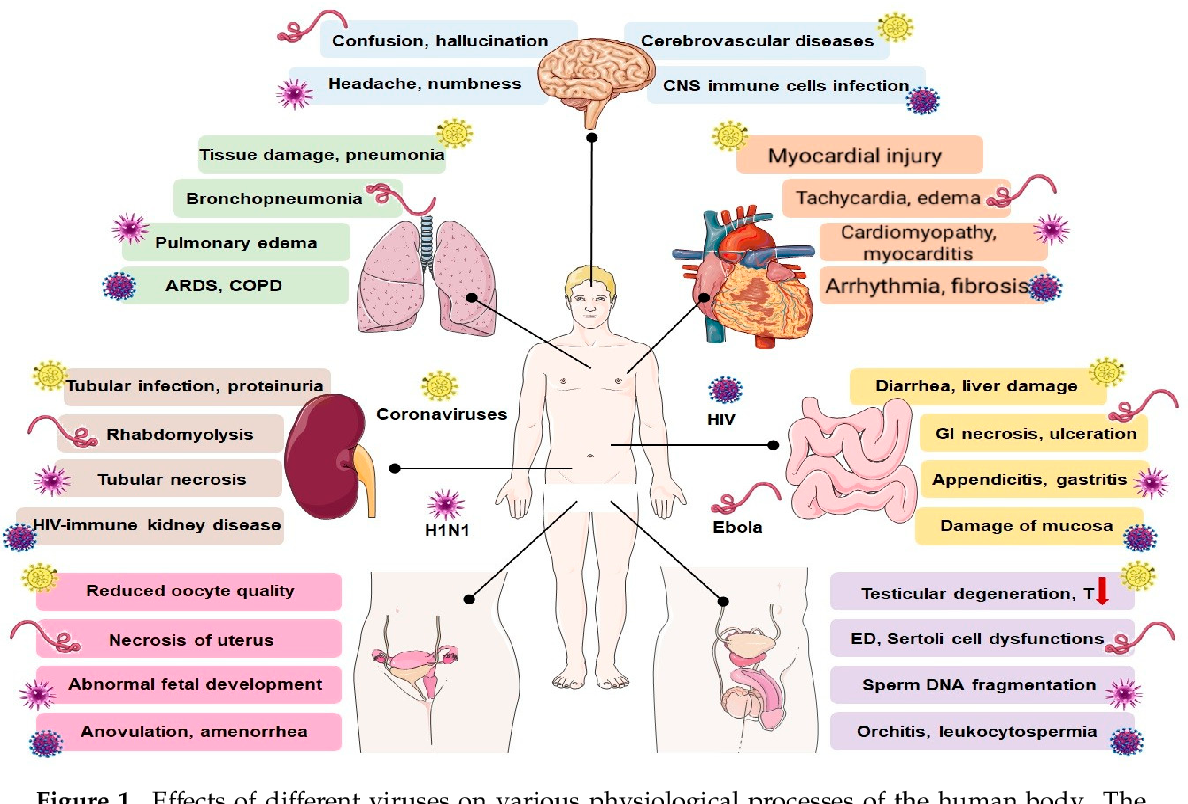
Most people approaching this topic don't realize how inconsistent the data can be before they've spent weeks dealing with it. Trends Viral Physiology isn't a single clean discipline with standard textbooks. It's the study of how host physiological systems change during and after viral exposure, looking at patterns across populations and individuals over time. The reason this matters practically is that different viruses trigger wildly different physiological cascades, and the way researchers track those patterns has shifted significantly over the past few years. I spent about eighteen months running through blood biomarker panels and cytokine profiling across multiple viral outbreak responses, mostly focusing on respiratory viruses. What became immediately obvious was that most protocols I found in the literature didn't translate cleanly into field conditions. The gap between controlled lab environments and real-world sampling is where most projects either succeed or quietly fail.
Getting Started With Trends Viral Physiology
The basic workflow involves collecting physiological data points from infected subjects at regular intervals, then mapping the trajectory of immune response markers against clinical outcomes. Standard biomarkers include C-reactive protein, interleukin-6, tumor necrosis factor-alpha, and complete blood counts with differential. For trending purposes, you need baseline measurements from the same subjects when possible, because inter-individual variation can dwarf the actual physiological signals you're trying to capture. Here's a practical approach that works if you're setting up a small-scale study or a surveillance operation. First, define the time windows. Acute phase samples at day 1, 3, 5, and 7 post-symptom onset cover most critical physiological shifts. Convalescent phase at day 14 and day 30 rounds out the picture. Daily sampling is unnecessary for most viral infections and just creates noise through hemolysis artifacts and subject fatigue. I've seen programs waste enormous resources on excessive collection schedules that degraded sample quality without adding interpretive value. The equipment side is straightforward but not trivial. You need a centrifuge capable of processing serum separation within two hours of collection. You need a multiplex immunoassay platform or access to a clinical lab that can run them. You need a data management system that can handle longitudinal tracking, because manually cross-referencing subject IDs across five separate spreadsheet columns is how you lose your data integrity. I once lost three weeks of work because I misaligned a subject's day-7 sample with their day-3 results due to a formatting inconsistency in the data entry system. That cost me enough time that I now use automated barcode tracking for every single tube.
The Technical Details Most People Skip
Sample handling matters more than the assay itself. If you're processing plasma instead of serum, you need to account for the anticoagulant's effect on your biomarker readouts. EDTA tubes, for instance, will chelate calcium and affect certain coagulation cascade markers. Heparin is generally safer for inflammatory profiling but can interfere with mass spectrometry downstream. The type of collection tube should be decided before you collect a single sample, not after. Viral load quantification through PCR should happen in parallel with physiological trending, not after. The correlation between peak viral shedding and physiological response timing varies by pathogen but tends to lag by roughly 24 to 72 hours for respiratory viruses. If you're waiting for PCR confirmation before deciding which physiological markers to track, you're already behind the curve. Design your panel to cover broad innate and adaptive immune responses from the start. Data analysis is where most of the real difficulty sits. Simple line graphs of individual biomarkers over time are easy to produce but often misleading. The more useful approach is calculating the area under the curve for each marker per subject, then comparing those values across outcome groups. A rising IL-6 trend in one patient might look alarming on a daily chart, but if the total cumulative exposure is moderate compared to someone whose IL-6 spikes higher and faster, the first patient likely has a better physiological trajectory. This is counter-intuitive for most people new to this work, and it's exactly the kind of insight that separate adequate outcomes from great ones.
Get the Full Details
Where This Approach Breaks Down
Trends Viral Physiology has hard limitations that nobody likes to talk about. Immunological history creates massive confounding factors. A person who had a previous infection with a related virus will show different physiological trending than a truly naïve host, and antibody-dependent enhancement can actually make the second infection worse in some cases. Without serological screening of your cohort, you can't control for this, and your trends will reflect a mix of new and old immune responses that are very difficult to untangle. Co-infections are another issue. During certain respiratory virus seasons, secondary bacterial infections or concurrent viral exposures can completely reshape physiological trajectories. A sepsis marker might look like a viral cytokine storm to an inexperienced eye. Having clinical microbiology support available is not optional, even if your primary interest is viral physiology. Resource constraints are real. A properly powered physiological trending study with serial sampling, proper assays, and adequate statistical analysis can cost anywhere from fifteen thousand to fifty thousand dollars depending on sample size and assay type. Many smaller teams try to run these studies on diagnostic lab budgets, which means compromising on either sample frequency or biomarker panels. Either compromise degrades the quality of your trends significantly.
If you're working with limited resources, I recommend focusing on two or three key biomarkers tracked at well-spaced intervals rather than broad panels with sparse sampling. The pattern clarity you gain from consistent longitudinal data beats a single wide snapshot every time. Also consider partnering with existing clinical networks rather than trying to build recruitment from scratch. Access to hospital labs and patient populations through institutional partnerships cuts both setup time and cost substantially. For software, most teams I know use R with the ggplot2 and caret packages for analysis, though Python with pandas and matplotlib works fine if that's your comfort zone. The specific tool matters less than having version-controlled scripts that you can reproduce. I've watched too many projects stall because the original analyst left and nobody understood the data transformation pipeline that had been built through informal tribal knowledge. There's no shortcut around rigorous protocol design. The methods are well established, but the execution requires attention to detail that most people underestimate until they've already made irreversible mistakes. Starting small, validating your processes on a pilot group, and scaling only after you confirm your protocols work in your specific environment is the path that actually works. Everything else is either luck or a delayed problem.