Understanding and Applying Trigger Point Massage Therapy
Trigger points are hyperirritable spots within taut bands of skeletal muscle. Pressing them reproduces local pain and often refers pain to distant areas. This is the core mechanism behind Trigger Point Massage Therapy, and it is distinct from general relaxation massage. Most people confuse the two. They are not the same. The method relies on sustained ischemic compression. You locate a trigger point, apply direct pressure using a thumb, knuckle, or tool, and hold it for 8 to 12 seconds without rubbing. The pressure should reach a point just before the client's pain tolerance threshold — what we call a seven out of ten on a standard pain scale. If you push harder than that, the muscle guards and contracts defensively, which defeats the entire purpose. The referred pain sensation should begin to diminish while the pressure is held. When you release, you wait a couple seconds and then reassess. The spot often feels different. Less dense. Less reactive. I once had a client whose trigger points in the upper trapezius kept coming back within 48 hours no matter what I did. I spent the better part of two sessions pressing into that muscle with diminishing returns. What I eventually figured out was that the trigger points there were secondary. The primary driver was a set of suppressed nodes in the levator scapulae and scalenes, both of which were being chronically overloaded by forward head posture from eight hours of desk work daily. Treating only the trapezius was like mopping water off a floor that had an open faucet. I shifted the focus upstream, addressed the scalenes and levator, and the trapezius trigger points stopped cycling back. That experience changed how I approach every subsequent referral pattern case.
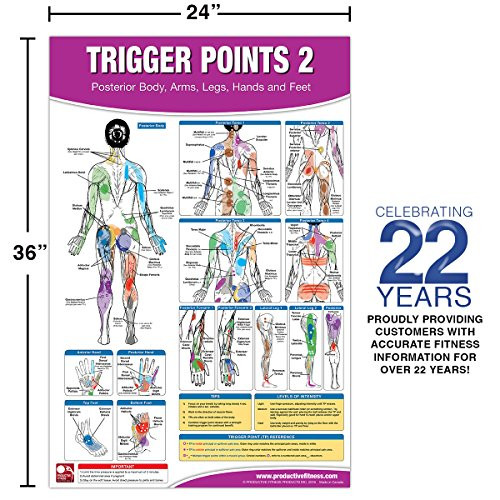
Here is a detail that surprises most beginners: the most common mistake is chasing the pain instead of mapping it. Referred pain from a trigger point in the serratus anterior can be felt along the inner arm all the way to the forearm. A client will point to their forearm and say that is where it hurts. The trigger point is not in the forearm. It is in the serratus. You have to understand referral patterns from actual published charts — not intuition. Gilbert Strattle and David Simons mapped these extensively. Without those references, you are guessing.
Technical Execution Details
The standard protocol involves three phases: identification, compression, and integration. For identification, you palpate the muscle in a lengthened position. Palpate along the muscle belly in perpendicular strokes. A trigger point feels like a taut nodule within the band. It may snap beneath your finger when pressed. That snapping is a localized myofascial twitch response, which confirms you are on the right structure. During the compression phase, hold steady. Do not bounce. Do not slide. Bouncing resets the neural adaptation every time and extends the total session by minutes without adding benefit. A single trigger point usually needs about 60 to 90 seconds of cumulative compressed time across all applications. Most of the time, you are done with a given point after two or three hold cycles. Integration means moving the muscle through its full range of motion after release. This helps the sarcomeres reset to a new resting length. Skipping this step is why some people leave treatment feeling fine and then snapping back into old postural habits within an hour, only for the trigger points to reload. Stretching the muscle through active motion seals the effect.
Get the Full Details
What This Method Does Not Fix
Trigger point therapy does not address structural problems. If a client has a scoliotic curve compressing one side of their thoracic spine, no amount of ischemic compression will resolve the asymmetry. You will treat the secondary trigger points, they will calm down temporarily, and then load returns and they flare again. You need to be honest about that boundary. Similarly, myofascial pain syndromes with central sensitization — where the nervous system itself has become hyperexcitable — will not respond reliably to localized pressure. In those cases, a multidisciplinary approach involving movement retraining, stress management, and sometimes pharmacological support is more appropriate. Acute inflammation is another hard stop. If a muscle is acutely strained with swelling, heat, and bruising, applying deep pressure is counterproductive. You need rest, ice, and medical evaluation first. Trigger point therapy is for chronic myofascial pain patterns, not acute injury management.
Practical Tools and Resources
You do not need expensive equipment to begin. A firm thumb is sufficient for most trunk and proximal limb points. For distal points and deeper tissues, a metal trigger point tool or a dense foam ball works better than fingers because fingers fatigue within 20 minutes. The Thera Cane and TriggerPoint Grid tools are standard industry items. They cost between $12 and $25. Nothing justifies spending more unless you are working full-time clinically. For reference material, the Persistent Painful Myofascial Trigger Points atlas by Simons, Travell, and Simons remains the definitive clinical reference. It covers over 170 trigger point patterns with referral diagrams. There are free digital versions of Strattle's referral pattern cards available online if you search for them. They are useful as quick desk references during sessions. Paid options like the TriggerPoint Reference app exist but replicate content already available for free.
Common Pitfalls to Avoid
One frequently overlooked issue is pressure direction. You should apply pressure perpendicular to the muscle fiber orientation, not parallel to it. Pressing along the grain tends to slip off the taut band and presses into surrounding tissue instead. The other is session duration. A full-body trigger point protocol for a new client with widespread myofascial involvement typically takes 45 to 60 minutes if done correctly. Anything shorter is usually incomplete. Anything longer than 90 minutes risks causing systemic fatigue and overstimulation, which can trigger a flare-up rather than relief. Another practical limitation: trigger point therapy is not effective for all types of chronic pain. Fibromyalgia, for instance, involves widespread tender points rather than true trigger points with referral patterns. Pressing into fibromyalgia tender points with the same intensity used for genuine trigger points will aggravate symptoms. Learning to distinguish between myofascial trigger points and generalized tenderness is a skill that develops over years of clinical practice, not from reading a single article.